

Bedside Snapshot
- Normal Result
- No growth in all sets at the final report. One negative set does not exclude bacteremia; the number of sets matters
- Significant Result
- Same organism in two or more separately drawn sets, or a recognized pathogen that matches a source. One bottle needs its time to positivity and source checked
- Positive Suggests
- Bacteremia from pneumonia, urinary, abdominal or skin source
- Endovascular infection if growth persists across sets
- Contamination when one set grows skin flora
- Negative Does Not Exclude
- Bacteremia when only one set was drawn, bottles were under-filled, or antibiotics were given before the draw
- Act Now If
- Possible septic shock, or probable or definite sepsis: antibiotics immediately, ideally within 1 hour. Collect cultures as soon as possible, ideally before antibiotics, but do not hold antibiotics in shock for a draw. Notify receiving team
- Watch Out For
- Acting on one bottle, or dismissing it, without the organism, time to positivity and source. A single skin-flora bottle is often contamination
Reference & Critical Ranges
Reference result
| Population | Result | Notes |
|---|---|---|
| Adult | No growth in any set | Usual normal result at the final report. Reporting windows are lab-specific |
| Children | No growth in any set | Same qualitative result; sample volume per bottle depends on the lab’s pediatric volume table |
Growth patterns & critical values
| Level | Growth pattern | What it means |
|---|---|---|
| Normal | No growth in any set | No bacteria or yeast detected at the final report |
| Possible contaminant | One set only, with common skin flora (for example, coagulase-negative staphylococci) | Often contamination. Check time to positivity, the number of sets and the clinical picture before acting or dismissing it |
| Likely true bacteremia | The same organism in two or more separately drawn sets | Bacteremia is more likely. Treat it with the suspected source |
| Critical | Organism seen on Gram stain of a positive bottle, or yeast | Call immediately (typical; lab-specific). The Gram stain is the first call, before identification |
Contamination benchmark: Labs aim low here. CLSI sets the contamination threshold below 3%, and 1% or less is considered optimal.
Units: The result is qualitative: growth or no growth. Time to positivity is in hours (h). Blood volume is in mL per bottle.
Causes of Abnormal Results
Positive result
| Cause | Clue |
|---|---|
| Bacteremia from a pneumonia, urinary, abdominal or skin source | Source signs on exam and imaging, with the same organism in any set |
| Endovascular infection (endocarditis, infected catheter) | Growth that persists or recurs across sets. Single-site draws are sufficient for most cases, but not for suspected endovascular infection |
| Fungemia (yeast on Gram stain or culture) | Yeast reported as a separate critical result. Treat per lab and sepsis protocol |
| Contamination of the draw (skin flora) | One set only; coagulase-negative staphylococci; longer time to positivity |
| Catheter or hub colonization | Growth from the line draw while the peripheral set is negative |
False positive vs true positive
| Feature | Favors contamination | Favors true bacteremia |
|---|---|---|
| Sets positive | One of two sets | Two or more separate sets with the same organism |
| Organism | Skin flora such as coagulase-negative staphylococci | A recognized pathogen that matches a source |
| Time to positivity | Longer. Median 25.8 h in contaminants in a 2025 single-hospital study | Shorter. Median 18.6 h in true bacteremia in the same study |
| Clinical context | No source, stable patient | Fever, hypotension or a clear source |
Low (negative) result: why a negative culture misleads
- One set only: In adult inpatients with three or more cultures in 24 hours, the first culture caught about 73% of bloodstream infections. Two cultures caught about 90%, three about 98% and four about 99.8% (2007 retrospective study at two university hospitals).
- Under-filled bottles: Fill adult bottles to 8 to 10 mL. A short fill holds less blood, and less blood means a lower chance of finding organisms.
- Antibiotics before the draw: Antibiotics given before collection can lower the yield. That's why you draw first, as long as the draw does not delay treatment.
- Rapid molecular panels: Many panels run on a positive bottle. They identify organisms and some resistance markers faster than culture does. Assays run directly on blood are less sensitive. So a negative direct-from-blood result does not exclude bacteremia. A negative panel is not a negative culture.
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Count the sets and check that they came from separate sites. Adults should have two sets, each with 8 to 10 mL per bottle.
- How sick is the patient? Sepsis-3 (2016) defines sepsis as life-threatening organ dysfunction from a dysregulated host response to infection. In practice that means a SOFA rise of 2 points or more. Septic shock means a vasopressor is needed to hold mean arterial pressure at 65 mm Hg or more, with lactate above 2 mmol/L and no hypovolemia to explain it. Outside the ICU, qSOFA (respiratory rate 22/min or more, altered mentation, systolic pressure 100 mm Hg or less) flags risk at the bedside. SSC 2026 recommends NEWS, NEW2, MEWS or SIRS over qSOFA as the single screening tool for acutely ill adults in hospital. A low qSOFA does not rule out sepsis.
- Time to positivity and trend: In one 2025 single-hospital study (71 patients), a 20-hour cutoff best separated true bacteremia from contamination for the organisms studied. Think of it as a local signal to validate. It is not a rule. Repeat sets show the trend, and the trend beats a single bottle.
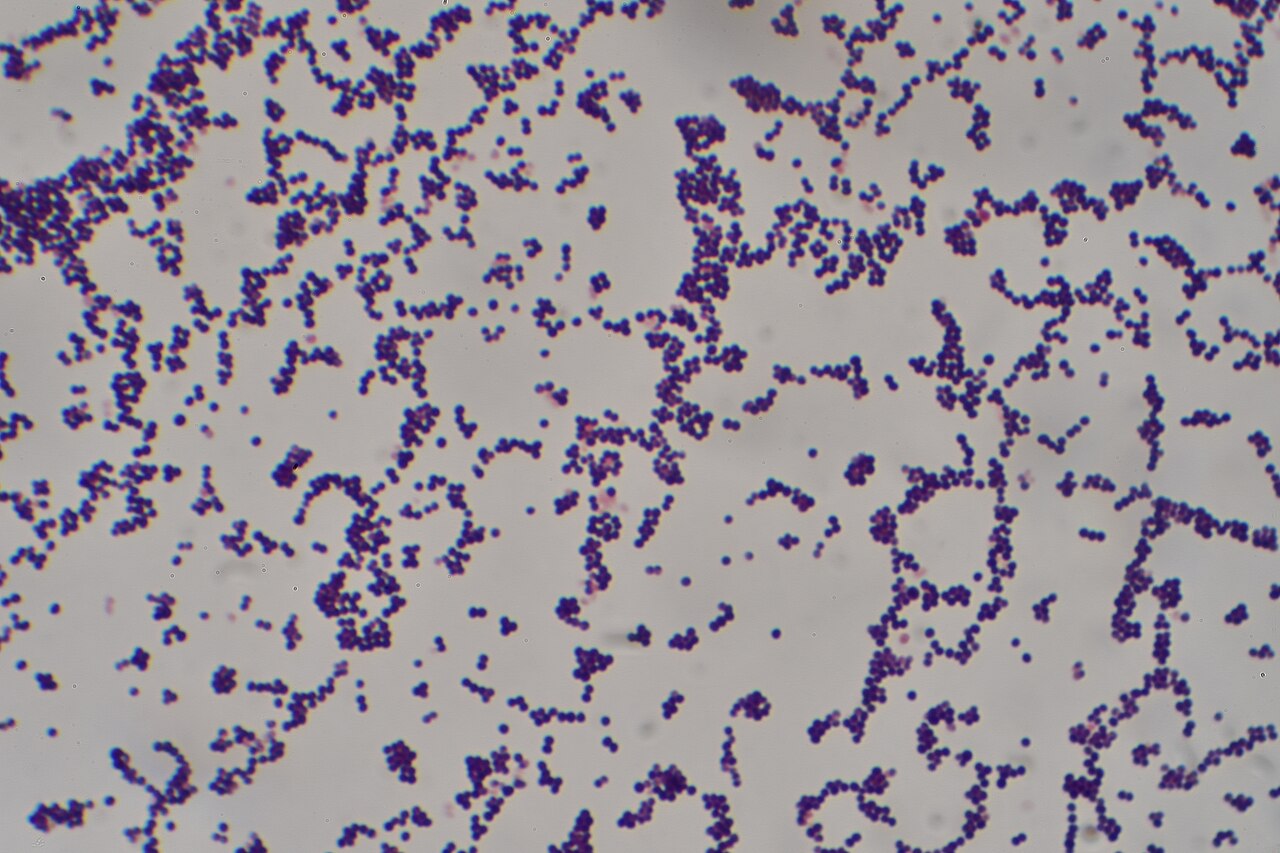
- Read the Gram stain: The shape of the organism narrows early therapy, even before identification is complete. Examples are clusters or chains of cocci, or gram-negative rods. Figure 1 shows gram-positive cocci in clusters.
- Match the organism to the source and the sets: Check the decision table below. A recognized pathogen with a clinical source, or the same organism in two sets, makes true bacteremia more likely.
- Escalate or dispose: In possible septic shock, antibiotics come first. Re-evaluate and de-escalate once infection is ruled out, or once the organism and susceptibilities are known. Tell the receiving team which sets were drawn and where the result stands.
Decision table
| Pattern | Suggests |
|---|---|
| Same organism in two or more separate sets, with fever or shock | True bacteremia. Act on the source and continue sepsis care |
| One set only, skin flora, longer time to positivity, stable patient | Likely contamination. Repeat sets and reassess the source. Do not stop antibiotics on one bottle while sepsis is still possible |
| Single set with a recognized pathogen and early positivity | Possible true bacteremia. Act on it while repeat sets are pending |
| Growth from a central line only, peripheral set negative | Catheter source or line contamination. Reassess the need for the line |
| Yeast on Gram stain | Fungemia. Treat as a critical result per lab and sepsis protocol |
Other specimens play by other rules. Urine and sputum cultures are judged on colony counts and specimen quality. This page is about blood cultures only.
Management Priorities
Emergency: possible septic shock or high likelihood of sepsis
- Cultures early: Draw cultures as soon as you can, ideally before antimicrobials (SSC 2026, strong recommendation, low certainty). Shock does not wait for a draw.
- Antibiotics now: Possible septic shock, or probable or definite sepsis? Give antimicrobials now, ideally within 1 hour of recognition (SSC 2026, strong recommendation, very low certainty).
- Fluids: Sepsis-induced hypoperfusion or septic shock: give at least 30 mL/kg IV crystalloid within the first 3 hours (SSC 2026, conditional suggestion, low certainty). Tailor it to the patient, reassess often and watch for over-resuscitation. Use actual body weight, or adjusted or ideal body weight if BMI is above 30. In heart failure or end-stage kidney disease, volume overload is more likely, so go carefully. Follow local protocol.
- Re-evaluate: Once cultures and susceptibilities return, reassess the choice. If infection is ruled out, stop the antibiotics.
Timing targets
| Scenario | Target | Strength |
|---|---|---|
| Adults: possible, probable or definite septic shock; probable or definite sepsis without shock | Antimicrobials immediately, ideally within 1 hour of recognition | Strong; very low certainty (per SSC 2026) |
| Adults: possible sepsis without shock | Time-limited rapid investigation; if concern for infection persists, antimicrobials within 3 hours of when sepsis was first suspected | Conditional; very low certainty (per SSC 2026) |
| Adults: low likelihood of infection, without shock | Consider deferring antimicrobials while monitoring closely | Conditional; very low certainty (per SSC 2026) |
| Children: septic shock | Antimicrobials as soon as possible, within 1 hour of recognition | Strong; very low-quality evidence (per SSC pediatric 2020) |
| Blood cultures | As soon as possible, ideally before antimicrobials; never delay shock antibiotics for a draw | Strong; low certainty (per SSC 2026) |
Medications
Empiric antibiotics follow the local antibiogram and protocol. This page gives no doses. See the ceftriaxone and vancomycin pages for dosing references.
Definitive care & disposition
- Narrow or stop by result: SSC 2026 says to keep reevaluating. Stop empiric antimicrobials when an alternative cause is demonstrated or strongly suspected and infection is still unconfirmed.
- Persistent or endovascular concern: Growth that persists across sets, or suspicion of endocarditis or a line infection, calls for a source workup and specialist input per local protocol.
Doses vary by protocol. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
Culture results live in the lab, not on scene. Out in the field there is nothing to act on from a culture. Your calls rest on the sepsis criteria and how fast antibiotics go in.
Before and during interfacility transport
- Do not delay treatment: Draw before antibiotics when that is quick. In an unstable patient, don't hold antibiotics or delay transport for a draw.
- Fill each bottle: Adults need 8 to 10 mL per bottle. An under-filled bottle lowers the chance of growth.
- Document: Record each set’s site and time of draw. The sets and their timing are what let the team read the result later.
Prehospital feasibility: A 2025 open-label randomized feasibility trial (35 patients) found paramedics collected blood cultures in 89% of patients. When ceftriaxone went in prehospital, antibiotics arrived a median of 108 minutes sooner. Paramedic practice needs local approval and medical direction.
| Setting | Consideration |
|---|---|
| EMS (field) | Collect cultures as soon as possible, ideally before antibiotics, but do not delay antibiotics in possible septic shock for a draw. Peripheral venipuncture per protocol. SSC 2026 suggests a standard sepsis screening tool for acutely ill adults en route by ambulance, and suggests prehospital antibiotics for probable or definite septic shock when in-hospital evaluation is expected to take over 60 minutes, only within a structured screening process (conditional; very low certainty) |
| ED / ICU | Two sets from separate sites, ideally before antibiotics but never delaying them in shock. Limit draws from existing lines, which raise contamination risk |
| Transport | Send bottles with the patient per lab instructions. Keep the set sites and times with the bottles |
Timing & Kinetics
| Parameter | Value | Clinical implication |
|---|---|---|
| Blood per bottle (adult) | 8 to 10 mL | Optimal fill. Under-filled bottles reduce yield |
| Sets per episode | Two sets, separate sites | Two sets detected about 90% of bloodstream infections in adults, three about 98%, four about 99.8% (2007 retrospective study) |
| Time to positivity | Median 18.6 h (true) vs 25.8 h (contaminant) | The traditional 24 h rule is unreliable: 43% of contaminants grew within 24 h. A single-hospital 2025 study (71 patients, mainly CoNS 70% and viridans streptococci 18%) proposed a 20 h cutoff for these major contaminants only. It does not establish a cutoff for S. aureus, gram-negative rods or Candida |
| Antibiotic timing | Within 1 hour (possible septic shock; probable or definite sepsis) | Antibiotics are not held for the final culture result or for a draw. Adjust choice when the organism is known |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Pediatric volumes and bottle types are lab-specific | Follow the lab’s pediatric volume table, which sets fill volumes and bottle types. The sources on this page do not give neonatal volumes |
| Children & adolescents | Cultures before antibiotics if no substantial delay; antibiotics within 1 hour in septic shock (per SSC pediatric 2020) | Same bundle logic as adults. Use the pediatric vital signs and weight-based dosing references |
| Pregnancy | No pregnancy-specific culture guidance is cited on this page | Use the same sepsis timing. Follow obstetric and local protocols for antibiotic choice |
| Older adults | Baseline organ dysfunction changes the SOFA rise | Use the trend from baseline. Sepsis-3 criteria apply to adults of any age |
| Indwelling devices (central lines, dialysis catheters, prosthetic valves) | Endovascular infection needs more than one site; line draws raise contamination | Draw peripheral sets where protocol allows. Limiting central-line draws was associated with lower contamination in a 2025 multicenter US study |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Single set or single site | False − | Fewer draws detect fewer infections | Two sets from separate sites |
| Under-filled bottles | False − | Less blood per bottle | Fill to 8 to 10 mL per adult bottle |
| Skin antisepsis | ↑ contamination | Skin flora on the needle path | Use the lab’s prep. The 2026 systematic review found consensus for 2% chlorhexidine in 70% alcohol |
| Draws from existing lines | ↑ contamination | Hub and line colonization | Limit line draws. A 2025 multicenter US study linked them to higher contamination |
Collection checklist
This is standard practice. Your lab’s collection manual gives the exact steps.
- Peripheral venipuncture first: Skip drawing through an existing catheter where you can. Line draws raise contamination.
- Antisepsis: Disinfect the bottle tops, and let the skin antiseptic dry fully before puncture.
- Order of draw: Culture bottles first, aerobic before anaerobic.
- Rarely contaminants: S. aureus, Candida and gram-negative rods are rarely contaminants. One positive bottle with any of these needs prompt action.
Medications & supplements
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Antibiotics before the draw | False − | Antibiotics can suppress growth | Draw first when it does not delay treatment (SSC 2026 recommends cultures ideally before antimicrobials, not at the cost of delay) |
Assay & device
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Rapid molecular assay run directly on blood | False − | Lower sensitivity than culture-based detection | A negative result does not exclude bacteremia. Keep the culture. Panels run on a positive bottle are a separate, faster identification step |
Common misinterpretations
- “One negative set rules out bacteremia.” No. In one study, a single set caught about 73% of adult bloodstream infections.
- “A single bottle of skin flora is always real.” Often it's contamination. Check the time to positivity and the sets.
- “A positive culture confirms the source.” The organism has to match a clinical source.
- “Waiting for the culture is safe in shock.” No. In possible septic shock, antibiotics are not held for cultures.
Physiology & Test Basics
What it measures
A blood culture picks up live bacteria or fungi circulating in the blood (bacteremia or fungemia). This page covers blood cultures only. Urine and sputum cultures use different criteria and are not covered here.
Physiology & regulation
- Sepsis is a dysregulated host response to infection. That response can cause life-threatening organ dysfunction (Sepsis-3, 2016).
- Bacteremia may come and go, so a single draw can miss it.
- Skin flora gets into draws. That is why labs track contamination rates.
How it is measured
Each set comes from a separate venipuncture, after skin antisepsis. Adults get 8 to 10 mL in each aerobic and anaerobic bottle. The lab loads the bottles into an automated system that signals growth. Time to positivity is the clock from loading to that signal. A Gram stain of the positive bottle comes first, then identification and susceptibility testing.
Why it matters
A positive result changes antibiotic choice and duration. An early negative does not rule out infection. In septic shock, the draw must not hold up the antibiotics.
Clinical Pearls
References
- Prescott H, Antonelli M, Alhazzani W, et al. Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock 2026. Crit Care Med. 2026 (published online 23 March 2026). https://doi.org/10.1097/CCM.0000000000007075
- Weiss SL, Peters MJ, Alhazzani W, et al. Surviving Sepsis Campaign International Guidelines for the Management of Septic Shock and Sepsis-Associated Organ Dysfunction in Children. Pediatr Crit Care Med. 2020;21(2):e52–e106. https://doi.org/10.1097/PCC.0000000000002198
- Singer M, Deutschman CS, Seymour CW, et al. The Third International Consensus Definitions for Sepsis and Septic Shock (Sepsis-3). JAMA. 2016;315(8):801–810. https://doi.org/10.1001/jama.2016.0287
- Lee A, Mirrett S, Reller LB, Weinstein MP. Detection of bloodstream infections in adults: how many blood cultures are needed? J Clin Microbiol. 2007;45(11):3546–3548. https://doi.org/10.1128/JCM.01555-07
- López-Rodríguez M, Álvarez-Fernández A, Smithson A, et al. Diagnostic stewardship for optimizing blood culture practices: a systematic review of clinical practice guidelines and evidence-based recommendations. J Hosp Infect. 2026;175:159–166. https://doi.org/10.1016/j.jhin.2026.06.024
- Fabre V, Hsu Y-J, Carroll KC, et al. Multicenter evaluation of blood culture contamination and blood cultures practices in US acute care hospitals: time for standardization. J Clin Microbiol. 2025;63(8):e00530-25. https://doi.org/10.1128/jcm.00530-25
- Manabe Y, Hagiya H, Fukushima S, et al. Time to positivity for differentiating blood culture contamination: A 20-hour cutoff for major contaminants. Diagn Microbiol Infect Dis. 2025;113(4):117030. https://doi.org/10.1016/j.diagmicrobio.2025.117030
- Cudini D, Smith K, Shao J, et al. Blood culture collection and administration of intravenous ceftriaxone by paramedics in patients with suspected sepsis (the PASS trial). Emerg Med Australas. 2025;37(2):e70027. https://doi.org/10.1111/1742-6723.70027
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.