

Bedside Snapshot
- Normal (Adult)
- 96–106 mEq/L (96–106 mmol/L)
- Critical Values
- <80 or >120 mEq/L (<80 or >120 mmol/L); typical, lab-specific
- High Suggests
- Salicylate artifact if anion gap very low or negative
- Large-volume 0.9% or hypertonic saline
- Diarrhea, renal tubular acidosis
- Hypernatremia (water loss)
- Low Suggests
- Vomiting or NG suction (metabolic alkalosis)
- Loop or thiazide diuretics
- Hyponatremia: SIADH, heart failure
- Post-hypercapnia, chronic CO₂ retention
- Act Now If
- Cl⁻ <80 or >120, or high Cl⁻ with a very low or negative anion gap: repeat, get a blood gas and full chemistry, send a salicylate level; notify medical control
- Watch Out For
- Falling HCO₃⁻ after liters of saline: check Cl⁻ and the anion gap before calling it worsening shock
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult | 96–106 mEq/L | 96–106 mmol/L | Some labs print 98–106 or 98–107; differences reflect the analyzer and reference population |
| Pregnancy and older adults | Same as adult | Same as adult | No separate interval in routine use; read changes against the cause (vomiting, diuretics) |
| Neonate (under 1 month) | Upper limit runs higher (about 113 mEq/L in some pediatric labs) | Same numbers in mmol/L | Use the pediatric laboratory's own interval |
| Children and adolescents | Same as adult in most labs | Same as adult | Some pediatric laboratories publish age-specific intervals |
Severity & critical values
| Level | Conventional | SI | What it means / typical findings |
|---|---|---|---|
| Low (hypochloremia) | <96 mEq/L | <96 mmol/L | Vomiting or NG suction, diuretics, hyponatremia; often with metabolic alkalosis and low K⁺ |
| Normal | 96–106 mEq/L | 96–106 mmol/L | Does not exclude a high anion gap acidosis; always read with Na⁺, HCO₃⁻ and the anion gap |
| High (hyperchloremia) | >106 mEq/L | >106 mmol/L | Normal anion gap acidosis, saline load or water loss; a very low or negative anion gap points to a lab artifact |
| Critical | <80 or >120 mEq/L (typical; lab-specific) | <80 or >120 mmol/L | Severe gastric losses with alkalosis, or a large chloride load or severe hypernatremia. Call limits vary by institution, roughly 75–85 low and 120–130 high |
Conversion: Chloride is monovalent, so mEq/L and mmol/L are the same number. The factor is 1.
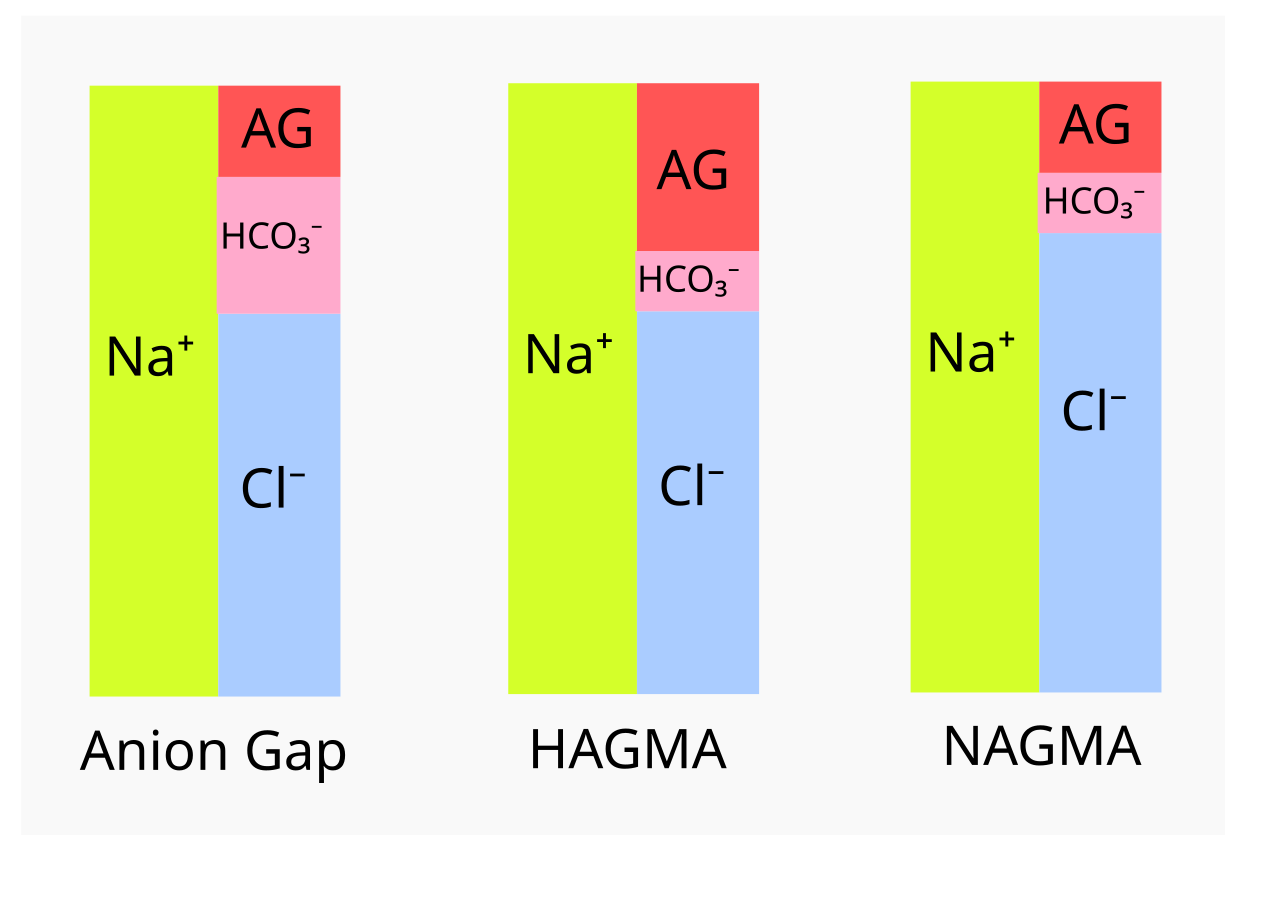
The E3 textbook normal gap is 8–12 mEq/L, but the gap depends on the analyzer: use your laboratory's range.
A low gap has causes of its own. Think hypoalbuminemia, paraproteinemia (for example, myeloma), hypercalcemia, lithium and bromide, and laboratory error.
For every 1 g/dL that albumin sits below 4 g/dL, add 2.5 mEq/L. Do this before you call the gap normal.
Causes of Abnormal Results
High (hyperchloremia >106 mEq/L)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Lab artifact (pseudohyperchloremia) | Salicylate poisoning (an important cause on some analyzers); bromide | Very low or negative AG; tinnitus, vomiting, tachypnea, mixed respiratory alkalosis and metabolic acidosis |
| Chloride load | Large-volume 0.9% saline, hypertonic saline, chloride-rich parenteral nutrition, arginine or lysine hydrochloride infusions | Cl⁻ rises and HCO₃⁻ falls with a normal AG after liters of fluid |
| GI bicarbonate loss | Diarrhea, villous adenoma, pancreatic or biliary drainage, ureteral diversion (ileal conduit, ureterosigmoidostomy) | Stool or drain output; normal AG; often low K⁺ |
| Renal bicarbonate loss or poor acid excretion | Renal tubular acidosis (RTA) types 1, 2 and 4; chronic kidney disease (CKD); toluene; acetazolamide, topiramate | Normal AG; K⁺ low in types 1 and 2, high in type 4 |
| DKA recovery | Ketone anions lost in urine while saline replaces volume | AG closes but HCO₃⁻ stays low: often hyperchloremic acidosis, not persistent ketoacidosis |
| Water loss greater than salt loss | Hypernatremia: dehydration, diabetes insipidus, poor water access | Na⁺ and Cl⁻ rise together; AG normal |
Low (hypochloremia <96 mEq/L)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Gastric acid (HCl) loss | Vomiting, NG suction, gastric outlet obstruction; pyloric stenosis in infants | Metabolic alkalosis, low K⁺, volume depletion; urine Cl⁻ <20 mEq/L |
| Renal chloride wasting | Loop and thiazide diuretics; Bartter and Gitelman syndromes | Urine Cl⁻ high while the diuretic is acting, low once it wears off |
| Other chloride losses | Chloride-losing diarrhea (congenital or acquired), laxative overuse, high-output ileostomy, cystic fibrosis (sweat loss) | Alkalosis with volume depletion; heat exposure in cystic fibrosis |
| Post-hypercapnia | Chronic CO₂ retention corrected quickly (for example, a COPD patient ventilated to a normal PaCO₂) | HCO₃⁻ stays high after PaCO₂ falls; low Cl⁻ maintains the alkalosis |
| Dilution | Hyponatremia: SIADH, heart failure, cirrhosis, hypotonic fluids, heavy water intake | Na⁺ and Cl⁻ fall together; HCO₃⁻ normal |
| Alkali gain or mineralocorticoid excess | Primary aldosteronism, Cushing syndrome, licorice; bicarbonate or citrate loads (massive transfusion); calcium-alkali syndrome | Hypertension or high HCO₃⁻ with low K⁺; urine Cl⁻ >20 mEq/L |
High or low chloride rarely causes symptoms on its own. What the patient shows comes from the acid–base disorder, the volume problem, or the sodium and potassium shifts that travel with it.
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? A sample drawn above a saline line raises Cl⁻ and Na⁺. A very low or negative gap with high Cl⁻ points to an artifact (salicylate, bromide).
- How sick is the patient? Check pH, perfusion, mental status and K⁺. Chloride is a clue. It is rarely the emergency.
- Read Cl⁻ against Na⁺ and HCO₃⁻. If Cl⁻ moves with Na⁺, think water balance. If it moves the opposite way to HCO₃⁻, think acid–base.
- Calculate the anion gap and correct it for albumin. Use Na⁺, Cl⁻ and HCO₃⁻ from the same sample and analyzer.
- Classify with a blood gas. Normal-AG acidosis, high-AG acidosis or metabolic alkalosis (table below); in alkalosis, send a spot urine Cl⁻.
- Trend and escalate. Watch for a rising Cl⁻ with a falling HCO₃⁻ during resuscitation, a negative anion gap, or a critical value. Any one of those means a call to the prescriber or medical control.
| Pattern | Suggests | Next step |
|---|---|---|
| ↑ Cl⁻, ↓ HCO₃⁻, normal AG | Hyperchloremic (normal-AG) acidosis: diarrhea, RTA, saline load, DKA recovery | Review fluids given and stool or drain output; K⁺; urine anion gap if the cause is unclear |
| ↑ Cl⁻, very low or negative AG | Pseudohyperchloremia: salicylate, bromide | Salicylate level; ask the lab to re-measure Cl⁻ by another method |
| Normal or ↓ Cl⁻, ↓ HCO₃⁻, high AG | High-AG acidosis: GOLDMARK (glycols, oxoproline, L-lactate, D-lactate, methanol, aspirin, renal failure, ketoacidosis); MUDPILES is the older mnemonic | Lactate, ketones, creatinine, osmolal gap, salicylate level |
| ↓ Cl⁻, ↑ HCO₃⁻ | Metabolic alkalosis, or compensation for chronic respiratory acidosis | Blood gas; spot urine Cl⁻ before saline or diuretics if possible |
Metabolic alkalosis: urine chloride
| Spot urine Cl⁻ | Category | Causes | What corrects it |
|---|---|---|---|
| <20 mEq/L | Chloride-responsive (saline-responsive) | Vomiting, NG suction, diuretic effect worn off, post-hypercapnia, chloride-losing diarrhea | If volume-depleted: replace chloride and volume (0.9% saline) and potassium (KCl). In volume overload (heart failure, cirrhosis) saline is not appropriate; treat per the prescriber (acetazolamide and potassium are typical alternatives) |
| >20 mEq/L | Chloride-resistant | Diuretic still acting, mineralocorticoid excess, licorice, Bartter or Gitelman syndrome, severe K⁺ depletion | Treat the cause and replace K⁺; saline does not correct it |
Cystic fibrosis usually gives a low urine Cl⁻ from sweat losses, so it is chloride-responsive. Don't lean on urine Na⁺ in any alkalosis with bicarbonaturia. The bicarbonate in the urine drags sodium along, so urine Na⁺ can read high even when the patient is volume depleted. Use urine Cl⁻ to classify.
Saline versus balanced crystalloids
0.9% saline carries 154 mEq/L of chloride, roughly 50% more than plasma. Liters of it push Cl⁻ up and HCO₃⁻ down. Lactated Ringer's (109 mEq/L) and Plasma-Lyte A (98 mEq/L) carry less chloride.
| Trial or guideline | Population | Finding |
|---|---|---|
| SMART (2018) | 15,802 adults, 5 ICUs; lactated Ringer's or Plasma-Lyte A vs saline | Fewer major adverse kidney events at 30 days with balanced fluid (14.3% vs 15.4%) |
| BaSICS (2021) | 11,052 ICU patients in Brazil; Plasma-Lyte 148 vs saline | No 90-day mortality difference (26.4% vs 27.2%); prespecified TBI subgroup (interaction P = .02) had higher 90-day mortality with balanced fluid (31.3% vs 21.1%) |
| PRoMPT BOLUS (2026) | 9,041 children enrolled (aged 2 months to under 18 years) with septic shock | Primary outcome, a major adverse kidney event (death, new renal replacement therapy, or persistent kidney dysfunction) within 30 days: 3.4% with balanced fluid vs 3.0% with saline, no meaningful difference; hyperchloremia 31.4% with balanced fluid vs 49.0% with saline |
| Surviving Sepsis Campaign (SSC) 2026, adults | Adults with sepsis or septic shock | Suggests balanced crystalloids over 0.9% saline (conditional recommendation) |
Field & Transport Considerations
Point-of-care testing
Many blood gas analyzers, and some handheld cartridge chemistry analyzers, report Cl⁻ on whole blood using a direct ion-selective electrode. Results can differ from the central lab's serum value by a few mEq/L. So trend on one analyzer. Never build an anion gap from values measured on different devices.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Before departure | Obtain the latest Na⁺, Cl⁻, HCO₃⁻, K⁺, anion gap and blood gas with timestamps; add a salicylate level if the gap is very low or the history fits |
| Fluid record | Hand off the type and total volume of every crystalloid given; several liters of saline explain a new normal-gap acidosis |
| Ongoing losses | Record vomiting and NG output; continuing gastric loss deepens alkalosis and hypokalemia en route |
| Long or ICU-level transfers | Re-check chemistry per protocol during hypertonic saline, large-volume resuscitation or DKA treatment; report a rising Cl⁻ with falling HCO₃⁻ or a critical value |
| Scope | EMS: fluid choice per protocol (many protocols use 0.9% saline in suspected TBI). ED/ICU and transport (Paramedic/RN/CCT): interpret the trend and escalate per protocol |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Upper reference limit runs higher in some pediatric labs; loop and thiazide diuretics in preterm infants lower Cl⁻; pyloric stenosis causes hypochloremic, hypokalemic alkalosis | Use the pediatric lab's interval; pyloric stenosis needs chloride, volume and K⁺ before surgery |
| Children & adolescents | Same causes as adults: gastroenteritis (normal-gap acidosis), vomiting (alkalosis), DKA recovery | In pediatric septic shock, saline caused more hyperchloremia than balanced fluid but no meaningful difference in the primary outcome of major adverse kidney events or death by 30 days (PRoMPT BOLUS) |
| Pregnancy | No separate chloride interval in routine use; hyperemesis gravidarum causes hypochloremic alkalosis with hypokalemia | Check K⁺ and replace chloride and volume as for other vomiting |
| Older adults | No clinically meaningful range difference; diuretic use is common | Low Cl⁻ with high HCO₃⁻ often reflects diuretics; watch K⁺ and volume |
| CKD / dialysis | Reduced renal acid excretion causes a normal-gap acidosis that becomes high-gap as CKD advances | Interpret against the patient's baseline and the timing of the last dialysis |
| Other: TBI, cystic fibrosis | TBI: many protocols prefer saline despite its chloride load (protocol-dependent, not guideline-mandated). Cystic fibrosis: sweat chloride loss causes alkalosis, especially in heat | Where the protocol prefers saline in TBI, accept a mild saline-related Cl⁻ rise; think cystic fibrosis in a young patient with unexplained hypochloremic alkalosis |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Drawn above or through a saline line | ↑ Cl⁻ and Na⁺ | Contamination with 154 mEq/L chloride | Draw from the opposite arm or pause the infusion and discard per policy |
| Mixing analyzers | False AG | Blood gas (direct) and central lab (indirect) electrodes differ slightly | Calculate the AG from one sample on one analyzer |
Medications & toxins
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Salicylate (toxic levels) | False + (↑ Cl⁻) | Chloride electrodes read salicylate as chloride; worse with some manufacturers and older electrodes | Salicylate level; re-measure Cl⁻ by another method |
| Bromide | False + (↑ Cl⁻) | Electrodes and some methods read bromide as chloride | Bromide level if exposure is possible |
Physiologic / biologic
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Severe hyperlipidemia or paraproteinemia | ↓ (false, central lab) | Lipid or protein displaces plasma water in diluted (indirect) measurement | Compare with a blood gas (direct electrode) value |
Common misinterpretations
- "Chloride is normal, so the acid–base is fine": A high-AG acidosis leaves Cl⁻ normal or low. Normal chloride does not rule out a high gap.
- "New acidosis after resuscitation means worsening shock": Rising Cl⁻ with a normal gap after liters of saline is usually the fluid. Check the AG and lactate first.
- "HCO₃⁻ is still low, so DKA is not resolving": If the anion gap has closed, the leftover acidosis is usually hyperchloremic.
- "Normal AG is 8–12 everywhere": Each analyzer sets its own range.
Physiology & Test Basics
What it measures
This page covers blood chloride. It shows up on every basic and comprehensive metabolic panel, and on many blood gas panels. Spot urine Cl⁻ is a different test: you use it to classify metabolic alkalosis. Sweat chloride, used for cystic fibrosis testing, is separate too.
Physiology & regulation
- Main extracellular anion: About two-thirds of plasma anions. It balances Na⁺ and sets much of plasma tonicity.
- Electroneutrality: Cl⁻ and HCO₃⁻ trade places. A primary HCO₃⁻ loss raises Cl⁻. A primary Cl⁻ loss raises HCO₃⁻.
- Strong ion difference: Plasma's is about 40 mEq/L. Saline's is 0 (Na⁺ 154, Cl⁻ 154 mEq/L). So large volumes narrow the plasma difference and acidify it.
- Kidney: Chloride is reabsorbed with sodium along the nephron, through the loop and distal transporters that diuretics block. In the collecting duct, chloride is swapped for HCO₃⁻. So low chloride stops the kidney from dumping excess bicarbonate.
- Stomach: Parietal cells secrete HCl. Gastric losses take chloride and acid out together.
- Red cells: The chloride shift swaps Cl⁻ in for HCO₃⁻ out. That is how CO₂ travels from the tissues to the lungs.
How it is measured
The sample is serum (gold-top serum separator tube) or plasma (light-green-top lithium heparin). An ion-selective electrode reads it. The central lab usually dilutes the sample first (indirect). Blood gas and cartridge analyzers read it undiluted (direct). No fasting is needed. It runs on the routine chemistry panel, so it comes back with Na⁺, K⁺ and HCO₃⁻.
Why it matters
Why look at chloride at all? It turns a chemistry panel into an acid–base tool. Paired with Na⁺ and HCO₃⁻, it gives you the anion gap and splits normal-gap acidosis from high-gap acidosis. It also tracks the chloride load of resuscitation fluids. And it picks out chloride-responsive alkalosis, the kind that needs saline and potassium.
Clinical Pearls
References
- MedlinePlus, U.S. National Library of Medicine. (2025). Chloride test – blood (review date May 19, 2025). https://medlineplus.gov/ency/article/003485.htm
- Do, C., Vasquez, P. C., & Soleimani, M. (2022). Metabolic alkalosis pathogenesis, diagnosis, and treatment: Core curriculum 2022. American Journal of Kidney Diseases, 80(4), 536–551. https://doi.org/10.1053/j.ajkd.2021.12.016
- Achanti, A., & Szerlip, H. M. (2023). Acid-base disorders in the critically ill patient. Clinical Journal of the American Society of Nephrology, 18(1), 102–112. https://doi.org/10.2215/CJN.04500422
- Wiederkehr, M. R., Benevides, R., Santa Ana, C. A., & Emmett, M. (2021). Pseudohyperchloremia and negative anion gap: Think salicylate! The American Journal of Medicine, 134(9), 1170–1174. https://doi.org/10.1016/j.amjmed.2021.03.017
- Semler, M. W., Self, W. H., Wanderer, J. P., et al. (2018). Balanced crystalloids versus saline in critically ill adults (SMART; landmark trial). New England Journal of Medicine, 378(9), 829–839. https://doi.org/10.1056/NEJMoa1711584
- Zampieri, F. G., Machado, F. R., Biondi, R. S., et al. (2021). Effect of intravenous fluid treatment with a balanced solution vs 0.9% saline solution on mortality in critically ill patients: The BaSICS randomized clinical trial. JAMA, 326(9), 818–829. https://doi.org/10.1001/jama.2021.11684
- Balamuth, F., Weiss, S. L., Long, E., et al. (2026). Balanced fluid or 0.9% saline in children treated for septic shock (PRoMPT BOLUS). New England Journal of Medicine, 395(9), 870–881. https://doi.org/10.1056/NEJMoa2601969
- Prescott, H. C., Antonelli, M., Alhazzani, W., et al. (2026). Surviving Sepsis Campaign: International guidelines for management of sepsis and septic shock 2026. Critical Care Medicine, 54(4), 725–812. https://doi.org/10.1097/CCM.0000000000007075
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.