

Bedside Snapshot
- Normal (Adult)
- Men 14.0–17.5 g/dL (140–175 g/L); women 12.0–16.0 g/dL (120–160 g/L). WHO anemia: men <13.0, women <12.0, pregnancy <11.0 (second trimester <10.5)
- Critical Values
- <7 or >20 g/dL (<70 or >200 g/L); typical, lab-specific. Neonatal limits are age-specific
- High Suggests
- Dehydration or burns (hemoconcentration)
- Chronic hypoxia: COPD, sleep apnea, altitude
- Smoking or CO; testosterone or ESAs
- Polycythemia vera (clot risk)
- Low Suggests
- Acute or occult bleeding
- Hemolysis, including transfusion reaction
- Iron, B12 or folate deficiency; CKD
- Dilution: IV fluids, pregnancy
- Act Now If
- Shock with bleeding: control bleeding, large-bore access, crossmatch, activate massive transfusion on clinical signs (not the Hb). Stable, Hb <7 g/dL (<10 in stable acute MI): transfuse per threshold
- Watch Out For
- A normal first Hb does not exclude major bleeding: it falls only as fluid dilutes the blood. Treat the patient and repeat the Hb
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult men | 14.0–17.5 g/dL | 140–175 g/L | WHO 2024 anemia cutoff <13.0 g/dL. A man at 13.0–13.9 g/dL is below this textbook range but not anemic by WHO: repeat, compare with baseline and read with MCV and ferritin |
| Adult women (not pregnant) | 12.0–16.0 g/dL | 120–160 g/L | WHO 2024 anemia cutoff <12.0 g/dL |
| Pregnancy, first trimester | Anemia if <11.0 g/dL | <110 g/L | Plasma volume expands faster than red cell mass |
| Pregnancy, second trimester | Anemia if <10.5 g/dL | <105 g/L | Lowest cutoff of pregnancy (dilution is greatest) |
| Pregnancy, third trimester | Anemia if <11.0 g/dL | <110 g/L | Recheck before delivery; obstetric bleeding is the main acute risk |
| Older adult | Adult range | Adult range | WHO cutoffs are defined for ages 15–65; a low value is not normal aging, so look for a cause |
| Newborn | 14–24 g/dL | 140–240 g/L | Highest at birth and in the first days, then falls through the first weeks |
| Infant 2–6 months | 9.5–14 g/dL | 95–140 g/L | Lower limit is lab-specific; term infants reach a physiologic nadir at 2–3 months, about 9–11 g/dL; preterm infants fall earlier and lower |
| Child 6–23 months | Anemia if <10.5 g/dL | <105 g/L | New WHO 2024 cutoff (was 11.0) |
| Child 2–4 years | Anemia if <11.0 g/dL | <110 g/L | WHO 2024 (24–59 months) |
| Child 5–11 years | Anemia if <11.5 g/dL | <115 g/L | WHO 2024 |
| Adolescent 12–14 years | Anemia if <12.0 g/dL | <120 g/L | Boys and girls; adult cutoffs from age 15 |
Severity & critical values
| Level | Conventional | SI | What it means / typical findings |
|---|---|---|---|
| Below the men's textbook range, not WHO anemia | Men 13.0–13.9 g/dL | 130–139 g/L | Below the Critical Care Transport lower limit (14.0) but above the WHO 2024 anemia cutoff (13.0): repeat, compare with baseline and read with MCV and ferritin before calling it anemia |
| Mild anemia | Men 11.0–12.9; women 11.0–11.9 g/dL | 110–129; 110–119 g/L | Often no symptoms; find the cause (WHO 2024 severity, non-pregnant adults) |
| Moderate anemia | 8.0–10.9 g/dL (pregnancy and children under 5: 7.0–9.9) | 80–109 g/L (pregnancy and children under 5: 70–99 g/L) | Fatigue, exertional dyspnea, tachycardia; worse if the fall was fast |
| Severe anemia | <8.0 g/dL (pregnancy and children under 5: <7.0) | <80 g/L (<70 g/L) | Symptoms at rest, angina in coronary disease; check the transfusion threshold for this patient |
| Erythrocytosis workup | Men >16.5; women >16.0 g/dL | >165; >160 g/L | WHO 2022 hemoglobin criterion for polycythemia vera (with JAK2 testing); can overlap the top of a lab's male range |
| Critical | <7 or >20 g/dL | <70 or >200 g/L | Typical; lab-specific. Below 7: under the restrictive transfusion threshold. Above 20: hyperviscosity and thrombosis risk |
Conversion: g/dL × 10 = g/L; g/dL × 0.6206 = mmol/L (used in some European labs)
The rule works when red cells are normal in size and fill. Hb 15 g/dL gives Hct 45%. A large gap suggests a bad specimen or abnormal red cell indices.
Causes of Abnormal Results
High (erythrocytosis: above the reference range; workup at Hb >16.5 g/dL in men or >16.0 g/dL in women)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Relative (low plasma volume) | Dehydration from vomiting, diarrhea, burns, diuretics or heat illness | Dry mucosa, rising BUN; Hb falls back once volume is replaced |
| Chronic hypoxia | COPD, obstructive sleep apnea, living at high altitude, cyanotic heart disease with a right-to-left shunt | Low SpO₂, clubbing, obesity or snoring history |
| Carbon monoxide | Smoking, chronic CO exposure | Normal SpO₂ despite exposure; carboxyhemoglobin on CO-oximetry |
| Drug-driven | Testosterone, anabolic steroids, erythropoiesis-stimulating agents (ESAs) such as epoetin | Medication history; check the Hb or Hct on testosterone therapy |
| Erythropoietin-secreting lesion | Renal cell carcinoma, hepatocellular carcinoma, cerebellar hemangioblastoma, erythrocytosis after kidney transplant | Flank mass, hematuria, liver disease; normal SpO₂ |
| Primary (clonal) | Polycythemia vera (JAK2-mutated myeloproliferative neoplasm) | Itching after a warm bath, splenomegaly, high WBC or platelets, arterial or venous clots |
| Neonatal polycythemia | Delayed cord clamping, maternal diabetes, growth restriction, recipient twin in twin-to-twin transfusion | Plethora, jitteriness, poor feeding; confirm with a venous hematocrit (>65%) |
Low (anemia: Hb <13.0 g/dL in men, <12.0 g/dL in women; moderate 8.0–10.9, severe <8.0)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Acute blood loss | Trauma, GI bleeding, postpartum hemorrhage, ruptured ectopic pregnancy or aneurysm, retroperitoneal bleeding | Tachycardia, rising shock index, melena or hematemesis; the first Hb may still be normal |
| Hemolysis | Hemolytic transfusion reaction, autoimmune hemolysis, G6PD deficiency after an oxidant drug, sickle cell crisis, microangiopathy (TTP, HUS, DIC) | Jaundice, dark urine; high LDH and indirect bilirubin, low haptoglobin, high reticulocytes |
| Dilution | Large crystalloid volumes, pregnancy, fluid overload | Albumin and other cell lines fall together; no bleeding source |
| Iron deficiency (microcytic) | Menstrual or occult GI loss, pregnancy, poor intake, malabsorption | Low MCV, high RDW, low ferritin; pica, restless legs |
| Other microcytic causes | Lead poisoning, sideroblastic anemia | Basophilic stippling (lead); ring sideroblasts on smear (sideroblastic); iron studies are not low |
| B12 or folate deficiency (macrocytic) | Pernicious anemia, alcohol use disorder, malabsorption, drugs such as methotrexate, hypothyroidism | High MCV; neuropathy or confusion with B12 deficiency |
| Underproduction | Chronic kidney disease (low erythropoietin), anemia of inflammation, marrow failure or infiltration, chemotherapy | Low reticulocytes; other cell lines low in marrow disease |
| Inherited hemoglobin disorder | Thalassemia trait, sickle cell disease, HbC or HbE | Microcytosis out of proportion to the anemia, normal ferritin, family history; chronic low baseline in sickle cell disease |
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? A sample drawn above a running IV, or through a line without enough discard, reads falsely low. A clotted sample can't be trusted. Repeat an unexpected value before you act on it.
- How sick is the patient? Check vital signs, shock index, active bleeding, chest pain or ischemic ECG changes, dyspnea at rest and syncope. Symptoms and bleeding outrank the number.
- Acute or chronic, and what is the trend? Compare with the last known baseline. The trend tells you more than any single value. Early in hemorrhage the Hb often looks normal, and it falls only once fluid refills the vessels.
- Calculate and cross-check. Hct ≈ 3 × Hb. The arterial oxygen content below explains why anemia cuts oxygen delivery while SpO₂ stays normal.
- Classify. Sort it with the WHO 2024 cutoffs and severity bands. Then look at the MCV (microcytic, normocytic, macrocytic) and the reticulocyte count. High reticulocytes point to loss or destruction. Low ones point to underproduction.
- Escalate or dispose. Transfuse by this patient's threshold (table below). Bring in hematology for hemolysis, pancytopenia or Hb >20 g/dL. Admit for active bleeding or symptomatic anemia.
At a normal Hb, oxygen content sits near 20 mL O₂/dL (Hb 15 g/dL, SaO₂ 100%). Cut the Hb in half and oxygen content roughly halves with it. Once SaO₂ is near 100%, pushing PaO₂ higher buys little.
Red cell transfusion thresholds (stable, not actively bleeding)
| Population | Consider RBCs below | Basis |
|---|---|---|
| Hospitalized adults, including ICU | 7 g/dL | AABB 2023, strong recommendation |
| Cardiac surgery | 7.5 g/dL | AABB 2023 (threshold used in trials) |
| Orthopedic surgery or preexisting cardiovascular disease | 8 g/dL | AABB 2023 (threshold used in trials) |
| Acute myocardial infarction | 10 g/dL (liberal) | AABB 2025 AMI guideline, conditional (low-certainty evidence): hospitalized, anemic, hemodynamically stable AMI patients; not for active hemorrhage or instability. A restrictive 7–8 g/dL strategy may increase mortality |
| Hematology and oncology inpatients | 7 g/dL | AABB 2023, conditional |
| Critically ill children (no hemoglobinopathy, cyanotic heart disease or severe hypoxemia) | 7 g/dL | AABB 2023, strong recommendation |
| Children with congenital heart disease | 7 (biventricular repair); 9 (single-ventricle palliation); 7–9 g/dL (uncorrected) | AABB 2023, conditional |
| Acute brain injury (TBI, SAH, ICH) | Contested: 7 vs 9 g/dL | TRAIN 2024 favored 9 g/dL for neurologic outcome; HEMOTION 2024 (TBI, 10 vs 7) found no significant difference. Follow the neurocritical care protocol |
| Active hemorrhage | No Hb trigger | Transfuse for shock and ongoing loss; if transfusing, target 7–9 g/dL (European trauma guideline 2023) |
Management Priorities
Doses vary by protocol; follow local protocols and medical direction.
Emergency: Hemorrhagic shock (any Hb)
- Stop the bleeding: direct pressure, tourniquet, hemostatic packing, pelvic binder; early surgical, interventional or obstetric source control.
- Recognize shock clinically: use the shock index and pulse pressure, not the Hb. A normal first Hb does not exclude major bleeding; activate massive transfusion on clinical grounds.
- Resuscitate with blood: red cells with plasma or fibrinogen and platelets per the massive transfusion protocol; limit crystalloid. Without brain injury, target systolic BP 80–90 mmHg until bleeding stops; with severe TBI (GCS ≤8), MAP ≥80 mmHg.
- Adjuncts & monitor: TXA within 3 hr of injury; keep ionized calcium 1.1–1.3 mmol/L; prevent hypothermia; repeat Hb, lactate, PT/INR, fibrinogen and platelets.
Emergency: Severe anemia without active bleeding (Hb <7 g/dL or symptomatic)
- Confirm & assess: repeat an unexpected value; 12-lead ECG for ischemia; search for occult bleeding and hemolysis.
- Draw before you transfuse: type and screen, reticulocytes, ferritin and iron studies, B12, folate, LDH, bilirubin, haptoglobin and a smear. Transfused cells confound every one of them.
- Transfuse to the threshold: one unit, then reassess symptoms and Hb before the next. Run it slower in heart failure, kidney failure, older adults and chronic severe anemia (circulatory overload risk).
- Treat the cause: iron, B12 or folate replacement, stop the offending drug, hematology for hemolysis or marrow failure.
Medications
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Red blood cells (packed) | Stable anemia below threshold: 1 unit IV, then reassess before the next (raises Hb about 1 g/dL and Hct about 3%) | 10–15 mL/kg IV, each unit within 4 hr (about 2 g/dL per 10 mL/kg); volume per local pediatric transfusion protocol | Immediate. Draw diagnostic labs first; watch for transfusion reactions and circulatory overload |
| Massive transfusion protocol products | Red cells with plasma (plasma to red cells at least 1:2) or fibrinogen, plus platelets per protocol | Weight-based pediatric massive transfusion protocol; titrate to hemorrhage control: no fixed max | Guide later rounds with labs or viscoelastic testing; see fibrinogen |
| Tranexamic acid (TXA) | Trauma hemorrhage: 1 g IV/IO over 10 min, then 1 g over 8 hr, within 3 hr of injury (max 2 g) | 15 mg/kg IV/IO over 10–20 min (max 1 g), then 2 mg/kg/hr for 8 hr; off-label, per protocol | Never start more than 3 hr after injury; IV only; not for GI bleeding. Postpartum (WOMAN trial): 1 g IV, second dose if bleeding continues after 30 min, within 3 hr of birth; follow the OB protocol |
| Calcium chloride 10% | Hypocalcemia during massive transfusion: 1 g (10 mL) IV, repeat to ionized calcium 1.1–1.3 mmol/L | 20 mg/kg (0.2 mL/kg) IV/IO slowly (max 1 g per dose in this reference; protocol-dependent) | Citrate in blood products binds calcium; central or large proximal vein; the European trauma guideline 2023 prefers calcium chloride and keeps ionized calcium 1.1–1.3 mmol/L |
Definitive care & disposition
- Bleeding: trauma center, GI endoscopy, obstetric or interventional radiology control; reverse anticoagulants per their pages.
- Chronic anemia: treat the cause; oral or IV iron, B12, folate. ESAs such as epoetin alfa take 2–6 weeks to raise Hb and are never for acute anemia; in CKD, targeting Hb >11 g/dL raised the risk of death, MI and stroke (FDA boxed warning).
- Polycythemia vera: hematology; phlebotomy to Hct <45% plus low-dose aspirin is standard care, with cytoreduction for high-risk disease.
- Admit or ICU: active bleeding, hemodynamic instability, ischemia, hemolysis with rapid fall, or Hb below threshold needing transfusion.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
- Hemoglobin photometers (capillary or venous drop). Quick, but capillary results shift with technique and run apart from venous lab values. Trend on one method.
- Blood gas co-oximetry reports total Hb plus carboxyhemoglobin, methemoglobin and sulfhemoglobin. Whatever the oxygen content, methemoglobin keeps SpO₂ near 85%. Some cartridge analyzers measure hematocrit by conductivity and calculate Hb. Heavy crystalloid dilution and low protein push those numbers low.
- Noninvasive SpHb: A trend tool only. Confirm with a blood sample before you make a transfusion decision.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Handoff (Paramedic/RN/CCT) | Last Hb with draw time and the trend, units transfused and the time, blood bank status (type and screen, crossmatched units), TXA time, ongoing losses |
| Prehospital blood | Protocol-dependent: the 2023 European trauma guideline makes no recommendation for or against prehospital blood products. Whole blood and low-titer O programs are local decisions |
| Blood running en route | Per local protocol: vital signs before, early in and after each unit; stop and treat suspected reactions; document unit numbers |
| Re-check cadence | Repeat Hb after each unit or resuscitation phase; a single reassuring value early after injury proves nothing |
| When to delay or redirect | Ongoing hemorrhage needs source control: go to the center that can stop it, with blood on board when available |
Altitude and flight
Anemia cuts oxygen content, and SpO₂ still reads normal. Cabin altitude lowers PaO₂ on top of that. In flight, give oxygen to symptomatic anemic patients and expect the heart rate to climb. SpO₂ will not show the deficit.
Timing & Kinetics
| Parameter | Value | Clinical implication |
|---|---|---|
| Acute hemorrhage | Hb near baseline at first; falls over hours as interstitial fluid and IV fluids dilute the blood | Repeat Hb serially and read each value with the fluid given since the last; never clear a bleeding patient on one normal value |
| After red cell transfusion | About 1 g/dL per unit in an average adult; about 2 g/dL per 10 mL/kg in a child | A smaller rise than expected suggests ongoing bleeding or hemolysis |
| Newborn to infant | Highest in the first days, nadir at 2–3 months (term), earlier and lower in preterm infants | A low value at 2–3 months can be physiologic; earlier or lower values need evaluation |
| Pregnancy | Falls from the first trimester to a low in the second, then partly recovers | Use trimester cutoffs; a value at the edge of normal leaves less reserve for postpartum hemorrhage |
| ESA therapy | Hb rises over 2–6 weeks | No role in acute anemia; transfusion or iron decisions cannot wait for it |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | High at birth (14–24 g/dL), then physiologic fall to a nadir at 2–3 months; polycythemia defined by venous Hct >65% | Use age-specific ranges; capillary and venous values differ; preterm transfusion thresholds are unit-specific |
| Children & adolescents | WHO 2024 cutoffs by age: 10.5 (6–23 months), 11.0 (2–4 yr), 11.5 (5–11 yr), 12.0 g/dL (12–14 yr) | Transfusion threshold 7 g/dL in stable critically ill children; congenital heart disease thresholds by physiology |
| Pregnancy | Plasma expansion dilutes Hb; cutoffs 11.0, 10.5 and 11.0 g/dL by trimester | Iron deficiency is the usual cause; high Hb (≥14 g/dL) is also linked to poor neonatal outcomes |
| Older adults | Adult ranges apply; anemia is common but not normal | Look for GI blood loss, CKD and marrow disease; transfuse slowly (circulatory overload risk) |
| CKD / dialysis | Low erythropoietin; chronic normocytic anemia | ESA hold points around Hb 11 g/dL; draw before dialysis, since fluid removal raises the post-run value |
| Liver disease | Bleeding varices, hypersplenism, alcohol-related macrocytosis | A falling Hb with melena or hematemesis is variceal bleeding until proven otherwise |
| Other: sickle cell disease, altitude, smoking, ancestry | Low chronic baseline in sickle cell disease; WHO publishes altitude and smoking adjustments to the cutoffs (see the guideline tables) | Compare sickle cell values with the patient's own baseline; WHO does not adjust by ancestry or race |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Draw above an IV infusion or through a line | ↓ (False −) | Dilution with IV fluid | Opposite arm, or stop the infusion and discard per policy |
| Clotted EDTA sample | ↓ or unreliable | Cells trapped in the clot | Mix gently by inversion right after the draw; redraw |
| Prolonged tourniquet | ↑ | Hemoconcentration | Release the tourniquet promptly; avoid fist pumping |
Physiologic / biologic
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Dehydration, burns | ↑ (true concentration) | Low plasma volume | Repeat after fluid replacement |
| Recent transfusion | ↑ (masks baseline) | Donor cells | Draw diagnostic labs before transfusing |
| Severe lipemia, extreme leukocytosis, paraproteins | ↑ (False +) | Turbidity in the photometric Hb measurement | Lab may correct or use an alternate method; suspect it when the MCHC is implausibly high |
| Smoking, CO exposure | ↑ (true) | Carboxyhemoglobin drives red cell production | WHO adjustment; measure COHb |
Assay & device-specific
Lab analyzers lyse the red cells and read Hb by spectrophotometry. Conductivity cartridges work it out from hematocrit, so they read low after large crystalloid or bypass dilution. Capillary photometers vary by model and by technique.
Common misinterpretations
- “Normal Hb, so not bleeding”: The early value lags. The patient's physiology does not wait for it.
- “SpO₂ 99%, so oxygen delivery is fine”: SpO₂ measures saturation, not content. Severe anemia cuts delivery even when SpO₂ reads normal.
- “Ferritin is normal, so no iron deficiency”: Ferritin climbs with inflammation. Below 15 ng/mL it confirms iron deficiency. In inflammation a higher value can hide it, so check transferrin saturation. Below 20% suggests iron deficiency.
Physiology & Test Basics
What it measures
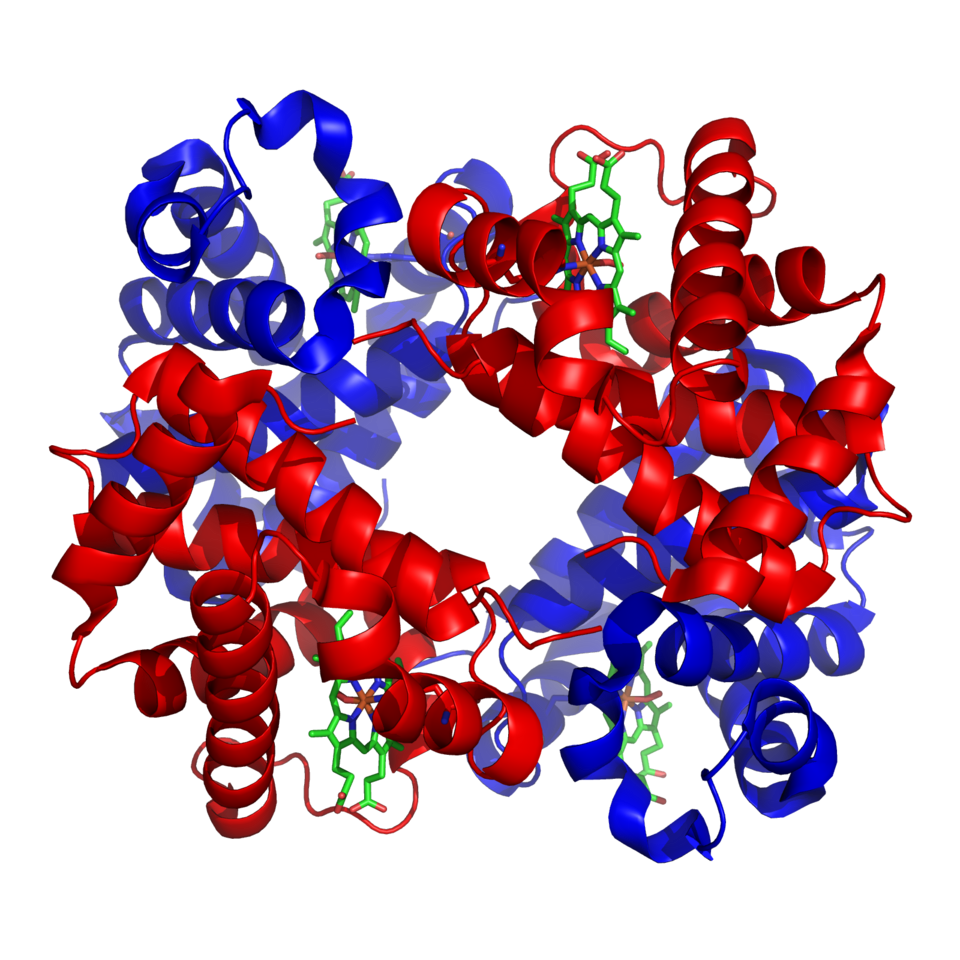
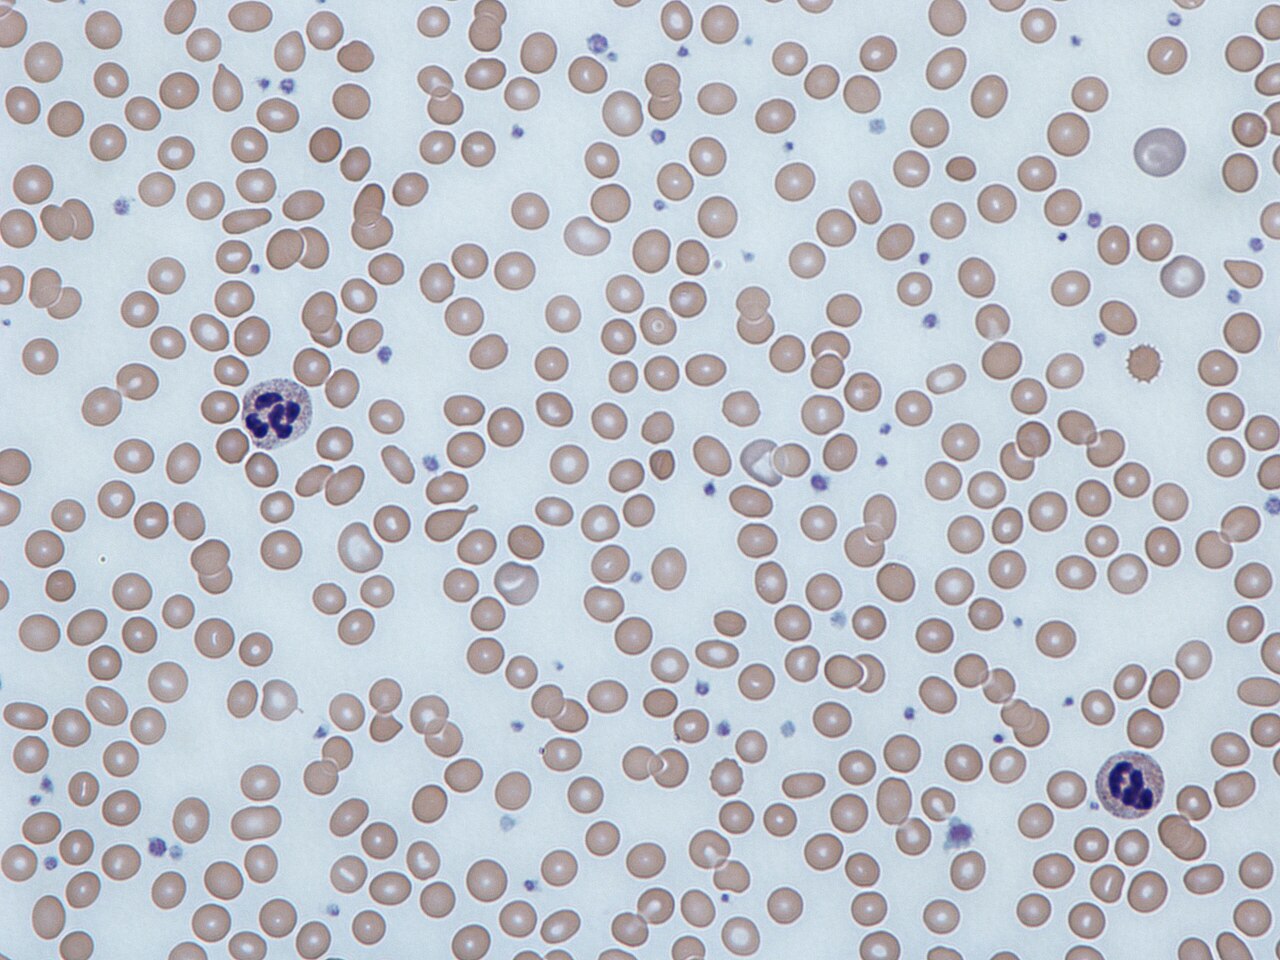
Hemoglobin (Hb, Hgb) is the iron-containing protein inside red cells. It carries oxygen from the lungs to the tissues, and some of the carbon dioxide back. The test reports its concentration in whole blood (g/dL). Hematocrit is the share of blood volume that is red cells. The RBC count is how many cells there are. Of the three, Hb is the most direct measure of oxygen-carrying capacity.
Physiology & regulation
- Structure: Four globin chains. Each carries a heme group, and the iron in each heme binds one O₂ molecule. Adult HbA is α₂β₂. HbA₂ (α₂δ₂) and fetal HbF (α₂γ₂) are minor in adults.
- Cooperative binding: Each O₂ that binds makes the next one bind more easily. That gives the sigmoid dissociation curve.
- Unloading: Acidosis, high CO₂, fever and 2,3-DPG push the curve right. That releases O₂ to the tissues.
- Production: When oxygen delivery falls, the kidney responds with erythropoietin. The marrow still needs iron, B12 and folate.
How it is measured
- Specimen: lavender top (K₂EDTA) whole blood, part of the CBC; venous is the reference; no fasting needed.
- Method: automated analyzers lyse red cells and read Hb by light absorbance; blood gas co-oximeters measure total Hb and its fractions; point-of-care photometers and noninvasive devices are less precise.
- Turnaround: minutes as part of a CBC or blood gas.
Why it matters
Hb defines anemia and erythrocytosis. It tracks blood loss over time and sets the red cell transfusion call. Read alone and early, it under-calls hemorrhage. Read as a trend, it is one of the most useful numbers in critical care. Don't read it alone.
Clinical Pearls
References
- World Health Organization. (2024). Guideline on haemoglobin cutoffs to define anaemia in individuals and populations. WHO. https://www.who.int/publications/i/item/9789240088542
- Carson, J. L., Stanworth, S. J., Guyatt, G., et al. (2023). Red blood cell transfusion: 2023 AABB international guidelines. JAMA, 330(19), 1892–1902. https://doi.org/10.1001/jama.2023.12914
- Pagano, M. B., Stanworth, S. J., Dennis, J., et al. (2025). Red cell transfusion in acute myocardial infarction: AABB international clinical practice guidelines. Annals of Internal Medicine, 178(10), 1469–1477. https://doi.org/10.7326/ANNALS-25-00706
- Rossaint, R., Afshari, A., Bouillon, B., et al. (2023). The European guideline on management of major bleeding and coagulopathy following trauma: sixth edition. Critical Care, 27(1), 80. https://doi.org/10.1186/s13054-023-04327-7
- Taccone, F. S., Rynkowski, C. B., Møller, K., et al. (2024). Restrictive vs liberal transfusion strategy in patients with acute brain injury: The TRAIN randomized clinical trial. JAMA, 332(19), 1623–1633. https://doi.org/10.1001/jama.2024.20424
- Tefferi, A., & Barbui, T. (2023). Polycythemia vera: 2024 update on diagnosis, risk-stratification, and management. American Journal of Hematology, 98(9), 1465–1487. https://doi.org/10.1002/ajh.27002
- AABB, American Red Cross, America’s Blood Centers, & Armed Services Blood Program. (2024). Circular of information for the use of human blood and blood components (June 2024). AABB. https://www.aabb.org/news-resources/resources/circular-of-information
- WOMAN Trial Collaborators. (2017). Effect of early tranexamic acid administration on mortality, hysterectomy, and other morbidities in women with post-partum haemorrhage (WOMAN). The Lancet, 389, 2105–2116. https://doi.org/10.1016/S0140-6736(17)30638-4
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.