

At a Glance
- Represents
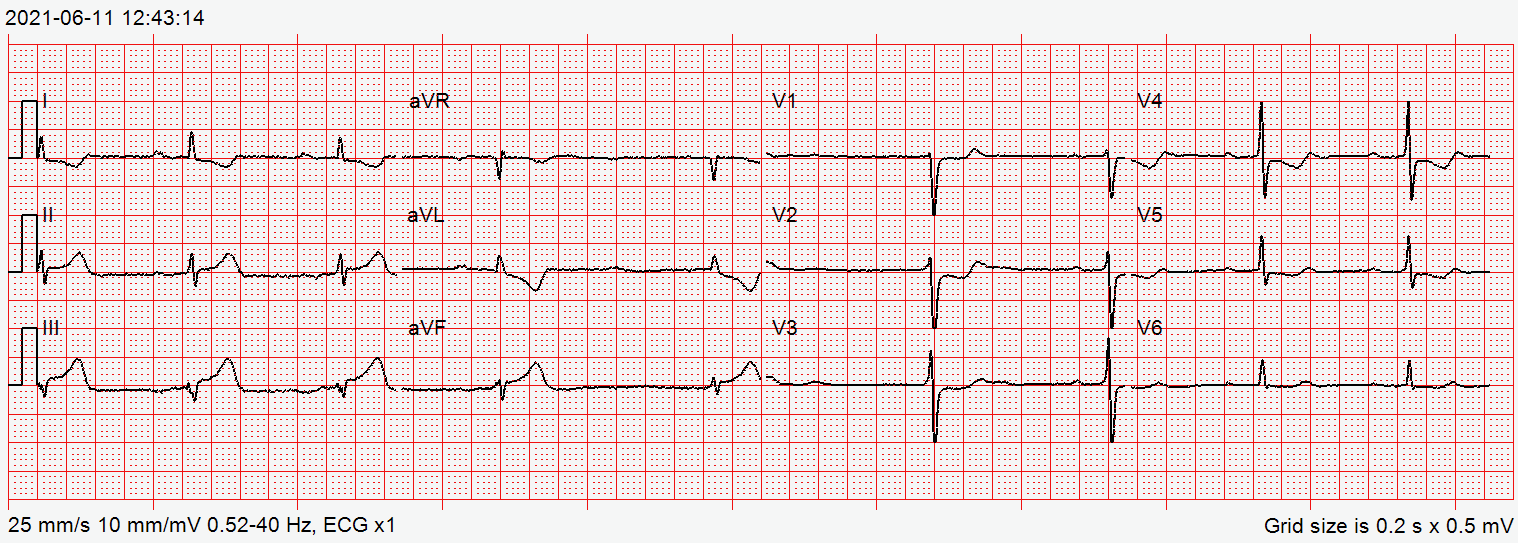
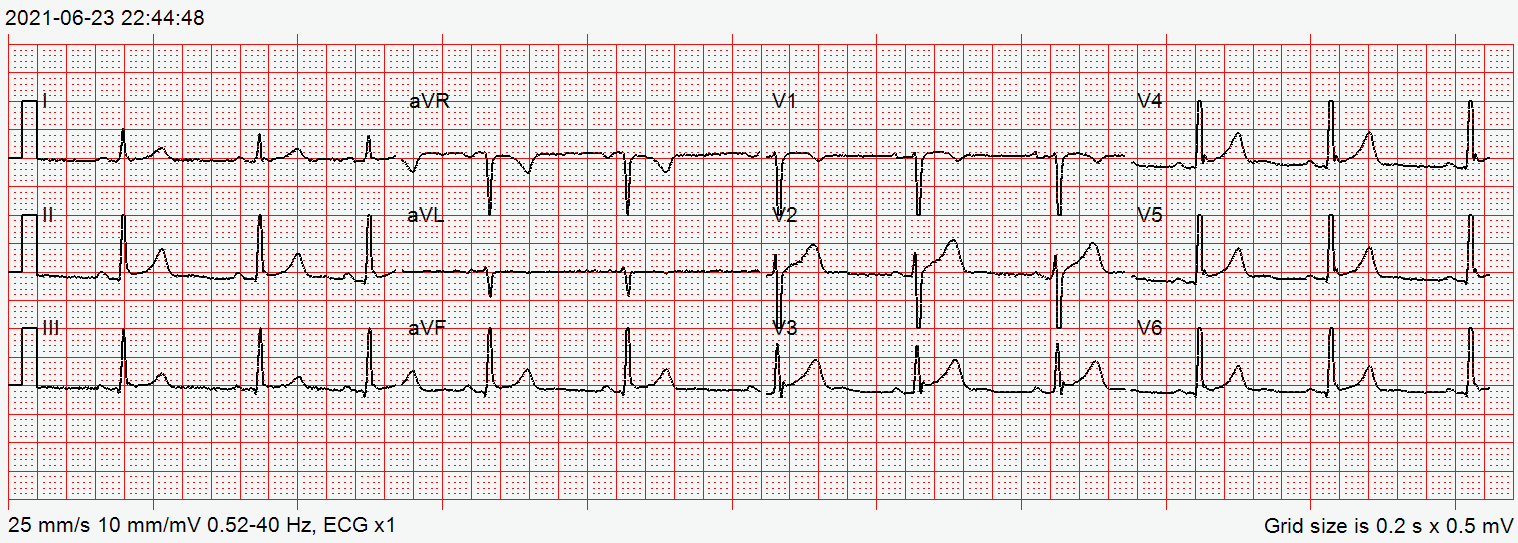
- The ST segment (J point to T start) is the plateau after the QRS. The T wave is ventricular repolarization. Deviation signals injury (elevation) or subendocardial ischemia (depression).
- Normal (Adult)
- Isoelectric at the J point; no horizontal or downsloping depression; T waves upright in I, II and V3–V6, inverted in aVR.
- Measure It
- Measure the ST deviation at the J point against the TP (or PR) baseline in each lead. Compare contiguous leads and the prior ECG.
- Abnormal → Think
- STE in contiguous leads: STEMI by territory
- Depression V1–V3: posterior MI until V7–V9 say otherwise
- STE aVR with diffuse depression: left main or multivessel disease
- Red Flags
- New STE meeting criteria or a STEMI equivalent (de Winter sign, hyperacute T, posterior pattern, Sgarbossa criteria). Do not wait for classic STE.
- Bedside Action
- Serial 12-leads every 15–30 min in ongoing symptoms; V4R and V7–V9 when indicated; notify the PCI center per protocol. Avoid stress testing in Wellens pattern.
Physiology & What It Represents
The ST segment runs from the J point, where the QRS ends, to the start of the T wave. Think of it as the plateau. In phase 2 of the ventricular action potential, every ventricular myocyte is depolarized at once. No net current flows, so the lead reads flat.
The T wave is ventricular repolarization (phase 3). That is the recovery back to resting membrane potential. Recovery is where the trouble shows up, so the ST segment and T wave react to injury, ischemia and metabolic change:
- Acute ischemia or injury: the most urgent cause of ST-T change
- Electrolytes: Potassium and calcium both reshape the T wave and the ST segment.
- Conduction and pacing: Bundle branch block and ventricular pacing change the order in which the ventricles repolarize.
- Drugs and structural disease: digoxin, pericarditis, and hypertrophy
A shifted segment is not automatically ischemic. Measure every shift from the same baseline, every time. Injury current shows as ST elevation in the leads facing the injured myocardium. Subendocardial ischemia shows as ST depression in the leads facing the non-injured wall.
Normal Values & How to Measure
| Parameter | Adult Normal | Pediatric Note | Where / How to Measure |
|---|---|---|---|
| J point and baseline | J point at the TP (or PR) baseline in most leads | Repolarization varies with age and heart rate; use age-matched norms | Mark the J point (end of QRS) and the TP baseline before judging the ST segment |
| ST elevation (ischemia) | Abnormal (STEMI): ≥1 mm at the J point in 2 contiguous leads (≥2 mm V2–V3 in men ≥40 y; ≥2.5 mm in men <40 y; ≥1.5 mm in women) | Pediatric ST elevation is usually non-ischemic; use age-based references | Read at the J point in each lead; compare with the TP baseline |
| ST depression (ischemia) | Abnormal (ischemic): ≥0.5 mm at the J point in 2 or more contiguous leads (horizontal or downsloping) | Rate-related and physiologic ST depression is more common with tachycardia | Confirm morphology and distribution; upsloping depression is less specific |
| T wave | Upright in I, II and V3–V6; inverted in aVR; variable in III, aVL and V1 | Pediatric T-wave pattern varies with age; age-based norms apply | Judge amplitude and symmetry in the same leads as the ST segment |
- Identify the J point in each lead as the end of the QRS, using a 12-lead with ECG paper at 25 mm/s.
- Set the baseline at the TP segment, or the PR segment when the TP is not usable.
- Measure the ST deviation at the J point. Some protocols also read at a fixed point after the J point (protocol-dependent).
- Compare contiguous leads to define the territory and check reciprocal depression.
- Check the shape: convex (tombstone), concave (smiley), horizontal or downsloping.
- Compare with the prior ECG and repeat the tracing when symptoms continue.
ST Elevation & STEMI Criteria
ST elevation is a current of injury. Injured muscle on the epicardial side sits at a different voltage from normal tissue during the plateau. The fourth universal definition of MI sets millimeter criteria for STEMI. Those criteria pick out who needs emergent reperfusion. They are not perfectly sensitive or specific.
ECG Criteria
- New ST elevation at the J point in 2 contiguous leads: ≥1 mm in all leads except V2–V3
- V2–V3, men ≥40 years: ≥2 mm
- V2–V3, men <40 years: ≥2.5 mm
- V2–V3, women: ≥1.5 mm
- Reciprocal ST depression: in leads opposite the territory; it adds specificity but is not always present
Causes
- Ischemic: STEMI from coronary occlusion
- Non-ischemic: acute pericarditis, early repolarization, left ventricular hypertrophy, left bundle branch block, Brugada pattern, ventricular aneurysm, and takotsubo cardiomyopathy
Clinical Significance
- Regional, convex or straight ST elevation with reciprocal depression? Treat it as STEMI until proven otherwise.
- Diffuse, concave ST elevation with no reciprocal change points to a non-ischemic cause. Chest pain plus risk factors still means you exclude ischemia.
STEMI Territories & Culprit Arteries
Elevation tells you which wall is at risk. Reciprocal depression shows the wall across from it. Localize the territory before the cath lab team asks.
| Territory | ST Elevation Leads | Reciprocal Depression | Typical Culprit |
|---|---|---|---|
| Anterior | V1–V4 | II, III, aVF | Proximal or mid LAD |
| Lateral | I, aVL, V5–V6 | III, aVF | Circumflex or first diagonal branch of the LAD |
| Inferior | II, III, aVF | I, aVL | RCA (right-dominant) or circumflex (left-dominant) |
| Posterior | V7–V9 (posterior leads) | V1–V3 (ST depression is the mirror image) | RCA or circumflex |
| Right ventricular | V3R–V6R (right-sided leads); V4R ≥0.5 mm (≥1 mm in men <30 years) | Variable | Proximal RCA |
- Inferior STEMI: Record V4R and V7–V9. You are checking for right ventricular and posterior involvement.
- Posterior STEMI: ≥0.5 mm of ST elevation in V7–V9 confirms the posterior wall. No sex or age modifier applies.
- Right ventricular infarction: ST elevation in V4R with an inferior STEMI is the sign. These patients depend on preload.
STEMI Equivalents & Occlusion MI
Not every occlusion meets the classic millimeter criteria. Some patterns point to one anyway. The 2022 ACC Expert Consensus Decision Pathway treats posterior STEMI, left bundle branch block or paced rhythm with Sgarbossa criteria, de Winter sign and hyperacute T waves as STEMI equivalents. A growing body of work on occlusion MI (OMI) says the STEMI criteria miss many occlusions. Inconclusive ECG and high suspicion? Repeat the tracings and add a posterior and right-sided lead set.
De Winter Sign
- Pattern: upsloping ST depression >1 mm at the J point in the precordial leads, with tall, prominent, symmetric T waves
- Significance: described in proximal LAD occlusion. It counts as a STEMI equivalent and can occur without ST elevation.
- Action: Activate cardiology or the cath lab right away, per protocol. Don't wait for ST elevation.
Hyperacute T Waves
- Pattern: broad, asymmetric or peaked T waves early in STEMI, often before ST elevation appears; the ECDP wording is broad, asymmetric, peaked
- Action: Repeat the ECG at short intervals. Treat it as a possible occlusion when the clinical picture agrees.
Posterior Pattern
- Standard ECG: horizontal ST depression in V1–V3, dominant R wave (R/S >1) in V2, and upright T waves in the anterior leads
- Confirmation: posterior leads V7–V9 with ST elevation ≥0.5 mm
Occlusion MI (OMI) and Non-Occlusion MI (NOMI)
- Concept: OMI is defined by the occlusion itself, not by millimeter thresholds. NOMI is injury without occlusion, and it is often diffuse.
- Bedside tools: 2026 reviews report higher sensitivity than STEMI criteria for some signs. Those signs don't yet replace guideline activation criteria.
ST Depression & NSTE Patterns
ST depression usually means subendocardial ischemia. The inner myocardium has the highest oxygen demand and the least perfusion. So it is the first to suffer. Horizontal or downsloping depression in two or more contiguous leads (≥0.5 mm at the J point) suggests ischemia.
Morphology
- Horizontal: the most specific shape for ischemia when it appears in contiguous leads.
- Downsloping: also points to ischemia, most of all with a convex ST segment.
- Upsloping: the least specific. It is common with tachycardia and digoxin effect. Use context and serial ECGs.
Causes
- NSTE-ACS: subendocardial ischemia. It is the most important cause.
- Reciprocal change: the mirror image of ST elevation when an occlusion is present.
- Posterior MI: what you see as ST depression in V1–V3 is posterior ST elevation seen from the front.
- Digoxin effect: sagging ST depression with a reverse-tick shape
- Hypokalemia and LVH strain: Read the potassium and hypertrophy pages for the detail.
- Rate-related: demand ischemia or physiologic depression with tachycardia
ST Elevation in aVR With Diffuse ST Depression
- Pattern: ST elevation in aVR with multilead ST depression in I, II, V4–V6 and no contiguous STE elsewhere
- Significance: the 2022 ECDP files this under ischemia findings, not STEMI equivalents. It most often comes from diffuse subendocardial ischemia with left main or multivessel disease.
- Threshold: ST elevation in aVR, commonly ≥1 mm, with multilead ST depression
- Action: Take the high-risk NSTE pathway. Get urgent cardiology review and serial ECGs.
Wellens Pattern
Wellens pattern is a T-wave signature of a critical proximal LAD stenosis. It shows up after recent angina, usually once the pain has settled and the ECG looks close to normal. Treat it as a high-risk NSTE finding. It is not an active occlusion. The original de Zwaan and Wellens series describes it.
ECG Criteria (2022 ECDP)
- Biphasic or deeply inverted, symmetric T waves in V2–V3 (may extend to V6)
- ST segment: isoelectric or minimally elevated (under 1 mm); troponin normal or minimally elevated
- Recent angina with pain resolved or minimal
- No pathologic Q waves in the same leads
Causes and Significance
- Cause: a critical proximal LAD stenosis. The T-wave change reflects myocardium that is reperfused but still ischemic.
- Risk: without urgent evaluation and revascularization, extensive anterior infarction is highly likely.
- Action: Get urgent cardiology review under the NSTE pathway. Don't discharge from the ED without that review.
ST Changes in LBBB & Paced Rhythm
In LBBB and ventricular paced rhythm, the ST-T changes run opposite the QRS. That is expected, and it is called discordant. Standard STEMI criteria do not apply. The modified Sgarbossa criteria were built to catch the concordant changes that suggest occlusion.
Smith-Modified Sgarbossa Criteria
- Concordant ST elevation: ≥1 mm in leads with a positive QRS
- Concordant ST depression: ≥1 mm in V1–V3
- Discordant ST elevation: ≥1 mm at the J point and ≥25% of the preceding S-wave depth
Causes and Significance
- New or presumed-new LBBB alone is not a STEMI equivalent. Apply the criteria to the tracing.
- Paced rhythm: the same criteria apply to ventricular pacing.
- Compare with a prior ECG when you have one. A previous LBBB changes how you read this tracing.
Differential Diagnosis & Mimics
Acute pericarditis and early repolarization are the main look-alikes for ST elevation. Both can clear the millimeter thresholds. Use the table below to split them from STEMI at the bedside.
| Feature | STEMI | Acute Pericarditis | Early Repolarization |
|---|---|---|---|
| ST elevation distribution | Regional (one vascular territory) | Diffuse, in most leads | Lateral or inferior leads, often symmetric |
| ST morphology | Convex (tombstone) or straight | Concave up (smiley face) | Concave up with J-point notch or slur |
| Reciprocal depression | Present in the opposite territory | Absent (except aVR) | Absent |
| PR segment | Normal; PR elevation in aVR may occur | PR depression in most leads; PR elevation in aVR | Normal |
| Q waves | May develop | Absent | Absent |
| Evolution | Rapid over hours; Q waves and T inversion | Evolves over days to weeks: ST normalizes, then T inversion may develop | Stable on serial ECGs |
Early repolarization means a J-point elevation (Jp) of ≥0.1 mV with an end-QRS notch or slur. You don't need ST elevation to meet that definition. Features that raise the risk: a J-point elevation of 0.2 mV or more, inferior or inferolateral leads, and a horizontal or descending ST segment. Pericarditis is a clinical call, with the ECG as one of several features (2015 ESC guideline).
Other STEMI Mimics
- LVH: high voltage with discordant ST elevation in V1–V3
- Brugada pattern: coved ST elevation of 2 mm or more with a negative T wave in V1–V2
- Ventricular aneurysm: persistent ST elevation with Q waves that does not evolve
- Takotsubo: wide-territory ST change after stress; a wall-motion abnormality that crosses coronary territories on echo
- Hyperkalemia: peaked, narrow-based T waves and a widening QRS. It can mimic a de Winter pattern, so check potassium.
- SAH or stroke: diffuse deep T-wave inversion with a long QT and no coronary occlusion
- Tricyclic toxicity: wide QRS with a tall R wave in aVR (3 mm or more)
Artifact & Lead Misplacement
- Limb-lead reversal: it shifts the axis and can make lead I or aVR look changed.
- Precordial electrodes placed too high: they can fake ST elevation in V1–V2.
- Tremor, shivering or motion: they can fake ST deviation and VT or VF.
- Transport vibration: it can make the baseline unreadable. Stop and re-record.
Bedside Management & Escalation
Your ECG picks the pathway. STEMI or a STEMI equivalent means reperfusion. A high-risk NSTE pattern means urgent cardiology review. Every drug and threshold below runs through local protocols and online medical direction.
| Situation | BLS (EMT) | ALS (AEMT / Paramedic / RN) | Critical Care / Transport |
|---|---|---|---|
| Unstable (hypotension, shock, pulmonary edema, ongoing pain) | Call ALS now; oxygen if SpO₂ <90% (or per local protocol); 12-lead acquisition and transmission where allowed | 12-lead; notify the PCI center; IV access; hold nitrates if SBP <90 mmHg or 30 mmHg or more below baseline; treat per protocol | Continuous monitoring; serial 12-leads; transport to a PCI-capable center; manage shock |
| Stable with ischemic-pattern ST change | 12-lead acquisition and transmission where allowed; oxygen if SpO₂ <90% (or per local protocol); notify ALS | 12-lead; aspirin 162–325 mg chewed and nitroglycerin per protocol; repeat the 12-lead; notify the receiving center | Serial 12-leads every 15–30 min in ongoing symptoms; cath lab team on arrival |
| Pulseless or in arrest | Start CPR and use the AED; a 12-lead does not delay CPR or shocks | Follow the cardiac arrest protocol; treat the rhythm | Post-ROSC 12-lead; reperfusion decision per protocol |
| Therapy | Adult | Pediatric | Key Notes |
|---|---|---|---|
| Aspirin (suspected ACS) | 162–325 mg PO loading dose, chewed (non-enteric-coated tablet) | Not established for ACS in children: specialist use only | Give unless truly allergic or actively bleeding; chewing speeds absorption |
| Nitroglycerin (chest pain) | ACS: 0.4 mg SL every 5 min, max 3 doses (nitroglycerin) | Not established in children: specialist use only | Contraindicated with PDE-5 inhibitors: avanafil within 12 h, sildenafil or vardenafil within 24 h, tadalafil within 48 h; also contraindicated with riociguat. Hold for SBP <90 mmHg or 30 mmHg or more below baseline, and in suspected RV infarction; heart-rate limits per protocol |
| Morphine (pain unrelieved by nitrates) | 2.5–5 mg IV every 10 min, titrate to effect (morphine) | Off-label: 0.05–0.1 mg/kg IV/IO/IM slowly (max initial 10 mg; some protocols 2 mg/dose); specialist direction in ACS | High-alert Opioid for pain that persists after nitrates and other anti-ischemic therapy; may delay oral P2Y12 absorption; avoid with hypotension or RV infarction; watch respiratory rate and BP |
| Unfractionated heparin (ACS) | 60 units/kg IV bolus (max 4,000 units), then 12 units/kg/hr (max 1,000 units/hr) (heparin) | Not established for ACS in children: specialist use only | High-alert Anticoagulant; follow the protocol and the cath lab plan |
| Clopidogrel (P2Y12 inhibitor) | ACS: 300–600 mg PO load (600 mg before PCI), then 75 mg daily. With fibrinolysis: 300 mg load if age 75 or younger; 75 mg with no load if older than 75 (clopidogrel) | Not established in children: specialist or medical-control use only | Agent and timing set by the cath lab and protocol; with a lytic, use the fibrinolysis dose (no 600 mg load) |
| Tenecteplase (STEMI, PCI >120 min away) | 30–50 mg IV single bolus by weight band; at age 75 or older bleeding risk is higher and some protocols reduce the dose, so confirm locally (fibrinolytics) | Systemic lytics not established in children | High-alert Give when FMC-to-device time is expected to exceed 120 min. Absolute contraindications include prior intracranial hemorrhage, known intracranial neoplasm or AVM, ischemic stroke within 3 months, active bleeding and suspected aortic dissection. Heparin adjunct per protocol. Follow local transfer protocol |
| Oxygen | Give for SpO₂ below 90%; no routine oxygen when SpO₂ is normal; 88–92% if hypercapnia risk (oxygen) | Titrate to age-specific target | Avoid hyperoxia (SpO₂ above 98%, or above 92% with hypercapnia risk). Some EMS protocols still use a 94% threshold; follow local protocol |
Doses vary by protocol; follow local protocols and medical direction.
Pediatric & Special Populations
Pediatrics
- Pattern: Repolarization changes shift with age and heart rate. Use age-based pediatric ECG references.
- Cause: In children, ST changes are more often non-ischemic (myocarditis, pericarditis, early repolarization). Ischemia is uncommon. When it is suspected, think about coronary anomalies and Kawasaki-related coronary disease.
- Action: Call pediatric cardiology or medical direction early for a new ST change with symptoms. For rate and BP norms, see the pediatric vital signs reference.
- Drugs: Pediatric dosing for nitrates, fibrinolytics and antiplatelet agents is not established. Use the weight-based dosing reference and specialist input.
Other Populations
- Older adults and women: often present atypically. ST depression may be the only finding.
- Pacemaker or ICD: paced rhythms call for the Sgarbossa criteria. Get a prior ECG to compare.
- Heart transplant: denervated hearts can show abnormal ST-T patterns and blunted symptoms. Compare with prior tracings.
- Pregnancy: ST-T changes can be normal in pregnancy. A true STEMI in pregnancy or the peripartum period is often spontaneous coronary artery dissection (SCAD). Fibrinolysis is generally avoided. It can extend the dissection, so PCI or conservative therapy is preferred. Bring in cardiology, obstetrics and the PCI center early. Follow medical direction for antithrombotics.
Monitoring & Transport Considerations
| Issue | What to Do |
|---|---|
| Monitoring lead | Use the lead that shows the abnormality on the 12-lead; V2–V5 are common choices for anterior and lateral ischemia |
| Serial 12-leads | Repeat every 15–30 min in ongoing chest pain or symptoms, and transmit each tracing where allowed |
| Prehospital 12-lead | Obtain and transmit the 12-lead early; the guideline target is an ECG within 10 min of first medical contact, with pre-arrival notification to the PCI center |
| Posterior and right-sided leads | V7–V9 for suspected posterior MI; V4R for suspected RV infarction in inferior STEMI |
| Artifact | Stop, check electrodes and limb placement, and re-record before acting on an ST change from vibration or shivering |
| Transport ECG | Place limb electrodes on the torso to limit movement artifact, and record with the patient still where possible |
| Before moving an unstable patient | Place anterior-posterior pads for transcutaneous pacing or defibrillation when bradycardia or unstable tachycardia is present |
| Arrhythmia surveillance | Continuous rhythm monitoring with defibrillation readiness; treat VF or pulseless VT per the arrest protocol |
Quiet the stretcher and cut the motion before you record. In transport, a clean tracing is the only reliable input for a diagnosis.
Step-by-Step Approach & Pitfalls
- Identify the J point and TP baseline in each lead before reading any shape.
- Measure the ST deviation at the J point and note its shape: convex, concave, horizontal or downsloping.
- Map the distribution to a territory, and check reciprocal leads.
- Check the STEMI equivalents: de Winter sign, hyperacute T waves, posterior ST depression, Sgarbossa criteria in LBBB or paced rhythm.
- Check the mimics: diffuse concave STE with PR depression (pericarditis), early repolarization, LVH, and artifact.
- Decide the pathway: STEMI or equivalent to reperfusion; high-risk NSTE (STE in aVR with diffuse depression, Wellens) to urgent cardiology review.
- Repeat and compare: serial ECGs and the prior tracing, and document each change with a time stamp.
Common Pitfalls
- Don't wait for classic ST elevation when a de Winter sign or posterior pattern is present.
- Don't label isolated V1–V3 ST depression as NSTEMI without posterior leads.
- Don't use STEMI thresholds in LBBB or a paced rhythm. Use the Sgarbossa criteria.
- Don't give nitrates to a hypotensive patient with inferior changes without checking V4R.
- Don't order an exercise stress test for a Wellens pattern.
ECG Examples
Clinical Pearls
References
- Rao SV, O'Donoghue ML, Ruel M, et al. 2025 ACC/AHA/ACEP/NAEMSP/SCAI guideline for the management of patients with acute coronary syndromes. J Am Coll Cardiol. 2025;85(22):2135-2237. https://doi.org/10.1016/j.jacc.2024.11.009
- Thygesen K, Alpert JS, Jaffe AS, et al. Fourth universal definition of myocardial infarction (2018). Circulation. 2018;138(20):e618-e651. https://doi.org/10.1161/CIR.0000000000000617
- Kontos MC, de Lemos JA, Deitelzweig SB, et al. 2022 ACC Expert Consensus Decision Pathway on the evaluation and disposition of acute chest pain in the emergency department. J Am Coll Cardiol. 2022;80(20):1925-1960. https://doi.org/10.1016/j.jacc.2022.08.750
- de Winter RJ, Verouden NJ, Wellens HJ, Wilde AA. A new ECG sign of proximal LAD occlusion. N Engl J Med. 2008;359(19):2071-2073. https://doi.org/10.1056/NEJMc0804737
- de Zwaan C, Bär FW, Wellens HJ. Characteristic electrocardiographic pattern indicating a critical stenosis high in left anterior descending coronary artery in patients admitted because of impending myocardial infarction. Am Heart J. 1982;103:730-736 (landmark study). https://doi.org/10.1016/0002-8703(82)90480-x
- Smith SW, Dodd KW, Henry TD, Dvorak DM, Pearce LA. Diagnosis of ST-elevation myocardial infarction in the presence of left bundle branch block with the ST-elevation to S-wave ratio in a modified Sgarbossa rule. Ann Emerg Med. 2012;60(6):766-776. https://doi.org/10.1016/j.annemergmed.2012.07.119
- Macfarlane PW, Antzelevitch C, Haissaguerre M, et al. The early repolarization pattern: a consensus paper. J Am Coll Cardiol. 2015;66(4):470-477. https://doi.org/10.1016/j.jacc.2015.05.033
- Adler Y, Charron P, Imazio M, et al. 2015 ESC guidelines for the diagnosis and management of pericardial diseases. Eur Heart J. 2015;36(42):2921-2964. https://doi.org/10.1093/eurheartj/ehv318
- McLaren JTT, Nunes de Alencar J, Smith SW. Diagnosis of occlusion myocardial infarction. Curr Opin Crit Care. 2026;32(3):230-238. https://doi.org/10.1097/MCC.0000000000001359
- Hayes SN, et al. Spontaneous coronary artery dissection: current state of the science. A scientific statement from the American Heart Association. Circulation. 2018;137(19). https://doi.org/10.1161/CIR.0000000000000564
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.