

At a Glance
- Covers
- PVCs, monomorphic and polymorphic VT, torsades, VF, asystole and PEA, escape rhythms and AIVR, and paced rhythms.
- Recognize It
- Wide QRS (≥120 ms) with no related P wave. VT: three or more beats over 100 bpm, with AV dissociation and capture or fusion beats.
- Most Dangerous
- VF and pulseless VT: no output. Torsades: polymorphic VT with a long QT, which can self-terminate or degenerate to VF.
- Unstable Patient
- Pulse with hypotension, altered mental status, chest pain or heart failure: synchronized cardioversion for monomorphic VT (100 J); polymorphic VT or torsades: unsynchronized defibrillation. No pulse: CPR, defibrillation, epinephrine.
- Stable Patient
- Monomorphic VT with a pulse and adequate perfusion: amiodarone, procainamide or sotalol may be considered (COR 2b), with cardiology input. Cardiovert if VT persists or drugs fail (COR 1).
- Do Not
- Give QT-prolonging antiarrhythmics for torsades. Give verapamil or diltiazem to wide-complex tachycardia (COR 3: Harm). Suppress an escape rhythm.
Physiology & What It Represents
The impulse starts below the bundle of His, in the bundle branches, the Purkinje network or the ventricular myocardium. It skips the normal road, so the QRS is wide (≥120 ms) and looks different from a sinus beat. Normal conduction goes from the SA node through the atria and AV node, then the His-Purkinje system to the ventricles.
Three mechanisms drive ventricular arrhythmias. Enhanced automaticity throws ectopic beats and escape rhythms. Triggered activity, from early afterdepolarizations in a prolonged QT, starts torsades de pointes (TdP). Re-entry around scar, most often from a prior MI, drives most sustained monomorphic VT. Escape rhythms take over when faster pacemakers fail. Ventricular escape runs at about 20–40 bpm. Accelerated idioventricular rhythm (AIVR) runs at about 40–100 bpm.
Recognition Approach
| Rhythm | Rate (bpm) | Regularity | P Waves | PR | QRS | First-Line Action |
|---|---|---|---|---|---|---|
| PVC | Underlying rate | Irregular beat | None related | — | Wide (≥120 ms) | Check electrolytes and ischemia; no drug if asymptomatic |
| Monomorphic VT | >100 | Regular | May dissociate | — | Wide, uniform | Unstable: synchronized cardioversion (100 J). Stable: an antiarrhythmic (COR 2b); synchronized cardioversion if VT persists or drugs fail (COR 1). Adenosine only if the cause of a regular WCT cannot be determined (COR 2b); it will not terminate VT |
| Polymorphic VT / TdP | >100 | Irregular | Usually not seen | — | Wide, twisting axis | Unstable or sustained: unsynchronized defibrillation (COR 1); stop QT-prolonging drugs; recurrent TdP with long QT: magnesium may be considered (COR 2b); overdrive pacing (isoproterenol only for acquired, pause-dependent TdP) |
| VF | None organized | Chaotic | None | — | None identifiable | CPR and unsynchronized defibrillation |
| Asystole / PEA | None (asystole) or organized (PEA) | — | Variable | Variable | Variable | CPR, epinephrine, reversible causes |
| Ventricular escape | 20–40 | Regular | None related | — | Wide | Treat the cause; pace if symptomatic |
| AIVR | 40–100 | Regular | None related | — | Wide, regular | Observe; do not suppress |
| Paced ventricular rhythm | Pacemaker rate | Regular | Per pacing mode | — | Wide, after a pacing spike | Confirm capture by pulse and SpO₂ waveform |
- Rate: Count the QRS complexes in a 6-second strip and multiply by 10.
- Regularity: Decide whether the R-R intervals are regular, irregular or regularly irregular.
- P waves: Find P waves in lead II and check for AV dissociation.
- QRS width: Measure in the widest lead. Narrow is under 120 ms; wide is 120 ms or more.
- Morphology: Decide whether the QRS shape is uniform (monomorphic) or changing (polymorphic), and measure the QT.
- Stability: Check pulse, blood pressure, mental status, chest pain and heart failure before choosing treatment.
Normal Conduction Values
| Parameter | Normal | Note |
|---|---|---|
| QRS | ≤110 ms | 110–119 ms is incomplete BBB or nonspecific IVCD; ≥120 ms is wide |
| PR | 120–200 ms (0.12–0.20 s; 3–5 small boxes) | Not applicable to a ventricular rhythm; used to exclude AV conduction |
| Escape rates | Junctional 40–60; ventricular 20–40 bpm | Slower escape means higher risk of asystole |
Premature Ventricular Complexes (PVCs)
A PVC is an early beat that starts in the ventricles. It is wide, no P wave comes before it, and a pause follows. PVCs are common, even in healthy adults. They increase with age, stress, stimulants, electrolyte shifts and structural heart disease.
ECG Criteria
- Wide QRS (≥120 ms): bizarre shape, unlike the sinus beats
- No related P wave: any P wave is buried in the QRS or does not link to it
- Discordant T wave: the T wave opposes the main QRS deflection
- Compensatory pause: the PVC plus the following pause equals two normal R-R intervals
Patterns
| Term | Definition | Why It Matters |
|---|---|---|
| Unifocal | All PVCs share one morphology | Usually more benign |
| Multifocal | Two or more PVC morphologies | Suggests irritable or diseased myocardium |
| Bigeminy / trigeminy | Every second or third beat is a PVC | Can reduce stroke volume and pulse pressure |
| Couplet / triplet | Two or three consecutive PVCs | Three or more at over 100 bpm is NSVT |
| R-on-T | PVC falls on the T wave of the prior beat | Can trigger VT or VF in the vulnerable window |
Clinical Significance
- A lone PVC in a structurally normal heart is usually benign.
- Look harder at multifocal PVCs, couplets, NSVT or R-on-T beats. Each one raises concern for ischemia, scar or irritable myocardium.
- A high PVC burden on 24-hour Holter can cause a reversible cardiomyopathy. Once ablation works, ejection fraction often improves.
- Palpitations, presyncope or poor exercise tolerance need evaluation. Reassurance alone is not enough.
- Still symptomatic after the workup? The options are a beta-blocker, a non-dihydropyridine calcium channel blocker or ablation, per cardiology.
Look-Alikes
- An aberrantly conducted supraventricular beat (see Differential Diagnosis & Mimics)
Monomorphic Ventricular Tachycardia
Three or more ventricular beats in a row, faster than 100 bpm, all with one QRS shape: that is monomorphic VT. Most of it traces back to a re-entry circuit around myocardial scar. Sustained means it lasts 30 seconds or more, or it makes the patient unstable. Non-sustained VT (NSVT) quits on its own before 30 seconds.
ECG Criteria
- Regular wide-complex tachycardia with uniform QRS morphology
- AV dissociation: P waves march through the QRS at their own rate. This finding favors VT.
- Capture beats: an occasional narrow QRS where a sinus impulse conducts normally
- Fusion beats: a QRS between the sinus and ventricular morphologies
Causes
- Prior MI with scar, the most common cause
- Non-ischemic cardiomyopathy and infiltrative disease
- Electrolyte shifts, mainly low potassium or magnesium
- Drug toxicity, including digoxin and sympathomimetics
Clinical Significance
- Any moment, it can slide into VF. A pulse with instability is an emergency.
- Stability makes the call, not the ECG alone. Unstable wide-complex tachycardia gets synchronized cardioversion (2025 AHA Part 9, COR 1, LOE B-NR). Stable wide-complex tachycardia gets it too once it persists after vagal maneuvers or drugs, or when drugs are ineffective or contraindicated (COR 1, LOE B-NR).
- Stable monomorphic VT: amiodarone, procainamide or sotalol may be considered (2025 AHA Part 9, COR 2b, LOE B-R). Keep verapamil and diltiazem out of wide-complex tachycardia. They should not be given there (COR 3: Harm, LOE B-NR).
- With NSVT, work up structural heart disease: echocardiogram, ischemia, cardiomyopathy. Whether the patient is an ICD candidate turns on the cause and the ejection fraction, per cardiology.
Polymorphic VT and Torsades de Pointes
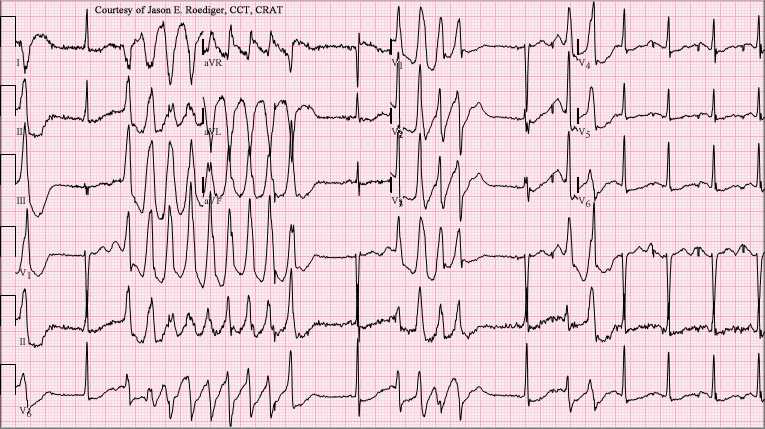
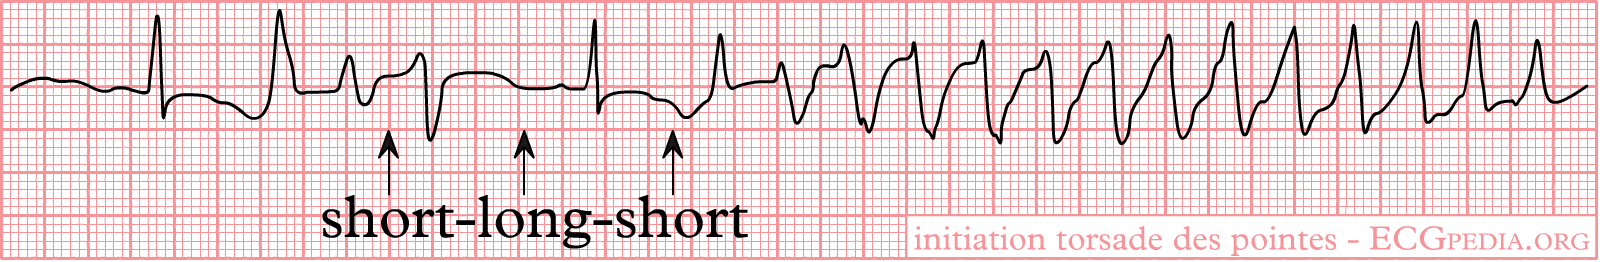
Polymorphic VT has a QRS shape that keeps changing. With a normal QT, assume acute ischemia until proven otherwise. The alternatives are channelopathies: Brugada syndrome, CPVT and early repolarization. Prolonged QT? Then the rhythm is torsades de pointes (TdP), meaning "twisting of the points." The QRS axis swings around the baseline in bursts. TdP often stops on its own, but it can degenerate to VF.
ECG Criteria
- Polymorphic QRS: changing amplitude and axis, with a twisting pattern
- Long QT before the run: QTc ≥500 ms or a rise of 60 ms or more from baseline is high risk
- Short-long-short sequence: a PVC, a long pause, then a second PVC on the T wave starts the run
Causes
- Drugs (most common acquired cause): antiarrhythmics such as sotalol, procainamide, amiodarone and dofetilide; macrolide and fluoroquinolone antibiotics; haloperidol, droperidol and ziprasidone; ondansetron and methadone
- Electrolytes: hypokalemia, hypomagnesemia, hypocalcemia
- Bradycardia or pauses: slow rates lengthen the QT
- Congenital long QT syndrome: ion channel disorders
- CNS events: subarachnoid hemorrhage and stroke
Clinical Significance
- Pulseless TdP gets treated like VF. That means CPR and unsynchronized defibrillation.
- Sustained polymorphic VT with a pulse gets an immediate unsynchronized shock at the maximum setting (2025 AHA Part 9, COR 1, LOE B-NR). The QRS changes beat to beat, so it cannot be reliably synchronized. Synchronized cardioversion is for monomorphic VT.
- Recurrent TdP with a pulse: magnesium may be considered (2025 AHA Part 9, COR 2b, LOE C-LD). Pair it with correcting potassium and magnesium, removing the offending drugs and overdrive pacing. Pause-precipitated torsades goes to expert consultation for overdrive pacing or isoproterenol, per 2025 AHA Part 9. Isoproterenol is a bridge only for acquired, pause-dependent TdP. Avoid it in congenital long QT syndrome. Beta-agonists can provoke TdP there, and beta-blockade is the mainstay.
- Polymorphic VT with a normal QT is ischemia until shown otherwise. Get a 12-lead, activate cardiology or the cath lab, and give a beta-blocker unless it is contraindicated. Antiarrhythmics go per cardiology. Routine magnesium is not recommended with a normal QT (2025 AHA Part 9, COR 3: No Benefit, LOE C-LD). For recurrences, lidocaine or amiodarone may be considered (COR 2b, LOE C-LD).
Ventricular Fibrillation (VF)
Ventricular fibrillation is chaos in the ventricles. Nothing contracts effectively, so there is no cardiac output. In a witnessed out-of-hospital cardiac arrest from cardiac causes, it is the most common initial rhythm.
ECG Criteria
- Chaotic undulations: no identifiable QRS, ST or T waves and no organized pattern
- Coarse VF: higher amplitude; more likely to be a recent arrest and to respond to defibrillation
- Fine VF: low amplitude; a longer arrest with a more depleted myocardium
Causes
- Acute ischemia or infarction, the most common cause
- Severe hyperkalemia or hypokalemia, and hypomagnesemia
- Hypothermia, electrocution, lightning strike and commotio cordis
- Channelopathies such as Brugada syndrome and long QT syndrome
- Drug toxicity, including digoxin, cocaine and sympathomimetics
Clinical Significance
- No pulse with VF, ever. Start CPR and defibrillate as soon as possible.
- Hunt the reversible causes, the H's and T's, while CPR and shocks continue.
- Severe hypothermia can make defibrillation fail. If shocks fail, put rewarming first, per local protocol.
Asystole and PEA
Asystole means no ventricular electrical activity at all. Pulseless electrical activity (PEA) shows organized electrical activity on the monitor, with no palpable pulse and no effective output. Neither is a shockable rhythm.
ECG Criteria
- Asystole: a flat line in at least two leads, after checking leads and gain
- PEA: organized QRS complexes, often slow or wide, with no pulse
Causes
- Hypoxia, hypovolemia, acidosis, hyper- or hypokalemia, hypothermia (H's)
- Tension pneumothorax, tamponade, toxins, thrombosis (T's)
Clinical Significance
- Management is CPR, epinephrine 1 mg IV/IO every 3–5 min given as soon as feasible (2025 AHA Part 9, COR 2a, B-R for dose; COR 2a, B-NR for timing), and a search for the reversible cause. See Cardiac Arrest Rhythms for the arrest algorithm.
- Before arrest, a slow or wide escape rhythm warns you the failure is progressing.
Look-Alikes
- Fine VF, lead misplacement or artifact (see Differential Diagnosis & Mimics)
Ventricular Escape & AIVR
Once the SA and AV nodes fail, the ventricles start their own beat. A ventricular escape rhythm runs at 20–40 bpm. Accelerated idioventricular rhythm (AIVR) runs at 40–100 bpm, quicker than escape but slower than VT. Both come out wide and regular.
ECG Criteria
- Escape: wide QRS at 20–40 bpm, often with complete heart block or sinus arrest
- AIVR: wide, regular, monomorphic QRS at 40–100 bpm, with a gradual onset and offset
Causes
- Escape: complete heart block, sinus arrest, late-stage bradycardia
- AIVR: reperfusion after thrombolysis or PCI, digoxin toxicity, myocarditis, post-cardiac surgery
Clinical Significance
- AIVR is usually well tolerated. It tends to burn out without treatment.
- In digoxin toxicity, reach for digoxin immune fab. Skip cardioversion where you can, since it can tip the patient into VF.
- Often that escape beat is all the output the patient has. Fix the cause and pace if needed.
Paced Ventricular Rhythms & Pacemaker Malfunction
Expect a pacing spike, then a wide QRS, in a paced ventricular rhythm. Seeing this is normal with a pacemaker, or during transcutaneous or transvenous pacing. The spike itself is not a QRS. What matters is whether it captures the ventricle.
ECG Criteria
- Capture: a spike followed by a wide QRS at the set rate
- Failure to capture: a spike with no following QRS
- Failure to sense: pacing spikes fall on native QRS complexes
Causes
- Lead dislodgement, fibrosis or threshold rise
- Low battery, wrong mode or output setting
- Electrolyte shifts that raise threshold, such as hyperkalemia or acidosis
Clinical Significance
- Don't trust the monitor by itself. Use the pulse and SpO₂ waveform to confirm capture.
- Transcutaneous pacing: see Transcutaneous Pacing.
Differential Diagnosis & Mimics
| Feature | Favors VT | Favors SVT with Aberrancy |
|---|---|---|
| AV dissociation | Present; P waves independent of QRS | Absent; 1:1 P to QRS relationship |
| Capture or fusion beats | Present; diagnostic of VT | Absent |
| QRS width and shape | Very wide QRS; atypical bundle branch morphology | Narrower or typical bundle branch block pattern |
| Precordial concordance | All precordial leads point the same direction | Normal R-wave progression |
| History | Prior MI, cardiomyopathy, structural disease | Young, known bundle branch block or prior SVT |
For precordial patterns, use the Brugada stepwise algorithm (a landmark derivation paper). The absence of an RS complex in all precordial leads, an R-to-S interval over 100 ms, and AV dissociation and morphology in V1–V2 and V6 all point to VT. When the diagnosis is uncertain, treat the wide-complex tachycardia as VT. Morphology supports the call but does not confirm it. The separate page Wide-Complex Tachycardia goes deeper.
Some wide-complex rhythms are not VT, and they need different treatment. Hyperkalemia, sodium-channel blocker or tricyclic toxicity, and paced rhythms can all draw a wide, sometimes sine-wave pattern. Check the history, the medications, the potassium and the paced rhythm. Calcium, bicarbonate or pacing may be indicated.
Artifact & Lead Misplacement
- Limb lead reversal: flips the axis, such as an inverted P or QRS in lead I, or a false bradycardia pattern
- Precordial misplacement: moves the R-wave progression and can mimic a prior MI or hypertrophy
- Motion or shivering: can pass for VF or VT. Check the pulse and SpO₂ waveform.
- Transport vibration: a rhythmic baseline that can pass for a ventricular rhythm
Normal Variants
- Isolated interpolated PVCs. They drop in between normal sinus beats, with no pause
Bedside Management & Escalation
Start with stability, then look at the rhythm. Adult and pediatric starting doses follow. They come from the FDA labels and the AHA algorithms. No source gives a pediatric dose? The table says so.
Stability Table
| Situation | BLS (EMT) | ALS (AEMT / Paramedic / RN) | Critical Care / Transport |
|---|---|---|---|
| Unstable with pulse | Oxygen if SpO₂ <94%; monitor; early ALS; notify | Synchronized cardioversion for monomorphic VT; unsynchronized defibrillation for polymorphic VT or torsades; sedate if time allows; if synchronization is delayed and the patient is critical, shock unsynchronized (2025 AHA Electrical Cardioversion algorithm) | Pacing pads on; cardioversion (monomorphic VT) with sedation as time allows; unsynchronized shock for polymorphic VT or torsades; antiarrhythmic infusion; 12-lead |
| Stable with pulse | Oxygen if SpO₂ <94%; monitor; 12-lead where allowed | 12-lead; look for ischemia and electrolytes; amiodarone, procainamide or sotalol may be considered (COR 2b); adenosine may be considered only if a regular WCT's cause cannot be determined (COR 2b; it will not terminate VT); cardiovert if VT persists or drugs fail (COR 1) | Continuous monitoring; repeat 12-lead; QTc check; cardiology input |
| Pulseless VT / VF | CPR; AED shock immediately | CPR; defibrillate; epinephrine; amiodarone or lidocaine; reversible causes | As ALS, plus advanced airway and a search for the cause |
Therapy Table
| Therapy | Adult | Pediatric | Key Notes |
|---|---|---|---|
| Synchronized cardioversion (VT with pulse) | 100 J synchronized for monomorphic VT only (2025 AHA Electrical Cardioversion algorithm); escalate per device | 0.5–1 J/kg, then 2 J/kg if the first shock fails | If the rhythm is uncertain, treat as VT. See Cardioversion |
| Defibrillation (pulseless VT / VF) | 120–200 J biphasic (device dose); 360 J monophasic | 2 J/kg, then 4 J/kg; subsequent shocks at least 4 J/kg, up to 10 J/kg or the adult dose (2025 AHA PALS cardiac arrest algorithm) | Unsynchronized. Do not synchronize for VF, pulseless VT, or polymorphic VT or torsades (with or without a pulse); polymorphic VT takes the maximum setting (2025 AHA Part 9, COR 1) |
| Amiodarone (shock-refractory VF / pulseless VT) | 300 mg IV/IO push, then 150 mg (2025 AHA ACLS cardiac arrest algorithm; 450 mg total) | 5 mg/kg IV/IO bolus (max 300 mg), may repeat up to 3 doses; later doses max 150 mg (2025 AHA PALS cardiac arrest algorithm) | High-alert Differs from FDA label: the label gives 150 mg over 10 min for breakthrough VF or hemodynamically unstable VT, then about 1000 mg over the first 24 hours; the 300 mg then 150 mg arrest bolus is the 2025 AHA ACLS cardiac arrest algorithm dose. Lidocaine is an alternative. Antiarrhythmics may be considered for VF or pulseless VT unresponsive to defibrillation (2025 AHA Part 9, COR 2b, LOE B-R); not routine. See Amiodarone |
| Amiodarone (VT with pulse) | 150 mg IV over 10 min, then 1 mg/min for 6 hr, then 0.5 mg/min (FDA label; first dose matches the 2025 AHA ACLS tachyarrhythmia algorithm) | Not established in children in the 2025 AHA PALS tachyarrhythmia algorithm; expert consultation before antiarrhythmics (specialist use only) | High-alert Do not exceed 30 mg/min. Not for torsades or pre-excited AF |
| Lidocaine (alternative for refractory VF / pulseless VT) | 1–1.5 mg/kg IV/IO first dose, then 0.5–0.75 mg/kg (2025 AHA ACLS cardiac arrest algorithm) | 1 mg/kg IV/IO (2025 AHA PALS cardiac arrest algorithm); further doses and infusion per cardiology | High-alert Avoid in WPW and complete heart block without a pacemaker. See Lidocaine |
| Procainamide (stable monomorphic VT, specialist) | 20–50 mg/min IV infusion until the arrhythmia is suppressed, hypotension occurs, QRS widens over 50%, or 17 mg/kg is given (2025 AHA ACLS tachyarrhythmia algorithm); infuse no faster than 50 mg/min (2025 AHA Part 9) | 15 mg/kg IV/IO over 30–60 min (specialist-directed; the 2025 PALS algorithm lists no procainamide dose) | High-alert Differs from FDA label: the label caps the loading dose at 1 g. Contraindicated: complete heart block, torsades (label: Group 1A drugs), systemic lupus (positive ANA). Avoid with prolonged QT and in heart failure. See Procainamide |
| Magnesium sulfate (recurrent torsades with a long QT) | 2 g IV, diluted, may repeat (2025 AHA Part 9, COR 2b, LOE C-LD). Infusion time: the 2025 statement gives none; the NASEMSO house position is 1–2 min for a pulseless or unstable patient (source not re-verified). Not for routine use in cardiac arrest (COR 3: No Benefit, LOE B-R) | 25–50 mg/kg IV/IO, diluted (max 2 g). Not given in the 2025 PALS algorithms; dose per NASEMSO National Model EMS Clinical Guidelines v3.0 (2022), the approved pediatric source for drugs the AHA does not dose. No faster than 150 mg/min (label). Adult infusion times do not apply | High-alert Differs from FDA label: torsades is not a labeled indication, and the label limits direct IV injection to 150 mg/min (about 13 min for 2 g), slower than the 1–2 min arrest infusion. Magnesium may be considered for recurrent TdP with a long QT, even with a normal serum magnesium (2025 AHA Part 9, COR 2b, LOE C-LD). Dilute before IV use. See Magnesium Sulfate |
| Isoproterenol (torsades bridge to pacing) | 0.5–5 mcg/min IV, titrated to the heart rate that stops pauses (off-label; the labeled shock range) | Pediatric cardiology directed | Acquired, pause-dependent torsades with a pulse only, as a bridge to pacing, with expert consultation (2025 AHA Part 9). Avoid in congenital long QT syndrome (can provoke TdP) and with ischemia or structural heart disease. Differs from FDA label: the label contraindicates ventricular arrhythmias. See Isoproterenol |
| Overdrive pacing (torsades) | Pacing above 70 bpm (AHA/ACCF 2010 torsades statement), transcutaneous or transvenous | Per pediatric cardiology | Pads on before moving an unstable patient. See Transcutaneous Pacing |
| Epinephrine (pulseless VT / VF) | 1 mg IV/IO every 3–5 min; shockable rhythm: give after initial defibrillation attempts have failed, without delaying defibrillation (2025 AHA Part 9, COR 2a, LOE B-NR) | 0.01 mg/kg IV/IO every 3–5 min (max 1 mg per dose) | Not for VT with a pulse. See Epinephrine 1:10,000 |
Before any dose goes in, check it against the current drug label and your agency's formulary.
Pediatric & Special Populations
Pediatrics
- Arrest rhythms: In children, VF and pulseless VT are less common than asystole and PEA. Dose by weight, using Weight-Based Dosing and Pediatric Cardiac Arrest.
- Normal rates by age: check Pediatric Vital Signs. Escape and AIVR rates in children are age-specific.
- Ventricular ectopy in children: Look for structural disease, channelopathy (long QT, Brugada, catecholaminergic polymorphic VT) and a family history of sudden death. That matters most after syncope.
- QTc: Read the QTc against age-specific references, not just the adult thresholds.
Other Populations
- Pregnancy: Pregnancy does not stop defibrillation. Fetal monitors should come off and stay off during resuscitation. They distract the team and can delay defibrillation (2025 AHA Part 10, COR 3: No Benefit, LOE C-EO; supportive text). When the fundal height is at or above the umbilicus, give manual left lateral uterine displacement with compressions (COR 1, LOE C-LD), and bring obstetrics in early. If fundal height is at or above the umbilicus and ROSC is not achieved, resuscitative delivery is indicated (COR 1, LOE B-NR). Start preparing the moment you recognize arrest, with delivery as the goal by 5 minutes (COR 1, B-NR). Review QT-prolonging drugs with the obstetric team. Magnesium is also used for eclampsia. Follow the obstetric protocol.
- Older adults and kidney or liver disease: Procainamide and lidocaine clearance drops. Reduce doses per protocol and watch for toxicity.
- Heart transplant: A denervated heart does not respond to atropine. For bradycardia-related rhythms, use isoproterenol or pacing.
- ICD or pacemaker: A device shock can cause symptoms and change the rhythm. Check the device. Use a magnet only if the device protocol allows it.
Monitoring & Transport Considerations
- Lead selection: Lead II shows P waves best. V1 or MCL1 shows bundle branch and wide-complex morphology best.
- Serial 12-leads: Ongoing chest pain or new ectopy means repeating the ECG every 15–30 min. For right-sided or posterior ischemia, add V4R and V7–V9.
- QTc trending: A QT-prolonging drug running? Set an alert for QTc ≥500 ms or a rise of 60 ms or more from baseline.
- Artifact: Shivering, vibration and movement can pass for VT or VF. Before you shock, check the pulse and SpO₂ waveform.
- Pacing checks: After every pacing change or patient move, confirm capture by pulse and SpO₂ waveform.
- Before moving an unstable patient: Place anterior and posterior pads first. Transmit the 12-lead where your system allows.
- Mechanical support: An intra-aortic balloon pump or an Impella needs ECG triggering that is free of artifact.
Step-by-Step Approach & Pitfalls
- Confirm the patient: check pulse, blood pressure, mental status and SpO₂ before the rhythm name.
- Measure the QRS: measure width in the widest lead; if it is 120 ms or more, treat as ventricular until proven otherwise.
- Find the pattern: monomorphic, polymorphic or twisting around a long QT (torsades).
- Act on stability: unstable monomorphic VT with a pulse means synchronized cardioversion. Unstable polymorphic VT or torsades, with or without a pulse, means unsynchronized defibrillation. Pulseless means CPR and defibrillation.
- Stable monomorphic VT: amiodarone, procainamide or sotalol may be considered (COR 2b), with cardiology input; cardiovert if VT persists or drugs fail (COR 1). If the cause of a regular WCT cannot be determined, adenosine may be considered (COR 2b); it will not terminate VT.
- Polymorphic VT or torsades: unstable or sustained means immediate unsynchronized shock (COR 1). Then correct electrolytes, stop the offending drugs, and overdrive pace; magnesium may be considered for recurrent TdP with a long QT (COR 2b). Isoproterenol is a bridge only for acquired, pause-dependent torsades and is avoided in congenital long QT syndrome.
- Look for the cause: ischemia, electrolytes, drugs, hypoxia and the H's and T's.
Common Pitfalls
- Calling a wide-complex tachycardia SVT and giving a calcium channel blocker
- Giving amiodarone or procainamide for torsades
- Suppressing an escape rhythm or AIVR, which can cause asystole
- Shocking asystole, or treating fine VF as asystole without checking two leads
- Drawing up the wrong concentration, or giving a rate in mg/min where mg/kg was intended
ECG Examples
Clinical Pearls
References
- American Heart Association. Part 9: Adult Advanced Life Support: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16_suppl_2):S538-S577. https://doi.org/10.1161/CIR.0000000000001376
- American Heart Association and American Academy of Pediatrics. Part 8: Pediatric Advanced Life Support: 2025 American Heart Association and American Academy of Pediatrics Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16_suppl_2):S479-S537. https://doi.org/10.1161/CIR.0000000000001368
- Cao D, Arens AM, Chow SL, et al. Part 10: Adult and Pediatric Special Circumstances of Resuscitation: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(suppl 2):S578-S672. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/adult-and-pediatric-special-circumstances-of-resuscitation
- Al-Khatib SM, Stevenson WG, Ackerman MJ, et al. 2017 AHA/ACC/HRS Guideline for Management of Patients With Ventricular Arrhythmias and the Prevention of Sudden Cardiac Death. Circulation. 2018;138(13):e272-e391. https://doi.org/10.1161/cir.0000000000000549
- Zeppenfeld K, Tfelt-Hansen J, de Riva M, et al. 2022 ESC Guidelines for the management of patients with ventricular arrhythmias and the prevention of sudden cardiac death. Eur Heart J. 2022;43(40):3997-4126. https://doi.org/10.1093/eurheartj/ehac262
- Drew BJ, Ackerman MJ, Funk M, et al. Prevention of torsade de pointes in hospital settings: a scientific statement from the American Heart Association and the American College of Cardiology Foundation. Circulation. 2010;121(8):1047-1060. https://doi.org/10.1161/circulationaha.109.192704
- Brugada P, Brugada J, Mont L, Smeets J, Andries EW. A new approach to the differential diagnosis of a regular tachycardia with a wide QRS complex (landmark derivation paper). Circulation. 1991;83(5):1649-1659. https://doi.org/10.1161/01.cir.83.5.1649
- Amiodarone hydrochloride injection, USP 50 mg/mL (Fresenius Kabi USA). US Food and Drug Administration prescribing information, DailyMed (accessed October 2026). https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=9772ab48-2ef1-4b9f-9a27-794f3e7e5c7a
- Procainamide hydrochloride injection, USP (Nexus Pharmaceuticals). US Food and Drug Administration prescribing information, DailyMed. Label updated December 2025. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d58751df-cd8b-45a6-8a32-af19e747e23a
- American Heart Association. Algorithms: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Adult and pediatric cardiac arrest, tachyarrhythmia with a pulse, and electrical cardioversion algorithms. 2025. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/algorithms
- National Association of State EMS Officials. NASEMSO National Model EMS Clinical Guidelines, Version 3.0. 2022. Pediatric magnesium dose for torsades and cardiac arrest; not re-verified online in this pass.
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.