

Bedside Snapshot
- Normal (Adult)
- 30–120 U/L (0.50–2.00 µkat/L); lab-specific. Children run far higher (up to about 500 U/L in infancy and puberty); third-trimester pregnancy is higher (placental).
- Critical Values
- No universal critical value: interpret by trend and clinical context. Critical by context: ALP or bilirubin rise with fever and jaundice (cholangitis).
- High Suggests
- Biliary obstruction or cholangitis
- Drug injury, sepsis, TPN, infiltration
- PBC, PSC, pregnancy cholestasis
- Bone: growth, fracture, Paget, metastases
- Low Suggests
- EDTA, citrate or oxalate tube
- Wilson disease in acute liver failure
- Severe illness, massive transfusion, low Mg or zinc
- Hypophosphatasia
- Act Now If
- Fever or rigors plus jaundice or RUQ pain, or hypotension: treat as cholangitis per local protocol: fluids, vasopressors, antibiotics within 1 h for shock per sepsis guidelines, blood cultures, drainage consult; notify medical control
- Watch Out For
- An isolated high ALP is often bone, growth or pregnancy: confirm the source with GGT before chasing liver disease.
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult | 30–120 U/L | 0.50–2.00 µkat/L | Typical; lab- and sometimes sex-specific. Use your lab's upper limit of normal (ULN). |
| Older adult | Mildly higher | — | Especially women over 50 (bone turnover). |
| Pregnancy (third trimester) | Above the non-pregnant range | — | Placental ALP; expected. |
| Neonate 0–14 d | 90–273 U/L | 1.50–4.56 µkat/L | Pediatric intervals are analyzer-specific. |
| Infant 15 d–<1 y | 134–518 U/L | 2.24–8.65 µkat/L | — |
| Child 1–<10 y | 156–369 U/L | 2.61–6.16 µkat/L | — |
| Age 10–<13 y | 141–460 U/L | 2.35–7.68 µkat/L | — |
| Age 13–<15 y | F 62–280; M 127–517 U/L | F 1.04–4.68; M 2.12–8.63 µkat/L | Boys peak later and higher. |
| Age 15–<17 y | F 54–128; M 89–365 U/L | F 0.90–2.14; M 1.49–6.10 µkat/L | — |
| Age 17–<19 y | F 48–95; M 59–164 U/L | F 0.80–1.59; M 0.99–2.74 µkat/L | — |
Severity & critical values
| Level | Conventional | SI | What it means |
|---|---|---|---|
| Low | Below the age- and sex-specific lower limit (adult <30 U/L on this range; 40 at some labs) | <0.50 µkat/L | Exclude a chelating tube (EDTA, citrate, oxalate) first; then see Causes. |
| Normal | 30–120 U/L | 0.50–2.00 µkat/L | Adult. |
| Mild | 1–2× ULN (121–240 U/L) | 2.02–4.00 µkat/L | Repeat; check gamma-glutamyl transferase (GGT). Workup negative: observe; persistent at 6 months: consider MRCP or biopsy. |
| Marked | >2× ULN (>240 U/L) | >4.00 µkat/L | Per ACG 2017 guidance, if ultrasound and antimitochondrial antibody (AMA) are unrevealing: MRCP or liver biopsy. |
| Critical | No numeric critical value | — | Critical by context: see the warning below. |
Conversion: U/L × 0.0167 = µkat/L
Interpretation: Sources disagree on the exact boundaries. R >5 points to hepatocellular injury. R 2–5 is mixed. R <2 is cholestatic, per the ACG 2017 guideline.
Causes of Abnormal Results
High (ALP above the age- and sex-specific ULN)
Mild is 1–2× ULN. Marked is >2× ULN. The pattern and the patient tell benign from dangerous, not the number alone.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Extrahepatic biliary obstruction | Common bile duct stones, acute cholangitis, pancreatic or bile duct cancer, stricture | RUQ pain, jaundice, pale stools; fever or rigors = cholangitis until proven otherwise; dilated ducts |
| Intrahepatic cholestasis | Drug-induced liver injury (DILI; e.g., amoxicillin-clavulanate, macrolides, anticonvulsants, anabolic steroids), primary biliary cholangitis (PBC), primary sclerosing cholangitis (PSC), intrahepatic cholestasis of pregnancy (ICP) | New drug or supplement; pruritus; AMA-positive middle-aged woman (PBC); inflammatory bowel disease (PSC); late pregnancy (ICP) |
| Infiltrative liver disease | Metastases, lymphoma, sarcoidosis, tuberculosis, amyloidosis, abscess; ectopic tumor ALP (Regan isoenzyme) | ALP out of proportion to AST/ALT; weight loss, fever, known cancer |
| Critical illness | Sepsis, total parenteral nutrition (TPN), ICU cholestasis, ischemic cholangiopathy, heart failure | ICU stay, TPN, recent shock, right heart failure |
| Hepatocellular disease (mixed pattern) | Viral or alcohol-associated hepatitis, cirrhosis, liver cancer | ALT/AST clearly raised; R ratio mixed or hepatocellular |
| Bone: high osteoblast activity | Healing fracture, Paget disease (ALP can exceed 1000 U/L), osteoblastic metastases, bone tumor, osteomalacia or rickets, hyperparathyroidism, CKD bone disease, hyperthyroidism | Normal GGT; bone pain; abnormal calcium, phosphate or PTH |
| Physiologic | Childhood and pubertal growth, third-trimester pregnancy, older age, fatty meal in blood group O or B | Normal GGT and liver tests; well patient |
Low (ALP below the age- and sex-specific lower limit)
Don't wave off a low ALP. Confirm it on a correctly collected sample, then find the cause.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Specimen artifact | EDTA (lavender), citrate (light blue) or oxalate (gray) tube or carry-over; hemolysis (variable, method-dependent) | Unexpected low result: redraw in a serum or lithium-heparin tube |
| Wilson disease with acute liver failure | Copper-mediated liver failure with hemolysis | Younger patient, very high bilirubin, low or normal ALP; ALP:bilirubin <4, AST:ALT >2.2 |
| Acute stress and transfusion | Severe illness, major surgery or trauma, massive transfusion | ICU or trauma context |
| Endocrine and nutritional | Hypothyroidism, hypoparathyroidism, zinc or magnesium deficiency, malnutrition, celiac disease, pernicious anemia | Low magnesium; poor intake |
| Drugs | Antiresorptive therapy, chemotherapy, excess vitamin D | Medication history |
| Hypophosphatasia (HPP) | Inherited loss-of-function variants in the ALPL gene | Persistently low ALP for age and sex; high pyridoxal 5′-phosphate (vitamin B6); poor fracture healing, early tooth loss |
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Per ACG 2017, repeat the panel or add GGT before you start a workup. A low result needs confirming on a non-chelating tube. A borderline post-meal rise gets repeated fasting.
- How sick is the patient? Fever, jaundice, RUQ pain, hypotension or confusion: that's cholangitis. Encephalopathy with a rising INR: acute liver failure. Both are time-critical.
- Liver or bone? Are AST, ALT or bilirubin abnormal too? Then the ALP is hepatic. Isolated? Check GGT or isoenzymes.
- Calculate the R ratio. The pattern narrows your differential and picks the first test.
- Image the biliary tree. RUQ ultrasound first. Dilated ducts point to an extrahepatic cause: magnetic resonance cholangiopancreatography (MRCP) or endoscopic retrograde cholangiopancreatography (ERCP). Non-dilated ducts point to an intrahepatic cause: review drugs, check AMA, antinuclear and smooth-muscle antibodies, and run a pregnancy test when relevant.
- If still unexplained: Per ACG 2017, when ALP is >2× ULN, go to MRCP or biopsy. At 1–2× ULN, observe. If it stays high at 6 months, biopsy or MRCP.
- Trend beats a single value. A fall after drainage or after stopping a drug backs the diagnosis. A new rise in known biliary disease suggests new obstruction.
Pattern recognition
| Pattern | Suggests |
|---|---|
| ALP ↑, GGT ↑ (other liver tests normal or mildly ↑) | Liver: obstruction, drugs, PBC, PSC, infiltration |
| ALP ↑, GGT normal, other liver tests normal | Bone, growth, pregnancy or intestinal ALP; not liver |
| ALP ↑, bilirubin ↑, fever or rigors, RUQ pain | Acute cholangitis |
| ALP ↑, positive AMA | PBC: AASLD 2018 guidance needs any two of ALP rise, AMA, histology |
| ALP ↑ with inflammatory bowel disease | PSC: MRCP even if the ultrasound is normal |
| AST:ALT >2 with GGT ↑ | Alcohol-associated liver disease |
Interpretation: A ratio under 4 plus AST:ALT above 2.2 suggests Wilson disease. Treat it as a screen from one derivation cohort. It doesn't diagnose anything.
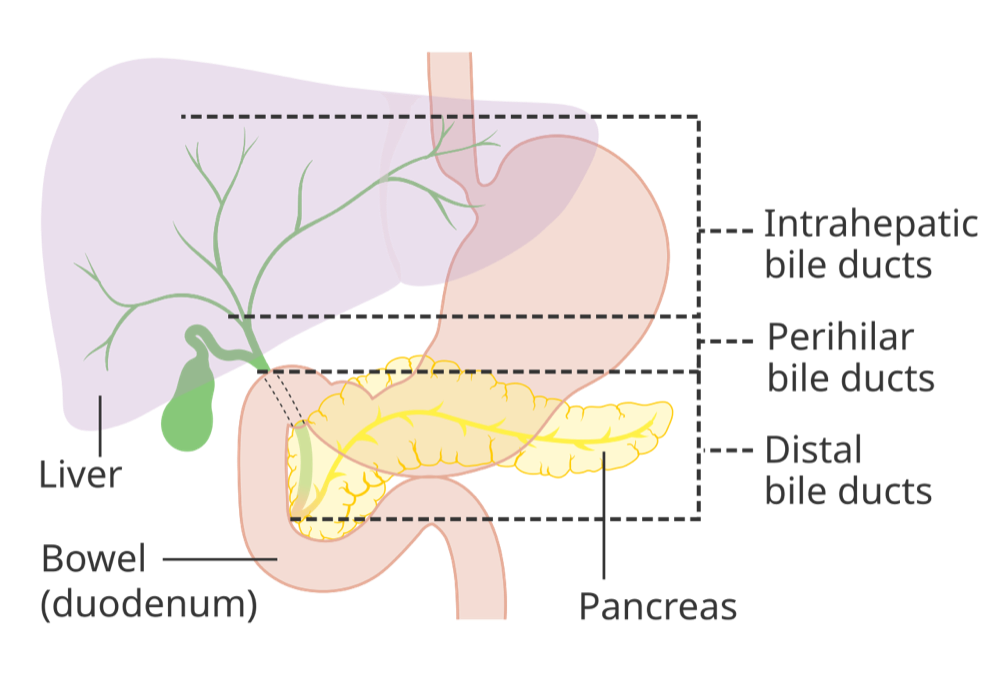
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Highest ALP of life; severe hypophosphatasia can cause seizures (vitamin B6 depletion). | Use age-specific intervals; low ALP with rickets or seizures: evaluate for HPP. |
| Children & adolescents | Growth keeps ALP several times the adult range; boys peak later and higher. | Isolated high ALP with normal GGT in a well child is usually growth; an adult-normal value may be low for age. |
| Pregnancy | Placental ALP raises total ALP in the third trimester. | Expected alone. Itching without rash in the second half: check bile acids and transaminases for ICP (bile acids >10 µmol/L often used). |
| Older adults | Drifts up, especially in women over 50 (bone turnover). | New isolated rise with bone pain: Paget disease or metastases. |
| CKD / dialysis | Renal bone disease and hyperparathyroidism raise it; adynamic bone disease lowers it. | Interpret with calcium, phosphate and PTH. |
| Liver disease | Key marker in PBC and PSC. | PBC treatment response is judged largely by ALP; track the trend. |
| Other | Blood group O or B: intestinal ALP after fatty meals. | Repeat fasting. |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| EDTA, citrate or oxalate tube (or carry-over) | False − | Chelates magnesium, an ALP cofactor | Serum or lithium heparin; follow order of draw; redraw |
| Hemolysis | Variable (method-dependent) | Interferes with the assay | Redraw |
| Non-fasting sample, blood group O or B | ↑ | Intestinal ALP after a fatty meal | Repeat fasting |
Medications & supplements
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Drugs, herbals, supplements | ↑ | Cholestatic or mixed DILI | Full medication and supplement history |
| Antiresorptive therapy, chemotherapy, excess vitamin D | ↓ (true) | Less bone turnover or ALP production | Consider before labelling HPP |
| Massive transfusion | ↓ (true) | Recognized cause of a low ALP | Recheck once stable |
Physiologic, biologic & assay
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Growth, pregnancy, older age | ↑ | Bone and placental ALP | Check GGT; use age-specific ranges |
| Low magnesium or zinc | ↓ | Both are ALP cofactors | Check magnesium |
| Analyzer and method | Varies | Activity assay; intervals are method-specific | Use the lab's own interval; trend on one lab |
Common misinterpretations
- "GGT is a liver screening test": it is non-specific. Alcohol, pancreatic or renal disease and some anticonvulsants can all push it up. Use it only to confirm where a high ALP comes from.
- "Normal bilirubin rules out obstruction": ALP can climb before bilirubin does.
- "Low ALP is good": Don't celebrate it. It may be a tube error, serious illness, Wilson disease or hypophosphatasia.
Physiology & Test Basics
What it measures
Total serum alkaline phosphatase (ALP) is the sum of several isoenzymes, and each one hydrolyzes phosphate esters at an alkaline pH. This page covers total ALP. For the enzyme you use to confirm a liver source, see the GGT page.
Physiology & regulation
- Cofactors: it is a metalloenzyme that needs zinc and magnesium. Short on either, and its activity drops.
- Liver: most of it sits on the canalicular (apical) membrane of hepatocytes, with some on biliary epithelium. Cholestasis, with bile acids building up, pushes up its synthesis and its release into the blood.
- Bone: osteoblasts make it, so it tracks bone formation: growth, healing, Paget disease, osteoblastic metastases.
- Placenta and intestine: placental ALP shows up in late pregnancy. Intestinal ALP rises after fatty meals in blood groups O and B.
- Tissue-nonspecific ALP: its job is clearing pyrophosphate (a mineralization inhibitor) and pyridoxal 5′-phosphate. Lose that function and you get hypophosphatasia.
How it is measured
- Specimen: draw serum (gold or red top) or lithium-heparin plasma (green top). Not EDTA (lavender), citrate (light blue) or oxalate/fluoride (gray).
- Method: an automated enzyme-activity assay on the chemistry analyzer. It is part of the comprehensive metabolic panel and the liver panel.
- Fasting: not routinely required. Repeat fasting when you suspect post-meal intestinal ALP.
Why it matters
A cholestatic ALP rise with fever is the lab picture of acute cholangitis. That is a cause of septic shock, and it needs drainage. In the ICU, ALP flags sepsis, TPN or drug cholestasis. A low ALP can be the first clue to Wilson disease in acute liver failure.
Clinical Pearls
References
- Kwo PY, Cohen SM, Lim JK. (2017). ACG Clinical Guideline: Evaluation of Abnormal Liver Chemistries. American Journal of Gastroenterology, 112(1), 18–35. https://doi.org/10.1038/ajg.2016.517
- Kiriyama S, Kozaka K, Takada T, et al. (2018). Tokyo Guidelines 2018: diagnostic criteria and severity grading of acute cholangitis. Journal of Hepato-Biliary-Pancreatic Sciences, 25(1), 17–30. https://doi.org/10.1002/jhbp.512
- Lindor KD, Bowlus CL, Boyer J, Levy C, Mayo M. (2019). Primary Biliary Cholangitis: 2018 Practice Guidance from the American Association for the Study of Liver Diseases. Hepatology, 69(1), 394–419. https://doi.org/10.1002/hep.30145
- Society for Maternal-Fetal Medicine; Lee RH, Greenberg M, Metz TD, Pettker CM. (2021). SMFM Consult Series #53: Intrahepatic cholestasis of pregnancy. American Journal of Obstetrics and Gynecology, 224(2), B2–B9. https://doi.org/10.1016/j.ajog.2020.11.002
- Khan AA, Brandi ML, Rush ET, et al. (2024). Hypophosphatasia diagnosis: current state of the art and proposed diagnostic criteria for children and adults. Osteoporosis International, 35(3), 431–438. https://doi.org/10.1007/s00198-023-06844-1
- Korman JD, Volenberg I, Balko J, et al. (2008). Screening for Wilson disease in acute liver failure: a comparison of currently available diagnostic tests. Hepatology, 48(4), 1167–1174. https://doi.org/10.1002/hep.22446
- Colantonio DA, Kyriakopoulou L, Chan MK, et al. (2012). Closing the gaps in pediatric laboratory reference intervals: a CALIPER database of 40 biochemical markers in a healthy and multiethnic population of children. Clinical Chemistry, 58(5), 854–868. https://doi.org/10.1373/clinchem.2011.177741
- MedlinePlus, U.S. National Library of Medicine. (2025). ALP – blood test. https://medlineplus.gov/ency/article/003470.htm
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.