

Bedside Snapshot
- Normal (Adult)
- About 11–35 µmol/L (19–60 µg/dL); assay-dependent. Neonates run higher.
- Critical Values
- >100 µmol/L (>170 µg/dL); neonates >150 µmol/L. Typical; lab-specific. No critical low.
- High Suggests
- Acute liver failure; cirrhosis or shunt
- Urea cycle disorder, organic acidemia
- Valproate, asparaginase, TPN, glycine irrigation
- Urease-producing UTI, GI bleed, bad sample
- Low Suggests
- Rarely clinically significant: a low ammonia has no recognized acute meaning.
- Act Now If
- No liver disease, encephalopathy >100 µmol/L (neonate >150): check glucose, airway, stop protein, IV dextrose; call metabolic center. ALF >150 or grade 3–4: airway, head up 30°, transplant ICU; do not restrict protein.
- Watch Out For
- In cirrhosis the level neither diagnoses nor grades HE. A delayed, warm, hemolyzed or capillary sample reads falsely high: redraw on ice.
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult | About 19–60 µg/dL | About 11–35 µmol/L | Venous plasma. The upper limit runs about 30–50 µmol/L depending on the assay; check whether your lab reports venous or arterial values. |
| Neonate (0–28 d) | Many labs: up to about 136 µg/dL | Many labs: up to about 80 µmol/L | Higher than adult; preterm infants can have transient hyperammonemia. >150 µmol/L is pathologic. |
| Infant, child, adolescent | Up to about 85 µg/dL | Up to about 50 µmol/L | >100 µmol/L with symptoms is a hyperammonemic emergency. |
| Pregnancy, older adult | Same as adult | Same as adult | No separate interval. |
Severity & critical values
| Level | Conventional | SI | What it means |
|---|---|---|---|
| Normal (adult) | 19–60 µg/dL | 11–35 µmol/L | Normal ammonia in a confused patient with cirrhosis makes hepatic encephalopathy less likely: look for another cause. |
| Elevated | 61–170 µg/dL | 36–100 µmol/L | Common and nonspecific in cirrhosis, including patients with no encephalopathy. Outside liver disease, find the cause. |
| Critical | >170 µg/dL (neonate >256) | >100 µmol/L (neonate >150) | With symptoms and no liver disease: treat as a hyperammonemic crisis now (stop protein, IV dextrose, scavengers). |
| ALF high risk | >256 µg/dL | >150 µmol/L | Acute liver failure: risk factor for intracranial hypertension; trend arterial ammonia rather than relying on one value. |
| Extracorporeal range | >341 µg/dL adult; 426–852 child | >200 µmol/L adult; 250–500 child | Non-hepatic crisis: consider dialysis in adults; in children prepare dialysis and start if no rapid fall in 3–6 h. >500 µmol/L: start immediately. Thresholds are institution-dependent; adult values are expert opinion. Follow the metabolic center. |
Conversion: µg/dL (as NH₃) × 0.587 = µmol/L; µmol/L × 1.7 = µg/dL. Some labs report ammonia-nitrogen (NH₃-N) in µg/dL. For those, multiply by 0.714 instead.
Causes of Abnormal Results
High (hyperammonemia >35 µmol/L)
Ammonia climbs for three reasons. The liver fails or gets bypassed. The urea cycle is blocked, by an inherited defect or by a drug. Or production simply outruns clearance.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Liver failure | Acute liver failure (acetaminophen, viral, drug-induced); decompensated cirrhosis; acute-on-chronic liver failure | New jaundice, INR ≥1.5 and encephalopathy without prior cirrhosis; ascites, known cirrhosis |
| Portosystemic shunting | TIPS, surgical or spontaneous portosystemic shunts | Encephalopathy soon after TIPS; recurrent HE with fairly preserved liver tests |
| Inherited metabolic disease | Urea cycle disorders (OTC deficiency is X-linked; carrier females can present at any age), organic acidemias, other inborn errors | Neonate who looks septic with respiratory alkalosis; episodic vomiting, confusion or psychosis after illness, fasting, a protein load or childbirth |
| Drug-induced urea cycle block | Valproate (even with normal liver tests), worse with topiramate; asparaginase or pegaspargase; carbamazepine and other anticonvulsants less often | Lethargy, vomiting or hypothermia on valproate; leukemia induction therapy |
| Increased nitrogen load or catabolism | GI bleeding; parenteral nutrition; glycine bladder irrigation (TURP); fasting, surgery, trauma, high-dose glucocorticoids, postpartum state | Melena or falling hemoglobin; recent TURP; new confusion after delivery |
| Increased production by bacteria | Urease-producing urinary infection with retention or obstruction (e.g., Proteus); Ureaplasma infection in transplant or immunosuppressed patients (classically after lung transplant) | Blocked catheter, distended bladder; immunosuppressed patient with unexplained coma and normal liver |
| Other | Reye syndrome (rare; aspirin in a child with a viral illness); after gastric bypass; seizures or intense exercise (transient) | Viral prodrome then vomiting and encephalopathy; bariatric surgery history |
| Spurious | Delayed or warm sample, hemolysis, capillary sample, prolonged tourniquet, crying or struggling | Unexpected value in a well-looking patient: repeat correctly |
Precipitants of hepatic encephalopathy in cirrhosis
Most overt hepatic encephalopathy (HE) episodes have a trigger. Often, correcting that trigger alone improves the patient:
- Infection: spontaneous bacterial peritonitis, urinary tract infection, pneumonia, bacteremia.
- GI bleeding: variceal or ulcer bleeding. Blood is a large protein load.
- Diuretic overuse and electrolyte disorders: hypokalemia, hyponatremia, dehydration, acute kidney injury.
- Constipation: including missed or refused lactulose.
- Sedating drugs: benzodiazepines, opioids, gabapentin, sleep aids; also TIPS placement.
Low
A low ammonia has no clinical meaning. You don't act on it.
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Delayed, warm, hemolyzed, capillary or tourniquet-heavy samples read falsely high. Surprised by a number in a well-looking patient? Redraw it on ice before you act.
- How sick is the patient? Glucose comes first. Then airway, GCS and West Haven grade. Look for seizures and for rising intracranial pressure: hypertension with bradycardia, pupil changes. Grade 3–4 needs ICU care.
- Known cirrhosis? HE is a clinical diagnosis, and a high ammonia adds nothing to its diagnosis, staging or prognosis. The ACG 2026 guideline advises against routine levels to guide treatment. A normal level is the one that should make you question the diagnosis.
- New liver injury without cirrhosis? INR ≥1.5 with any encephalopathy is acute liver failure (ALF). Here arterial ammonia tells you the risk. Rising levels, grade 3–4 HE, vasopressors or renal replacement therapy, and >150 µmol/L all mark high risk of cerebral edema.
- No liver disease? Review the drugs (valproate, asparaginase), parenteral nutrition, recent TURP, urinary retention, immunosuppression and recent delivery. Send plasma amino acids, acylcarnitines and urine organic and orotic acids. Don't wait for those results to treat.
- Escalate or dispose: cirrhosis with overt HE means treating the trigger and starting lactulose. ALF means ICU and a transplant center. Non-hepatic >100 µmol/L (neonate >150) with symptoms is a metabolic emergency: ICU and a metabolic specialist.
Patterns
| Pattern | Suggests |
|---|---|
| Cirrhosis, confusion, a clear trigger | Overt HE: treat clinically whatever the ammonia level |
| Cirrhosis, confusion, normal ammonia | Look for a mimic: hypoglycemia, sepsis, intoxication or withdrawal, Wernicke encephalopathy, hyponatremia, hypercalcemia, intracranial bleed, nonconvulsive seizures |
| High ammonia, normal liver tests, on valproate | Valproate-induced hyperammonemic encephalopathy |
| Neonate, poor feeding, lethargy, respiratory alkalosis | Urea cycle disorder; ketonuria or metabolic acidosis points instead to an organic acidemia |
| ALF with arterial ammonia >150 µmol/L that keeps rising | High risk of intracranial hypertension and herniation |
West Haven grading of hepatic encephalopathy
| Grade | Clinical features |
|---|---|
| Minimal (covert) | Abnormal psychometric or neurophysiologic tests only; normal clinical exam |
| Grade 1 (covert) | Trivial lack of awareness, euphoria or anxiety, short attention span, altered sleep rhythm; oriented |
| Grade 2 (overt) | Lethargy, disoriented to time, personality change, inappropriate behavior, asterixis |
| Grade 3 (overt) | Somnolent to semistuporous but responds to stimuli; disoriented to place; bizarre behavior |
| Grade 4 (overt) | Coma: no response to painful stimuli |
Asterixis is not specific to hepatic encephalopathy. Uremia, hypercapnia and drug toxicity cause it too.
Ammonia does not map to a West Haven grade. Grade the patient and watch the trend. Not the number.
Management Priorities
Emergency: Hyperammonemic crisis without liver disease (>100 µmol/L; neonate >150)
- Stabilize: Secure the airway, check glucose and control seizures. No hypotonic fluids.
- Stop the nitrogen load: Halt protein for no longer than 24–48 h. Start IV 10% dextrose with Na⁺ and K⁺ to reverse catabolism, and add insulin for hyperglycemia. Stop valproate.
- Scavenge: Work with a metabolic specialist. Start IV sodium phenylacetate/sodium benzoate plus arginine. Undiagnosed patients also get carglumic acid, carnitine, hydroxocobalamin and biotin.
- Remove: Plan hemodialysis or CRRT early. Thresholds are in Reference & Critical Ranges.
- Monitor & transfer: Check ammonia every 3 h. Move the patient to a metabolic center without delay.
Emergency: Acute liver failure with ammonia >150 µmol/L or grade 3–4 encephalopathy
- Airway: Admit to ICU. Intubate when the patient can't protect the airway.
- Brain: Head up 30°, keep the patient normothermic and normocapnic, and avoid hypotonic fluids. Use hypertonic saline when intracranial hypertension is a risk, per ICU protocol.
- Lower ammonia: Start CRRT early for hyperammonemia, even without a standard dialysis indication. Use plasma exchange where available. Lactulose and rifaximin have no proven role in ALF.
- Treat the cause and refer: Give acetylcysteine for acetaminophen and many non-acetaminophen causes. Call a transplant center early.
Medications
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Lactulose (overt HE) | 25 mL PO/NG every 1–2 hr until at least 2 soft stools, then titrate to 2–3 soft stools/day (titrate to stool goal: no fixed max). Retention enema if aspiration risk: 300 mL in 700 mL water or saline, held 30–60 min, every 4–6 hr | Infant 2.5–10 mL/day divided; child or adolescent 40–90 mL/day divided; titrate to 2–3 soft stools/day (label: limited pediatric data) | First-line. Improvement often within 24–48 hr. Overuse causes dehydration, hypernatremia and hypokalemia and can worsen HE |
| Rifaximin | 550 mg PO twice daily, added to lactulose (max 1,100 mg/day) | Not established under 18 years for HE | Non-absorbed antibiotic; ACG 2026 suggests adding it during acute overt HE and continuing to prevent recurrence. Not studied alone |
| Polyethylene glycol–electrolyte solution | 4 L PO/NG once as an alternative to lactulose for acute overt HE | Not established in children for HE: consult | Protect the airway first in an obtunded patient |
| Sodium phenylacetate/sodium benzoate (Ammonul; urea cycle disorders) | Over 20 kg: 5.5 g/m² of each IV over 90–120 min, then 5.5 g/m² over 24 hr | 20 kg or less: 250 mg/kg of each IV over 90–120 min, then 250 mg/kg over 24 hr | Specialist-directed. Dilute in D10W. Label: administer through a central line only (peripheral administration can cause burns). Do not repeat the loading dose. Give with IV arginine; the arginine dose depends on the disorder. Monitor K⁺ (hypokalemia), glucose and acid-base (hyperchloremic acidosis). Phenylacetate neurotoxicity: somnolence, fatigue, disorientation |
| Levocarnitine (valproate hyperammonemia) | Not labeled for valproate hyperammonemia; dose per poison center or toxicology | Weight-based, per poison center or toxicology; confirm the maximum | Off-label; regimens vary. Stop valproate. Call poison control (1-800-222-1222) |
| Dextrose 10% (metabolic crisis) | Glucose infusion rate about 6 mg/kg/min with Na⁺ and K⁺; add insulin infusion for hyperglycemia (titrate to glucose: no fixed max) | Neonate 8–10 mg/kg/min, infant or child 6–8 mg/kg/min; titrate to glucose (protocol-dependent) | If hyperglycemia occurs with lactate >3 mmol/L, lower the dextrose rate rather than raise insulin. High-alert |
Definitive care & disposition
- Cirrhosis with overt HE: Find and treat the trigger. Start lactulose and add rifaximin. Grade 3–4 means ICU. No recovery after 48–72 hr? Reassess the diagnosis. Don't restrict protein: 1.2–1.5 g/kg/day, or up to 2 g/kg/day if critically ill.
- Acute liver failure: ICU at or near a transplant center. Use hypertonic saline per protocol and acetylcysteine. Don't restrict protein.
- Non-hepatic hyperammonemia: metabolic specialist and ICU. Hemodialysis clears ammonia fastest. CVVHD or CVVHDF is commonly used in neonates, in unstable patients, or where hemodialysis is unavailable. Peritoneal dialysis is only a bridge. Never exchange transfusion.
- Valproate: Stop it. Give levocarnitine. Then look for an underlying urea cycle disorder.
These doses are typical references. Stick to local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
Ammonia is not a prehospital test. Handheld meters exist, but they are imprecise and have a low upper limit of detection. Use them in hospital, with caution. In any altered patient with liver disease or a known metabolic disorder, the point-of-care number that matters is glucose.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Cirrhosis with overt HE | Document West Haven grade, GCS, last lactulose dose and stool count, glucose, Na⁺ and K⁺. Aspiration precautions; decide on intubation before a long transfer in grade 3–4. |
| Acute liver failure | Move early to a transplant center. Send the latest arterial ammonia with its time, INR, glucose and lactate. Hourly neuro checks with pupils; glucose at least hourly. |
| Urea cycle or metabolic crisis | Do not delay transfer to a metabolic center. Keep dextrose and scavenger infusions running on pumps (scavengers by central line only). Bring the patient’s emergency letter if they have one. |
| Valproate toxicity | Send valproate level, ammonia, time and amount of last dose, and co-ingestants (topiramate). |
Scope notes
EMS: manage the airway, glucose and seizures. Then hand over the history: liver disease, metabolic disorder, valproate. Lactulose, scavengers and levocarnitine are given in hospital, or by critical-care transport teams (Paramedic/RN/CCT) per local protocol.
Timing & Kinetics
| Parameter | Value | Clinical implication |
|---|---|---|
| Sample stability | Ammonia keeps rising in a tube left at room temperature | On ice and to the lab immediately; follow your lab’s time limit |
| Lactulose response | Often within 24 hr; may take 48 hr or longer | Titrate to 2–3 soft stools; do not escalate beyond the stool goal |
| Overt HE not improving | No recovery after 48–72 hr of adequate therapy and trigger reversal | Reconsider the diagnosis and search for mimics |
| ALF trend | Ammonia stays high in patients who develop intracranial hypertension and falls in those who do not | Trend arterial ammonia; a persistently high level is a warning |
| Dialysis decision (children) | Assess response about 4 hr after starting medical therapy | No rapid fall within 3–6 hr at 250–500 µmol/L: start hemodialysis or CRRT |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Higher upper limit. Urea cycle disorders and organic acidemias present as sepsis, poor feeding, lethargy and respiratory alkalosis. | Check ammonia in any encephalopathic neonate. >150 µmol/L is an emergency; a normal value makes a proximal urea cycle disorder unlikely in an acutely symptomatic newborn if the sample was handled correctly. |
| Children & adolescents | Late-onset urea cycle disorders, valproate, asparaginase; Reye syndrome is now rare. | >100 µmol/L with symptoms is an emergency. Doses: see Management Priorities. |
| Pregnancy & postpartum | No separate range. Postpartum catabolism can unmask OTC deficiency in carrier women. Third-trimester encephalopathy with jaundice, hypoglycemia or high INR: think acute fatty liver of pregnancy or HELLP. | Check ammonia in postpartum confusion or a psychosis-like presentation. Acute fatty liver of pregnancy or HELLP is an obstetric emergency: early obstetric and transplant-center contact. Valproate has a boxed warning for fetal harm; decisions about it need neurology input. |
| Older adults | No age-specific range. Sedatives, opioids and occult infection commonly trigger HE. | Reconcile medications; search for infection and mimics. |
| CKD / dialysis | Uremic encephalopathy can overlap with HE in end-stage liver disease. | Consider both causes of confusion. |
| Liver disease | Chronic elevation is common without symptoms in cirrhosis; ammonia is prognostic in acute liver failure. | Cirrhosis: treat the patient, not the level. ALF: trend arterial ammonia. |
| Transplant, cancer therapy | Ureaplasma infection after lung transplant or in immunosuppression; asparaginase. | Unexplained coma with normal liver tests: check ammonia. |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Delay at room temperature | ↑ False + | Ammonia keeps forming in the tube | Ice slurry, deliver immediately, follow the lab time limit |
| Hemolysis | ↑ False + | Red cells release ammonia | Redraw with a free-flowing sample |
| Tourniquet, fist clenching, crying, struggling, seizure | ↑ | Muscle releases ammonia | Minimal tourniquet time, relaxed limb; note recent seizure |
| Capillary (heel or finger) sample | ↑ False + | Cell content and sweat contamination | Use venous or arterial blood |
| Ammonium heparin tube | ↑ False + | The anticoagulant contains ammonium | Use the tube your lab specifies (lithium heparin or EDTA) |
Physiologic, assay & device-specific
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Arterial vs venous sample | Values differ | Muscle takes up and releases ammonia between artery and vein | Use the range for the specimen type and the same site for serial levels; ALF thresholds are arterial |
| Handheld ammonia meter | False − at high levels | Low upper limit of detection | Confirm with a laboratory plasma level |
| µg/dL vs µmol/L, or NH₃ vs NH₃-N | Misread severity | Different units and conversion factors | Check units before applying any threshold |
Common misinterpretations
- High ammonia equals HE: Many patients with cirrhosis run high levels with no encephalopathy. Look for mimics.
- The level grades the HE: It doesn't. Don't trend ammonia to titrate lactulose. Titrate to stools and mental status.
- Normal liver tests exclude a drug cause: Wrong. Valproate hyperammonemia happens with normal liver tests.
- Units: 150 µg/dL is only about 88 µmol/L. Check the unit first. ALF and urea cycle thresholds are in µmol/L.
Physiology & Test Basics
What it measures
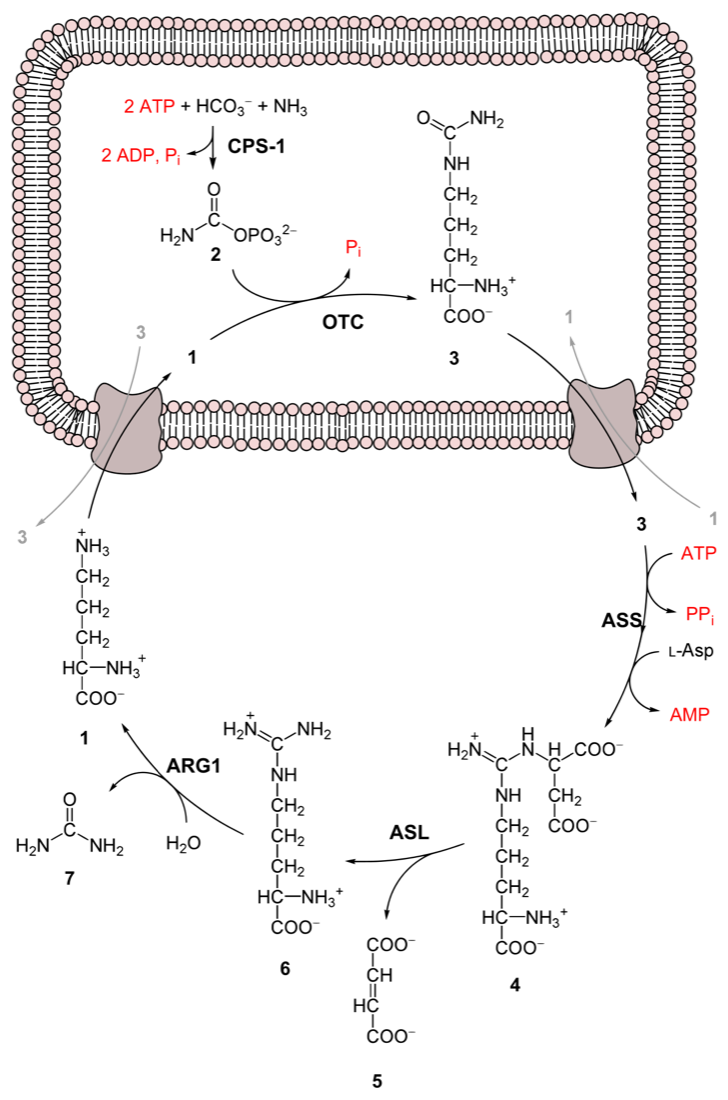
Plasma ammonia is free ammonia (NH₃) plus ammonium (NH₄⁺) in the blood. Production comes from the gut, muscle and kidney. Clearance is mainly the liver’s urea cycle. The number reflects that balance. It is the key test for unexplained encephalopathy, acute liver failure, urea cycle disorders and valproate toxicity.
Physiology & regulation
- Production: Gut bacteria break down protein and urea. Small-bowel glutamine metabolism, muscle and kidney add more.
- Clearance: The liver turns ammonia into urea, and the kidney excretes it. Muscle and brain astrocytes trap it as glutamine.
- Brain injury: Glutamine builds up in astrocytes, and they swell. In acute liver failure, that swelling causes cerebral edema.
- pH: Alkalosis shifts NH₄⁺ to NH₃, and NH₃ crosses the blood–brain barrier. Hypokalemia increases renal ammonia production.
- Treatment targets: Lactulose acidifies the colon and traps NH₄⁺. Rifaximin reduces ammonia-producing bacteria. Scavengers bypass the urea cycle.
How it is measured
- Specimen: venous or arterial plasma, usually lithium heparin (green top) or EDTA (lavender top) per your lab; free-flowing draw, minimal tourniquet, no fist clenching.
- Handling: fill the tube, place it in an ice slurry and send it to the lab immediately; many labs reject delayed or hemolyzed samples.
- Method: laboratory enzymatic assay; handheld meters are imprecise.
- Timing: No fasting in an emergency. Order it as STAT.
Why it matters
In acute liver failure and urea cycle disorders, ammonia drives cerebral edema. The level guides dialysis and scavenger therapy. In cirrhosis, the exam matters more than the number.
Clinical Pearls
References
- Bajaj, J. S., Jakab, S. S., Jesudian, A. B., et al. (2026). ACG clinical guideline: Hepatic encephalopathy. American Journal of Gastroenterology, 121(3), 588–618. https://doi.org/10.14309/ajg.0000000000003899
- Vilstrup, H., Amodio, P., Bajaj, J., et al. (2014). Hepatic encephalopathy in chronic liver disease: 2014 practice guideline by the American Association for the Study of Liver Diseases and the European Association for the Study of the Liver (landmark guideline; source of the West Haven grading table). Hepatology, 60(2), 715–735. https://doi.org/10.1002/hep.27210
- Shingina, A., Mukhtar, N., Wakim-Fleming, J., et al. (2023). Acute liver failure guidelines. American Journal of Gastroenterology, 118(7), 1128–1153. https://doi.org/10.14309/ajg.0000000000002340
- Nanchal, R., Subramanian, R., Alhazzani, W., et al. (2023). Guidelines for the management of adult acute and acute-on-chronic liver failure in the ICU: Neurology, peri-transplant medicine, infectious disease, and gastroenterology considerations. Critical Care Medicine, 51(5), 657–676. https://doi.org/10.1097/CCM.0000000000005824
- Häberle, J., Burlina, A., Chakrapani, A., et al. (2019). Suggested guidelines for the diagnosis and management of urea cycle disorders: First revision. Journal of Inherited Metabolic Disease, 42(6), 1192–1230. https://doi.org/10.1002/jimd.12100
- US Food and Drug Administration. (2026). Valproate sodium injection: Prescribing information (sections 5.8–5.10, hyperammonemia, topiramate, hypothermia). DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=8d5fc1c1-d3c0-497e-971b-6c4dba9a3fad
- US Food and Drug Administration. (2018). Ammonul (sodium phenylacetate and sodium benzoate) injection: Prescribing information. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d564f2b1-9fc7-4201-8066-d745ac3a671f
- US Food and Drug Administration. (2024). Generlac (lactulose solution, USP) for portal-systemic encephalopathy: Prescribing information. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=35207edd-a5fe-4369-a079-7a8b0d2f2e91
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.