

Bedside Snapshot
- Normal (Adult)
- Total: ≤1.2 mg/dL (≤21 µmol/L)
Direct: ≤0.3 mg/dL (≤5 µmol/L) - Critical Values
- Adults: no universal critical value; interpret by trend and context.
Age <1 yr: ≥15 mg/dL (≥257 µmol/L), typical; lab-specific. Newborns: use AAP 2022 hour-specific thresholds. - High Suggests
- Mostly direct: cholangitis or duct obstruction, acute liver injury, sepsis, drug injury
Mostly indirect: hemolysis, Gilbert syndrome, newborn jaundice - Low Suggests
- Rarely clinically significant: a low bilirubin has no recognized diagnostic meaning.
- Act Now If
- Fever, jaundice, RUQ pain: sepsis care, ERCP-capable destination. Jaundice with confusion or bleeding: possible liver failure. Newborn near exchange threshold or neuro signs: NICU now.
- Watch Out For
- Newborns: visual estimates and TcB mislead. Get a TSB when TcB is ≥15 mg/dL or within 3 mg/dL of the phototherapy threshold, and never subtract the direct fraction.
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult: total | ≤1.2 mg/dL | ≤21 µmol/L | Same for men and women |
| Adult: direct | ≤0.3 mg/dL | ≤5 µmol/L | Conjugated plus delta (albumin-bound) bilirubin |
| Pregnancy | Same as adult | Same as adult | New jaundice is abnormal |
| Newborn 0–6 days | Hour-specific | Hour-specific | Plot TSB by age in hours on the AAP 2022 curves |
| Infant 7–14 days | ≤14.9 mg/dL | ≤255 µmol/L | Breast milk jaundice can last longer and is usually benign |
| Child 15 days–17 y | Total ≤1 mg/dL | Total ≤17 µmol/L | Total bilirubin only. Infant direct bilirubin is a separate test; see Special Populations |
Severity & critical values
| Level | Conventional | SI | What it means |
|---|---|---|---|
| Elevated | >1.2 mg/dL | >21 µmol/L | Fractionate; isolated indirect rise with normal enzymes is usually Gilbert syndrome |
| Cholangitis criterion | ≥2 mg/dL | ≥34 µmol/L | Cholestasis item in the Tokyo Guidelines 2018 (TG18) |
| Visible jaundice | about 2.5–3 mg/dL | about 43–51 µmol/L | Scleral icterus; easy to miss in artificial light |
| Likely duct stone | >4 mg/dL | >68 µmol/L | With a dilated common bile duct: high likelihood per ASGE 2019 |
| Critical | ≥15 mg/dL (age <1 y) | ≥257 µmol/L | Typical; lab-specific. Adults: no universal critical value |
| Hazardous (newborn) | ≥30 mg/dL | ≥513 µmol/L | Term used in the AAP 2022 FAQ (hazardous hyperbilirubinemia); high kernicterus risk |
Conversion: mg/dL × 17.1 = µmol/L
In a normal result, most of the total is indirect. Every newborn decision runs on the total serum bilirubin (TSB).
Causes of Abnormal Results
High, mostly indirect (>1.2 mg/dL total)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Hemolysis | Hemolytic transfusion reaction, TTP, HUS or DIC, G6PD crisis, autoimmune or sickle cell hemolysis, mechanical valve | Falling hemoglobin, high LDH, low haptoglobin, high reticulocytes |
| Heme load | Resorbing large hematoma, ineffective erythropoiesis | Recent bleed or trauma |
| Reduced conjugation | Gilbert syndrome (UGT1A1 variant, 3–7% of Americans); Crigler-Najjar type I (rare; kernicterus risk, needs phototherapy and transplant referral) | Well patient, normal enzymes; worse with fasting, illness, dehydration, exercise or menses |
| Drug effect | Atazanavir (inhibits UGT1A1) | Asymptomatic; reversible |
High, mostly direct
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Duct obstruction | Bile duct stone with cholangitis, pancreatic or bile duct cancer, stricture, blocked stent | RUQ pain, fever, pale stools, dark urine; high ALP and GGT; dilated ducts |
| Hepatocellular injury | Acetaminophen toxicity, shock liver, viral or alcohol-associated hepatitis, drug-induced liver injury (DILI) | Very high AST and ALT; rising INR or confusion means liver failure |
| Intrahepatic cholestasis | Sepsis, parenteral nutrition, drugs, primary biliary or sclerosing cholangitis | ALP-predominant; no duct dilation |
| Chronic liver disease | Decompensated cirrhosis, congestion from right heart failure | Ascites, low albumin, high INR |
| Inherited | Dubin-Johnson, Rotor (rare, benign) | Isolated direct rise, normal enzymes |
Newborns and young infants
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Isoimmune hemolysis | ABO or Rh(D) disease, other maternal antibodies | Jaundice under 24 hours; positive direct antiglobulin test (DAT); rapid rise |
| Other hemolysis | G6PD deficiency, spherocytosis | TSB rises despite phototherapy or rebounds suddenly |
| Infection | Sepsis, urinary tract infection | Poor feeding, lethargy, temperature instability |
| Physiologic and feeding | Physiologic jaundice, suboptimal intake, breast milk jaundice (up to 3 months) | Excess weight loss and few stools suggest poor intake |
| Cholestasis (direct) | Biliary atresia, galactosemia, hypothyroidism, tyrosinemia | Jaundice beyond 2–3 weeks, pale stools, dark urine |
Low
A low bilirubin rarely matters clinically. It has no recognized diagnostic meaning.
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Light exposure lowers results; gross hemolysis interferes in an assay-dependent direction. Repeat on a protected sample if it does not fit; confirm a high newborn transcutaneous bilirubin (TcB) with a TSB.
- How sick is the patient? Look for sepsis, new confusion or bleeding (liver failure) and falling hemoglobin. In a newborn: poor feeding, lethargy, high-pitched cry, arching, apnea.
- Fractionate. Mostly indirect means hemolysis or reduced conjugation; a raised direct fraction means hepatocellular disease or cholestasis.
- Read the companion tests. ALT/AST-predominant is hepatocellular; ALP/GGT-predominant is cholestatic. Add CBC, LDH, haptoglobin and INR.
- Apply named criteria: TG18 for cholangitis, ASGE 2019 for duct stones, Hy's law for drug injury, AAP 2022 for newborns.
- Image and escalate. Ultrasound first for direct hyperbilirubinemia. Trend beats a single value: a rising bilirubin with fever, confusion or coagulopathy is an emergency.
Pattern recognition
| Pattern | Suggests |
|---|---|
| Indirect only; normal enzymes and hemoglobin | Gilbert syndrome |
| Indirect with anemia, high LDH, low haptoglobin | Hemolysis: smear, DAT, reticulocytes |
| Direct with high ALP/GGT and dilated ducts | Extrahepatic obstruction |
| Direct with AST and ALT in the thousands | Acetaminophen, ischemia or viral hepatitis |
| AST:ALT >2 with rising bilirubin | Alcohol-associated hepatitis |
| ALT >3× and bilirubin >2× upper limit, ALP not high | Hy's law: about 1 in 10 such drug-injury cases die or need a transplant |
Acute cholangitis: TG18 criteria
| Domain | Criteria |
|---|---|
| A. Inflammation | Fever >38 °C (100.4 °F) or chills; or WBC <4 or >10 ×10³/µL, or CRP ≥1 mg/dL |
| B. Cholestasis | Bilirubin ≥2 mg/dL; or ALP, GGT, AST or ALT >1.5× upper limit |
| C. Imaging | Biliary dilation, or a stone, stricture or stent |
| Diagnosis | Suspected: A plus B or C. Definite: A, B and C |
Duct stone likelihood, ASGE 2019: high (stone on imaging, bilirubin >4 mg/dL with a dilated duct, or cholangitis) goes to ERCP; intermediate (abnormal liver tests, age >55 years or a dilated duct) gets EUS, MRCP or an intraoperative cholangiogram first.
Management Priorities
Emergency: Newborn TSB at the escalation threshold (exchange threshold minus 2 mg/dL) or encephalopathy signs
- Escalate: call neonatology; urgent transfer to a NICU that can exchange-transfuse, admitted directly rather than through the ED.
- Treat: emergent intensive phototherapy (blue LED, at least 30 µW/cm² per nm) and IV hydration, continued during transfer if possible.
- Send STAT: total and direct bilirubin, CBC, albumin, chemistries, type and crossmatch; TSB at least every 2 hours.
- Exchange transfusion: urgent at the exchange threshold, or at any TSB with hypertonia, arching, retrocollis, opisthotonos, high-pitched cry or recurrent apnea.
Emergency: Suspected acute cholangitis
- Resuscitate: sepsis protocol: cultures, prompt broad-spectrum antibiotics, fluids, vasopressors for persistent hypotension.
- Grade: organ dysfunction (hypotension, confusion, PaO₂/FiO₂ <300, creatinine >2 mg/dL, INR >1.5, platelets <100 ×10³/µL) is severe (TG18 grade III).
- Source control: biliary drainage by ERCP, or percutaneously; urgent once stabilized in severe cases.
Medications
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Immune globulin IV (IVIG) | Not used for this indication | Newborn isoimmune hemolysis (positive DAT), TSB at or above the escalation threshold: 0.5–1 g/kg IV over 2 hr; may repeat in 12 hr. Weight-based, no fixed maximum; AAP option, protocol-dependent | AAP option only: benefit unclear, linked to necrotizing enterocolitis |
| Ceftriaxone | No bilirubin-related restriction | Contraindicated in hyperbilirubinemic and premature neonates (up to postmenstrual age 41 weeks); also contraindicated in neonates ≤28 days who need or are expected to need calcium-containing IV solutions | Displaces bilirubin from albumin; encephalopathy risk |
| Sulfamethoxazole-trimethoprim | No bilirubin-related restriction | Contraindicated under 2 months of age | Bilirubin displacement and kernicterus risk |
Definitive care & disposition
- Exchange transfusion: NICU only. Bilirubin-to-albumin ratio (TSB mg/dL ÷ albumin g/dL) supports the decision: ≥8 at ≥38 weeks without neurotoxicity risk factors; ≥7.2 at ≥38 weeks with one, or 35–37 weeks without; ≥6.8 at 35–37 weeks with one.
- Infant direct >1 mg/dL: prompt pediatric gastroenterology or hepatology referral.
- Adults: ERCP, EUS or MRCP by stone likelihood; jaundice with confusion or coagulopathy needs ICU care and early transplant-center contact; stop suspect drugs.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
Transcutaneous meters screen newborns only. Get a TSB when TcB is ≥15 mg/dL or within 3 mg/dL of the phototherapy threshold. Never read a meter over skin that has had phototherapy. Adult bilirubin is a lab test, not a bedside number.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Newborn handoff | Gestational age, age in hours, latest TSB and its time, direct bilirubin, albumin, DAT, blood types, risk factors |
| Newborn en route | Continue phototherapy and IV fluids if possible; reassess tone, cry, feeding and breathing |
| Adult with fever and jaundice | Treat as sepsis; destination with ERCP and ICU |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Unconjugated bilirubin can enter the brain; thresholds depend on gestational age and hours of age | Neurotoxicity risk factors: under 38 weeks, albumin <3 g/dL, isoimmune or other hemolysis, G6PD deficiency, sepsis, instability in the past 24 hours |
| Prolonged infant jaundice | AAP 2022: check direct bilirubin if breastfed and jaundiced at 3–4 weeks, or formula-fed at 2 weeks; NASPGHAN/ESPGHAN: any infant after 2 weeks | Direct >1 mg/dL needs cholestasis evaluation; review newborn screening |
| Children & adolescents | Normal total ≤1 mg/dL | Hemolytic disease and Gilbert syndrome are common causes |
| Pregnancy | Adult range applies | Evaluate new jaundice urgently. New jaundice in pregnancy suggests HELLP, acute fatty liver of pregnancy (third trimester, with hypoglycemia, coagulopathy or encephalopathy) or intrahepatic cholestasis of pregnancy (pruritus, raised bile acids). It needs urgent obstetric evaluation; EMS and transport should treat it as an obstetric emergency. A positive or unknown maternal antibody screen means the newborn needs a DAT and blood type |
| Older adults | No clinically meaningful difference | Painless obstructive jaundice raises concern for malignancy |
| Liver disease | Rises as cirrhosis decompensates | A rising trend is a prognostic warning; bilirubin is a MELD and Child-Pugh component |
| Other | Gilbert syndrome in 3–7%; G6PD deficiency commoner in some ancestries | Screen newborns for G6PD when TSB rises unexpectedly |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Light or delayed analysis | ↓ | Bilirubin is photodegraded | Shield the tube; analyze promptly |
| Gross hemolysis | Assay-dependent (↑ or ↓) | Hemoglobin interferes with the diazo reaction; direction depends on the assay | Recollect; check the lab's interference limits |
| Lipemia | Assay-dependent | Turbidity interferes with photometric reading | Check the lab's interference limits |
Medications & supplements
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Atazanavir | ↑ indirect | Inhibits UGT1A1 | Expected; evaluate if transaminases also rise |
| Sulfonamides, aspirin, penicillins | Neonatal free bilirubin ↑ (binding displacement); no reliable assay change | Displace bilirubin from albumin in vivo; serum total is not falsely lowered | Avoid sulfonamides in jaundiced neonates (see medications table); review other drugs on the list |
Physiologic / biologic
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Fasting or illness | ↑ indirect | Unmasks Gilbert syndrome | Repeat when well and fed |
| Delta bilirubin | Direct stays ↑ | Albumin-bound; clears over weeks (tracks albumin's half-life, about 2–3 weeks) | Expect a slow fall after obstruction is relieved |
| Paraproteins (myeloma, IgM) | False + or unreliable | Assay interference | Discuss with the lab |
Assay & device-specific
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Phototherapy | Direct ↑ | Photobilirubin isomers react as direct | Interpret direct cautiously |
| TcB over treated skin | False − | Phototherapy bleaches skin | Use TSB |
Common misinterpretations
- Subtracting direct from total in a newborn: The thresholds use the total. If direct exceeds 50% of TSB, consult an expert.
- A normal bilirubin excludes serious liver injury: Early injury can show up in the transaminases first.
- A slow fall after ERCP means failure: Delta bilirubin clears over weeks. A slow fall is what you should expect.
Physiology & Test Basics
What it measures
Three numbers matter here: total, direct and indirect. Direct bilirubin (conjugated plus delta) reacts with the diazo reagent with no accelerator. Indirect is total minus direct, so it is mostly unconjugated.
Physiology & regulation
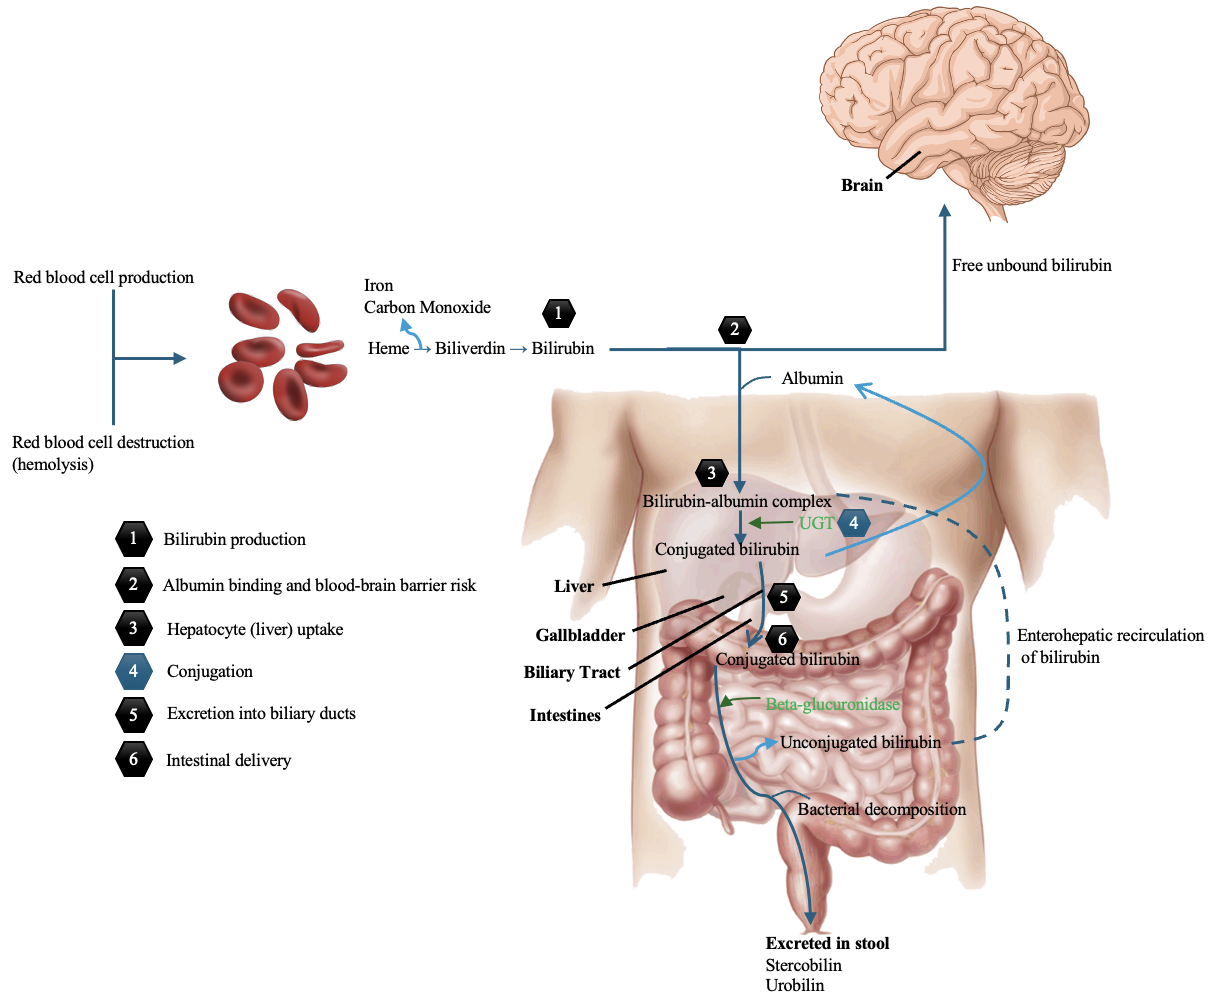
- Production: About 85% comes from the heme in hemoglobin, released as red cells age.
- Transport: Unconjugated bilirubin does not dissolve, so it rides on albumin. Unbound bilirubin can enter the brain.
- Conjugation: UGT1A1 in the liver cells adds glucuronic acid. That makes it water-soluble.
- Excretion: Into bile. Gut bacteria turn it into urobilinogen and stercobilin, and stercobilin colors the stool.
- Urine: Only conjugated bilirubin gets filtered into urine. So bilirubinuria means direct hyperbilirubinemia.
How it is measured
Serum or plasma, per local lab. Newborns give a heel stick. Protect the sample from light. Automated diazo chemistry does the measuring. Newborn screening uses TcB or TSB at 24–48 hours of age or before discharge. No fasting needed.
Why it matters
The fractions do the sorting. Bilirubin separates hemolysis from liver injury and obstruction. A rising level signals cholangitis or liver failure. In newborns, unconjugated bilirubin is a neurotoxin. Hour-specific monitoring prevents kernicterus.
Clinical Pearls
References
- Kemper, A. R., Newman, T. B., Slaughter, J. L., et al. (2022). Clinical practice guideline revision: Management of hyperbilirubinemia in the newborn infant 35 or more weeks of gestation. Pediatrics, 150(3), e2022058859. https://doi.org/10.1542/peds.2022-058859
- Fawaz, R., Baumann, U., Ekong, U., et al. (2017). Guideline for the evaluation of cholestatic jaundice in infants: Joint recommendations of NASPGHAN and ESPGHAN. Journal of Pediatric Gastroenterology and Nutrition, 64(1), 154–168. https://doi.org/10.1097/MPG.0000000000001334
- Kwo, P. Y., Cohen, S. M., & Lim, J. K. (2017). ACG clinical guideline: Evaluation of abnormal liver chemistries. American Journal of Gastroenterology, 112(1), 18–35. https://doi.org/10.1038/ajg.2016.517
- Chalasani, N. P., Maddur, H., Russo, M. W., Wong, R. J., & Reddy, K. R. (2021). ACG clinical guideline: Diagnosis and management of idiosyncratic drug-induced liver injury. American Journal of Gastroenterology, 116(5), 878–898. https://doi.org/10.14309/ajg.0000000000001259
- Kiriyama, S., Kozaka, K., Takada, T., et al. (2018). Tokyo Guidelines 2018: Diagnostic criteria and severity grading of acute cholangitis. Journal of Hepato-Biliary-Pancreatic Sciences, 25(1), 17–30. https://doi.org/10.1002/jhbp.512
- ASGE Standards of Practice Committee, Buxbaum, J. L., Abbas Fehmi, S. M., et al. (2019). ASGE guideline on the role of endoscopy in the evaluation and management of choledocholithiasis. Gastrointestinal Endoscopy, 89(6), 1075–1105.e15. https://doi.org/10.1016/j.gie.2018.10.001
- Hikma Pharmaceuticals USA Inc. (2021, revised December 2021; DailyMed listing updated September 30, 2026). Ceftriaxone for Injection, USP: Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=8351aa37-552d-471d-b293-c564dcb6ec29
- Mayo Clinic Laboratories. (2026). Bilirubin, Total, Serum: Test catalog (reference values, interpretation and cautions). https://www.mayocliniclabs.com/test-catalog/overview/81785
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.