

Bedside Snapshot
- Normal (Adult)
- Total 8.5–10.5 mg/dL (2.12–2.62 mmol/L)
Ionized 4.5–5.3 mg/dL (1.12–1.32 mmol/L) - Critical Values
- Total <6 or >13 mg/dL (<1.5 or >3.24 mmol/L)
Ionized <3.2 or >6.4 mg/dL (<0.8 or >1.6 mmol/L)
Typical; lab-specific - High Suggests
- Malignancy (PTHrP, bone metastases, myeloma)
- Primary hyperparathyroidism
- Vitamin D excess, granulomatous disease
- Thiazides, lithium, immobilization
- Low Suggests
- Low albumin (total only: check ionized)
- Citrate (transfusion), sepsis, pancreatitis
- Post-thyroidectomy, low Mg²⁺
- CKD, vitamin D deficiency, hydrofluoric acid
- Act Now If
- Tetany, seizure, stridor, long QT or ionized <0.8 mmol/L: monitor, 12-lead, IV calcium. Total >13 mg/dL with confusion or vomiting: isotonic fluids, notify medical control
- Watch Out For
- Corrected calcium misclassifies, especially with low albumin, CKD or critical illness. Measure ionized calcium before treating or dismissing a result.
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult, total calcium | 8.5–10.5 mg/dL | 2.12–2.62 mmol/L | Serum or plasma chemistry; about 40% is albumin-bound, so read it with the albumin |
| Adult, ionized calcium | 4.5–5.3 mg/dL | 1.12–1.32 mmol/L | Whole blood on a blood-gas or point-of-care analyzer; the active fraction; pH-dependent |
| Pregnancy | Total falls as albumin falls | — | Ionized calcium stays in the adult range: use it to judge true calcium status |
| Older adult | Same as adult | Same as adult | Low albumin is common, so check ionized calcium before treating a low total |
| Infant 0–90 days | 7.8–11.3 mg/dL | 1.95–2.82 mmol/L | Neonates in the first days of life: use NICU-specific limits |
| Infant 91 days–1 year | 8.8–11.4 mg/dL | 2.20–2.84 mmol/L | Upper limit higher than adult |
| Child 1–3 years | 8.8–11.1 mg/dL | 2.20–2.77 mmol/L | Total calcium; vitamin D-replete children |
| Child 4–11 years | 8.8–10.7 mg/dL | 2.20–2.67 mmol/L | Total calcium |
| Adolescent 12–19 years | 8.5–10.6 mg/dL | 2.12–2.64 mmol/L | Approaches the adult range |
Pediatric sources: Pediatric total-calcium intervals are age-specific intervals from Roizen et al., J Clin Endocrinol Metab 2013;98(12):E1946–E1950, doi:10.1210/jc.2013-3105 (vitamin D-replete children). Pediatric ionized calcium ranges are not listed; use the lab's pediatric reference.
Severity & critical values
| Level | Conventional | SI | What it means |
|---|---|---|---|
| Mild hypocalcemia | Total 7.6–8.4 mg/dL, no symptoms | 1.90–2.10 mmol/L | Confirm with ionized calcium; look for the cause (magnesium, vitamin D, PTH, kidneys) |
| Severe hypocalcemia | Total <7.6 mg/dL, or symptoms at any low value | <1.90 mmol/L | Paresthesias, tetany, carpopedal spasm, laryngospasm, seizures, QT prolongation: IV calcium |
| Ionized hypocalcemia in hemorrhage | Ionized <3.6 mg/dL | <0.9 mmol/L | Correct promptly during massive transfusion; below 0.8 mmol/L is linked to dysrhythmias |
| Mild hypercalcemia | Total >10.5 to <12 mg/dL | >2.62 to <3.0 mmol/L | Often no symptoms, or fatigue and constipation; usually outpatient workup |
| Moderate hypercalcemia | Total 12–14 mg/dL | 3.0–3.5 mmol/L | Polyuria, dehydration, nausea; treat if symptomatic or rising |
| Severe hypercalcemia | Total >14 mg/dL | >3.5 mmol/L | Hypercalcemic crisis risk: vomiting, AKI, confusion, coma, arrhythmia |
| Critical | Total <6 or >13 mg/dL; ionized <3.2 or >6.4 mg/dL | Total <1.5 or >3.24; ionized <0.8 or >1.6 mmol/L | Typical panic values (lab-specific): the lab calls; assess, monitor and treat now |
Conversion: calcium mg/dL × 0.25 = mmol/L (mmol/L × 4 = mg/dL); mmol/L × 2 = mEq/L
SI: corrected Ca (mmol/L) = measured Ca + 0.02 × (40 − albumin in g/L)
Set the result against the adult total range (8.5–10.5 mg/dL). The corrected number is an estimate and nothing more. It ignores pH, it misclassifies many patients, and it fails worst when albumin is below 3 g/dL, in CKD and in critical illness. When the decision matters, measure ionized calcium.
Causes of Abnormal Results
High (Hypercalcemia >10.5 mg/dL)
Two causes account for about 90% of hypercalcemia. Primary hyperparathyroidism is usually mild, chronic and found on routine labs. Malignancy is often higher, rises faster and shows up in sicker, hospitalized patients. Severity by total calcium: mild <12, moderate 12–14, severe >14 mg/dL.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Malignancy: PTH-related peptide (PTHrP) | Squamous cell cancers (lung, head and neck), renal, breast | Known cancer, rapid rise, PTH suppressed |
| Malignancy: bone destruction | Multiple myeloma, bone metastases (breast and others) | Bone pain, anemia, kidney injury, high total protein (myeloma) |
| Calcitriol (active vitamin D) excess | Lymphoma, sarcoidosis and other granulomatous disease, vitamin D toxicity | Suppressed PTH; supplements, lymphadenopathy, abnormal chest film |
| PTH-mediated | Primary hyperparathyroidism, tertiary hyperparathyroidism (long-standing CKD), lithium | PTH high or inappropriately normal; kidney stones, osteoporosis |
| Familial hypocalciuric hypercalcemia (FHH) | Inherited calcium-sensing receptor defect | Lifelong mild elevation, low urine calcium, family history; benign |
| Medications and supplements | Thiazides, calcium carbonate antacids (milk-alkali syndrome), vitamin D or A, teriparatide | Medication list; metabolic alkalosis and AKI suggest milk-alkali |
| Bone turnover and endocrine | Immobilization, thyrotoxicosis, adrenal insufficiency | Bedbound patient (especially adolescents or Paget disease); tachycardia; hypotension |
Symptoms ("stones, bones, abdominal groans, psychiatric overtones"). Expect kidney stones, polyuria and thirst, bone pain, constipation, nausea, pancreatitis, fatigue, depression, confusion. ECG: short QT. Bradycardia and AV block come at high levels.
Low (Hypocalcemia <8.5 mg/dL)
First, decide whether it is real. Low albumin drags total calcium down while ionized calcium can stay normal. True hypocalcemia is mild at 7.6–8.4 mg/dL with no symptoms. It is severe below 7.6 mg/dL (1.9 mmol/L) or with any symptoms.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Citrate chelation | Massive transfusion, plasma exchange, citrate anticoagulation on CRRT | Ionized calcium falls while total looks normal; worse with shock or liver failure |
| Critical illness | Sepsis, burns, pancreatitis, early rhabdomyolysis | Ionized hypocalcemia is common in ICU patients; corrected calcium misses it |
| Hydrofluoric acid exposure | Rust removers, glass etching, industrial cleaners | Pain out of proportion to the burn; QT prolongation; ventricular arrhythmia |
| Hypoparathyroidism | Thyroid or parathyroid surgery, autoimmune, 22q11.2 deletion (DiGeorge), neck radiation | Recent neck surgery, perioral tingling; PTH low, phosphate high |
| Magnesium depletion | Alcohol use disorder, diarrhea, proton pump inhibitors, diuretics | Calcium will not correct until Mg²⁺ is replaced; often low K⁺ too |
| Vitamin D deficiency or resistance | Low intake or sun, malabsorption, gastric bypass, liver disease, CKD | PTH high; phosphate low (high in CKD) |
| Phosphate excess | CKD, tumor lysis syndrome, rhabdomyolysis, phosphate enemas | High phosphate, kidney injury |
| Medications | Bisphosphonates, denosumab, cinacalcet, foscarnet, loop diuretics, phenytoin | Recent antiresorptive dose; denosumab (Prolia) carries a boxed warning for severe hypocalcemia in advanced CKD |
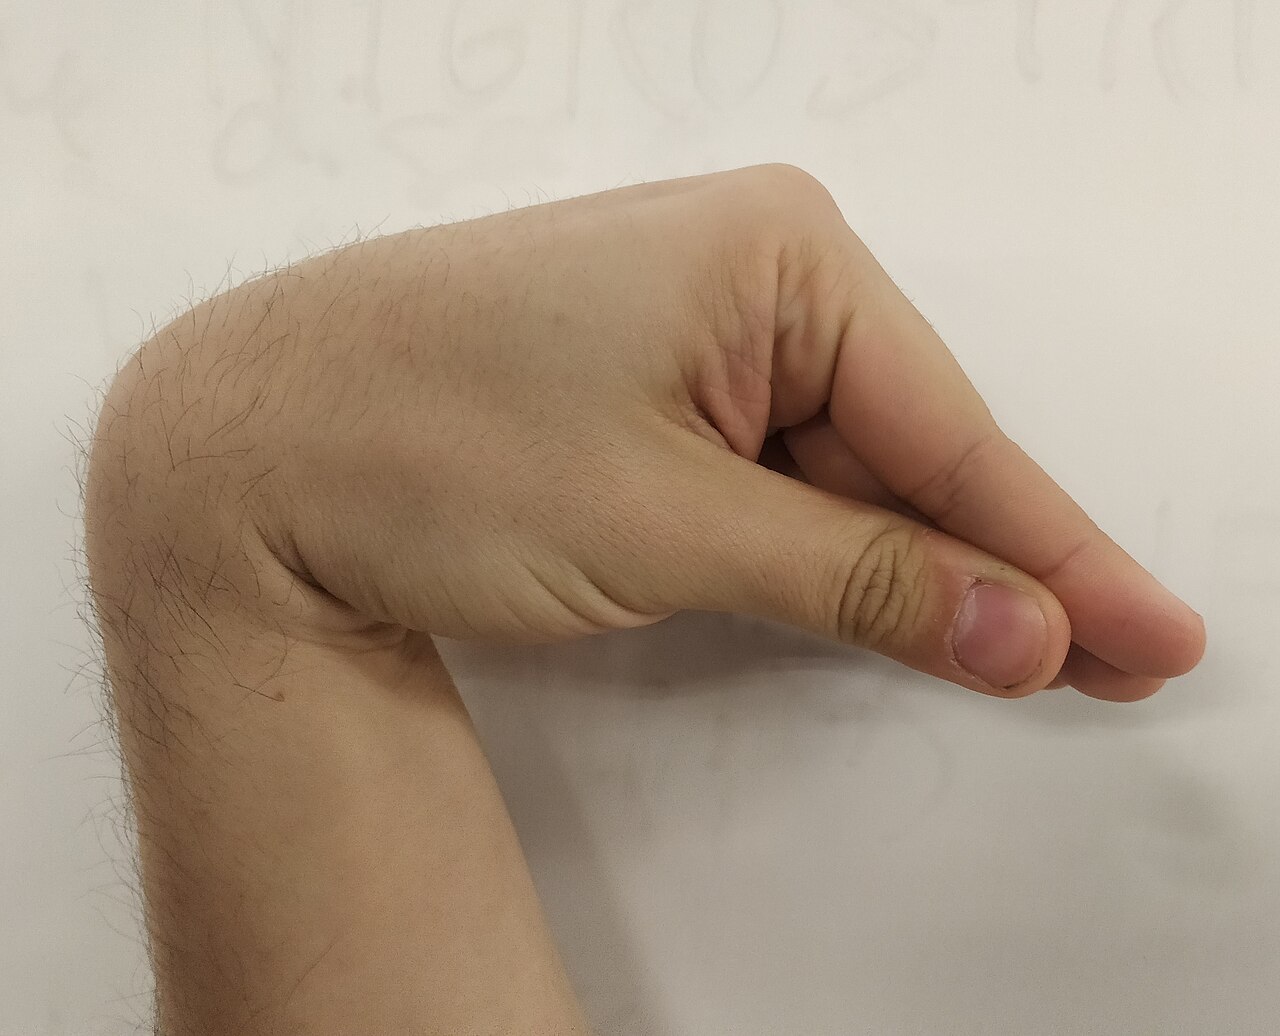
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Check the albumin and the sample. Calcium very low with K⁺ very high? Think EDTA contamination. Redraw. Measure ionized calcium when albumin or pH is abnormal, in CKD, in critical illness and during transfusion.
- How sick is the patient? Look for tetany, seizure, stridor, confusion, vomiting, dehydration and QT changes. Symptoms or ECG changes? Treat now and investigate in parallel.
- Acute or chronic? Compare with earlier values. A fast change makes symptoms show up at milder numbers. A slow rise over years points to hyperparathyroidism. Trend beats a single value.
- Calculate carefully. Corrected calcium is a rough screen, and ionized calcium decides. Read it alongside the pH from the same sample.
- Classify with PTH. In hypercalcemia, intact PTH is the first test that matters. High or normal means PTH-mediated. Suppressed (below about 20 pg/mL, assay-dependent) points to malignancy, vitamin D or another cause. In hypocalcemia, check magnesium, phosphate, PTH, 25-hydroxyvitamin D and creatinine.
- Escalate or dispose. Symptomatic hypocalcemia, a calcium infusion, or severe or symptomatic hypercalcemia needs a monitored bed. Involve endocrinology, oncology or nephrology, depending on the cause.
Corrected calcium: limits
Paired-sample studies are blunt about this. Plain total calcium agrees with ionized status at least as often as the corrected figure does. Correction goes wrong most when albumin is below 3 g/dL, in CKD and in ICU patients, and there it often hides true ionized hypocalcemia. Treat the patient and the ionized calcium. The formula comes last.
Pattern recognition
| Pattern | Suggests |
|---|---|
| High Ca, high or normal PTH, low phosphate | Primary hyperparathyroidism or lithium; low urine calcium suggests FHH |
| High Ca, suppressed PTH, high PTHrP | Humoral hypercalcemia of malignancy |
| High Ca, suppressed PTH, high vitamin D metabolites | High 1,25-dihydroxy: lymphoma or granulomatous disease; very high 25-hydroxy: vitamin D toxicity |
| High Ca, suppressed PTH, anemia, kidney injury | Myeloma: protein electrophoresis and free light chains |
| Low Ca, low or inappropriately normal PTH, high phosphate | Hypoparathyroidism (post-surgical is most common) |
| Low Ca, high PTH, high phosphate, high creatinine | CKD with secondary hyperparathyroidism |
| Low Ca, high PTH, low phosphate | Vitamin D deficiency |
| Low Ca with low Mg²⁺ | Magnesium-dependent hypocalcemia: replace Mg²⁺ first |
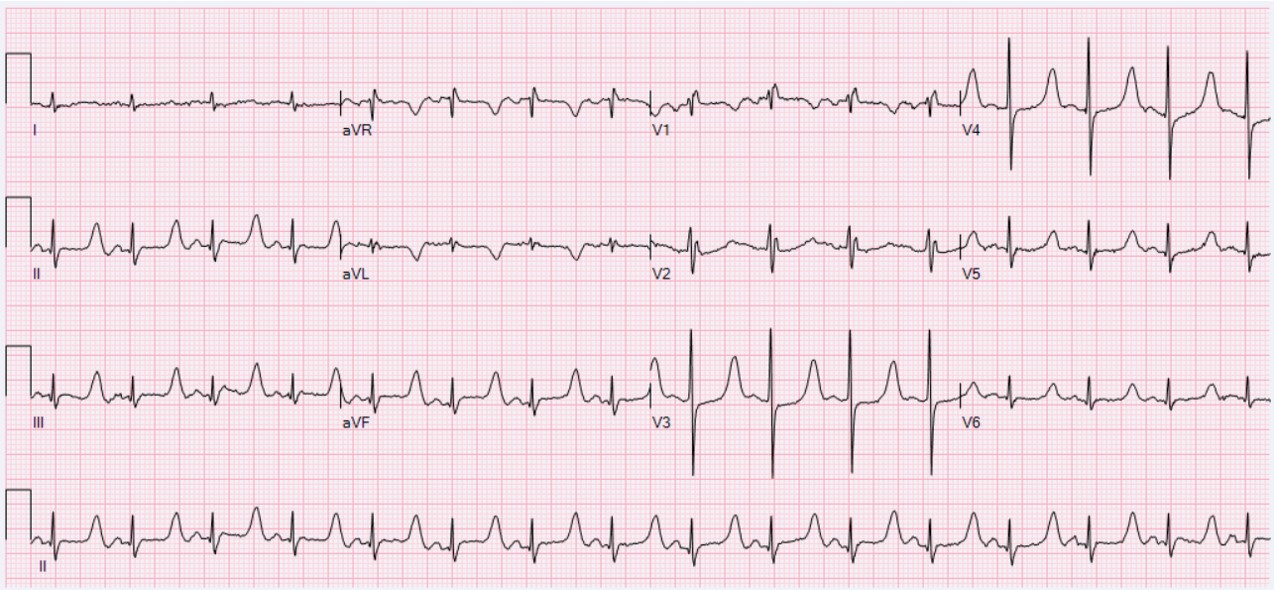
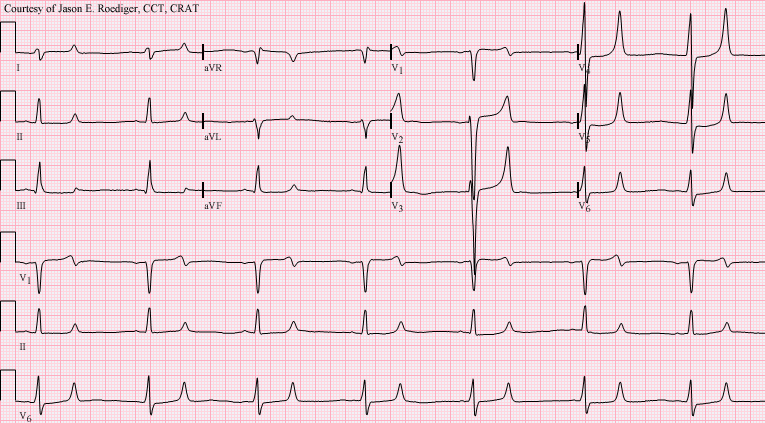
ECG changes
| Condition | ECG findings | Bedside meaning |
|---|---|---|
| Hypocalcemia | QT prolongation from a long ST segment; T wave itself often normal | Risk of torsades, worse with QT-prolonging drugs or low K⁺ or Mg²⁺ |
| Hypercalcemia | Short QT (short ST segment); bradycardia and AV block at high levels; J (Osborn) waves are rare | Short QT with confusion and dehydration: check calcium |
Management Priorities
Emergency: Symptomatic or severe hypocalcemia (tetany, seizure, laryngospasm, QT prolongation, or total Ca <7.6 mg/dL)
- Monitor: continuous ECG, airway (laryngospasm), seizure precautions, secure IV.
- Bolus calcium: calcium gluconate 1–2 g IV, diluted, over 10–20 min with ECG monitoring; repeat until symptoms settle. Calcium chloride only through a central line or IO, or in arrest. Digoxin or cardiac glycoside therapy: avoid if possible; otherwise give slowly in small aliquots with continuous ECG monitoring.
- Infuse and recheck: follow with a calcium gluconate infusion titrated to ionized calcium; check calcium every 1–4 hr on an infusion.
- Fix the driver: check and replace magnesium; treat the cause (hypoparathyroidism needs oral calcium plus calcitriol, vitamin D deficiency needs vitamin D).
Emergency: Hypercalcemic crisis (total Ca >14 mg/dL, or symptomatic: confusion, vomiting, AKI)
- Rehydrate: isotonic saline, tailored to cardiac and kidney function; target urine output 100–150 mL/hr.
- Stop the inputs: thiazides, lithium, calcium and vitamin D supplements, calcium-containing fluids.
- Lower calcium: calcitonin for a rapid effect plus an antiresorptive (IV bisphosphonate or denosumab) for a durable one; glucocorticoids first when calcitriol drives it (lymphoma, granulomatous disease, vitamin D toxicity).
- Refractory or kidney failure: nephrology for dialysis; loop diuretics only to treat volume overload after rehydration, not routinely.
Medications
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Calcium gluconate 10% (symptomatic hypocalcemia) | 1–2 g (10–20 mL) IV, diluted, over 10–20 min (max rate 200 mg/min); repeat every 6 hr as needed, or infuse 5.4–21.5 mg/kg/hr titrated to calcium | Over 1 month: 29–60 mg/kg IV (max 2 g/dose, the adult dose); neonate: 100–200 mg/kg; max rate 100 mg/min; infusion 8–13 mg/kg/hr (neonate 17–33) | Minutes; peripheral IV acceptable; low end of range in renal impairment |
| Calcium gluconate 10% (hyperkalemia with ECG changes) | 3 g (30 mL of 10%) IV over 10 min per UKKA 2026; repeat if ECG changes persist. Differs from FDA label: the US labels list only hypocalcemia and cap the rate (calcium gluconate 200 mg/min for adults, so 3 g takes at least 15 min; calcium chloride 1 mL/min, central or deep vein, no bolus). The hyperkalemia rate here (gluconate 30 mL over 10 min, chloride 10 mL over 5 min) is from UKKA 2026 and is off-label. The labeled bolus for hypocalcemia is 1–2 g (10–20 mL) over 10–20 min | 60 mg/kg (0.6 mL/kg of 10%) IV, max 3 g (the adult dose), per NASEMSO v3.0 (2022), Calcium Channel Blocker Poisoning, p. 296; the per-kg dose is not in AHA 2025 or the US label; label maximum rate 100 mg/min in pediatric patients | Onset 1–3 min, lasts 30–60 min; does not lower K⁺: start insulin-glucose at once |
| Calcium chloride 10% (calcium chloride; arrest or peri-arrest, massive transfusion) | 1 g (10 mL) IV over 5 min with central, deep or large proximal access, or in peri-arrest; IV/IO push in arrest; repeat by ECG or ionized calcium | 20 mg/kg (0.2 mL/kg of 10%) IV/IO slowly over 5 min, max 1 g per dose (NASEMSO v3.0, 2022: Cardiac Arrest p. 119; Crush Injury p. 223) | 3 times the calcium of gluconate per mL; central line or IO preferred. Differs from FDA label: the US labels list only hypocalcemia and cap the rate (calcium gluconate 200 mg/min for adults, so 3 g takes at least 15 min; calcium chloride 1 mL/min, central or deep vein, no bolus). The hyperkalemia rate here (gluconate 30 mL over 10 min, chloride 10 mL over 5 min) is from UKKA 2026 and is off-label. Arrest from suspected hyperkalemia: 2025 AHA Guidelines for CPR and ECC, Part 10, COR 2b, LOE C-LD (effectiveness not well established) |
| Calcium salts (calcium channel blocker poisoning) | Chloride 2 g (20 mL) or gluconate 6 g (60 mL) IV, then chloride 20–40 mg/kg/hr or gluconate 60–120 mg/kg/hr | Chloride 20 mg/kg (0.2 mL/kg of 10%) IV, max 2 g (the adult dose); gluconate 60 mg/kg (0.6 mL/kg), max 6 g; then the same infusion. Child doses per AHA 2025 Table 4. Differs: NASEMSO v3.0 (2022, Calcium Channel Blocker Poisoning, p. 296) caps the pediatric chloride bolus at 1 g. | Titrate to blood pressure; keep ionized calcium ≤1.5–2 times the upper limit; give with high-dose insulin and vasopressors. Doses: 2025 AHA Guidelines for CPR and ECC, Part 10, Table 4. Calcium for life-threatening CCB poisoning: COR 2a, LOE C-EO (Part 10, CCB recommendation 5) |
| Magnesium sulfate (low Mg²⁺ with hypocalcemia) | IV replacement per institutional protocol | 25–50 mg/kg IV (max 2 g) | High-alert Hypocalcemia will not correct until Mg²⁺ is replaced |
| Isotonic saline (hypercalcemia) | 1–2 L bolus, then 200–500 mL/hr to urine output 100–150 mL/hr; less in heart or kidney failure | Per pediatric fluid protocol and specialist advice; titrate to urine output: no fixed max | Immediate; watch for volume overload |
| Calcitonin salmon (hypercalcemia) | 4 units/kg IM or subcut every 12 hr; may increase to 8 units/kg every 12 hr (max 8 units/kg every 6 hr); limit to 48–72 hr | Not established in children: consult | Onset 4–6 hr; lowers calcium 1–2 mg/dL; tachyphylaxis |
| Zoledronic acid (hypercalcemia of malignancy) | 4 mg IV over at least 15 min; may repeat after 7 days | Not established in children: consult | Onset 48–72 hr; check renal function first; check calcium, magnesium and vitamin D beforehand and watch for hypocalcemia over the following days |
| Denosumab (hypercalcemia of malignancy) | 120 mg subcut; repeat on days 8 and 15, then every 4 weeks | Not established in children: consult | Onset 3–10 days; no renal dose change, but risk of severe hypocalcemia in advanced CKD (boxed warning on Prolia, same molecule): check calcium, magnesium and vitamin D first and monitor calcium closely |
Definitive care & disposition
- Hypocalcemia: ICU or step-down while on a calcium infusion or with airway or seizure risk; endocrinology after neck surgery.
- Hypercalcemia: admit severe or symptomatic patients; oncology for malignancy (treating the cancer controls recurrence); endocrine surgery referral for primary hyperparathyroidism; nephrology when dialysis is needed.
- Toxicology: poison center for calcium channel blocker poisoning and hydrofluoric acid exposure. For hydrofluoric acid skin burns, topical calcium gluconate gel is first-line; systemic toxicity can need large, repeated IV calcium titrated to ECG and ionized calcium.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
Cartridge blood-gas and chemistry analyzers measure ionized calcium on heparinized whole blood within minutes. The result depends on pH. Analyze the sample promptly and without air. Know whether your device reports measured or pH-normalized ionized calcium. No calcium result in the field? History and the ECG (long or short QT) carry the decision.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Blood products en route | Get ionized calcium before departure and with each blood gas; keep it in the normal range (1.12–1.32 mmol/L); give calcium on a separate line from blood |
| Calcium infusion running | Record the latest ionized calcium and time, use a pump and dedicated line, and check the site often for extravasation |
| After thyroid or parathyroid surgery | Perioral tingling or cramps are early hypocalcemia; note the surgery time and last calcium |
| Hypercalcemic crisis | Continue fluids, track urine output and mental status; ask what antiresorptive was given and when |
| Dialysis patient | A 12-lead ECG screens for both hyperkalemia and hypocalcemia; ask about missed sessions |
Scope notes
IV calcium is a Paramedic, RN and CCT intervention. Give it per local protocol and medical direction. Scope for boluses and infusions varies by state and agency.
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Wider and higher ranges; early neonatal hypocalcemia is common in preterm infants and infants of diabetic mothers | Use age-specific limits; NICU dosing differs; never give IV calcium with ceftriaxone in neonates |
| Children & adolescents | Upper limit higher than adult until adolescence; 22q11.2 deletion can present with hypocalcemic seizures | A total of 10.8 mg/dL may be normal in a toddler; seizures plus low calcium: treat and check PTH |
| Pregnancy | Albumin falls, so total calcium falls; ionized calcium stays normal | Judge with ionized calcium; magnesium sulfate for preeclampsia can cause hypermagnesemia that calcium reverses |
| Older adults | No clinically meaningful difference in range; more thiazide use, hyperparathyroidism and malignancy | Low albumin is common: check ionized calcium before treating a low total |
| CKD / dialysis | Low calcitriol, high phosphate, secondary hyperparathyroidism; corrected calcium least reliable | Use ionized calcium; avoid large-volume calcium infusions in end-stage kidney disease and follow nephrology advice |
| Liver disease | Low albumin; slow citrate clearance during transfusion | Total calcium misleads; expect ionized hypocalcemia with blood products |
| Other: critical illness | Ionized hypocalcemia is common in sepsis, burns and trauma | Measure ionized calcium; correct for symptoms, hemorrhage or hemodynamic instability |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| EDTA (lavender-top) contamination | ↓ total calcium, often with very high K⁺ | EDTA chelates calcium | Redraw; follow the order of draw |
| Prolonged tourniquet, fist clenching | ↑ total and ionized calcium | Hemoconcentration and local acidosis | Short tourniquet time; no pumping |
| Air in a blood-gas sample | ↓ ionized calcium | CO₂ loss raises pH, more calcium binds albumin | Expel air, cap, analyze promptly |
| Liquid or excess heparin in the syringe | ↓ ionized calcium | Heparin binds calcium; dilution | Use balanced-heparin blood-gas syringes, fill to the line |
Medications & supplements
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Citrate (blood products, CRRT, plasma exchange) | ↓ ionized calcium (true) | Citrate chelates calcium | Measure ionized, not total, calcium |
| Biotin (high-dose supplements) | False − or False + PTH; calcium itself unaffected | Interferes with biotin-streptavidin immunoassays | Ask about supplements; discuss timing with the lab |
Physiologic / biologic
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Low albumin | ↓ total; ionized often normal | Less protein-bound calcium | Measure ionized calcium |
| Paraprotein (myeloma) | ↑ total; ionized normal | Abnormal protein binds calcium | Measure ionized calcium |
| Alkalosis or acidosis | Alkalosis ↓ ionized; acidosis ↑ ionized | pH changes albumin binding | Read ionized calcium with the pH |
Common misinterpretations
- Treating a low total from low albumin when the ionized calcium is normal.
- Trusting a normal corrected calcium in an ICU or CKD patient with ionized hypocalcemia.
- Reading a toddler's 10.8 mg/dL as hypercalcemia against the adult range.
- Expecting IV calcium to lower K⁺. It doesn't. It only protects the heart.
Physiology & Test Basics
What it measures
This page covers serum total calcium and whole-blood ionized calcium. Total calcium (on the CMP and BMP) adds up three pools. Ionized calcium is about 50%, and it is the active form. Albumin-bound calcium is about 40%. Calcium complexed to citrate, phosphate and bicarbonate makes up about 10%. Only ionized calcium acts on nerves, muscle, the heart and clotting.
Physiology & regulation
- 99% of body calcium sits in bone. The blood holds about 1%.
- The parathyroid calcium-sensing receptor sees the drop and triggers PTH release.
- PTH pulls calcium out of bone, holds on to it in the kidney and drives calcitriol production.
- Calcitriol (1,25-dihydroxyvitamin D) pushes more calcium and phosphate through the gut.
- PTH needs magnesium to be secreted and to act.
- Ionized calcium steadies nerve and muscle membranes. It is also a clotting cofactor.
How it is measured
- Total calcium: Serum (gold or red top) or lithium-heparin plasma (green top) on a chemistry analyzer. Never from a lavender (EDTA) tube.
- Ionized calcium: Arterial or venous whole blood in a balanced-heparin blood-gas syringe. Seal it without air and analyze it promptly. Results come in minutes on blood-gas and point-of-care analyzers.
- Related tests: albumin, magnesium, phosphate, intact PTH, PTHrP, 25-hydroxy and 1,25-dihydroxyvitamin D, urine calcium.
Why it matters
In emergency and critical care, calcium disorders show up as seizures, laryngospasm, arrhythmia, confusion and dehydration. Ionized calcium steers resuscitation in hemorrhage, citrate exposure and calcium channel blocker poisoning. Total calcium can mislead in all three.
Clinical Pearls
References
- El-Hajj Fuleihan, G., Clines, G. A., Hu, M. I., Marcocci, C., Murad, M. H., Piggott, T., et al. (2023). Treatment of hypercalcemia of malignancy in adults: An Endocrine Society clinical practice guideline. Journal of Clinical Endocrinology & Metabolism, 108(3), 507–528. https://doi.org/10.1210/clinem/dgac621
- Walker, M. D., & Shane, E. (2022). Hypercalcemia: A review. JAMA, 328(16), 1624–1636. https://doi.org/10.1001/jama.2022.18331
- Turner, J., Gittoes, N., Selby, P., & Society for Endocrinology Clinical Committee. (2016). Society for Endocrinology endocrine emergency guidance: Emergency management of acute hypocalcaemia in adult patients. Endocrine Connections, 5(5), G7–G8. https://doi.org/10.1530/EC-16-0056
- Fresenius Kabi USA. (2026). Calcium Gluconate Injection, USP, for intravenous use: prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=8b77c3d2-992d-4261-8421-9cfd07328fbf
- Desgagnés, N., King, J. A., Kline, G. A., Seiden-Long, I., & Leung, A. A. (2025). Use of albumin-adjusted calcium measurements in clinical practice. JAMA Network Open, 8(1), e2455251. https://doi.org/10.1001/jamanetworkopen.2024.55251
- Rossaint, R., Afshari, A., Bouillon, B., Cerny, V., Cimpoesu, D., Curry, N., et al. (2023). The European guideline on management of major bleeding and coagulopathy following trauma: Sixth edition. Critical Care, 27, 80. https://doi.org/10.1186/s13054-023-04327-7
- Alfonzo, A., Harrison, A., Baines, R., Chu, A., Mann, S., & MacRury, M. (2026). Clinical practice guidelines: Treatment of acute hyperkalaemia in adults (updated July 2026). UK Kidney Association. https://www.ukkidney.org/sites/default/files/documents/FINAL%20VERSION%20-%20UKKA%20CLINICAL%20PRACTICE%20GUIDELINE%20-%20MANAGEMENT%20OF%20HYPERKALAEMIA%20IN%20ADULTS%20-%20UPDATED%20JULY%202026_0.pdf
- American Heart Association. (2025). 2025 AHA Guidelines for CPR and ECC, Part 8: Pediatric Advanced Life Support. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/pediatric-advanced-life-support
- American Heart Association. (2025). 2025 AHA Guidelines for CPR and ECC, Part 9: Adult Advanced Life Support. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/adult-advanced-life-support
- American Heart Association. (2025). 2025 AHA Guidelines for CPR and ECC, Part 10: Adult and Pediatric Special Circumstances of Resuscitation. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/adult-and-pediatric-special-circumstances-of-resuscitation
- Roizen, J. D., Shah, V., Levine, M. A., & Carlow, D. C. (2013). Determination of reference intervals for serum total calcium in the vitamin D-replete pediatric population. Journal of Clinical Endocrinology & Metabolism, 98(12), E1946–E1950. https://doi.org/10.1210/jc.2013-3105
- National Association of State EMS Officials. (2022). NASEMSO National Model EMS Clinical Guidelines, Version 3.0. https://nasemso.org/content.aspx?page_id=22&club_id=157064&module_id=701974
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.