

Bedside Snapshot
- Normal (Adult)
- 0.8–1.8 ng/dL (10–23 pmol/L)
Typical; assay-specific. Always read with TSH - Critical Values
- No universal critical value: interpret by trend and clinical context. Thyroid storm and myxedema coma are clinical diagnoses; FT4 does not grade them.
- High Suggests
- Graves disease, toxic nodular goiter
- Thyroiditis (incl. amiodarone type 2, postpartum)
- Excess or recent levothyroxine
- Artifact: heparin, biotin, FDH
- Low Suggests
- Primary hypothyroidism (TSH high): Hashimoto, post-ablation
- Central hypothyroidism (TSH low or normal)
- Nonthyroidal critical illness
- Amiodarone, lithium, checkpoint inhibitors
- Act Now If
- High FT4 + fever, delirium, HR ≥130 or heart failure: treat as thyroid storm; β-blocker, ICU.
Low FT4 + hypothermia, ↓LOC, bradycardia: myxedema coma; hydrocortisone, then IV levothyroxine. - Watch Out For
- Heparin and high-dose biotin falsely raise FT4. A high FT4 with a normal TSH in a well patient is usually artifact or a recent dose: repeat before treating.
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult | 0.8–1.8 ng/dL | 10–23 pmol/L | Typical immunoassay range; one commercial electrochemiluminescence assay reports 0.82–1.77 ng/dL |
| Pregnancy | Assay- and trimester-specific | — | Immunoassays read falsely high in pregnancy; use the lab’s trimester range and lean on TSH |
| Older adult | Same as adult | Same as adult | No separate band; interpret with TSH and illness |
| Neonate 0–3 days | 0.66–2.71 ng/dL | 8.5–34.9 pmol/L | Postnatal TSH surge; never compare with adult limits |
| Neonate 4–30 days | 0.83–3.09 ng/dL | 10.7–39.8 pmol/L | Confirmatory sample after an abnormal newborn screen |
| Infant 1–12 months | 0.48–2.34 ng/dL | 6.2–30.1 pmol/L | Age-specific band from the same assay |
| Child 1–5 years | 0.85–1.75 ng/dL | 10.9–22.5 pmol/L | — |
| Child 6–10 years | 0.90–1.67 ng/dL | 11.6–21.5 pmol/L | — |
| Adolescent 11–19 years | 0.93–1.60 ng/dL | 12.0–20.6 pmol/L | Adult band applies after 19 years |
Severity & critical values
| Level | Conventional | SI | What it means / typical findings |
|---|---|---|---|
| Normal FT4, abnormal TSH | 0.8–1.8 ng/dL | 10–23 pmol/L | Subclinical disease: high TSH = subclinical hypothyroidism; low TSH = subclinical hyperthyroidism or T3 toxicosis |
| Low | <0.8 ng/dL | <10 pmol/L | High TSH: overt primary hypothyroidism. Low or normal TSH: central hypothyroidism or nonthyroidal illness |
| High | >1.8 ng/dL | >23 pmol/L | Suppressed TSH: overt thyrotoxicosis. Normal or high TSH: artifact, recent levothyroxine dose, amiodarone; rarely a TSH-secreting adenoma |
| Neonatal congenital hypothyroidism | <0.39 / 0.39–0.78 / 0.78–1.17 ng/dL | <5 / 5–10 / 10–15 pmol/L | Severe / moderate / mild when TSH is high (ESPE 2021 grading); severe disease gets the highest starting dose |
| Critical | No universal value | — | Thyroid storm and myxedema coma are clinical diagnoses; the FT4 level confirms thyroid status but does not define severity |
Conversion: ng/dL × 12.87 = pmol/L
Causes of Abnormal Results
High (thyrotoxicosis, FT4 >1.8 ng/dL)
Overt thyrotoxicosis means high FT4 (and/or T3) and a suppressed TSH. Thyroid storm is a clinical diagnosis layered on top. It is not a higher FT4.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| TSH-receptor stimulation | Graves disease (most common cause of thyroid storm) | Diffuse goiter, eye signs; TSH-receptor antibodies (TRAb) positive |
| Autonomous nodules | Toxic multinodular goiter, toxic adenoma; iodine-induced (iodinated contrast, amiodarone type 1) | Nodular goiter; recent contrast load |
| Release of stored hormone (destructive thyroiditis) | Subacute (painful), painless and postpartum thyroiditis; amiodarone type 2 | Tender gland, recent delivery or amiodarone; usually self-limited |
| Exogenous hormone | Levothyroxine over-replacement, dose taken just before the draw, factitious use | Medication history; small or normal gland |
| hCG-driven | Gestational transient thyrotoxicosis with hyperemesis gravidarum | First trimester; resolves by about 18–19 weeks; no antithyroid drug |
| TSH-driven (rare) | TSH-secreting pituitary adenoma, resistance to thyroid hormone | TSH normal or high despite a high FT4; exclude assay interference first |
| Spurious (not true thyrotoxicosis) | Heparin, high-dose biotin, familial dysalbuminemic hyperthyroxinemia (FDH), anti-T4 antibodies | Well patient, TSH not suppressed; repeat on another platform |
| Ectopic thyroid tissue | Struma ovarii (rare) | Pelvic mass; no goiter on neck exam |
Low (hypothyroxinemia, FT4 <0.8 ng/dL)
Overt hypothyroidism means low FT4. Primary disease sends TSH high. Central disease leaves TSH low or inappropriately normal. Subclinical hypothyroidism is TSH high with FT4 still normal.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Decompensated hypothyroidism | Myxedema coma, usually long-standing untreated or undertreated disease plus a trigger | Altered mental status, hypothermia, bradycardia, hypoventilation, hyponatremia; older women in winter |
| Primary thyroid failure | Hashimoto thyroiditis (up to 85% in iodine-sufficient areas), radioactive iodine, thyroidectomy, neck radiation, iodine deficiency | TSH high; goiter or surgical scar |
| Drug-induced | Amiodarone, lithium, immune checkpoint inhibitors, tyrosine kinase inhibitors (sunitinib), excess antithyroid drug | Medication list; new oncology therapy |
| Central (pituitary or hypothalamic) | Pituitary tumor, surgery or radiation, Sheehan syndrome (postpartum pituitary infarction), traumatic brain injury, infiltrative disease | TSH low or normal; other pituitary deficits: check cortisol before giving levothyroxine |
| Nonthyroidal illness | Critical illness, starvation; dopamine and glucocorticoids suppress TSH | Low T3 first; FT4 normal or low in severe illness; TSH low, normal or briefly high in recovery |
| Congenital | Thyroid dysgenesis or dyshormonogenesis; central congenital hypothyroidism | Abnormal newborn screen; confirm with serum FT4 and TSH |
| Assay or binding effect | Phenytoin, carbamazepine (total and free T4 fall 20–40%) | TSH normal and patient euthyroid |
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Check for heparin given before the draw, high-dose biotin, a levothyroxine dose taken within a few hours, and pregnancy. A high FT4 with a normal TSH in a well patient is artifact until proven otherwise.
- How sick is the patient? Urgency comes from temperature, heart rate and rhythm, mental status, heart failure, glucose and sodium. The FT4 value does not set it.
- Read it with TSH. TSH points the way and FT4 confirms it, then grades it. Overt means FT4 is abnormal. Subclinical means FT4 is normal. In central disease TSH misleads, so FT4 is the marker to follow.
- Acute vs chronic and the trend. FT4 drops over days once antithyroid treatment starts. TSH can stay suppressed for weeks. So TSH is a poor judge of early response.
- Classify with named criteria. Suspected storm is scored with the Burch–Wartofsky Point Scale and the Japan Thyroid Association/Japan Endocrine Society (JTA/JES) criteria, per the 2026 ETA/BTA consensus. Neither one replaces your judgment.
- Escalate or dispose. Storm or myxedema coma: ICU and endocrinology now. Stable discordant results: repeat, ideally on a different assay, before labeling disease.
TSH and FT4 patterns
| TSH | Free T4 | Suggests | Next step |
|---|---|---|---|
| High | Low | Overt primary hypothyroidism | Look for myxedema features; start levothyroxine |
| High | Normal | Subclinical hypothyroidism, or recovery from illness | Repeat before labeling; TPO antibodies |
| Suppressed | High | Overt thyrotoxicosis | Assess for storm; TRAb, cause; β-blocker if symptomatic |
| Low | Normal | Subclinical hyperthyroidism or T3 toxicosis | Check free T3 |
| Low or normal | Low | Central hypothyroidism or nonthyroidal illness | Morning cortisol, pituitary review; in ICU, recheck after recovery |
| Normal or high | High | Assay interference, recent levothyroxine, amiodarone; rarely TSHoma or thyroid hormone resistance | Repeat on another platform; exclude interference before rare diagnoses |
| Normal | Normal | Euthyroid | — |
Thyroid storm scoring
| Tool | Threshold | Notes |
|---|---|---|
| Burch–Wartofsky Point Scale | <25 unlikely; 25–44 impending; ≥45 highly suggestive | Points for temperature, CNS, GI-hepatic, heart rate, heart failure, AF and a trigger; does not need lab results; may overcall storm in sepsis |
| JTA/JES criteria | Definite (TS1) or suspected (TS2) | Requires high FT3 and/or FT4 plus combinations of CNS change, fever ≥38°C (100.4°F), HR ≥130, heart failure, GI-hepatic signs |
Management Priorities
Emergency: Thyroid storm (thyrotoxicosis with fever, delirium, HR ≥130 or heart failure; Burch–Wartofsky ≥45)
- Support: ICU or high-dependency care, monitor, oxygen, IV fluids, cooling and acetaminophen; avoid aspirin (it raises free hormone). Watch glucose; give thiamine; pregnancy test. Treat the trigger.
- Block adrenergic effects: propranolol, or esmolol if cardiomyopathy, hypotension or shock is possible (get an echocardiogram early).
- Stop synthesis: high-dose methimazole or propylthiouracil; then iodide no sooner than 1 hr after the thionamide.
- Block conversion and support: IV hydrocortisone; consider cholestyramine. Refractory: plasma exchange, thyroidectomy, VA-ECMO for cardiogenic shock.
Emergency: Myxedema coma (low FT4 with altered mental status, hypothermia, bradycardia or hypoventilation)
- Airway and breathing: hypoventilation and CO₂ retention are common; ventilation may be needed for days to weeks.
- Steroid first: stress-dose hydrocortisone before or with thyroid hormone until adrenal insufficiency is excluded.
- IV levothyroxine: loading dose then daily IV maintenance; lower end in older or cardiac patients. Some protocols use a smaller load for older, cardiac or low-weight patients, so follow endocrinology and local protocol. Oral absorption is unreliable.
- Supportive care: passive rewarming (active external warming can drop blood pressure), treat hypoglycemia and hyponatremia, broad-spectrum antibiotics, stop sedatives.
Medications
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Propranolol (storm) | 60–80 mg PO/NG every 4 hr; IV 1–3 mg at ≤1 mg/min; repeat once after 2 min; no further IV dose for at least 4 hr after the repeat (label) | Not established in children: consult | Start lower if heart failure is suspected; high doses also slow T4-to-T3 conversion. IV dosing is the label's arrhythmia dose, not a storm-specific one. IV: High-alert |
| Esmolol (storm) | 500 mcg/kg IV over 1 min (optional), then 50 mcg/kg/min, titrated in steps to HR (max 200 mcg/kg/min) | Not established in children: consult | Preferred with suspected thyrotoxic cardiomyopathy, hypotension or shock: switch off in minutes. High-alert |
| Methimazole (storm) | 60–80 mg/day PO/NG; reduce to 30 mg/day once stable | Not routinely used (consult) | Favored if transaminases or bilirubin >3× ULN; PTU preferred in the first trimester. Methimazole carries first-trimester fetal risk (aplasia cutis, choanal atresia) |
| Propylthiouracil (PTU, storm) | 500–1,000 mg PO/NG/PR load, then 250 mg every 4 hr; reduce to 400 mg/day once stable | Not routinely used (consult) | Boxed warning: severe liver injury and acute liver failure. Reserve for methimazole intolerance (or when radioiodine or surgery is unsuitable) and for the first trimester. Also blocks T4-to-T3 conversion |
| Iodide (storm) | SSKI 5 drops or Lugol solution 8 drops PO/NG four times daily, diluted in milk or juice; start ≥1 hr after the thionamide; stop once stable | Not routinely used (consult) | Useless in destructive thyroiditis; delays radioactive iodine for 2–3 months |
| Hydrocortisone | Storm: 100 mg IV, then 50 mg IV every 6 hr (protocol-dependent; older guidance used higher doses). Myxedema coma: 100 mg IV every 8 hr until adrenal insufficiency is excluded | Not established for thyroid storm in children: consult | Stop once stable if adrenal function is adequate. Monitor K⁺ (thyrotoxic periodic paralysis) and glucose |
| Cholestyramine (storm adjunct) | 4 g PO three times daily (off-label) | Not routinely used (consult) | Interrupts enterohepatic recycling of thyroid hormone; binds other oral drugs, including levothyroxine, so separate doses |
| Levothyroxine IV (myxedema coma) | 300–500 mcg IV load (label; lower end if older or cardiac), then 50–100 mcg IV daily until oral intake (max load 500 mcg) | Not established in children: consult | Lyophilized powder: reconstitute with 5 mL 0.9% saline per label; give by direct IV injection, never added to IV fluids. Doses >500 mcg: arrhythmia, ischemia |
| Levothyroxine PO (hypothyroidism) | Full replacement about 1.6 mcg/kg/day; start lower in older or cardiac patients (doses >200 mcg/day seldom needed) | 0–3 mo 10–15 mcg/kg/day; 3–6 mo 8–10; 6–12 mo 6–8; 1–5 y 5–6; 6–12 y 4–5; >12 y, growth incomplete 2–3 mcg/kg/day (titrate to TSH and FT4) | Not for myxedema coma. Congenital hypothyroidism: start within 2 weeks of birth |
Definitive care & disposition
- ICU criteria (storm): vasopressor need, depressed consciousness, ventilatory support, acute heart failure or arrhythmia, multi-organ dysfunction or rapid deterioration. Expect improvement within 24–72 hr; failure by 24–48 hr prompts reassessment.
- After storm: continue thionamide and β-blocker while thyrotoxic; plan definitive therapy (radioactive iodine or thyroidectomy) before discharge.
- Myxedema coma: ICU admission; recovery of temperature and mental status can take days. Switch to oral levothyroxine when the patient can take it and recheck TSH and FT4 a few weeks later.
- Consults: endocrinology for both emergencies; obstetrics and neonatology if pregnant; pediatric endocrinology for any child.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | FT4 and TSH run higher in the first weeks after birth | Use age-specific ranges. Abnormal newborn screen: serum FT4 and TSH; treat at once if FT4 is low and TSH high |
| Children & adolescents | Ranges narrow toward adult values | On levothyroxine, a high FT4 with a normal TSH is acceptable; do not cut the dose on one high FT4 |
| Pregnancy | TBG rises, hCG lowers TSH in the first trimester, and immunoassays overestimate FT4 | Use trimester-specific ranges; levothyroxine needs rise (often 30–50%); gestational thyrotoxicosis needs no antithyroid drug |
| Older adults | Same range; more cardiac disease | Thyrotoxicosis may be apathetic; start levothyroxine lower and use the lower IV load in myxedema coma |
| Critical illness | Nonthyroidal illness lowers T3, then FT4; dopamine and steroids lower TSH | Test only when thyroid disease is suspected; low FT4 here signals severity, not a reason for thyroid hormone |
| Central hypothyroidism | TSH is unreliable | Dose levothyroxine to FT4 in the upper half of normal; exclude adrenal insufficiency first |
| Other (amiodarone) | FT4 often high-normal or high with normal TSH in euthyroid patients | Judge by TSH, T3 and symptoms; true amiodarone thyrotoxicosis (type 1 or 2) or hypothyroidism needs specialist care |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Heparin given before the draw | ↑ (False +) | Activates lipoprotein lipase; free fatty acids made in the tube displace T4 | Draw before heparin or well after it; tell the lab |
| Levothyroxine taken shortly before the draw | ↑ | Post-dose peak | Draw before the daily dose or at least 4 hr after it |
| Wrong tube | Rejected or unreliable | EDTA, citrate and oxalate plasma not validated for many assays | Serum (red or gold top) or lithium heparin plasma, per lab |
Medications & supplements
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Biotin (high-dose supplements) | ↑ FT4 (False +) with ↓ TSH | Interferes with streptavidin–biotin immunoassays; mimics hyperthyroidism | Stop biotin before testing (at least 2 days); follow lab guidance |
| Amiodarone | ↑ FT4, ↓ or normal T3 | Blocks T4-to-T3 conversion | Expected in euthyroid patients; use TSH and the clinical picture |
| Salicylates >2 g/day, furosemide >80 mg IV, fenamate NSAIDs | Transient ↑ | Displace T4 from binding proteins | Interpret with timing; repeat later |
| Phenytoin, carbamazepine | ↓ (False −) | Reduce protein binding; total and free T4 fall 20–40% | Usually euthyroid with normal TSH |
| Propranolol >160 mg/day, dexamethasone >4 mg/day | ↓ T3, T4 little changed | Block T4-to-T3 conversion | Expected; no treatment |
Physiologic / biologic & assay
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Familial dysalbuminemic hyperthyroxinemia (FDH) | ↑ (False +) | Albumin variant binds T4 avidly; indirect assays overestimate | Different method; family testing, genetic confirmation |
| Anti-T4, heterophile or anti-reagent antibodies | Usually ↑ | Antibodies bind tracer or assay reagents | Repeat on another platform; specialist lab |
| Pregnancy | ↑ vs reference method | Binding-protein changes distort immunoassays | Trimester-specific ranges; rely on TSH |
| Immunoassay vs reference method | Variable | Methods disagree, most at high FT4; equilibrium dialysis and mass spectrometry are reference methods | Trend on the same lab and method |
Levothyroxine absorption and monitoring
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Proton pump inhibitors | ↓ absorption | Higher gastric pH reduces T4 absorption | Take levothyroxine alone on an empty stomach; recheck TSH after starting or stopping |
| Calcium, iron | ↓ absorption | Bind T4 in the gut | Separate by about 4 hr |
| Cholestyramine, colestipol | ↓ absorption | Bile acid sequestrants bind T4 | Separate by about 4–6 hr |
| Soy products, dietary fiber | ↓ absorption | Reduce uptake of T4 when taken together | Take levothyroxine apart from them |
| Rifampin, phenytoin, carbamazepine, phenobarbital | ↑ requirement | Speed hepatic T4 clearance | Expect a higher dose; recheck TSH |
On levothyroxine, TSH is the test that matters most. Recheck it 6–8 weeks after any dose change. Recheck sooner after starting or stopping an interacting drug. An FT4 in the upper half of the reference range is common on therapy.
Common misinterpretations
- A high FT4 with a normal TSH is not hyperthyroidism until heparin, biotin, a recent dose and interference are excluded.
- Dismissing low FT4 with a low TSH as “not hypothyroid” misses central disease. Cortisol testing comes first.
- TSH tells you little in the first days of storm treatment. Follow the patient, FT4 and free T3.
- Starting thyroid hormone for nonthyroidal illness in the ICU is the wrong move.
Physiology & Test Basics
What it measures
Free T4 is the unbound thyroxine in serum. That fraction is available to the tissues. This page covers free T4. Total T4 adds the bound hormone to the free, and T4 compares the two. Over 99.9% of T4 is protein-bound (label: 99.96%). Binding changes move total T4 far more than FT4 does.
Physiology & regulation
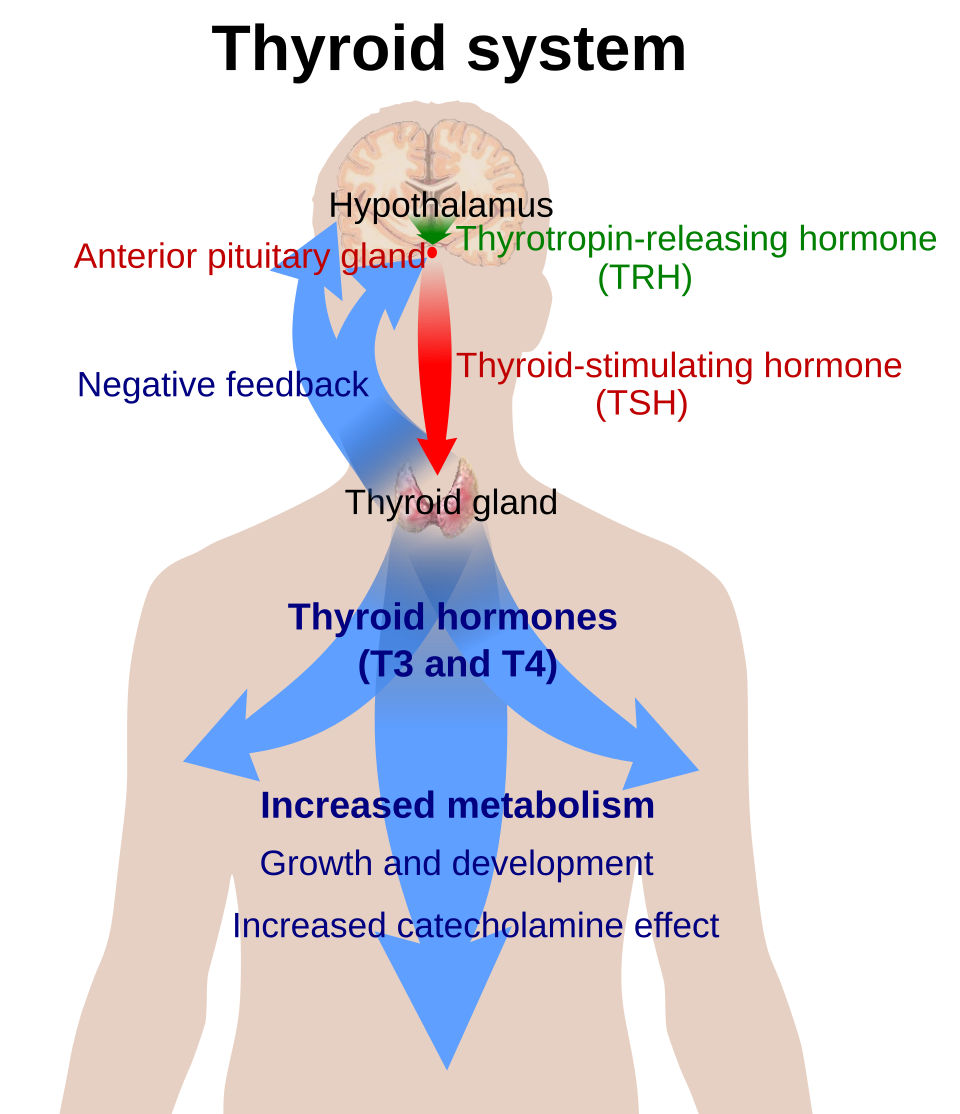
- Axis: hypothalamic TRH drives pituitary TSH. TSH drives thyroid T4 and T3. Both feed back to shut down TRH and TSH.
- Binding proteins: thyroxine-binding globulin (TBG), transthyretin and albumin carry the hormone. Pregnancy, estrogen and hepatitis push TBG up. Nephrosis, severe liver disease, androgens and corticosteroids push it down.
- Prohormone: About 80% of circulating T3 is made from T4 out in the periphery, by deiodination. T3 is about 4 times as potent.
- Half-life: The T4 half-life runs about 6–8 days. It is 9–10 days in hypothyroidism and 3–4 days in hyperthyroidism. So recheck TSH 6–8 weeks after a dose change.
- Pattern: Primary disease moves TSH opposite to FT4. Central disease moves them together. TSH misleads there, so FT4 is the marker.
How it is measured
- Specimen: serum (red or gold top) or lithium heparin plasma, per lab; not EDTA, citrate or oxalate. No fasting needed.
- Method: Most labs run an automated competitive immunoassay. Specialist labs use equilibrium dialysis or ultrafiltration with mass spectrometry.
- Timing: Draw before the daily levothyroxine dose, and not during or soon after heparin. FT4 is usually a core-lab test, and point-of-care options are limited.
Why it matters
Once TSH is abnormal, FT4 confirms the dysfunction and grades it. When the pituitary is the problem, FT4 is the only reliable marker. In the ED and ICU it supports the clinical diagnosis of thyroid storm and myxedema coma. It never replaces that diagnosis.
Clinical Pearls
References
- Taylor, P., Okosieme, O., Effraimidis, G., Gibb, F., Parekh, D., Moran, C., Kopp, P., & Boelaert, K. (2026). Management of thyroid emergencies: Joint consensus statement on management of thyroid storm. European Thyroid Journal, 15(4), ETJ260043. https://doi.org/10.1530/ETJ-26-0043
- Campi, I., Feldt-Rasmussen, U., Gruson, D., Halsall, D., Raverot, V., van den Berg, S., & Moran, C. (2026). 2026 ETA guideline on interference in immunoassay measurements used in assessment of thyroid function. European Thyroid Journal, 15(4), ETJ260011. https://doi.org/10.1530/ETJ-26-0011
- Zhang, Y., Chu, L., & Han, H. (2025). Myxedema coma: Challenges and future directions, a systematic survey and review. Thyroid Research, 18, 48. https://doi.org/10.1186/s13044-025-00268-1
- Ross, D. S., Burch, H. B., Cooper, D. S., Greenlee, M. C., Laurberg, P., Maia, A. L., Rivkees, S. A., Samuels, M., Sosa, J. A., Stan, M. N., & Walter, M. A. (2016). 2016 American Thyroid Association guidelines for diagnosis and management of hyperthyroidism and other causes of thyrotoxicosis. Thyroid, 26(10), 1343–1421. https://doi.org/10.1089/thy.2016.0229
- Jonklaas, J., Bianco, A. C., Bauer, A. J., Burman, K. D., Cappola, A. R., Celi, F. S., Cooper, D. S., Kim, B. W., Peeters, R. P., Rosenthal, M. S., Sawka, A. M., & American Thyroid Association Task Force on Thyroid Hormone Replacement. (2014). Guidelines for the treatment of hypothyroidism: Prepared by the American Thyroid Association Task Force on Thyroid Hormone Replacement. Thyroid, 24(12), 1670–1751. https://doi.org/10.1089/thy.2014.0028
- MAIA Pharmaceuticals. (2026). Levothyroxine sodium for injection, for intravenous use: Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=4e9adc35-3aba-4a0d-9c4e-7e7ee2ffdabd
- van Trotsenburg, P., Stoupa, A., Léger, J., Rohrer, T., Peters, C., Fugazzola, L., et al. (2021). Congenital hypothyroidism: A 2020–2021 consensus guidelines update. An ENDO-European Reference Network initiative endorsed by the European Society for Pediatric Endocrinology and the European Society for Endocrinology. Thyroid, 31(3), 387–419. https://doi.org/10.1089/thy.2020.0333
- Labcorp. (2026). Thyroxine (T4), free, direct, serum (test 001974): Reference intervals and specimen requirements. https://www.labcorp.com/tests/001974/thyroxine-t-sub-4-sub-free-direct-serum
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.