

Bedside Snapshot
- Normal (Adult)
- 5–40 U/L (0.08–0.67 µkat/L); lab-specific. Men run higher than women. Newborns run several times higher; GGT does not rise in normal pregnancy.
- Critical Values
- No universal critical value: interpret by trend and clinical context. Critical by context: GGT and ALP rising with fever, jaundice or RUQ pain (cholangitis).
- High Suggests
- Biliary obstruction or cholangitis
- Alcohol, obesity, MASLD, diabetes
- Phenytoin, carbamazepine, phenobarbital
- Sepsis or prolonged ketamine cholangiopathy
- Low Suggests
- Rarely clinically significant in adults (oral contraceptives lower it). In a jaundiced infant or child, a normal or low GGT suggests an inherited bile acid disorder.
- Act Now If
- High GGT and ALP with fever or rigors plus jaundice or RUQ pain, or hypotension: treat as cholangitis: sepsis care, blood cultures, early antibiotics, urgent drainage consult; notify receiving/medical control
- Watch Out For
- A high GGT is not proof of drinking, and a normal one does not exclude it: obesity, diabetes and enzyme-inducing drugs raise it too. Use PEth to confirm alcohol use.
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult | 5–40 U/L | 0.08–0.67 µkat/L | Typical. Men run higher than women, so many labs report sex-specific limits; use your lab's upper limit of normal (ULN). |
| Pregnancy | Not raised | — | Unlike alkaline phosphatase (ALP), no placental rise; values are similar to or slightly below non-pregnant values. |
| Older adult | Similar to adult | — | Regular drinking raises GGT at lower intakes after age 40. |
| Neonate & young infant | Several times the adult ULN at birth | — | Falls toward adult values over the first months of life; use age-specific intervals. |
| Child & adolescent | Close to the adult range | — | Use the lab's age-specific interval. Unlike ALP, GGT does not rise with growth. |
Severity & critical values
| Level | Conventional | SI | What it means |
|---|---|---|---|
| Normal | 5–40 U/L | 0.08–0.67 µkat/L | Adult. |
| Raised, isolated | >40 U/L; ALP, ALT, AST and bilirubin normal | >0.67 µkat/L | Most often alcohol, obesity or metabolic liver disease, or enzyme-inducing drugs. Take the history before imaging. |
| Cholestatic | >1.5× ULN (>60 U/L) | >1.00 µkat/L | Meets the abnormal-liver-test item of the Tokyo Guidelines 2018 (TG18) cholestasis criterion for acute cholangitis. Usually rises with ALP. |
| Raised with hazardous drinking | Persistently raised; no fixed cutoff | — | Per the British Society of Gastroenterology (BSG) 2018 guideline, assess for liver fibrosis. |
| Critical | No numeric critical value | — | Critical by context: see the warning below. |
Conversion: U/L × 0.0167 = µkat/L
Causes of Abnormal Results
High (GGT above the lab's ULN, adult >40 U/L)
There is no standard severity grade. Look at the company GGT keeps (ALP, ALT, bilirubin) and at the patient. Those matter more than the number.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
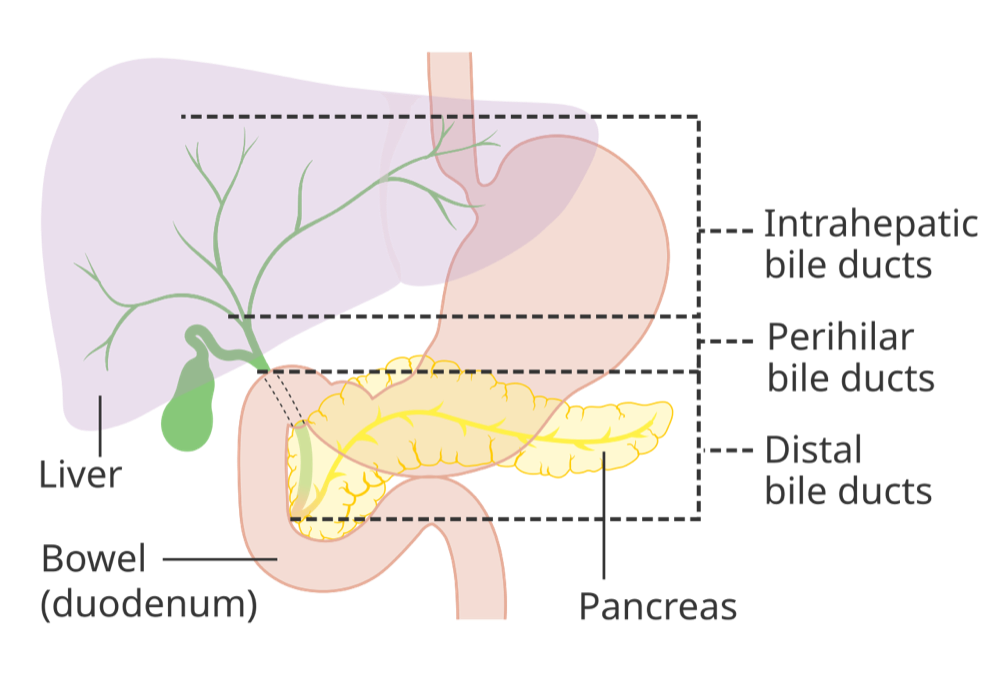
| Extrahepatic biliary obstruction | Common bile duct stones, acute cholangitis, pancreatic or bile duct cancer, stricture, blocked stent | RUQ pain, jaundice, dark urine, pale stools; fever or rigors = cholangitis until proven otherwise; ALP rises in parallel; dilated ducts |
| Intrahepatic cholestasis | Drug-induced liver injury (DILI), primary biliary cholangitis (PBC), primary sclerosing cholangitis (PSC), infiltration (metastases), hepatic congestion | New drug or supplement; pruritus; inflammatory bowel disease (PSC); raised neck veins and edema (heart failure) |
| Critical illness | Sepsis, secondary sclerosing cholangitis after shock or a long ICU stay, prolonged or high-dose ketamine | ICU, burns or severe ARDS; GGT and ALP climbing over days to weeks, often with rising bilirubin |
| Alcohol | Regular drinking (enzyme induction), alcohol-associated hepatitis or cirrhosis | Positive AUDIT-C screen; AST higher than ALT; high mean corpuscular volume (MCV) |
| Metabolic | Obesity, metabolic dysfunction-associated steatotic liver disease (MASLD, formerly NAFLD), type 2 diabetes | High body mass index (BMI) or waist, diabetes; ALT often mildly raised |
| Enzyme-inducing drugs | Phenytoin, carbamazepine, phenobarbital | Medication list; other liver tests normal |
| Hepatocellular disease | Viral hepatitis, cirrhosis, liver cancer, ischemic liver injury | ALT and AST clearly raised; GGT rise is secondary |
| Other organs | Pancreatic disease, heart failure, lung disease | Pancreatitis or a pancreatic mass can also obstruct the bile duct |
Low (below the lab's lower limit)
A low GGT rarely matters in adults, and no adult disease is diagnosed from one. The jaundiced infant or child is the exception.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Drug effect | Oral contraceptives | Medication history; no action needed |
| Low-GGT cholestasis (children) | Inherited disorders of bile acid synthesis or transport | Jaundice and pruritus with conjugated hyperbilirubinemia, yet GGT normal or low: refer to pediatric hepatology |
Interpretation & Bedside Approach
Step-by-step approach
- Is it real and is it new? Per the BSG 2018 guideline, interpret it against previous results, history and current illness. Redraw a grossly hemolyzed sample.
- How sick is the patient? Fever, jaundice, RUQ pain, hypotension or confusion: think cholangitis. Encephalopathy with a rising INR points to acute liver failure, and GGT adds little there.
- Read it with ALP. Both ALP and GGT high: the ALP came from the liver or biliary tree. ALP high with a normal GGT: think bone, growth or pregnancy (placental ALP).
- Name the pattern. ALT/AST-predominant is hepatocellular; ALP/GGT-predominant is cholestatic. Use the R ratio on the ALP page to classify mixed results.
- Cholestatic: image the biliary tree. RUQ ultrasound first. Dilated ducts or fever: urgent gastroenterology or surgical review for drainage.
- Isolated GGT: take the history. Start with alcohol (AUDIT-C), weight, diabetes and the medication list. Under BSG 2018, a persistently raised GGT with hazardous drinking calls for a liver fibrosis assessment. A raised ALT or GGT with metabolic risk factors can mean MASLD, even when the ultrasound is normal.
- Trend beats a single value. After drainage, or after a culprit drug or drinking stops, GGT should fall. In heavy drinkers it typically falls over the first few weeks of abstinence. Full normalization can take longer, especially with obesity or liver disease. A value that stays high points to liver disease or ongoing exposure.
Pattern recognition
| Pattern | Suggests |
|---|---|
| GGT ↑, ALP ↑ | Hepatobiliary cholestasis: obstruction, drugs, PBC, PSC, infiltration, congestion |
| GGT normal, ALP ↑ | Bone, growth or pregnancy; not liver |
| GGT ↑ alone | Alcohol, obesity or MASLD, diabetes, enzyme-inducing drugs |
| GGT ↑ (>1.5× ULN), fever or rigors, jaundice or RUQ pain | Acute cholangitis (TG18: inflammation plus cholestasis or imaging = suspected; all three = definite) |
| GGT and ALP climbing on prolonged or repeated ketamine | Ketamine cholangiopathy: stop ketamine and refer |
| Cholestatic infant, GGT normal or low | Inherited bile acid synthesis or transport disorder |
GGT as an alcohol marker
GGT is an indirect marker. It reflects weeks of regular drinking and liver stress, not the last drink. The 2024 American College of Gastroenterology (ACG) alcohol-associated liver disease guideline rates indirect markers (GGT, MCV, carbohydrate-deficient transferrin) as highly variable between individuals and of limited use. The same guideline says direct markers perform better.
| Marker | Specimen | Window | Use |
|---|---|---|---|
| Phosphatidylethanol (PEth) | Blood | About 30 days | Direct marker; useful to confirm or monitor drinking |
| Ethyl glucuronide (EtG) / ethyl sulfate (EtS) | Urine | 3–7 days | Direct markers of recent drinking |
| Carbohydrate-deficient transferrin (CDT) | Blood | 2–4 weeks | Indirect; more specific than GGT, less sensitive |
| GGT | Blood | Falls over the first weeks of abstinence; slower to normalize with obesity or liver disease | Indirect; raised by obesity, MASLD and drugs too |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | GGT is several times the adult ULN at birth and falls over the first months. | A "high" newborn GGT can be normal. Any infant jaundiced after 2 weeks of age needs total and direct bilirubin; direct bilirubin >1 mg/dL (>17 µmol/L) needs prompt evaluation, because biliary atresia is the leading cause. |
| Children & adolescents | Near adult values; ALP is high from growth. | GGT is the better marker of biliary disease in children. Cholestasis with a normal or low GGT points to an inherited disorder. |
| Pregnancy | No placental rise; similar to or slightly below non-pregnant values. | A high ALP with a normal GGT is expected late in pregnancy; a high GGT needs a cause. |
| Older adults | Over age 40, about 8 standard drinks a week in men and 4 in women can begin to raise GGT; women react at lower intakes at any age. | Ask about alcohol even when intake sounds modest. |
| Liver disease | Tracks with ALP in PBC and PSC. | Trend it with ALP and bilirubin; a new rise in known biliary disease suggests a new obstruction. |
| Critically ill | Sepsis, shock and prolonged high-dose ketamine sedation can cause cholangiopathy. | Trend liver tests during long ICU stays and report a climbing cholestatic pattern early. |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Gross hemolysis | Unreliable | Assay interference; many labs reject the sample | Redraw with a clean venipuncture |
| Tube type | Varies | Accepted tubes differ by lab and analyzer | Serum (gold or red top) or lithium-heparin plasma (green top) unless your lab says otherwise |
| Delayed transport | Minimal | Stable for about 1 week after separation, refrigerated or at room temperature | Separate within 2 hours when sending out |
Medications & substances
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Phenytoin, carbamazepine, phenobarbital | ↑ | Enzyme induction | Expected; on its own does not mean liver injury |
| Acetaminophen | ↑ (weak association) | Listed among drugs that raise GGT; overdose or chronic high dose can cause hepatotoxicity | Check the dose and ALT/AST for toxicity |
| Regular alcohol | ↑ | Induction and liver injury | History; PEth if confirmation matters |
| Ketamine, repeated or prolonged | ↑ (often marked) | Cholangiopathy, sometimes sclerosing cholangitis | Baseline and periodic ALP and GGT; stop ketamine if grossly raised |
| Oral contraceptives | ↓ | Lower measured GGT | None needed |
| Regular coffee | ↓ | Coffee drinkers, including heavy drinkers, tend to have lower GGT | Do not read a normal GGT as proof of light drinking |
Physiologic & biologic
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Obesity, diabetes, MASLD | ↑ | Fatty liver and oxidative stress | Weight and metabolic history before blaming alcohol |
| Smoking | ↑ | Adds to the effect of alcohol on GGT | Ask about tobacco |
Common misinterpretations
- "High GGT means drinking": obesity, MASLD, diabetes and drugs are at least as common as drinking.
- "Normal GGT rules out heavy drinking": GGT needs sustained heavy intake before it rises. It also varies widely from person to person.
- "One drink last night explains it": GGT reflects weeks of regular intake. It takes weeks to fall.
- "GGT measures liver function": it tracks injury and induction. Liver function is measured by the INR, albumin and bilirubin.
Physiology & Test Basics
What it measures
The liver and biliary tree release a membrane-bound enzyme. Serum GGT (gamma-glutamyl transferase, also called gamma-glutamyl transpeptidase or GGTP) measures the activity of that enzyme. This page covers GGT. The ALP page covers the enzyme GGT is most often ordered to explain.
Physiology & regulation
- Function: It moves gamma-glutamyl groups around in glutathione metabolism. That is why it also tracks oxidative stress.
- Tissues: The liver is rich in it. Kidney, intestine, prostate and pancreas have it too. Not in bone, so it separates liver from bone ALP.
- Cholestasis: Bile duct and canalicular injury push it up, usually along with ALP.
- Induction: Alcohol and some anticonvulsants turn up its production. That can happen without necessarily injuring the liver.
How it is measured
- Specimen: serum (gold or red top) or lithium-heparin plasma (green top); accepted tubes vary by lab.
- Method: automated enzyme-activity assay on the chemistry analyzer. Part of many hospital liver panels but not of the standard comprehensive metabolic panel; order it when ALP is high.
- Fasting: not required.
- Point of care: not available in the field.
Why it matters
GGT tells you if a high ALP is biliary. A cholestatic rise with fever is the lab face of cholangitis, a cause of septic shock that needs drainage. In the ICU, a climbing GGT flags sepsis cholestasis or ketamine injury. A raised GGT is also linked to higher liver-related and all-cause mortality.
Clinical Pearls
References
- Newsome PN, Cramb R, Davison SM, et al. (2018). Guidelines on the management of abnormal liver blood tests. Gut, 67(1), 6–19. https://doi.org/10.1136/gutjnl-2017-314924
- Jophlin LL, Singal AK, Bataller R, et al. (2024). ACG Clinical Guideline: Alcohol-Associated Liver Disease. American Journal of Gastroenterology, 119(1), 30–54. https://doi.org/10.14309/ajg.0000000000002572
- Niemelä O. (2016). Biomarker-based approaches for assessing alcohol use disorders. International Journal of Environmental Research and Public Health, 13(2), 166. https://doi.org/10.3390/ijerph13020166
- Kiriyama S, Kozaka K, Takada T, et al. (2018). Tokyo Guidelines 2018: diagnostic criteria and severity grading of acute cholangitis. Journal of Hepato-Biliary-Pancreatic Sciences, 25(1), 17–30. https://doi.org/10.1002/jhbp.512
- Fawaz R, Baumann U, Ekong U, et al. (2017). Guideline for the evaluation of cholestatic jaundice in infants: joint recommendations of NASPGHAN and ESPGHAN. Journal of Pediatric Gastroenterology and Nutrition, 64(1), 154–168. https://doi.org/10.1097/MPG.0000000000001334
- Par Health USA. (2026). KETALAR (ketamine hydrochloride) injection: prescribing information, section 5.6 Drug-Induced Liver Injury. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=14e8f864-8b8a-4e7e-8439-e510d3107063
- MedlinePlus, U.S. National Library of Medicine. (2025). Gamma-glutamyl transferase (GGT) blood test. https://medlineplus.gov/ency/article/003458.htm
- ARUP Laboratories. (2025). Gamma Glutamyl Transferase, Serum or Plasma (test 0020009). ARUP Laboratory Test Directory. https://ltd.aruplab.com/Tests/Pub/0020009
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.