

Bedside Snapshot
- Use It For
- AF or atrial flutter with rapid ventricular response (stable, no pre-excitation, LVEF >40%); stable narrow, regular PSVT when vagal maneuvers and adenosine fail or are unsuitable
- Adult Dose
- Bolus: 0.25 mg/kg IV over 2 min (about 20 mg)
- At 15 min if needed: 0.35 mg/kg IV over 2 min (about 25 mg)
- AF/flutter infusion: 5–10 mg/hr by product label, up by 5 mg/hr (max 15 mg/hr, 24 hr)
- Pediatric Dose
- Not established in children: specialist/medical-control use only; avoid in infants. Pediatric SVT: vagal maneuvers, adenosine, or synchronized cardioversion if unstable (PALS)
- Onset / Duration
- IV bolus: ≤3 min (peak 2–7 min) / 1–3 hr. After an infusion stops: 0.5 to over 10 hr (median 7 hr). PO IR: 30–60 min / dosed every 6 hr
- Do Not Give / Hold If
- Pre-excited AF/flutter (WPW); wide QRS not proven SVT; HFrEF, decompensated HF or ACS; SBP <90 mmHg or shock; sick sinus or 2nd/3rd-degree AV block without pacer; IV beta-blocker within hours
- Watch For
- Hypotension (frequent BP); bradycardia, pauses or AV block (continuous ECG); worsening heart failure (crackles, SpO₂); VF if the rhythm was pre-excited or VT (defibrillator ready)
- Reversal / Rescue
- No specific antidote. Stop it; fluids; vasopressors and high-dose insulin for hypotension; calcium chloride 2 g IV (Class 2a); atropine or pacing for bradycardia (standard ALS)
- Must Remember
- Exclude pre-excitation and HFrEF before you push. Error trap: the bolus is mg/kg over 2 min, the infusion is mg/hr (1 mg/mL: 10 mg/hr = 10 mL/hr, max 15 mg/hr)
Indications
Emergency & Prehospital
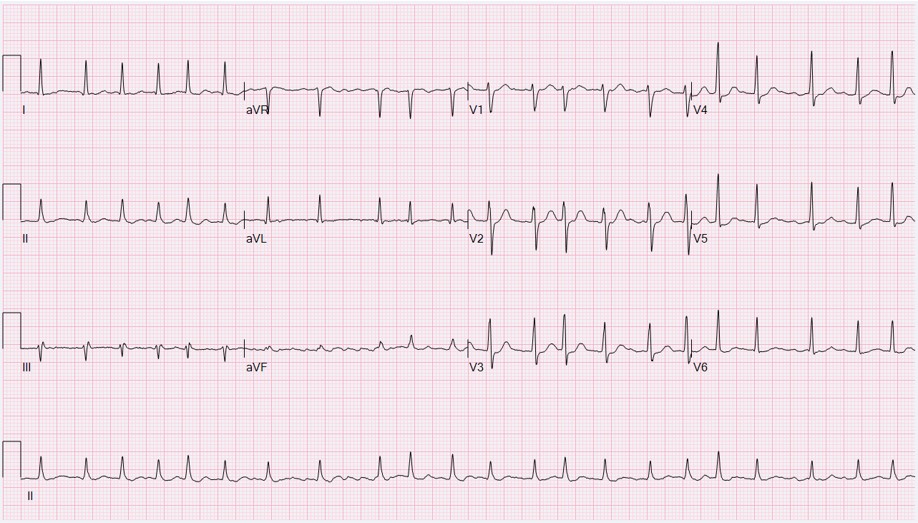
- Atrial fibrillation (AF) or atrial flutter with rapid ventricular response (RVR): hemodynamically stable, no pre-excitation, left ventricular ejection fraction (LVEF) >40%; FDA-labeled for temporary rate control and an ACC/AHA first-line option with beta-blockers
- Stable paroxysmal supraventricular tachycardia (PSVT): AV nodal re-entry or orthodromic AV re-entry (narrow, regular); FDA-labeled for rapid conversion to sinus rhythm after vagal maneuvers; AHA guidance places it after adenosine (or when adenosine fails, recurs or is unsuitable)
ED / ICU / Transport
- Ongoing AF/flutter rate control: continuous infusion for up to 24 hr after an effective bolus, then oral or other agents
Other Uses
- Long-term AF rate control (oral): LVEF >40%
- Chronic stable angina and coronary vasospasm (oral): FDA-labeled
- Hypertension (oral extended-release): FDA-labeled for extended-release products
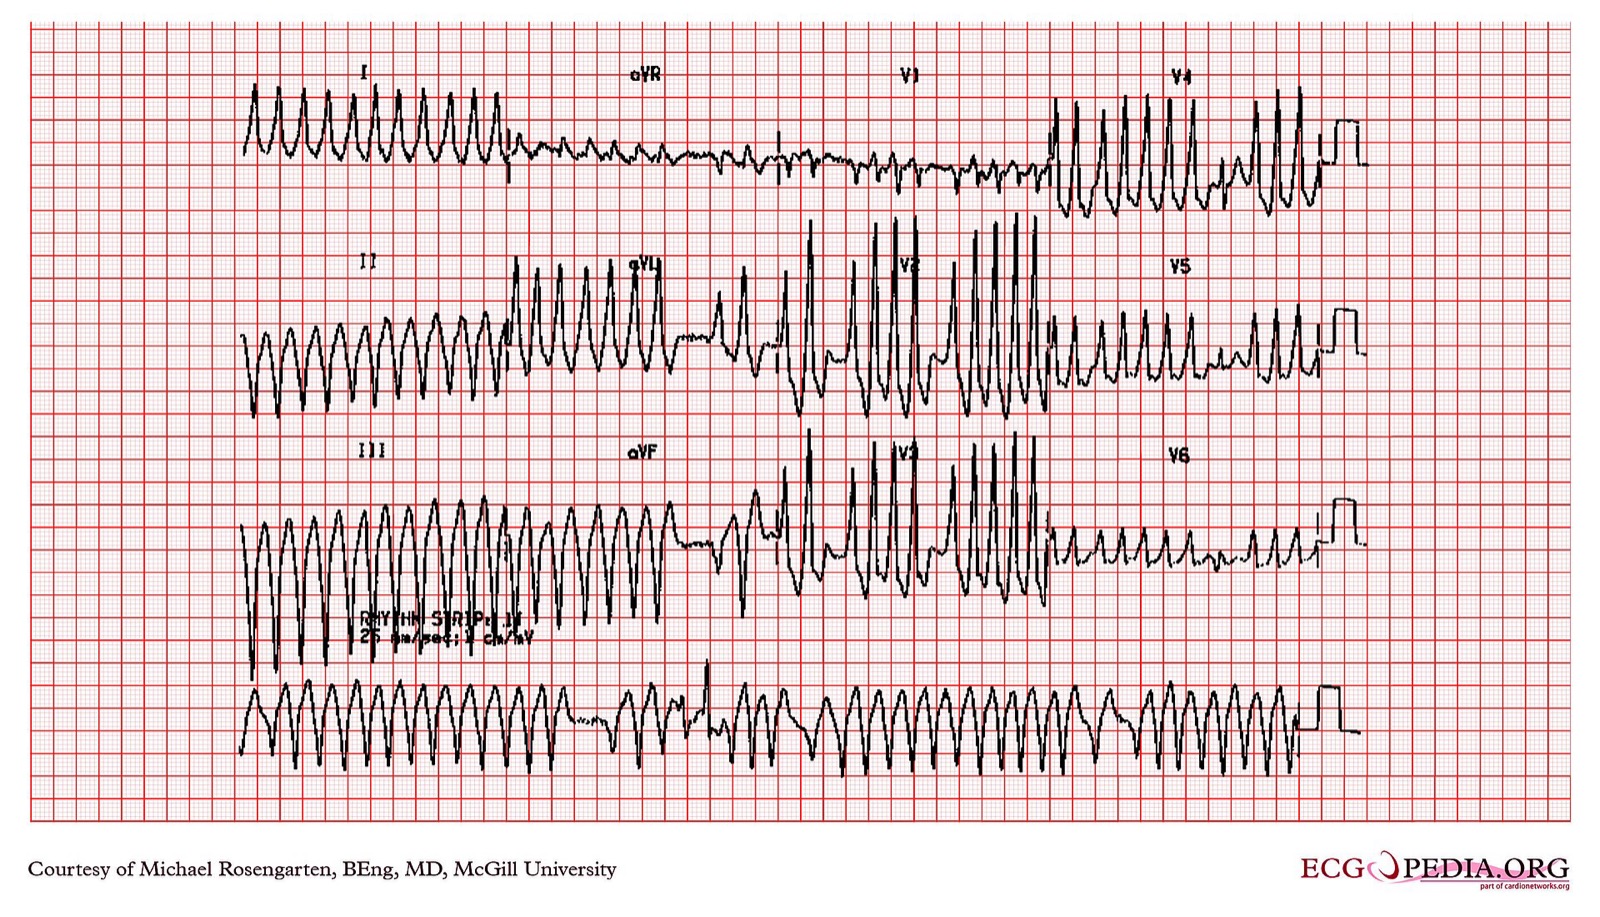
Not for Wide-Complex or Pre-Excited Tachycardia: Ventricular tachycardia (VT) and AF or flutter over an accessory pathway are labeled contraindications. IV calcium channel blockers have caused hemodynamic collapse and ventricular fibrillation (VF) in these patients. Wide-complex and you can't prove it's SVT? Treat it as VT.
Dosing & Administration
These doses follow the FDA label and AHA 2025. Your protocol may differ from them.
Available Forms
- Injection (bolus or infusion): 5 mg/mL in 5 mL (25 mg), 10 mL (50 mg) and 25 mL (125 mg) single-dose vials; the vial EMS and transport usually carry. Refrigerated.
- Premixed bag (1 mg/mL): 100 mg/100 mL and 250 mg/250 mL in sodium chloride, ready to hang. Labeled for both bolus and infusion, but mainly used for infusion. The bolus is usually drawn from the 5 mg/mL vial (per institution).
- For injection (infusion only): 100 mg lyophilized ADD-Vantage vial, labeled "Not for bolus".
- Oral: immediate-release (IR) tablets 30, 60, 90 and 120 mg (Cardizem tablets); extended-release (ER) once-daily tablets 120, 180, 240, 300, 360 and 420 mg (Cardizem LA); ER capsules are also marketed (Hospira label).
High-Alert Medication: Four ways this goes wrong. Units: the bolus is mg/kg, the infusion is mg/hr, and it is never mg/kg/hr. Pushing it faster than the 2-min window. Drawing a bolus from the infusion-only ADD-Vantage vial. Giving it to a patient who just had an IV beta-blocker. Get an independent double-check of the weight, the dose in mg and the pump rate.
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| AF/flutter with RVR or PSVT: first bolus | 0.25 mg/kg IV over 2 min (actual body weight; about 20 mg for an average adult) | Reassess at 15 min; first bolus 0.25 mg/kg | High-alert Continuous ECG, frequent BP, defibrillator ready. The label notes some respond to 0.15 mg/kg (shorter effect, limited data); in an ED cohort, doses under about 0.19 mg/kg controlled the rate less often. |
| Second bolus (response inadequate) | 0.35 mg/kg IV over 2 min (about 25 mg for an average adult) | 15 min after the first; further boluses individualized: no fixed label max | High-alert Do not repeat into hypotension, bradycardia or new heart failure signs. |
| AF/flutter: maintenance infusion | 5–10 mg/hr IV right after the bolus, per product label and protocol: premixed-bag label 5 mg/hr; vial label 10 mg/hr (5 mg/hr enough for some) | Increase by 5 mg/hr as needed; max 15 mg/hr for up to 24 hr | High-alert Rates above 15 mg/hr and infusions beyond 24 hr have not been studied. Not labeled for PSVT. |
| Long-term AF rate control (oral) | 120–360 mg/day PO (ER once daily, or IR divided every 6 hr); the infusion equivalents below are from the label | Usual max 360 mg/day | Infusion equivalents (Hospira label): 3, 5, 7 and 11 mg/hr ≈ 120, 180, 240 and 360 mg/day oral. Oral AF dosing is guideline-based (ACC/AHA), not FDA-labeled for AF. Oral IR tablets are labeled for angina, starting 30 mg four times daily and usually 180–360 mg/day (Cardizem tablets); Cardizem LA is once daily, starting 180 mg for angina (max 360 mg) or 180–240 mg for hypertension (max 540 mg). |
Pediatric Dosing
Not Established in Children: The FDA label says safety and effectiveness in children have not been established. Use it only on pediatric cardiology or medical-control advice. Avoid IV nondihydropyridine CCBs in infants. IV verapamil caused cardiovascular collapse needing CPR in three infants with SVT and heart failure. For diltiazem itself, the class effect is inferred. For pediatric SVT, follow PALS: vagal maneuvers, adenosine, or synchronized cardioversion if unstable. Adenosine-refractory without cardiopulmonary compromise? Get expert consultation to pick a second-line agent (for example procainamide or amiodarone; AHA 2025 Part 8).
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| Any indication (children and neonates) | Not established in children | Specialist use only | Alternative: PALS tachycardia pathway. See weight-based dosing. |
Continuous Infusion
| Setting | Example Concentration | Start | Titrate | Usual Range / Max |
|---|---|---|---|---|
| AF/flutter rate control (adult) | 1 mg/mL: 125 mg in 125 mL total, or premix 100 mg/100 mL or 250 mg/250 mL (example, institution-specific) | 5–10 mg/hr (5–10 mL/hr at 1 mg/mL): premixed-bag label 5 mg/hr, vial label 10 mg/hr | Up by 5 mg/hr as needed for rate | 5–15 mg/hr; max 15 mg/hr, 24 hr |
Preparation & Administration
- Bolus: undiluted 5 mg/mL over 2 min (20 mg = 4 mL; 25 mg = 5 mL); flush.
- Infusion dilution (label): 125 mg (25 mL) into 100 mL normal saline, D5W or D5W/0.45% NaCl = 125 mL at 1 mg/mL. Larger bags: 250 mg (50 mL) into 250 mL = 0.83 mg/mL; into 500 mL = 0.45 mg/mL. Keep this vial admixture refrigerated until use (an ADD-Vantage admixture may be kept at room temperature or refrigerated); use within 24 hr.
- Line: dedicated line when possible; do not mix with other drugs in the same container.
- Pump: infusion on a smart pump in mg/hr; start it right after the effective bolus.
- Transition: move to an oral or other agent within 24 hr. The effect can last a median of 7 hr after the infusion stops. Reassess before you stack a new AV-nodal blocker on top.
For renal and hepatic dosing, see Special Populations.
Contraindications & Precautions
Contraindications
- Sick sinus syndrome or 2nd/3rd-degree AV block without a functioning ventricular pacemaker
- Severe hypotension or cardiogenic shock
- AF or atrial flutter with an accessory pathway (Wolff-Parkinson-White, WPW, or short-PR syndrome)
- Ventricular tachycardia, or a wide-complex tachycardia (QRS ≥0.12 s) not proven supraventricular
- IV beta-blocker given together or within a few hours
- Moderate or severe LV systolic dysfunction, decompensated or not (ACC/AHA 3: Harm for IV use); acute decompensated heart failure or cardiogenic shock (label: do not initiate)
- Oral diltiazem: acute myocardial infarction with pulmonary congestion on chest x-ray
- Hypersensitivity to diltiazem
Precautions
- Borderline blood pressure or volume depletion: Hypotension is the main adverse effect. Correct volume first, or choose another agent.
- Drugs that lower BP, contractility or conduction: Effects add up. A patient on an oral beta-blocker can still get IV diltiazem, with close monitoring.
- Acute coronary syndrome or acute MI: Avoid IV diltiazem (AHA 2025 rate-control table), especially with pulmonary congestion or LV dysfunction. In ACS, AF with ongoing ischemia, hemodynamic compromise or poor rate control needs urgent synchronized cardioversion.
- Older adults, hepatic or renal impairment: start at the low end of the range.
- AF over 48 hr or unknown onset: Diltiazem rarely converts AF. Any conversion carries stroke risk, so address anticoagulation before a planned cardioversion.
Hold / Reassess If
- SBP <90 mmHg or symptomatic hypotension: stop the bolus or infusion; fluids; see Reversal
- Symptomatic bradycardia, pauses, junctional rhythm or new 2nd/3rd-degree AV block: stop; atropine or pacing ready
- New crackles, rising O₂ need or falling perfusion: stop; treat heart failure
- QRS widens or the rhythm turns irregular and broad: stop; reassess for pre-excitation or VT
Pre-Excited AF (WPW): Irregular, very fast and broad, with QRS complexes that keep changing? That is AF conducting down an accessory pathway. Diltiazem, verapamil, adenosine, beta-blockers, amiodarone and digoxin can all trigger VF here. Unstable: cardiovert. Stable: IV procainamide may be considered (AHA 2025 Part 9, wide-complex tachycardia, 2b).
Adverse Effects & Toxicity
Common
- Hypotension: asymptomatic 4.3%, symptomatic 3.2% in IV trials; usually fluids or positioning were enough
- Injection-site itching or burning: 3.9%
- Flushing: 1.7%
- Junctional rhythm or isorhythmic dissociation: 1%
- Transient ventricular premature beats on conversion of PSVT (benign)
- Oral: edema, headache, dizziness, constipation, nausea
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
| Hypotension / shock | Falling BP after a bolus; can last 1–3 hr (longer after an infusion) | Stop; fluids; calcium; vasopressors |
| Bradycardia, AV block, asystole | Monitor: slow rate, pauses, dropped beats | Stop; atropine; pacing for high-grade block |
| Heart failure | Dyspnea, crackles, hypoxia; mostly with impaired LV function | Stop; treat heart failure; inotropes if needed |
| VF in pre-excited AF or VT | Wide, chaotic rhythm after the dose | Defibrillate; ACLS |
| Hepatic injury, severe skin reactions | Rising liver enzymes; rash, blistering (rare; mostly oral) | Stop; supportive care |
Overdose & Toxicity Management
- Signs: Expect hypotension, bradycardia, AV block, cardiogenic or vasoplegic shock. Toxicity can be delayed, especially after an extended-release ingestion.
- Ingestion, still well: Send every intentional ingestion to the ED, and any ingestion above the usual maximum single dose. Toxicity can show up late. An asymptomatic patient is unlikely to develop symptoms more than 6 hr after an IR ingestion, or more than 18 hr after a modified-release diltiazem ingestion. Follow poison center advice on observation, which is often longer for ER products. Consider activated charcoal if it is available and there is no contraindication. Do not delay transport for it (see the CCB consensus guideline in References).
- Treat (2025 AHA Guidelines, Part 10): crystalloid boluses while the patient is fluid-responsive; norepinephrine and/or epinephrine for hypotension (vasopressors, Class 1, C-LD; high-dose insulin for hypotension is also Class 1, B-NR); high-dose insulin 1 unit/kg IV, then 1–10 units/kg/hr with dextrose and potassium monitoring (Table 4); IV calcium chloride 2 g (20 mL of 10%), or calcium gluconate 6 g if peripheral (Class 2a, C-EO), then 20–40 mg/kg/hr of calcium chloride titrated to BP, without exceeding an ionized calcium of 1.5–2 times the upper limit of normal; methylene blue for refractory vasodilatory shock (Class 2b, C-EO): 1–2 mg/kg IV, repeated hourly if needed, then 1 mg/kg/hr, maximum 5–7 mg/kg; glucagon (Class 2b, C-EO); atropine for symptomatic bradycardia is standard ALS, not a Part 10 recommendation.
- Pediatric calcium: calcium chloride 20 mg/kg (0.2 mL/kg of 10%) IV slowly over 10 min, max 1 g or 10 mL per dose (NASEMSO v3.0 p. 296, calcium channel blocker poisoning). Calcium gluconate 60 mg/kg over 10 min is preferred in children because chloride carries more tissue-injury risk (NASEMSO v3.0 p. 296). Differs: AHA 2025 Part 10 Table 4 gives 20 mg/kg with no child maximum (adult ceiling 2 g). Central line preferred in children; see the calcium chloride page.
- Refractory: Escalate insulin. Use transcutaneous pacing for unstable bradycardia. VA-ECMO is for refractory cardiogenic shock or cardiac arrest (Class 2a: adults B-NR, children C-LD). IV lipid emulsion has uncertain usefulness (Class 2b, C-EO). An expert consensus advises against routine use, so give it only on toxicology advice.
- Removal: Hemodialysis and peritoneal dialysis do not remove it. Call poison control (1-800-222-1222).
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: ECG rhythm and QRS | Continuous, from before the first dose | Wide or irregular-broad QRS: stop and reassess; high-grade AV block or pauses: stop, prepare to pace |
| Clinical: heart rate response | 15 min after each bolus; with each titration | AF/flutter: ≥20% fall in HR (label trials) or HR <100/min (ED cohort); PSVT: conversion to sinus rhythm. Long-term lenient target <110/min. Inadequate at 15 min: second bolus |
| Clinical: blood pressure | Frequently during boluses and titration | SBP <90 mmHg or symptoms: stop; fluids; calcium |
| Clinical: heart failure signs | Lung sounds, SpO₂, work of breathing each reassessment | New crackles or hypoxia: stop; treat heart failure |
| Laboratory: digoxin, ALT | Digoxin level if co-prescribed; liver tests with symptoms or long-term use | Excess slowing on digoxin: check level; rising enzymes: stop |
| Infusion safety | Track start time, current rate and running total | Over 15 mg/hr or nearing 24 hr: plan the oral or alternative agent |
| After stopping | Effect lasts 0.5 to over 10 hr (median 7 hr) after an infusion | Keep monitoring; delayed hypotension or bradycardia can follow |
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| IV beta-blockers (metoprolol, esmolol) | Bradycardia, AV block, low output | Contraindicated together or within a few hours. Chronic oral beta-blockers: monitor closely |
| Digoxin, amiodarone, clonidine, ivabradine | Additive AV-nodal and sinus slowing; clonidine has caused bradycardia needing a pacemaker | Monitor HR and PR; avoid ivabradine |
| Midazolam, triazolam | AUC up 3- to 4-fold; prolonged sedation | Smaller, titrated doses (for example, for cardioversion sedation) |
| Anesthetics, antihypertensives | Additive hypotension and myocardial depression | Titrate both carefully |
| Apixaban, rivaroxaban | In a large Medicare cohort (age ≥65), more serious bleeding than with metoprolol, greatest above 120 mg/day oral but also higher at lower doses | Weigh a beta-blocker for long-term rate control; watch for bleeding |
| CYP3A4 substrates: simvastatin, lovastatin, cyclosporine, carbamazepine, buspirone, quinidine, and other CYP3A4 substrates | Levels rise (simvastatin AUC about 5-fold; cyclosporine dose cut 15–48%) | If coadministered, limit simvastatin to 10 mg/day and diltiazem to 240 mg/day (label); monitor for statin adverse effects; check cyclosporine trough levels |
| CYP3A4 inhibitors (for example cimetidine); inducers (rifampin or any known CYP3A4 inducer) | Inhibitors raise diltiazem levels; rifampin lowered diltiazem to undetectable levels | Monitor response; avoid inducers when possible |
IV Compatibility
- Diluents: normal saline, D5W, D5W/0.45% NaCl (stable 24 hr at up to 1 mg/mL).
- Same container: do not mix with other drugs; use a dedicated line when possible.
- Y-site incompatible (label): acetazolamide, acyclovir, aminophylline, ampicillin ± sulbactam, cefoperazone, diazepam, furosemide, hydrocortisone and methylprednisolone sodium succinate, regular insulin, nafcillin, phenytoin, rifampin, sodium bicarbonate. Several were compatible with the 1 mg/mL ADD-Vantage product only; treat all as incompatible.
- Verify with an institutional compatibility resource.
Special Populations
- Pediatrics: Safety and effectiveness are not established, so this is specialist use only. Avoid it in infants, where the risk is profound hypotension and cardiovascular collapse. The Pediatric Dosing block has the alternative pathway.
- Pregnancy: Decades of published use have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. Animal studies at 5–10 times human doses did show embryo-fetal harm. ACC/AHA prefer beta-blockers or digoxin for rate control in pregnancy. Electrical cardioversion is safe. In an emergency, treat the mother.
- Lactation: It gets into breast milk at levels that may approach serum, and effects on the infant are unknown. The labels do not agree. The premixed-bag label says to weigh breastfeeding benefits against the mother's need. The vial label says to use another feeding method if diltiazem is essential.
- Older Adults: Start at the low end of the range. The AGS Beers Criteria 2023 says to avoid nondihydropyridine CCBs in heart failure with reduced ejection fraction (HFrEF). See Heart Failure below.
- Renal Impairment: No specific adjustment is established. In label studies, renal failure did not change oral disposition. Dialysis does not remove it.
- Hepatic Impairment: Cirrhosis cut oral clearance and stretched the half-life. Use with caution and titrate carefully.
- Obesity / Dosing Weight: The label bases the bolus on actual body weight. Obesity dosing is not well studied, so follow local protocol for any per-dose cap.
- Heart Failure: IV diltiazem is an option when LVEF >40% and the patient is not in acute decompensated HF. Do not give it with known moderate or severe LV systolic dysfunction, decompensated or not (ACC/AHA 3: Harm). Do not give it in acute decompensated HF or cardiogenic shock either (label).
Field & Transport Considerations
- Scope: usually paramedic and critical-care transport, per local protocol; varies by state and agency protocol.
- Storage & Stability: Keep vials and premixed bags refrigerated at 2–8°C (36–46°F). Do not freeze them. Either can sit at room temperature for up to 1 month, then discard it. Date the box the moment it leaves the refrigerator. For premixed bags, that month counts only in the original aluminum overwrap. Out of the overwrap, use within 28 days. Lyophilized vials live at room temperature.
- Carried Concentration: Carry 5 mg/mL vials for boluses. Infusions run at 1 mg/mL. Never draw a bolus from the lyophilized ADD-Vantage vial (infusion only).
- Infusions in Transport: smart pump in mg/hr, dedicated line, enough volume for the trip; confirm the concentration and the 24-hr start time at handoff.
- Handoff Essentials: each bolus time, dose in mg and mg/kg, infusion rate and start time, HR and BP response, any hypotension treatment, AF onset time, anticoagulant use and known LVEF.
Clinical Pearls
Irregular, Wide and Very Fast: Treat that pattern as pre-excited AF until proven otherwise. Slowing the AV node pushes conduction down the accessory pathway, and that can cause VF. Unstable means shock. Stable means procainamide may be considered (2b).
Exam Discriminator: WPW With a Narrow, Regular SVT: Orthodromic AV re-entry runs down the AV node, which is why diltiazem is labeled for it. Pre-excitation on the resting ECG changes the picture. Keep it as a fallback after other therapies fail, with a defibrillator ready, because AF can start and conduct down the pathway. In AF or flutter, it is contraindicated.
Diltiazem vs Metoprolol for AF With RVR: When LVEF >40%, both are ACC/AHA first-line.
- Known HFrEF (LVEF ≤40%): avoid IV diltiazem. If compensated, a cautious beta-blocker is an option. If decompensated or critically ill, avoid IV beta-blockers too (AHA 2025 3: Harm). Use IV amiodarone or digoxin, or cardiovert if unstable.
Give the Full Weight-Based Bolus: In an ED cohort, token low doses controlled the rate less often and needed more rescue therapy. They bought no safety gain. Borderline BP? Choose another agent instead of underdosing.
Bolus, Then Bridge: The bolus wears off in 1–3 hr. Start the infusion right after an effective bolus, or switch to oral therapy, so the rate does not come back.
Rate Control Is Not Rhythm Control: Diltiazem rarely converts AF. An unstable patient needs synchronized cardioversion, not one more bolus.
Pharmacology
Mechanism of Action
- L-type Ca²⁺ channel block in the AV node: Conduction slows and refractoriness lengthens. That gives ventricular rate control in AF/flutter and ends AV-nodal re-entry.
- Use-dependent: The effect is stronger at fast rates. At normal rates it does little to normal AV conduction.
- No effect on accessory pathways or His-Purkinje tissue: That is why it cannot slow pre-excited AF, and why it may speed it up.
- Vascular smooth muscle: Systemic vascular resistance drops, so BP falls. Negative inotropy can worsen systolic function.
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| IV bolus | ≤3 min | 2–7 min | 1–3 hr |
| IV infusion | Maintains bolus effect | — | 0.5 to over 10 hr after stopping (median 7 hr) |
| PO (IR tablet) | 30–60 min | 2–4 hr | Dosed every 6 hr |
- Half-life: about 3.4 hr after an IV bolus; 4–5 hr during infusion (nonlinear kinetics); 3–4.5 hr orally.
- Metabolism: extensive hepatic (CYP3A4 substrate and inhibitor); oral bioavailability about 40% after first-pass metabolism.
- Active metabolites: desacetyldiltiazem (25–50% as potent as a coronary vasodilator), seen after oral use or a 24-hr infusion.
- Elimination: metabolites in urine and bile; 2–4% unchanged in urine; not dialyzable.
- Protein binding / Vd: 70–80%; about 305 L.
Names & Classification
- Generic Name
- Diltiazem hydrochloride
- Brand Names
- Cardizem (IR tablets), Cardizem CD, Cardizem LA, Cartia XT, Tiazac, Matzim LA; injection sold as generic
- Pharmacologic Class
- Nondihydropyridine (benzothiazepine) calcium channel blocker; Vaughan Williams class IV
- Therapeutic Class
- Antiarrhythmic (AV-nodal rate control); antianginal; antihypertensive
- Controlled Substance
- Not controlled
- ISMP High-Alert
- Yes: ISMP high-alert medication (antiarrhythmics, IV); diltiazem is not a named example
- Look-Alike / Sound-Alike
- Product mix-up: diltiazem injection (bolus or infusion) vs diltiazem for injection (infusion only, not for bolus)
References
- Wigginton, J. G., Agarwal, S., Bartos, J. A., Coute, R. A., et al. (2025). Part 9: Adult advanced life support: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation, 152(16 Suppl 2), S538–S577. https://doi.org/10.1161/CIR.0000000000001376
- Cao, D., Arens, A. M., Chow, S. L., et al. (2025). Part 10: Adult and pediatric special circumstances of resuscitation: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation, 152(suppl 2), S578–S672. https://doi.org/10.1161/CIR.0000000000001380; cpr.heart.org
- Joglar, J. A., et al. (2024). 2023 ACC/AHA/ACCP/HRS guideline for the diagnosis and management of atrial fibrillation. Circulation, 149(1), e1–e156. https://doi.org/10.1161/CIR.0000000000001193
- Hospira, Inc. (2026). Diltiazem hydrochloride injection and diltiazem hydrochloride for injection: Prescribing information. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=bba03666-ff4f-4bf6-fa92-78e1ec2d9073
- WG Critical Care. (2026). Diltiazem hydrochloride in sodium chloride injection: Prescribing information. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=8bae87a5-2137-467e-a1ad-79b2bc075e07
- Ray, W. A., Chung, C. P., Stein, C. M., Smalley, W., Zimmerman, E., Dupont, W. D., Hung, A. M., Daugherty, J. R., Dickson, A., & Murray, K. T. (2024). Serious bleeding in patients with atrial fibrillation using diltiazem with apixaban or rivaroxaban. JAMA, 331(18), 1565–1575. https://doi.org/10.1001/jama.2024.3867
- Bausch Health US LLC. CARDIZEM (diltiazem hydrochloride) tablets, prescribing information (revised 2025-04-30), and CARDIZEM LA (diltiazem hydrochloride) extended-release tablets, prescribing information (revised 2025-11-11). DailyMed. tablets; Cardizem LA
- Posen, A., Bursua, A., & Petzel, R. (2023). DOsing Strategy Effectiveness of Diltiazem in Atrial Fibrillation With Rapid Ventricular Response. Annals of Emergency Medicine, 81(3), 288–296. https://doi.org/10.1016/j.annemergmed.2022.08.462
- Lasa, J. J., Dhillon, G. S., Duff, J. P., et al. (2025). Part 8: Pediatric advanced life support: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation, 152(suppl 2), S479–S537. https://doi.org/10.1161/CIR.0000000000001368; cpr.heart.org
- Olson, K. R., Erdman, A. R., Woolf, A. D., et al. (2005). Calcium channel blocker ingestion: an evidence-based consensus guideline for out-of-hospital management. Clinical Toxicology, 43(7), 797–822. https://doi.org/10.1080/15563650500357404
- Epstein, M. L., Kiel, E. A., & Victorica, B. E. (1985). Cardiac decompensation following verapamil therapy in infants with supraventricular tachycardia. Pediatrics, 75(4), 737–740. https://pubmed.ncbi.nlm.nih.gov/3982906/
- National Association of State EMS Officials. (2022). National Model EMS Clinical Guidelines, Version 3.0 (March 2022). https://nasemso.org/content.aspx?page_id=22&club_id=157064&module_id=701974
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.