

Bedside Snapshot
- Use It For
- Disabling ischemic stroke within 4.5 hr; STEMI when PCI is more than 120 min away; PE with shock or arrest; occluded central line (Cathflo)
- Adult Dose
- Stroke: tenecteplase 0.25 mg/kg IV bolus (max 25 mg), or alteplase 0.9 mg/kg (max 90 mg), 10% over 1 min, rest over 60 min
- STEMI: tenecteplase 30–50 mg IV bolus by weight
- PE: alteplase 100 mg IV over 2 hr
- Pediatric Dose
- Systemic lytics not established in children: specialist use only. Cathflo: 2 mg in 2 mL if 30 kg or more; under 30 kg, 110% of lumen volume (max 2 mg)
- Onset / Duration
- IV: lysis begins immediately / drug cleared within hours, but bleeding risk is highest for 24 hr and can appear 1 or more days later
- Do Not Give / Hold If
- Current ICH; active bleeding/diathesis; recent CNS surgery/trauma; aortic dissection; stroke: BP ≥185/110, plt <100K, INR >1.7, endocarditis; STEMI: prior ICH, stroke <3 mo, AVM or malignant brain tumor, uncontrolled BP
- Watch For
- Intracranial bleed (headache, vomiting, BP surge, new deficit: stop, CT); systemic bleeding (sites, Hgb drop, flank pain); tongue or lip angioedema; reperfusion arrhythmias
- Reversal / Rescue
- No antidote. Stop the lytic; cryoprecipitate 10 units (fibrinogen 150 mg/dL or higher); tranexamic acid 1,000 mg IV over 10 min; STAT CBC, PT/INR, aPTT, fibrinogen, crossmatch
- Must Remember
- Tenecteplase has two doses: stroke 0.25 mg/kg (max 25 mg), STEMI 30–50 mg. Never order tPA or TNK; name the drug, indication and mg dose and double-check the band
Indications
Emergency & Prehospital
- Acute ischemic stroke (AIS): disabling deficit within 4.5 hr of last known well (LKW); mobile stroke units can start it before arrival where available; give it before thrombectomy when both are indicated
- STEMI without timely PCI: symptoms under 12 hr and first-medical-contact-to-device time over 120 min
- Cardiac arrest from confirmed PE: systemic lysis during CPR (2025 AHA Guidelines for CPR and ECC, Part 10: Class 2a); suspected PE is Class 2b; off-label
- Children, cardiac arrest from confirmed PE: systemic lysis is reasonable (2025 AHA Guidelines for CPR and ECC, Part 10, Class 2a, C-LD); suspected PE may be considered (Class 2b, C-EO)
ED / ICU / Transport
- PE with cardiopulmonary failure: AHA/ACC PE Category E1–2 (persistent hypotension with cardiogenic shock, refractory shock or arrest); D1–2 may be considered; harmful in A–C2
- PE Category C3: no routine lysis; anticoagulate, and give rescue lysis if the patient deteriorates into Categories D–E. In PEITHO (intermediate-risk PE with right ventricular dysfunction and troponin; tenecteplase plus heparin vs placebo plus heparin), tenecteplase reduced death or hemodynamic decompensation within 7 days (2.6% vs 5.6%) but increased extracranial bleeding (6.3% vs 1.2%) and stroke (2.4% vs 0.2%) (Meyer 2014, ref 12)
- Catheter-directed thrombolysis (PE, DVT, limb ischemia): low-dose alteplase by interventional radiology or vascular protocol; off-label; adults only
- Extended-window or unknown-onset stroke: 4.5–9 hr with salvageable penumbra, or MRI DWI-FLAIR mismatch: stroke-expert decision (off-label)
- Late STEMI (over 12 hr), still symptomatic: benefit not established; 2025 ACS text (no class) allows a lytic for a large at-risk territory when PCI is unavailable
- Pediatric AIS or PE with hemodynamic compromise: specialist decision
Other Uses
- Occluded central venous access device: alteplase 2 mg (Cathflo Activase) instilled into the lumen
- Left-sided mechanical valve thrombosis: low-dose, slow-infusion lysis or surgery; cardiology and surgery decision (off-label; 2020 ACC/AHA valvular guideline)
Dosing & Administration
Each dose below tracks current guidelines and the FDA label. When the two split, the row tells you how. Read the row before you draw up anything.
Available Forms
- Tenecteplase (TNKase): 25 mg and 50 mg vials; reconstitute to 5 mg/mL. The 25 mg vial covers every stroke dose. Band detail and reconstitution: tenecteplase page
- Alteplase (Activase): 50 mg and 100 mg vials; reconstitute to 1 mg/mL (may dilute to 0.5 mg/mL with 0.9% sodium chloride or D5W)
- Alteplase 2 mg (Cathflo Activase): add 2.2 mL Sterile Water for 1 mg/mL
- Reteplase (Retavase): 10.4-unit vial (18.1 mg) delivers 10 units at 1 unit/mL
High-Alert Medication: Abbreviations cause the swaps. Orders written as "tPA" or "TNK" have ended up as the wrong drug. The stroke and STEMI tenecteplase doses differ about twofold. Order by generic name, indication and mg dose. Then a second clinician independently checks drug, weight, band and syringe volume before the bolus.
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| AIS: tenecteplase | 0.25 mg/kg single IV bolus over 5 sec, by weight band | Single dose; max 25 mg | High-alert Class 1, equal to alteplase, within 4.5 hr. Differs from FDA label: within 3 hr. 0.4 mg/kg is not recommended |
| AIS: alteplase | 0.9 mg/kg IV: 10% as a bolus over 1 min, remaining 90% over 60 min | Single course; max 90 mg | High-alert Class 1 within 4.5 hr. Differs from FDA label: within 3 hr. Discard excess from the vial |
| STEMI: tenecteplase | 30–50 mg single IV bolus over 5 sec, by weight band | Single dose; max 50 mg | High-alert With aspirin, clopidogrel and anticoagulant; transfer to PCI immediately |
| STEMI: alteplase (accelerated) | Over 67 kg: 15 mg bolus, 50 mg over 30 min, then 35 mg over 60 min. 67 kg or less: 15 mg bolus, 0.75 mg/kg over 30 min (max 50 mg), then 0.5 mg/kg over 60 min (max 35 mg) | Max 100 mg total | High-alert Studied only with heparin and aspirin |
| STEMI: reteplase | 10 units IV over 2 min, repeated 30 min later | Two boluses; max 20 units | High-alert Never through a heparin line |
| PE: alteplase | 100 mg IV infusion over 2 hr | Max 100 mg | High-alert Category E1–2 (reasonable) or D1–2 (may be considered). Class 2b: a lower-dose regimen may be considered to reduce bleeding; the guideline gives no dose |
| Occluded central line: alteplase (Cathflo) | 30 kg or more: 2 mg in 2 mL (1 mg/mL) into the lumen; dwell 30 min, reassess, up to 120 min | Second equal dose if not patent at 120 min; max 4 mg | High-alert Not for mechanical occlusion; instill without force |
Stroke and STEMI each get their own band. Stroke runs 15–25 mg and STEMI 30–50 mg, both at 5 mg/mL. The bands are on the tenecteplase page. Pick the band for the indication you are treating.
Pediatric Dosing
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| Occluded central line: alteplase (Cathflo) | Under 30 kg: 110% of the lumen volume of 1 mg/mL solution (Cathflo label); 30 kg or more: adult dose | Max 2 mg in 2 mL per dose; max 2 doses | High-alert Labeled; studied from 2 weeks to 17 yr. Aspirate 3 mL if under 10 kg, or 4–5 mL at 10 kg or more, before flushing (Cathflo label) |
| AIS, 28 days to 18 yr | Not established in children: pediatric stroke team only | Per specialist protocol | Alteplase may be considered (Class 2b); tenecteplase data limited |
| PE with hemodynamic compromise | Not established in children: pediatric hematology or ICU only | Per specialist protocol | ASH/ISTH suggest thrombolysis then anticoagulation |
See weight-based dosing.
Indication Checklists
Stroke Lytic Checklist
- Time and deficit: Within 4.5 hr of LKW. The deficit must be disabling, regardless of NIHSS. Mild non-disabling deficits get dual antiplatelets instead.
- Glucose: Treat a glucose below 50 or above 400 mg/dL, then reassess the deficit.
- Imaging: Noncontrast CT should show no hemorrhage and no extensive clear hypodensity. Do not wait for CTA or perfusion imaging.
- BP: below 185/110 mmHg before the bolus
- Labs: No lytic if platelets sit below 100,000/mm³, INR is over 1.7, aPTT is over 40 s or PT is over 15 s. You do not wait on coagulation tests unless anticoagulants or a bleeding disorder are suspected.
- Exclusions: Check Contraindications & Precautions. Weight can be actual or a best estimate. Do not delay to weigh.
STEMI Lytic Checklist
- Eligibility: Look for ST elevation, or a true posterior MI, with symptoms under 12 hr. FMC-to-device time is expected to run over 120 min.
- Aspirin (2025 ACC/AHA ACS): 162–325 mg chewed (non-enteric-coated)
- Clopidogrel: 300 mg PO if 75 yr or younger; 75 mg PO without a load if older than 75 yr (2025 ACC/AHA ACS)
- Anticoagulant (2025 ACC/AHA ACS): enoxaparin under 75 yr 30 mg IV, then 1 mg/kg subcut every 12 hr starting 15 min later (max 100 mg for the first 2 doses); 75 yr or older no bolus, 0.75 mg/kg subcut every 12 hr (max 75 mg for the first 2 doses); or UFH 60 units/kg IV (max 4,000 units), then 12 units/kg/hr (max 1,000 units/hr), aPTT 50–70 s
- Transfer: Transfer to a PCI center at once. Angiography within 2–24 hr, or right away if reperfusion fails.
PE Lytic Checklist
- Category: E1–2, or selected D1–2, with acceptable bleeding risk. If not, the PE response team picks catheter-directed lysis (adults, off-label, protocol), mechanical therapy or VA-ECMO.
- Anticoagulation: Start it near the end of the infusion or right after, once aPTT is 2× normal or less.
- Cardiac arrest: A lytic during CPR is reasonable for confirmed PE (2025 AHA Part 10, Class 2a). It may be considered for suspected PE (Class 2b). How long CPR should continue after lysis is unclear.
- Airway: Avoid sedation and intubation unless you need them. Have vasopressors and ECMO ready.
Preparation & Administration
- Tenecteplase: push the band volume over 5 sec; it precipitates with dextrose, so flush dextrose lines with 0.9% sodium chloride before and after. Reconstitution and syringe steps: tenecteplase page
- Cathflo reconstitution: 2.2 mL Sterile Water for Injection, not bacteriostatic water; swirl gently, do not shake (Cathflo label)
- Alteplase infusion: bolus by syringe or pump, discard any volume above the calculated dose, then infuse the rest; add no other drug
- Line and puncture: peripheral IV is acceptable; avoid internal jugular, subclavian and IM sites; arterial puncture only at a compressible site, with 30 min of pressure
- Stability: reconstituted alteplase within 8 hr; tenecteplase immediately, or refrigerated and used within 8 hr
Contraindications & Precautions
Contraindications
- Active internal bleeding or a known bleeding diathesis
- Current intracranial hemorrhage, including subarachnoid hemorrhage
- Intracranial or intraspinal surgery or serious head trauma within 2–3 months (labels; the ACS guideline uses 2 months for surgery and 3 months for significant closed-head trauma)
- Intracranial neoplasm, arteriovenous malformation or aneurysm (labels). Stroke: intra-axial neoplasm excludes; extra-axial neoplasm or unruptured aneurysm does not
- Severe uncontrolled hypertension: stroke, BP not lowered below 185/110 mmHg; STEMI, SBP over 180 or DBP over 110 mmHg unresponsive to treatment
- Suspected aortic dissection
- STEMI: any prior intracranial hemorrhage, or ischemic stroke within 3 months (except AIS treated within 4.5 hr). PE (alteplase label): recent stroke
- Stroke: mild non-disabling deficit (no benefit over dual antiplatelets)
- Stroke, 2026 AHA/ASA absolute (ref 1): platelets below 100,000/mm³, INR over 1.7, aPTT over 40 s or PT over 15 s; infective endocarditis; intra-axial neoplasm; aortic arch dissection; intracranial or spinal surgery, or moderate to severe traumatic brain injury, within 14 days; acute spinal cord injury within 3 months; amyloid-related imaging abnormalities or amyloid immunotherapy
- STEMI: ST depression alone unless true posterior MI is suspected (harm)
- Cathflo Activase: hypersensitivity to alteplase is the only labeled contraindication
Precautions
- Stroke relative (2026 AHA/ASA, ref 1; stroke-team decision): prior intracranial hemorrhage (higher risk with amyloid angiopathy); ischemic stroke within 3 months; DOAC within 48 hr (weigh last dose, renal function and reversal); GI or GU bleeding within 21 days; major surgery or trauma; STEMI within 3 months; active systemic malignancy; unruptured intracranial vascular malformation
- STEMI relative (2025 ACS): chronic, severe, poorly controlled hypertension; current oral anticoagulant, weighed against the expected time to PCI; ischemic stroke over 3 months ago
- Bleeding risk (all indications): major surgery within 3 weeks, internal bleeding within 2–4 weeks, recent obstetric delivery or organ biopsy, noncompressible puncture, prolonged (over 10 min) CPR, active peptic ulcer, severe liver or kidney disease. Also: diabetic hemorrhagic retinopathy or other hemorrhagic ophthalmic conditions, acute pericarditis, subacute bacterial endocarditis (infective endocarditis excludes a stroke lytic), septic thrombophlebitis (label items, ref 5); likely left-heart thrombus, dementia, and more than 10 cerebral microbleeds (benefit uncertain; stroke items, ref 1). Pregnancy: see Special Populations
- Anticoagulants (stroke): start before coagulation results; if the INR returns over 1.7 or the aPTT is elevated, the alteplase label and AHA/ASA say stop, while the tenecteplase label says monitor closely
- Planned PCI (STEMI): do not give a full-dose lytic as a bridge when primary PCI is available within 120 min
- Older adults: higher intracranial bleeding (stroke over 77 yr; STEMI 65 yr or older), but age alone does not exclude
Hold / Reassess If
- Severe headache, vomiting, acute hypertension or a worse neuro exam: stop the infusion; emergent noncontrast CT
- BP over 180/105 mmHg after a stroke lytic: check more often and treat
- Serious bleeding not controlled by pressure: stop the lytic and any heparin or antiplatelet
- Tongue, lip or airway swelling: stop any infusion; follow the angioedema steps
Rule Out Aortic Dissection: Dissection can hide behind chest pain with ST elevation, or it can look like a stroke. In that patient a lytic can be fatal. Suspected dissection is an absolute contraindication.
Adverse Effects & Toxicity
Common
- Bleeding is the most common reaction: puncture-site oozing, gum bleeding, bruising, epistaxis
- Orolingual angioedema, about 1%; ACE inhibitors raise the risk
- Reperfusion arrhythmias after coronary lysis (accelerated idioventricular rhythm, sinus bradycardia, PVCs, VT: usually transient; standard antiarrhythmic care); hypersensitivity (rash, urticaria)
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
| Symptomatic intracranial hemorrhage | Headache, vomiting, BP surge, falling GCS or new deficit, most within 36 hr. NINDS trials: 6.4% vs 0.6% placebo (Activase label Table 3) | Stop the lytic; CT; steps below; neurosurgery and hematology |
| Major extracranial bleeding | GI, GU or retroperitoneal bleeding (flank pain, hypotension); hemopericardium after STEMI lysis; can appear 1 or more days later. 3-hour alteplase AMI regimen (not the accelerated regimen above): GI bleeding 5%, GU 4% (Activase label Table 4, ref 5) | Stop the lytic, heparin and antiplatelets; compress; transfuse; fibrinogen replacement |
| Anaphylaxis | Urticaria, bronchospasm, laryngeal edema, shock | Stop; epinephrine, antihistamines, steroids |
| Embolic events | Cholesterol emboli (livedo, purple toes, AKI); emboli from a left heart thrombus | Investigate any new embolic event; supportive |
Bleeding within 24 hr of a stroke lytic
- Stop: the alteplase infusion, or the tenecteplase push if still in progress (terminate the Activase infusion for serious bleeding, ref 5)
- Labs: STAT CBC, PT/INR, aPTT, fibrinogen, type and crossmatch, plus an emergent noncontrast head CT
- Cryoprecipitate: 10 units IV over 10–30 min to keep fibrinogen at 150 mg/dL or higher (see fibrinogen)
- Antifibrinolytic: tranexamic acid 1,000 mg IV over 10 min, or aminocaproic acid 4–5 g IV over 1 hr, then 1 g/hr IV until bleeding is controlled
- Support: BP, ICP, temperature and glucose, plus protamine if heparin is running
Orolingual Angioedema Steps
- Airway: swelling of the larynx, floor of mouth or oropharynx, or rapid progression within 30 min, predicts intubation; awake fiberoptic is preferred
- Stop: the infusion; hold ACE inhibitors
- Medicines (drug classes per the Activase label, ref 5): methylprednisolone 125 mg IV, diphenhydramine 50 mg IV, famotidine 20 mg IV; if swelling progresses, epinephrine 1 mg/mL: 0.3 mg subcut, or 0.5 mg nebulized
- Bradykinin-directed options: icatibant 30 mg subcut (repeat every 6 hr, max 3 doses in 24 hr) or C1 esterase inhibitor 20 units/kg
Overdose & Toxicity Management
- Risk: alteplase above 0.9 mg/kg for stroke and 150 mg or more for MI raised intracranial hemorrhage; a STEMI tenecteplase band given for stroke doubles the dose
- Antidote: none; cryoprecipitate and an antifibrinolytic treat bleeding; the short half-life limits ongoing exposure
- Report: file a medication-error report; review drug selection and band charts
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: neuro checks and BP (stroke) | Every 15 min during and for 2 hr after, every 30 min for 6 hr, then hourly to 24 hr | BP over 180/105 mmHg: treat (labetalol, nicardipine, clevidipine); do not target SBP below 140 mmHg. Neuro decline: stop, CT |
| Clinical: ECG (STEMI) | Reassess for reperfusion 60–90 min after the lytic | Less than 50% ST resolution, ongoing pain, shock or arrhythmia: immediate angiography for rescue PCI |
| Clinical: bleeding and airway | Every assessment: puncture sites, gums, urine, stool, flank; tongue and lips for 2 hr | New bleeding or Hgb drop: stop lytic, STAT labs (hemoglobin); swelling: angioedema steps |
| Laboratory: aPTT (PE) | Near the end of the alteplase infusion | 2× normal or less: start anticoagulation |
| Imaging: CT or MRI (stroke) | 24 hr after the lytic | Required before starting antiplatelets or anticoagulants |
- Lab artifact: On therapy, coagulation tests and fibrinogen can read falsely abnormal. Ask whether the lab prevents in-vitro lysis. Without that, the numbers are unreliable.
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| Anticoagulants (heparin, enoxaparin, fondaparinux, DOACs, warfarin) | Additive bleeding | STEMI: part of the regimen at guideline doses. PE: start after lysis. Stroke: none for 24 hr |
| Antiplatelets (aspirin, clopidogrel, GP IIb/IIIa) | Additive bleeding | STEMI: aspirin plus clopidogrel. Stroke: no IV aspirin with or within 90 min of the lytic (harm); adjunctive eptifibatide gives no benefit |
| NSAIDs and other drugs that impair hemostasis | Additive bleeding | Avoid when possible |
| ACE inhibitors | Higher risk of orolingual angioedema | Watch tongue and lips; hold if swelling starts |
| Antifibrinolytics (tranexamic acid, aminocaproic acid) | Oppose fibrinolysis | Use only to treat lytic-related bleeding |
IV Compatibility
- Tenecteplase: incompatible with dextrose; flush with 0.9% sodium chloride before and after
- Alteplase: no other drug in the infusion; diluent 0.9% sodium chloride or D5W only
- Reteplase: incompatible with heparin
- Verify with an institutional compatibility resource.
Special Populations
- Pediatrics: Not established. Specialists decide (see Pediatric Dosing). For pediatric cerebral sinovenous thrombosis, ASH/ISTH suggest anticoagulation alone (ref 7).
- Neonates: A life-threatening neonatal renal vein thrombosis is a specialist call. ASH/ISTH suggest thrombolysis, then anticoagulation.
- Pregnancy: Case reports with related thrombolytics have not shown more major birth defects. The data are limited, though. Alteplase was embryocidal in rabbits at MI-level exposure. Pregnancy also raises bleeding risk. STEMI, stroke and massive PE can be fatal. Do not withhold life-sustaining therapy. Decide with obstetrics.
- Lactation: There are no data on tenecteplase or alteplase in milk. Weigh breastfeeding against the mother's need.
- Older Adults: Intracranial hemorrhage climbs with age. Over 75 yr with STEMI, give clopidogrel with no load and enoxaparin with no IV bolus. Some non-US protocols (ESC) halve the STEMI tenecteplase dose over 75 yr (pooled STREAM data, Bainey 2024). That change is not in the US label or the 2025 ACC/AHA guideline. Follow local protocol.
- Renal Impairment: No lytic dose adjustment. Severe kidney disease raises bleeding risk. Enoxaparin at CrCl below 30 mL/min: 1 mg/kg subcut every 24 hr. Fondaparinux is contraindicated.
- Hepatic Impairment: There is no labeled adjustment. Significant liver dysfunction raises bleeding risk.
- Obesity / Dosing Weight: Use actual body weight. Doses stop climbing at a ceiling: alteplase 90 mg at 100 kg or more, and tenecteplase 25 mg for stroke or 50 mg for STEMI at 90 kg or more. Do not delay treatment to weigh.
Field & Transport Considerations
- Scope: MSU teams give stroke lytics. Paramedic prehospital STEMI lysis happens only where a protocol and physician oversight exist. Critical-care transport continues alteplase infusions. It varies by state and agency protocol.
- Storage & Stability: Powder keeps at room temperature up to 30°C (86°F) or refrigerated. Protect Activase from light. Cathflo stays refrigerated at 2–8°C (36–46°F). Do not leave kits in a hot vehicle.
- Carried Concentration: Tenecteplase is 5 mg/mL in both vial sizes. Read the stroke band, not the STEMI band.
- Infusions in Transport: Alteplase runs on a pump, on its own dedicated line. Nothing else goes in that line. Record the start and finish times.
- After a Stroke Lytic: No IM injections, new punctures or antithrombotics. If the neuro exam worsens, stop the infusion and divert for CT (schedule in Monitoring).
- After a STEMI Lytic: Keep defibrillator pads on. Watch for reperfusion arrhythmias.
- Handoff Essentials: Hand off the agent and mg dose, the weight you used, LKW, bolus and infusion times, the BP and neuro trend, antithrombotics given, and any bleeding or swelling.
Clinical Pearls
Exam Discriminator: STEMI vs ST Depression: Lytics are for ST elevation, or a true posterior MI, when PCI is more than 120 min away. ST depression alone gets no lytic. The lytic adds bleeding and gives nothing back.
Disabling, Not a Number: The NIHSS score is not the test. A disabling deficit gets treated even when the score is low, such as a patient who cannot walk. Isolated sensory loss gets dual antiplatelet therapy, not a lytic.
Antiplatelets Do Not Exclude: Aspirin does not rule a patient out. Neither does dual antiplatelet therapy. They remain eligible for a stroke lytic.
Do Not Skip the Lytic Before Thrombectomy: Qualifies for both? The lytic goes in as fast as possible. Then send them for thrombectomy.
Pharmacology
Mechanism of Action
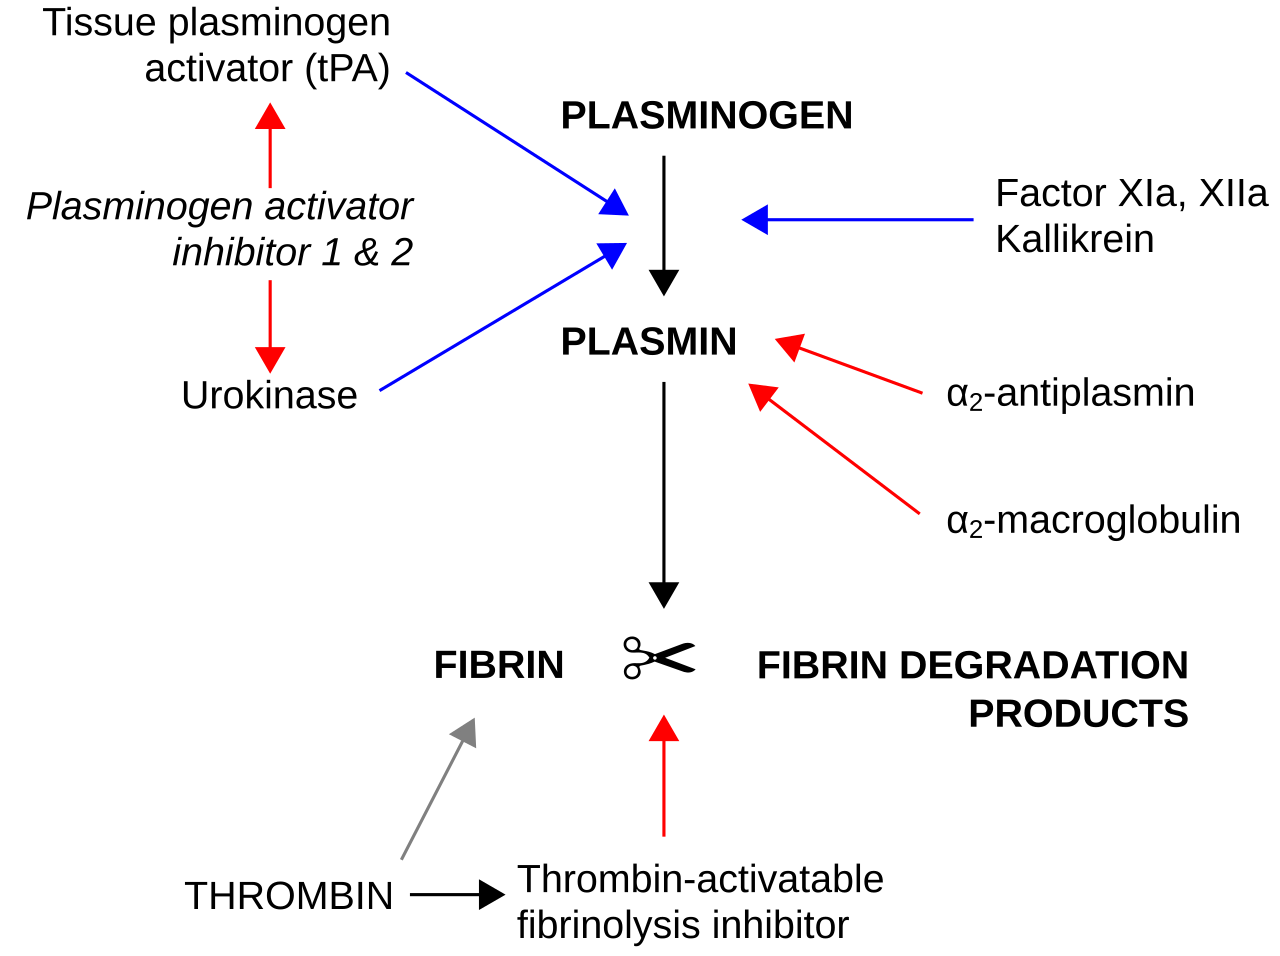
- The drug binds fibrin inside the thrombus. Clot-bound plasminogen becomes plasmin. Plasmin cuts the fibrin, so the clot dissolves and flow returns.
- Fibrin specificity limits systemic plasminogen activation. It does not prevent it. The result is bleeding at punctures, recent surgery sites and the brain.
- Tenecteplase is a modified tPA. It is more fibrin specific and clears more slowly. That allows a single bolus.
- Antifibrinolytics such as tranexamic acid and aminocaproic acid stop plasminogen from binding to fibrin.
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| IV (alteplase) | Immediate | During the infusion | Mostly cleared within minutes; bleeding risk outlasts the drug |
| IV (tenecteplase) | Immediate | End of the bolus | Hours; bleeding can appear 1 or more days later |
| IV (reteplase) | Immediate | After each bolus | Short; second bolus at 30 min |
| Intracatheter (Cathflo) | Local | 30–120 min dwell | Systemic levels not expected to reach pharmacologic range |
- Half-life: alteplase initial under 5 min; tenecteplase terminal 90–130 min; reteplase effective 13–16 min
- Metabolism / Elimination: hepatic clearance for alteplase and tenecteplase; reteplase by liver and kidney
Names & Classification
- Generic Name
- Alteplase (AL-te-plase, /ˈæltəpleɪs/); tenecteplase (ten-EK-te-plase, /tɛˈnɛktəpleɪs/); reteplase
- Brand Names
- Activase and Cathflo Activase (alteplase); TNKase (tenecteplase); Retavase (reteplase). Streptokinase is no longer available in the US
- Pharmacologic Class
- Plasminogen activators (recombinant tPA and variants)
- Therapeutic Class
- Thrombolytics (fibrinolytics)
- Controlled Substance
- Not controlled
- ISMP High-Alert
- Yes: ISMP high-alert medication (antithrombotic agents, including thrombolytics)
- Look-Alike / Sound-Alike
- Activase / TNKase / Cathflo Activase; alteplase / tenecteplase; tPA / TXA (tranexamic acid)
- Error-Prone Abbreviations to Avoid
- "tPA", "TPA", "rt-PA" and "TNK": write the generic name
References
- Prabhakaran, S., Gonzalez, N. R., Zachrison, K. S., et al. (2026). 2026 guideline for the early management of patients with acute ischemic stroke: A guideline from the American Heart Association/American Stroke Association. Stroke, 57(8), e316–e436. https://doi.org/10.1161/STR.0000000000000513
- Rao, S. V., O'Donoghue, M. L., Ruel, M., et al. (2025). 2025 ACC/AHA/ACEP/NAEMSP/SCAI guideline for the management of patients with acute coronary syndromes. Circulation, 151(13), e771–e862. https://doi.org/10.1161/CIR.0000000000001309
- Creager, M. A., Barnes, G. D., Giri, J., et al. (2026). 2026 AHA/ACC/ACCP/ACEP/CHEST/SCAI/SHM/SIR/SVM/SVN guideline for the evaluation and management of acute pulmonary embolism in adults. Circulation, 153(12), e977–e1051 (correction: Circulation, 154(2), e24). https://doi.org/10.1161/CIR.0000000000001415
- Genentech, Inc. (2025). TNKase (tenecteplase) for injection: Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=e647640d-c395-4b4b-a0be-1162f9c21d84
- Genentech, Inc. (2022; DailyMed update 2026). Activase (alteplase) for injection: Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=c669f77c-fa48-478b-a14b-80b20a0139c2
- Genentech, Inc. (2019). Cathflo Activase (alteplase) for injection: Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=91ecdef2-95ff-42dd-a31c-c8a09cab3ad9
- Monagle, P., Azzam, M., Bercovitz, R., et al. (2025). American Society of Hematology/International Society on Thrombosis and Haemostasis 2024 updated guidelines for treatment of venous thromboembolism in pediatric patients. Blood Advances, 9(10), 2587–2636. https://doi.org/10.1182/bloodadvances.2024015328
- Baig, M. U., & Patel, P. (2026). Thrombolytic therapy. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK557411/
- Cao, D., Arens, A. M., Chow, S. L., et al. (2025). Part 10: Adult and pediatric special circumstances of resuscitation: 2025 American Heart Association guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation, 152(16, suppl 2). https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/adult-and-pediatric-special-circumstances-of-resuscitation
- Otto, C. M., Nishimura, R. A., Bonow, R. O., et al. (2021). 2020 ACC/AHA guideline for the management of patients with valvular heart disease. Circulation, 143(5). https://doi.org/10.1161/CIR.0000000000000923
- Bainey, K. R., Welsh, R. C., Zheng, Y., et al. (2024). Pharmaco-invasive strategy with half-dose tenecteplase in STEMI patients: Prespecified pooled analysis of patients 75 years and older in STREAM-1 and STREAM-2. Journal of the American College of Cardiology, 83(13), 870. https://doi.org/10.1016/s0735-1097(24)02860-2
- Meyer, G., Vicaut, E., Danays, T., et al. (2014). Fibrinolysis for patients with intermediate-risk pulmonary embolism. New England Journal of Medicine, 370(15), 1402–1411. https://doi.org/10.1056/NEJMoa1302097
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.