

Bedside Snapshot
- Normal (Adult)
- INR 0.8–1.1; PT 11–13.5 s (same in SI); typical, reagent-specific. Warfarin target INR 2.0–3.0 for most indications, 2.5–3.5 for mechanical mitral valves
- Critical Values
- No critical low. INR >5.0 (typical; lab-specific). Any INR above target with bleeding is an emergency
- High Suggests
- Warfarin excess or a new interacting drug
- Liver failure, DIC, massive transfusion
- Vitamin K deficiency (newborn VKDB, malabsorption)
- Superwarfarin rodenticide; rivaroxaban or edoxaban
- Low Suggests
- Below 0.8: rarely clinically significant, usually a specimen issue. Below target on warfarin: missed doses, enzyme inducers or more dietary vitamin K, so clot and stroke risk
- Act Now If
- Bleeding or head injury on warfarin with a high INR: airway, pressure, IV access, INR, CBC and type and crossmatch; notify medical control; 4F-PCC plus IV vitamin K for major bleeding
- Watch Out For
- A normal INR does not rule out a DOAC: apixaban barely changes it. Get the drug and last-dose time before calling a head-injured patient not anticoagulated
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult | PT 11–13.5 s; INR 0.8–1.1 | Same (seconds; INR has no unit) | Typical; each thromboplastin reagent has its own PT range |
| Pregnancy | Same as adult | Same as adult | Normal or slightly short: factor levels rise in pregnancy |
| Older adult | Same as adult | Same as adult | — |
| Neonate, term (venous) | Higher than adult; use the lab's neonatal range | Same | Reagent- and lab-specific; the newborn system matures over the first months |
| Infant and child | Lab age-specific range | — | Close to adult after early infancy |
Severity & critical values
| Level | INR | SI | What it means / typical findings |
|---|---|---|---|
| Normal | 0.8–1.1 | Same | Does not exclude apixaban effect, a platelet disorder or a factor deficiency on the aPTT side |
| Mildly prolonged, no anticoagulant | 1.2–1.9 | Same | Early liver injury, vitamin K deficiency, early DIC or a specimen problem; repeat and investigate |
| Usual warfarin target | 2.0–3.0 | Same | Most indications (target 2.5); higher for some mechanical valves (table below) |
| Above target on warfarin | Above range to <4.5 | Same | Bleeding risk rising; dose adjustment by the anticoagulation team |
| Supratherapeutic | 4.5–10 | Same | Hold warfarin; vitamin K not routinely needed without bleeding |
| Markedly supratherapeutic | >10 | Same | Hold warfarin and give oral vitamin K, even without bleeding |
| Critical | >5.0 | Same | Typical; lab-specific call value. Assess for bleeding and find the cause; off warfarin it means severe coagulopathy |
Warfarin INR targets
| Indication | Target (range) | Notes |
|---|---|---|
| Venous thromboembolism (DVT, PE) | 2.5 (2.0–3.0) | All treatment durations |
| Atrial fibrillation | 2.5 (2.0–3.0) | Non-valvular AF; also AF with mitral stenosis |
| Mechanical aortic valve (bileaflet or Medtronic Hall) | 2.5 (2.0–3.0) | Sinus rhythm, no left atrial enlargement, and no added thromboembolic risk factors. Use the 3.0 row below when risk factors are present |
| Mechanical aortic valve with thromboembolic risk factors or an older-generation valve (caged-ball or tilting-disk) | 3.0 (2.5–3.5) | Risk factors: atrial fibrillation, prior thromboembolism, left ventricular dysfunction, hypercoagulable state. Bridging and aspirin per the guideline and prescriber |
| Mechanical mitral valve; caged-ball or caged-disk valve | 3.0 (2.5–3.5) | DOACs are not an alternative for mechanical valves |
| Bioprosthetic mitral valve | 2.5 (2.0–3.0) | First 3–6 months after surgical insertion (guideline: reasonable, INR 2.5) |
Valve targets: these come from the 2020 ACC/AHA valvular heart disease guideline (see References), and that guideline gives the INR for each valve type. The patient's own prescribed target governs. Confirm it with the prescriber. Mechanical valves need a VKA. DOACs are not an alternative.
Conversion: none. The PT is reported in seconds. The INR is a unitless ratio in both systems.
Normal is about 1.0. The International Sensitivity Index (ISI) calibrates each thromboplastin reagent. That is why INRs agree between labs in patients stably anticoagulated with warfarin.
Causes of Abnormal Results
High (prolonged PT, INR >1.1)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Vitamin K antagonist | Warfarin excess: dose error, new interacting drug, illness, less dietary vitamin K | Medication list; recent antibiotic, antifungal or amiodarone start |
| Other anticoagulant | Rivaroxaban, edoxaban, argatroban, dabigatran (variable); apixaban little or none | Time of last dose; INR does not measure their effect |
| Vitamin K deficiency | Newborn vitamin K deficiency bleeding (VKDB); malnutrition, malabsorption, biliary obstruction, prolonged antibiotics | No birth vitamin K; poor intake; corrects with vitamin K |
| Reduced synthesis | Acute liver failure, decompensated cirrhosis, shock liver | Jaundice, encephalopathy, low albumin; factor V low |
| Consumption | Disseminated intravascular coagulation (DIC): sepsis, trauma, obstetric catastrophe, malignancy | aPTT also long; low platelets and fibrinogen, high D-dimer |
| Dilution and blood loss | Massive hemorrhage resuscitated with red cells and crystalloid | aPTT also long; fibrinogen falls early |
| Long-acting rodenticide | Superwarfarin (brodifacoum) ingestion: accidental, intentional or covert | Very high INR, no warfarin prescription, rebound after short treatment |
| Inherited factor deficiency | Factor VII (isolated long PT); factors X, V, II or fibrinogen (PT and aPTT long) | Lifelong bleeding history; family history |
Low (below target on warfarin, INR <2.0)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Not enough drug | Missed doses, recent dose reduction, held for a procedure | Pill count, recent hospital stay |
| Enzyme induction | Rifampin, carbamazepine, phenobarbital, St. John's wort | New drug or herbal product |
| More vitamin K | Large increase in leafy greens, supplements or enteral feeds | Diet change |
A subtherapeutic INR puts the patient at risk of clots and stroke. It is not a bleeding problem. A value below normal (INR <0.8) is rarely clinically significant. Usually it is a specimen or collection issue. It does not diagnose a clotting tendency.
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Confirm a full light-blue top drawn away from heparin. Recheck an unexpected point-of-care (POC) result, or any POC INR above the therapeutic range, with a venous lab sample.
- How sick is the patient? Bleeding, head injury, a falling hemoglobin or hypotension all matter more than the number. With any of them, an INR above normal is an emergency (Management Priorities).
- On which anticoagulant? On warfarin, compare the INR with the patient's target. On a DOAC or argatroban, the INR does not measure the drug. Ask which drug, what dose and when it was last taken.
- Not anticoagulated? Read the PT/INR with the aPTT, platelets, fibrinogen and D-dimer (tables below) and ask about liver disease, diet, antibiotics and rodenticide exposure.
- Trend beats a single value. One number is a snapshot. A rising INR in sepsis suggests DIC. In liver injury, it marks lost synthetic function.
- Escalate or dispose. Major bleeding on warfarin: reverse now. New INR ≥1.5 with encephalopathy and no known cirrhosis suggests acute liver failure: transplant-center discussion. Unexplained isolated long PT: hematology.
PT/INR and aPTT pattern
| PT/INR | aPTT | Suggests |
|---|---|---|
| Prolonged | Normal | Warfarin, early vitamin K deficiency or liver disease, factor VII deficiency, rivaroxaban or edoxaban |
| Normal | Prolonged | Heparin, factor VIII, IX, XI or XII deficiency, von Willebrand disease, lupus anticoagulant |
| Prolonged | Prolonged | DIC, massive transfusion, severe liver disease, high-INR warfarin, superwarfarin, factor X, V, II or fibrinogen deficiency |
| Normal | Normal, but bleeding | Platelet disorder or thrombocytopenia, von Willebrand disease, factor XIII deficiency, apixaban |
Long PT off warfarin: which cause?
| Finding | Vitamin K deficiency | Liver failure | DIC |
|---|---|---|---|
| Factor V | Normal (not vitamin K-dependent) | Low | Low |
| Factor VIII | Normal | Normal or high | Low or normal |
| Fibrinogen and platelets | Normal | Low-normal; platelets low with portal hypertension | Falling; D-dimer high |
| Response to vitamin K | INR improves within hours to a day | Little or none | None |
INR as a liver synthetic function marker
- Prognosis, not bleeding risk: in cirrhosis, the INR tracks how well the liver makes clotting factors. It misses the parallel fall in natural anticoagulants (proteins C and S, antithrombin) and the rise in factor VIII and von Willebrand factor. AASLD 2020 guidance: do not use it to gauge procedural bleeding risk. Do not give plasma or other measures to lower it before procedures in patients not taking warfarin.
- MELD: the Model for End-Stage Liver Disease combines the INR with bilirubin, creatinine and sodium (MELD-Na). MELD 3.0 (2021) adds albumin and sex. It predicts 90-day survival and ranks liver transplant candidates.
- Liver INR is not the warfarin INR: the ISI is calibrated on warfarin plasma. Run a liver patient's sample on different reagents and the INRs can disagree.
Management Priorities
Doses vary by protocol; follow local protocols and medical direction.
Emergency: Major or life-threatening bleeding on warfarin
- Stop and support: hold warfarin; pressure, airway and hemodynamic support; large-bore access; type and crossmatch. Any of these counts: intracranial bleeding, airway bleeding or hemodynamically significant bleeding.
- Labs now: INR close to the time of dosing (4F-PCC is dosed by it), CBC, fibrinogen, creatinine.
- Reverse: 4-factor prothrombin complex concentrate (4F-PCC) dosed by INR and weight, or a fixed dose per institutional protocol, plus vitamin K 5–10 mg IV, diluted, no faster than 1 mg/min. Plasma 10–15 mL/kg only if 4F-PCC is unavailable.
- Monitor & repeat: Recheck the INR after the 4F-PCC infusion, then again 6–8 hr after IV vitamin K. Skip the vitamin K and the INR rebounds. Watch for thrombosis.
High INR on warfarin: what to do
| Situation | Action | Recheck |
|---|---|---|
| Above target, <4.5, no bleeding | Lower or skip the next dose per the anticoagulation team; look for the cause | Within days, per the team |
| INR 4.5–10, no bleeding | Hold warfarin; no routine vitamin K (no proven benefit; overcorrection risk) | Per the anticoagulation team; restart at a lower dose when in range |
| INR >10, no bleeding | Hold warfarin; oral vitamin K 2.5–5 mg (protocol-dependent) | INR at 12–48 hr; repeat vitamin K if still high |
| Minor or nonmajor bleeding | Hold warfarin, local measures; vitamin K 2–5 mg PO or IV if admission, procedure or transfusion is needed | INR 6–8 hr (IV) or 12–48 hr (PO) |
| Major or life-threatening bleeding, or urgent surgery | 4F-PCC plus vitamin K 5–10 mg IV (box above) | INR after 4F-PCC and at 6–8 hr |
Medications
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| 4F-PCC (Kcentra) | Pre-treatment INR 2–<4: 25 units/kg; INR 4–6: 35 units/kg; INR >6: 50 units/kg IV (factor IX units; weight capped at 100 kg); max 2,500 / 3,500 / 5,000 units (Kcentra label); repeat dosing: safety and efficacy not established | Not established in children: consult pediatric hematology | INR ≤1.3 at 30 min in about 55–62% of trial patients (label). Infuse 0.12 mL/kg/min, max 8.4 mL/min. Boxed warning: thrombosis. Contraindicated in known anaphylactic or severe systemic reactions to Kcentra or any component (including heparin, factors II, VII, IX and X, proteins C and S, antithrombin III, human albumin), in DIC, and in known HIT (contains heparin). Other 4F-PCC products, such as Balfaxar, have their own label dosing: use the product-specific label |
| Vitamin K (phytonadione) | Major bleed: 5–10 mg IV, no faster than 1 mg/min; nonmajor bleed: 2–5 mg PO or IV; INR >10 without bleeding: 2.5–5 mg PO; recheck INR and repeat if high | VKDB bleeding: 1 mg per protocol, by subcut or slow IV route; avoid IM in an actively bleeding infant (hematoma risk); neonatal IV use only with the label's hypersensitivity precautions; child on warfarin: per pediatric hematology; repeat per INR | IV: INR falls over hours; PO slower. Anaphylaxis risk with IV: dilute, infuse slowly, monitor. Route: IV for major bleeding. Subcutaneous absorption is unpredictable and too slow for urgent reversal. Differs from FDA label: the boxed warning says avoid IV and IM unless the subcutaneous route is not feasible. |
| Plasma (FFP) | 10–15 mL/kg IV when 4F-PCC is unavailable; titrate to INR and bleeding; watch volume | 10–15 mL/kg IV; same | Slow: thawing, ABO match and large volume; risk of circulatory overload and lung injury |
| Idarucizumab | Dabigatran reversal: 5 g IV; single dose | Not established in children: consult | Dabigatran only; the INR does not guide it (use thrombin time or aPTT) |
| 4F-PCC for factor Xa inhibitors | Apixaban, rivaroxaban, edoxaban major bleeding: per institutional protocol (off-label); no INR-based dose | Not established in children: consult | Andexanet alfa (Andexxa) availability in the US has changed: confirm local stock and current status with pharmacy. Otherwise use 4F-PCC per institutional protocol (ACC 2020 ECDP) |
Definitive care & disposition
- Intracranial hemorrhage on warfarin: 4F-PCC and IV vitamin K immediately, repeat CT per protocol, neurosurgery and ICU.
- Superwarfarin ingestion: poison center or toxicology; high-dose oral vitamin K for weeks to months guided by serial INRs.
- Liver failure: treat the bleeding, not the INR. Vitamin K is for suspected deficiency only. Acute liver failure goes to a transplant center early.
- DIC: treat the cause. If it is bleeding, replace platelets, fibrinogen and plasma. Per label, 4F-PCC is contraindicated in DIC.
- ICU criteria: intracranial or airway bleeding, ongoing transfusion, reversal with hemodynamic instability, or acute liver failure with encephalopathy.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
Fingerstick INR meters show up in anticoagulation clinics, at home and on some transport programs. Within the usual range, they agree well with the lab. They can read differently at high INRs and in some patients: hematocrit outside the device's range, or antiphospholipid antibodies. Recalls have hit both falsely high and falsely low strips. Confirm a high or unexpected POC INR with a venous lab sample. And never use a POC INR for a DOAC.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Handoff (Paramedic/RN/CCT) | Anticoagulant, dose and last-dose time; INR with draw time; 4F-PCC units and time; vitamin K dose, route and time; plasma volume; next INR due |
| Head injury on an anticoagulant | Go to a CT-capable center even when well-appearing; give the medication list to the receiving team |
| After 4F-PCC | Watch for new chest pain, dyspnea, limb swelling or stroke signs (thrombosis); expect the INR to rise again if vitamin K was not given |
| Vitamin K infusing | Pump, no faster than 1 mg/min; stop for flushing, dyspnea or hypotension (anaphylaxis) |
| When to delay or redirect | Ongoing major bleeding without reversal available, or acute liver failure: go to a center with blood bank, neurosurgery or transplant hepatology |
Timing & Kinetics
| Parameter | Value | Clinical implication |
|---|---|---|
| Warfarin onset | Effect within 24 hr; peak 72–96 hr | Early INR rise reflects factor VII; full antithrombotic effect takes days |
| Factor half-lives | VII 4–6 hr; protein C about 8 hr; IX 24 hr; X 48–72 hr; II about 60 hr | Protein C falls early: overlap heparin when starting warfarin for VTE |
| Warfarin half-life | Effective 20–60 hr (mean about 40 hr) | After stopping, the effect lasts 2–5 days |
| Monitoring on warfarin | Daily at start until stable in range, then every 1–4 weeks | More often with new drugs, illness, diet change or kidney disease |
| Heparin overlap | 4–5 days and until the INR is in range | Draw the INR ≥5 hr after an IV heparin bolus, 4 hr after stopping an infusion, 24 hr after subcut heparin |
| Argatroban to warfarin | Argatroban raises the INR; stop it when the INR is >4 on combined therapy (doses up to 2 mcg/kg/min) | Repeat the INR 4–6 hr later; restart argatroban if below range |
| 4F-PCC | INR ≤1.3 at 30 min in about 55–62% of trial patients (Kcentra label) | Effect wanes over hours without vitamin K |
| Vitamin K | IV: INR falls within hours; PO: slower | Recheck 6–8 hr after IV and 12–48 hr after PO |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | INR higher than adult at birth; low vitamin K stores | Use age-specific ranges; VKDB without the birth dose; a draw from a heparinized umbilical line affects coagulation tests |
| Children & adolescents | Close to adult values; warfarin use is extrapolated from adult data | Targets set by pediatric hematology or cardiology; avoid contact sports while on warfarin |
| Pregnancy | PT normal or slightly short | Warfarin is contraindicated in pregnancy except some mechanical valves; monitor breastfed infants of mothers on warfarin for bruising |
| Older adults | Greater INR response to warfarin from age 60 | Lower starting and maintenance doses; more falls and bleeding |
| CKD / dialysis | More INR variability on warfarin | Check INR more often; warfarin can cause calciphylaxis |
| Liver disease | INR rises with synthetic failure; warfarin effect potentiated | INR overstates bleeding risk; closer monitoring on warfarin |
| Other: genetics and ancestry | CYP2C9 and VKORC1 variants; Asian patients often need lower doses | Genotype-guided starting doses where available; slower titration |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Underfilled citrate tube | ↑ (False +) | Too much citrate for the plasma volume | Fill to the line; the lab rejects underfilled tubes |
| Hematocrit >55% | ↑ (False +) | Less plasma, so relatively excess citrate | Lab supplies a tube with adjusted citrate volume |
| Draw through a heparinized line | ↑ | High heparin can exceed the reagent's heparin neutralizer | Peripheral draw, or adequate discard per policy |
| Clotted or hemolyzed sample | Unreliable | Factors consumed or activated | Reject and redraw |
Medications & supplements
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Amiodarone, fluconazole, metronidazole, trimethoprim-sulfamethoxazole | ↑ on warfarin | Inhibit warfarin metabolism (CYP2C9 and others) | Check INR within days of starting or stopping; anticipate dose reduction |
| Any antibiotic or antifungal | ↑ or ↓ on warfarin | Inconsistent; illness and diet also change | Monitor INR closely when started or stopped |
| Rifampin, carbamazepine, phenobarbital, St. John's wort | ↓ on warfarin | Induce warfarin metabolism | Expect higher dose needs; recheck after stopping |
| Rivaroxaban, edoxaban, argatroban, dabigatran | ↑ | Inhibit factor Xa or thrombin in the test | INR does not measure these drugs |
| Aspirin, clopidogrel, NSAIDs, SSRIs | No change | Increase bleeding risk without changing the INR | Count them in bleeding risk |
| Dietary vitamin K, supplements, enteral feeds | ↓ on warfarin | Bypass warfarin's block | Keep intake consistent; do not avoid greens |
Assay & device-specific
Thromboplastin reagents differ in sensitivity (ISI). That is why the PT in seconds is not comparable between labs. For warfarin, the INR is comparable. POC meters and some lab reagents read differently in patients with antiphospholipid antibodies. Confirm against the lab method the patient's anticoagulation service uses.
Common misinterpretations
- "INR 2.5 in cirrhosis means autoanticoagulated": false. These patients still form clots.
- "Normal INR, so no anticoagulant effect": false for apixaban. The INR also misses heparin and platelet drugs.
- "Low INR means hypercoagulable": an INR below 0.8 has no proven clinical meaning. Recheck the sample.
- "Warfarin INR in range, so no bleeding risk": bleeding still happens in range, especially with antiplatelet drugs or NSAIDs.
Physiology & Test Basics
What it measures
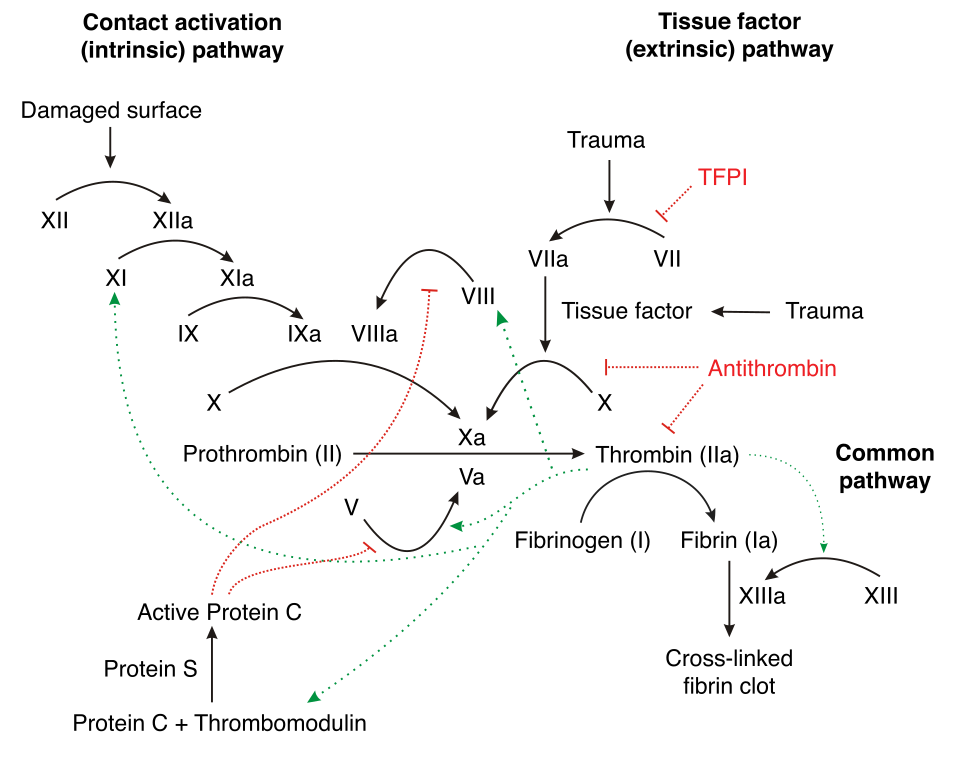
The prothrombin time (PT) counts the seconds citrated plasma takes to clot once you add tissue factor (thromboplastin), phospholipid and calcium. It tests the tissue factor (extrinsic) and common pathways: factor VII, then X, V, II (prothrombin) and fibrinogen. The INR turns the PT into a ratio that does not depend on the reagent. That matters for patients on warfarin. The aPTT covers the contact pathway instead.
Physiology & regulation
- Vitamin K-dependent factors: the liver needs vitamin K to activate factors II, VII, IX and X, and proteins C and S. Three of these (II, VII, X) sit on the PT side.
- Warfarin: blocks vitamin K recycling (VKORC1). New factors come out inactive. The PT lengthens as the old factors get used up, fastest for factor VII.
- Liver: makes almost every PT factor. A long PT is an early sign of synthetic failure. Factor VIII comes mainly from endothelium, and it stays normal or high.
- Lab pathways vs the body: in the body, tissue factor starts clotting and thrombin amplifies it. The PT and aPTT split is a test-tube model.
How it is measured
- Specimen: light-blue top (3.2% sodium citrate), filled to the line (9 parts blood to 1 part citrate); platelet-poor plasma after centrifugation. Fingerstick whole blood for POC meters.
- Method: the analyzer detects the clot automatically once thromboplastin is added. It applies the reagent's ISI and the lab's mean normal PT to report the INR.
- Timing: no fasting; on warfarin, draw at a consistent time relative to the dose.
Why it matters
Dose warfarin by the INR. Use the PT in seconds to diagnose a long PT. The INR guides every warfarin dose and every warfarin reversal. It flags DIC and dilution in sepsis and trauma. It tracks liver synthetic failure, and it is part of the MELD score and the definition of acute liver failure. Misread, it leads to unnecessary plasma or a missed DOAC effect.
Clinical Pearls
References
- Amneal Pharmaceuticals LLC. (2022). Warfarin sodium tablets, USP: Prescribing information (revised 11/2022; DailyMed record updated May 2026). DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=558b7a0d-5490-4c1b-802e-3ab3f1efe760
- CSL Behring LLC. (2023). Kcentra (prothrombin complex concentrate, human): Prescribing information (revised May 2023). https://labeling.cslbehring.com/PI/US/Kcentra/EN/Kcentra-Prescribing-Information.pdf
- Tomaselli, G. F., Mahaffey, K. W., Cuker, A., et al. (2020). 2020 ACC expert consensus decision pathway on management of bleeding in patients on oral anticoagulants. Journal of the American College of Cardiology, 76(5), 594–622. https://doi.org/10.1016/j.jacc.2020.04.053
- Witt, D. M., Nieuwlaat, R., Clark, N. P., et al. (2018). American Society of Hematology 2018 guidelines for management of venous thromboembolism: Optimal management of anticoagulation therapy. Blood Advances, 2(22), 3257–3291. https://doi.org/10.1182/bloodadvances.2018024893
- Khatib, R., Ludwikowska, M., Witt, D. M., et al. (2019). Vitamin K for reversal of excessive vitamin K antagonist anticoagulation: A systematic review and meta-analysis. Blood Advances, 3(5), 789–796. https://doi.org/10.1182/bloodadvances.2018025163
- Northup, P. G., Garcia-Pagan, J. C., Garcia-Tsao, G., et al. (2021). Vascular liver disorders, portal vein thrombosis, and procedural bleeding in patients with liver disease: 2020 practice guidance by the American Association for the Study of Liver Diseases. Hepatology, 73(1), 366–413. https://doi.org/10.1002/hep.31646
- Kim, W. R., Mannalithara, A., Heimbach, J. K., et al. (2021). MELD 3.0: The Model for End-Stage Liver Disease updated for the modern era. Gastroenterology, 161(6), 1887–1895.e4. https://doi.org/10.1053/j.gastro.2021.08.050
- Otto, C. M., Nishimura, R. A., Bonow, R. O., et al. (2021). 2020 ACC/AHA guideline for the management of patients with valvular heart disease. Circulation, 143(5), e72–e227. https://doi.org/10.1161/CIR.0000000000000923
- Hospira, Inc. (2026). Vitamin K1 Injection (phytonadione injectable emulsion, USP): Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=e8808230-2c44-44c6-8cab-8f29b6b34051
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.