

Bedside Snapshot
- Use It For
- Moderate to severe acute trauma pain in a conscious, stable patient; brief painful procedures such as dressing changes (New Zealand, Canada). Not FDA-approved: unavailable in the US
- Adult Dose
- Trauma pain: 3 mL INH, self-administered via Penthrox inhaler; second 3 mL bottle only if needed
- Max 6 mL/day and 15 mL/week; not on consecutive days
- Pediatric Dose
- Age ≥6 yr (UK label): 3 mL INH, fixed dose, same limits as adults (max 6 mL/day). Under 6 yr: not established in the UK; New Zealand sets no lower age (minimum effective dose). Canada: not authorized under 18 yr
- Onset / Duration
- INH: relief after 6–10 breaths (median about 5 min) / 25–30 min with continuous use; about 1 hr with intermittent breaths
- Do Not Give / Hold If
- Altered consciousness (head injury, drugs, alcohol); significant renal impairment; hemodynamic instability; respiratory depression; malignant hyperthermia risk; prior liver injury from halogenated anesthetics
- Watch For
- Drowsiness or confusion (remove inhaler); respiratory depression (RR, SpO₂); hypotension, bradycardia (older adults); dose-related renal injury (mainly above dose limits); very rare liver injury even at analgesic doses
- Reversal / Rescue
- No specific reversal: remove the inhaler (effects usually resolve quickly); oxygen and ventilatory support as needed; polyuria after overdose: replace fluid and electrolytes
- Must Remember
- Not FDA-approved: US services cannot stock it. Where licensed, the patient holds the inhaler and self-titrates; never exceed 6 mL/day or 15 mL/week (fluoride nephrotoxicity).
Indications
US regulatory status: Methoxyflurane is not FDA-approved, and no US agency or hospital can stock it. It is not marketed in the United States. The reason goes back to 2005, when the FDA determined that the old anesthetic, Penthrane, was withdrawn for safety reasons: nephrotoxicity and hepatotoxicity. The Penthrox analgesic inhaler has no US marketing approval. In the US it may be used only within an FDA-authorized clinical investigation. It is licensed as an analgesic in Australia and New Zealand, the UK, Canada and many EU countries.
Emergency & Prehospital
- Moderate to severe acute pain from trauma (labelled indication in every licensing country): conscious, hemodynamically stable patients, e.g., fractures, dislocations, sprains, lacerations, burns
- Early analgesia without IV access: the patient holds a portable, non-invasive inhaler, and relief can come within a few breaths
ED / ICU / Transport
- Acute trauma pain in the ED: in European ED trials it acted faster and reduced pain more than standard first-line analgesia
- Short painful procedures: dressing changes and similar brief procedures in monitored, conscious patients (labelled in New Zealand; Canada labels "interventional medical procedures" in adults)
- Outpatient procedures: e.g., bone marrow biopsy (studied in a placebo-controlled trial; off-label in the UK)
Other Uses
- Historical only: general anesthesia and obstetric (labor) analgesia. Anesthetic use is now contraindicated, and Canada does not authorize use in pregnancy or labor
- Not appropriate: chronic pain, breakthrough pain or closely repeated painful episodes in the same patient, because of the dose limits
Dosing & Administration
Doses vary by protocol; follow local protocols and medical direction.
Available Forms
- Penthrox 3 mL bottle: methoxyflurane 99.9% volatile liquid, 3 mL (fixed dose); stabilizer butylated hydroxytoluene (BHT)
- Combination pack: one 3 mL bottle, one single-patient Penthrox inhaler and one activated carbon (AC) chamber; the form ambulance services carry where licensed
- Other presentations: packs of ten bottles; New Zealand also lists a 1.5 mL bottle
- United States: no approved product; do not import or stock
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| Acute trauma pain | 3 mL INH (max 6 mL/day), self-administered through the Penthrox inhaler under supervision | One more 3 mL bottle only if needed; max 6 mL/day and 15 mL/week; not on consecutive days | UK and New Zealand limits. Canada: max 6 mL per 48 hr and 15 mL per 3 months; do not repeat a course within 3 months. Fixed dose, not weight-based. |
| Procedural pain (dressing changes, brief procedures) | 3 mL INH, inhaled intermittently during the procedure | Same limits; add up every bottle across repeated procedures (max 6 mL/day, 15 mL/week) | New Zealand and Canada (adults) indication; not a UK indication. Patient must stay conscious and monitored. |
Pediatric Dosing
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| Acute trauma pain, age ≥6 yr | 3 mL INH (fixed dose, not per kg), self-administered under supervision | Second 3 mL bottle only if needed; max 6 mL/day and 15 mL/week; not on consecutive days | UK label (2026) covers age 6 yr and older; children may need more breaths for relief. The New Zealand data sheet sets no lower age limit but data are limited: use the minimum effective dose. Canada: not authorized under 18 yr. |
| Age <6 yr | UK label: safety and efficacy not established under 6 yr; no dose recommended | — | New Zealand: no lower age limit, limited data; give the minimum effective dose. Follow local protocol; intranasal fentanyl is a weight-based alternative. |
Preparation & Administration
- Assemble: check the inhaler for damage; insert the AC chamber into the dilutor hole on top of the inhaler.
- Load: loosen the bottle cap (by hand or with the inhaler base), tilt the inhaler to 45° and pour the whole 3 mL into the base while rotating; recap the empty bottle. Load in a well-ventilated area.
- Coach: wrist loop over the patient's wrist; the patient holds the inhaler, takes a few gentle breaths (warn them of the fruity smell), then breathes normally and exhales back into the inhaler so exhaled vapor passes through the AC chamber.
- Titrate: inhale intermittently to effect; covering the dilutor hole with a finger gives stronger analgesia. Continuous inhalation shortens the duration of one bottle.
- Second bottle: pour it into the same inhaler; the AC chamber stays in place.
- Disposal: used inhaler and bottle into the sealed plastic bag provided; dispose per local requirements.
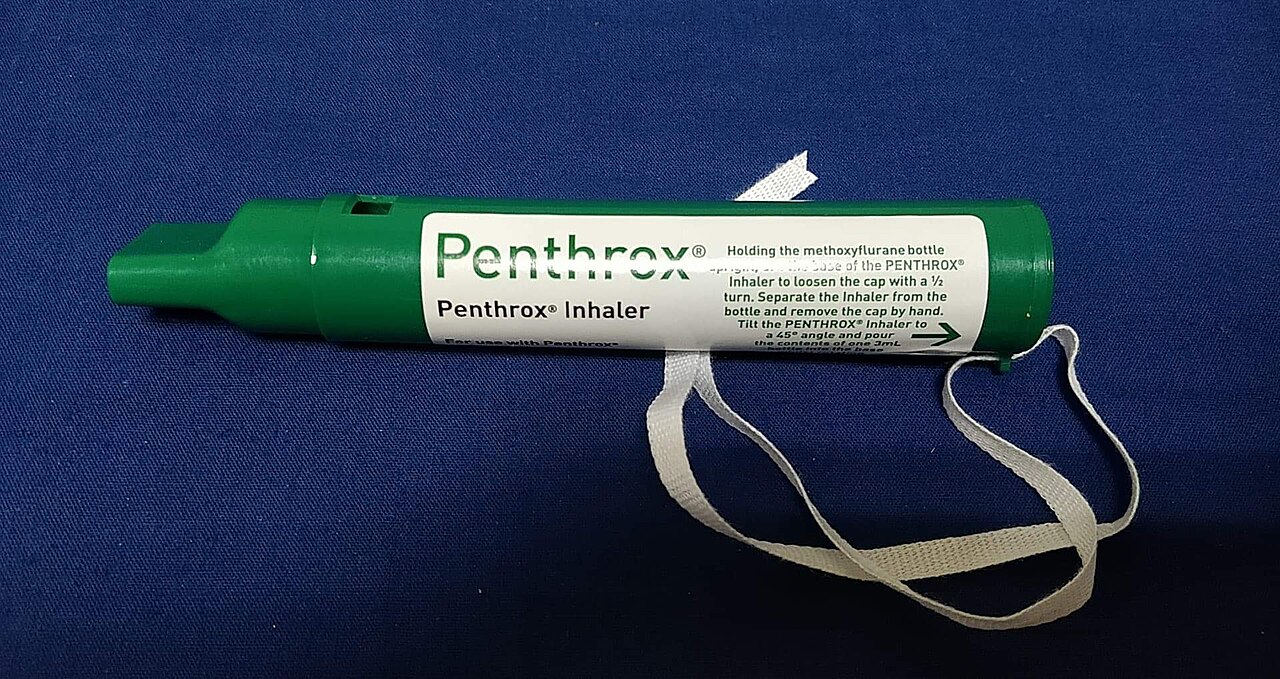
Dosing Notes:
- Record the time of the first breath and every bottle used. Each one counts toward the daily and weekly maximum.
- Lowest effective dose, every time. Older adults, obese patients and anyone with renal risk factors need the most care.
- Before discharge, advise the patient: no driving or operating machinery until any drowsiness or dizziness has fully resolved.
Contraindications & Precautions
Contraindications
- Altered level of consciousness from any cause, including head injury, drugs or alcohol
- Clinically significant renal impairment
- Clinically evident cardiovascular (hemodynamic) instability
- Clinically evident respiratory depression or respiratory impairment
- Known or genetic susceptibility to malignant hyperthermia, or severe reactions to inhaled anesthetics in the patient or relatives
- Liver damage after previous methoxyflurane or halogenated anesthetic exposure
- Hypersensitivity to methoxyflurane, any fluorinated anesthetic or BHT
- Use as an anesthetic agent
Precautions
- Renal risk factors: older age, conditions predisposing to renal injury, nephrotoxic drugs; preeclampsia: avoid (New Zealand data sheet).
- Diabetes: higher risk of nephropathy with impaired renal function, polyuria, obesity or poor control.
- Hepatic disease, recent halogenated anesthesia or repeat exposure: earlier exposure to halogenated anesthetics (e.g., sevoflurane, isoflurane, desflurane, or methoxyflurane itself) can raise the risk of liver injury, most of all within the last 3 months. Needing methoxyflurane more than once every 3 months calls for cautious judgement. Take care with underlying liver disease or enzyme inducers.
- Enzyme inducers and obesity: faster metabolism pushes fluoride levels up, and toxicity risk follows.
- Older adults and CNS depressants: be alert for hypotension, bradycardia and additive sedation. Canada: do not give with alcohol ingestion.
- Misuse potential: the CNS effects bring a small abuse risk. Misuse has been reported, but very rarely, after marketing. Store securely.
Hold / Reassess If
- Patient becomes drowsy, confused or stops following commands: take the inhaler away.
- Respiratory rate falls or SpO₂ drops: stop, give oxygen, support ventilation.
- Hypotension or bradycardia develops: stop and reassess.
- The 6 mL daily total is reached: no further methoxyflurane; switch to another analgesic.
Health Canada Serious Warnings: Doses above the therapeutic range cause serious, irreversible, dose-related nephrotoxicity, so treat the dose limits as hard stops. Hepatotoxicity has been seen very rarely, even at analgesic doses. There is no FDA boxed warning because there is no US label.
Adverse Effects & Toxicity
Common
- Dizziness: about 30% of adults and adolescents aged 12 yr and older in the pivotal ED trial (8% with placebo); 41% of children aged 6–17 yr
- Headache: about 22% (16% with placebo)
- Somnolence: about 5%
- Euphoria, feeling drunk, amnesia, slurred speech: euphoric mood in 12% of children
- Cough, nausea, altered taste: common in the UK label (altered taste uncommon in the New Zealand data sheet). In the pivotal trial, nausea (1.3% vs 3.4%) and vomiting (1.3% vs 2.7%) were no more frequent than with placebo
- Dry mouth, vomiting: uncommon (UK label)
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
| Excess sedation, respiratory depression | Drowsiness, falling RR or SpO₂, hypoxia (post-marketing reports at analgesic doses) | Remove inhaler; oxygen, airway positioning, assisted ventilation if needed |
| Nephrotoxicity | Polyuric (high-output) or oliguric renal failure hours to days after excessive dosing; rising creatinine and BUN | Prevent by dose limits; replace fluid and electrolyte losses; nephrology input. Often irreversible |
| Hepatotoxicity | Jaundice, hepatitis, rising liver enzymes; very rare, including hepatic failure | Supportive care; never re-expose |
| Hypotension, bradycardia | Mainly older adults; BP and HR on monitor | Stop, lay flat, IV fluids per protocol |
| Hypersensitivity | Rash or other hypersensitivity reactions (Canada patient information: difficulty breathing, facial swelling); BHT can cause contact dermatitis and irritate the eyes and mucous membranes | Stop; treat as allergic reaction or anaphylaxis |
Overdose & Toxicity Management
- Signs: anesthetic effects: excessive drowsiness up to loss of consciousness, low blood pressure, respiratory depression, pallor, muscle relaxation.
- Immediate: remove the inhaler. Effects usually resolve quickly. Give cardiorespiratory support as needed.
- Delayed renal injury: renal injury can come late. After repeated high doses, watch urine output and creatinine for days. If polyuria develops, replace fluid and electrolytes.
- Antidote: none. If malignant hyperthermia is suspected (a historical anesthetic-dose risk): treat per malignant hyperthermia protocol with dantrolene.
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: level of consciousness | Before use (must be alert) and continuously while inhaling | Drowsy, confused or not following commands: take the inhaler away |
| Clinical: RR and SpO₂ | Labels: monitor respiration (risk of respiratory depression and hypoxia). Suggested: baseline, then continuously or every 5 min during use; intervals per local protocol | Falling RR or SpO₂: stop, oxygen, support ventilation |
| Clinical: BP and HR | Suggested: baseline and after each bottle, closer in older adults; intervals per local protocol | Hypotension or bradycardia: stop and reassess |
| Clinical: pain score | Suggested: baseline and every 5 min during use | No relief after the second bottle: switch to another analgesic |
| Dose tracking | Each bottle; at handoff | Document mL and times; stop at 6 mL/day and 15 mL/week |
| Laboratory: renal | If limits were exceeded, renal risk factors exist or polyuria develops | Creatinine or BUN rising: treat as nephrotoxicity, replace losses |
| Laboratory: hepatic | If jaundice or malaise follows exposure |
No monitoring intervals appear in the labels. According to the Canadian monograph, standard opioid-type observation and monitoring after administration is not required.
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| CNS depressants (opioids, benzodiazepines, sedating antihistamines, alcohol) | Additive sedation and respiratory depression | Canada: avoid; if an opioid is needed, observe closely and consider a lower opioid dose |
| Nephrotoxic drugs (tetracyclines, aminoglycosides, colistin, polymyxin B, amphotericin B, IV contrast, NSAIDs) | Additive nephrotoxicity; tetracycline with anesthetic-dose methoxyflurane caused fatal renal failure | Avoid the combination; choose a non-nephrotoxic alternative |
| Enzyme inducers (alcohol, isoniazid, phenobarbital, rifampin, carbamazepine, efavirenz, nevirapine) | Faster metabolism to fluoride; higher toxicity risk | Avoid concomitant use |
| Sevoflurane | Raises serum fluoride further | Tell anesthesia; avoid sevoflurane anesthesia after methoxyflurane |
| Beta-blockers | Increased risk of hypotension | Monitor BP |
| IV epinephrine or norepinephrine | Myocardium only minimally sensitized (UK, Canada); the New Zealand data sheet advises using IV adrenaline or noradrenaline cautiously during administration | Use cautiously and monitor cardiac rhythm |
This is not an IV drug, so no IV compatibility data apply.
Special Populations
- Pediatrics: The UK label covers age 6 yr and older. The New Zealand data sheet sets no lower age limit but advises the minimum effective dose. Canada has not authorized use under 18 yr. Dizziness and euphoria are more common than in adults. The child must be able to hold and use the inhaler. Anesthetic-class label warning (UK, New Zealand): in animals, anesthetic exposure during rapid brain growth caused neuronal loss in the developing brain, mainly with prolonged or repeated exposure. Clinical significance at a single analgesic dose is unknown, so give the minimum effective dose. Doses: Pediatric Dosing table.
- Pregnancy: animal studies showed delayed fetal development with repeated dosing. Historical obstetric use at low concentrations showed little fetal effect. One report describes neonatal respiratory depression after high exposure. Neonates exposed during labor showed raised serum fluoride (Canada) and briefly raised serum uric acid (New Zealand). The same anesthetic-class warning on developing-brain neurotoxicity covers late pregnancy (New Zealand). Canada does not authorize use in pregnancy or labor. The UK advises caution, especially in the first trimester. Avoid in preeclampsia. In an emergency, prefer an alternative analgesic and follow local protocol.
- Lactation: Excretion into breast milk is unknown. Use with caution in breastfeeding patients.
- Older Adults: Fluoride peaks are higher and earlier, and hypotension and bradycardia are more common. Use the lowest effective dose and monitor BP.
- Renal Impairment: contraindicated in clinically significant renal impairment. Use caution with any condition that predisposes to renal injury. No dose adjustment exists for this, so avoid instead.
- Hepatic Impairment: contraindicated after prior liver injury from methoxyflurane or halogenated anesthetics. Take care with underlying liver disease, with enzyme inducers, and after any halogenated anesthetic (e.g., sevoflurane, isoflurane) or methoxyflurane exposure in the last 3 months. That exposure may increase the risk of liver injury.
- Obesity / Dosing Weight: the dose is fixed, not weight-based. Obesity increases CYP2E1 activity and brings earlier, higher fluoride peaks. Use the lowest effective dose.
- Malignant Hyperthermia Susceptibility: contraindicated in patients with known or genetic susceptibility, or a family history of severe reactions to inhaled anesthetics.
Field & Transport Considerations
- Scope: United States: no EMS, hospital or transport service can offer it outside an FDA-authorized clinical investigation. Where it is licensed, paramedics, nurses and other staff trained in its use give it. Rules vary by country, state and agency protocol.
- Storage & Stability: UK label: no special storage conditions, but keep it in a locked cabinet. New Zealand: below 30 °C (86 °F). Canada: 5–30 °C (41–86 °F). Shelf life 36 months.
- Carried Concentration: one strength only, a 3 mL bottle of 99.9% liquid. The error to prevent is exceeding the cumulative dose, not a concentration mix-up.
- Cabin Environment: load the inhaler in a well-ventilated area, and always fit the AC chamber in an ambulance or aircraft cabin. Crews who are regularly exposed have reported dizziness, headache and nausea.
- Handoff Essentials: hand off the time of first breath, number of bottles (mL), pain scores before and after, level of consciousness and other analgesics given. Flag methoxyflurane exposure to the surgical team (avoid sevoflurane), so the daily and weekly maximums keep being counted.
Clinical Pearls
Not an option in the US: You will see methoxyflurane in Australian, UK and Canadian protocols and literature. It has no FDA approval. US crews should plan non-IV analgesia around the agents they actually carry, such as intranasal fentanyl or ketamine.
Safety is in the patient's hand: Self-administration limits the dose. A patient who becomes drowsy stops inhaling. Coach intermittent breaths, and take the inhaler away at the first sign of sedation.
Methoxyflurane vs nitrous oxide:
- Nitrous oxide accumulates in gas-filled spaces, so it needs caution in chest injury (pneumothorax). Methoxyflurane labels carry no such restriction.
- Nitrous oxide needs bulky cylinders. Methoxyflurane is a pocket-sized, disposable inhaler.
- An indirect comparison found no significant difference in pain reduction.
Going to the OR: Anesthesia needs to know the patient had methoxyflurane. Sevoflurane pushes serum fluoride even higher, so avoid it afterward.
Exam discriminator: Methoxyflurane is the classic cause of fluoride-induced, dose-related high-output renal failure. That is what ended its anesthetic use (40–60 mL doses). One 3 mL analgesic dose keeps serum fluoride below 10 µmol/L, well under the levels linked to nephrotoxicity in anesthetic use: above about 40 µmol/L in the UK label, and 50–80 µmol/L for subclinical toxicity in the Canadian monograph.
Make one bottle last: Breathe it in continuously and one 3 mL bottle gives relief for up to about 25–30 minutes. Intermittent breaths stretch that to about an hour (Canada). When needed, covering the dilutor hole gives a stronger effect.
Pharmacology
Mechanism of Action
- A halogenated (fluorinated) volatile ether anesthetic. It gives analgesia at low, subanesthetic inhaled concentrations. The analgesic mechanism is not fully established.
- Unusual among halogenated agents, it is analgesic at subanesthetic doses. Effects on substance P and beta-endorphin have been proposed.
- At analgesic doses, the pivotal ED trial found no clinically relevant effect on BP, HR or respiration. Some fall in BP with bradycardia can still occur, especially in older adults. Respiratory depression and hypoxia have been reported after marketing. Drowsiness and euphoria are class effects.
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| INH (Penthrox inhaler) | After 6–10 breaths (median about 5 min) | Arterial level about 15 min | 25–30 min continuous; about 1 hr intermittent |
- Half-life: methoxyflurane about 3 hr (venous median, wide range); inorganic fluoride metabolite about 33 hr.
- Distribution: very lipophilic, with an oil/gas partition coefficient of 825 and a blood/gas value of 10–14. Fat acts as a reservoir and releases drug slowly over days.
- Metabolism: hepatic dechlorination and O-demethylation by CYP2E1, CYP2B6 and CYP2A6 to free fluoride, oxalic acid, difluoromethoxyacetic acid and dichloroacetic acid. Free fluoride and oxalic acid are the main nephrotoxic metabolites, and they cause nephrotoxicity at levels above those a single analgesic dose produces. The New Zealand data sheet also links clinical-dose nephrotoxicity to dichloroacetic acid combined with fluoride.
- Elimination: about 60% of uptake is excreted in urine as fluoride, organic fluorine and oxalic acid. The rest is exhaled unchanged or as CO₂ (UK and Canadian labels). The New Zealand data sheet instead gives about 30% urinary and 20% exhaled.
Names & Classification
- Generic Name
- Methoxyflurane
- Brand Names
- No US brand. International: Penthrox ("green whistle"). Penthrane: former US anesthetic product, withdrawn (FDA approval withdrawn 2001)
- Pharmacologic Class
- Halogenated (fluorinated) volatile ether
- Therapeutic Class
- Inhaled analgesic (subanesthetic dose); formerly a general anesthetic
- Controlled Substance
- Not controlled (not DEA-scheduled); prescription-only where licensed
- ISMP High-Alert
- No: not individually listed; ISMP lists inhaled general anesthetic agents as a class, but methoxyflurane is used only at analgesic doses and is not marketed in the US
- Look-Alike / Sound-Alike
- None commonly reported
References
- Medical Developments UK Ltd / Galen Ltd. (2026). PENTHROX 99.9%, 3 ml inhalation vapour, liquid: Summary of Product Characteristics (revised 15 June 2026). electronic medicines compendium (emc). https://www.medicines.org.uk/emc/product/1939/smpc
- Knight Therapeutics Inc. (2026). PENTHROX (methoxyflurane volatile liquid for inhalation): Product monograph (revised 18 August 2026). Health Canada Drug Product Database. https://pdf.hres.ca/dpd_pm/00085834.PDF
- Douglas Pharmaceuticals Ltd. (2023). PENTHROX volatile liquid for inhalation: New Zealand data sheet (revised 7 November 2023). Medsafe. https://medsafe.govt.nz/profs/Datasheet/p/penthroxinh.pdf
- U.S. Food and Drug Administration. (2005). Determination that Penthrane (methoxyflurane) inhalation liquid, 99.9 percent, was withdrawn from sale for reasons of safety or effectiveness (regulatory notice). Federal Register, 70(171), 53019. https://www.govinfo.gov/content/pkg/FR-2005-09-06/html/05-17559.htm
- Johnston, L., Poelman, S., Barankin, B., Yadav, G., Rao, J., & Metelitsa, A. (2024). Inhaled analgesia in dermatologic settings: A comprehensive overview of methoxyflurane. Skin Therapy Letter, 29(5). https://www.skintherapyletter.com/dermatology/inhaled-analgesia-methoxyflurane/
- Porter, K. M., Dayan, A. D., Dickerson, S., & Middleton, P. M. (2018). The role of inhaled methoxyflurane in acute pain management. Open Access Emergency Medicine, 10, 149–164. https://doi.org/10.2147/OAEM.S181222
- Borobia, A. M., Collado, S. G., Cardona, C. C., Pueyo, R. C., Alonso, C. F., Torres, I. P., et al. (2020). Inhaled methoxyflurane provides greater analgesia and faster onset of action versus standard analgesia in patients with trauma pain: InMEDIATE, a randomized controlled trial in emergency departments. Annals of Emergency Medicine, 75(3), 315–328. https://doi.org/10.1016/j.annemergmed.2019.07.028
- Coffey, F., Wright, J., Hartshorn, S., Hunt, P., Locker, T., Mirza, K., et al. (2014). STOP!: A randomised, double-blind, placebo-controlled study of the efficacy and safety of methoxyflurane for the treatment of acute pain (landmark trial). Emergency Medicine Journal, 31(8), 613–618. https://doi.org/10.1136/emermed-2013-202909
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.