

Bedside Snapshot
- Use It For
- Hypoxemia below the target range; cardiac arrest and post-ROSC; shock and major trauma; carbon monoxide poisoning; preoxygenation; cluster headache
- Adult Dose
- Most acute illness: titrate to SpO₂ 94–98%
- Hypercapnia risk (COPD): SpO₂ 88–92% by 24–28% Venturi
- Arrest: 100% by bag-mask or advanced airway
- Shock, CO: nonrebreather 15 L/min, then titrate to 94–98% (not in CO)
- Pediatric Dose
- Newborn: start 21% (≥35 wk), 21–30% (32–34 wk), 30–100% (<32 wk), titrate to preductal SpO₂. Child post-ROSC: SpO₂ 94–99%. Bronchiolitis: 90–97%
- Onset / Duration
- INH: SpO₂ rises within seconds to minutes; recheck 5 min after each change. Effect fades within minutes of stopping
- Do Not Give / Hold If
- No absolute contraindication when hypoxemic. Lower if SpO₂ >98% (>92% with hypercapnia risk); withhold in normoxemic ACS or stroke (outside a thrombectomy-center protocol); smoking or open flame nearby
- Watch For
- Rising PaCO₂ and drowsiness in COPD (blood gas, EtCO₂); hyperoxemia (SpO₂ above target); normal SpO₂ masking CO poisoning or hypoventilation; fire
- Reversal / Rescue
- No antidote: lower FiO₂ to the target. CO₂ narcosis: step down to 88–92% (never off) and NIV if pH <7.35 with PaCO₂ >45 mmHg persists after initial treatment. Fire: stop the flow
- Must Remember
- Oxygen is a drug with a target range: prescribe and titrate to an SpO₂ range, not to 100%. A normal SpO₂ does not exclude CO poisoning, anemia or hypoventilation.
Indications
Emergency & Prehospital
- Hypoxemia: SpO₂ below the patient's target range. Treat the cause as well, whatever it is
- Cardiac arrest and post-ROSC care: maximal oxygen during CPR, then titrated once SpO₂ is reliable
- Shock, sepsis, major trauma, anaphylaxis, drowning, status epilepticus: high-concentration oxygen until reliable oximetry is available
- Carbon monoxide poisoning and smoke inhalation: maximal oxygen regardless of SpO₂; suspect cyanide co-poisoning in fire victims (see hydroxocobalamin)
- Gas embolism and decompression illness: 100% oxygen while arranging hyperbaric therapy
- Newborn resuscitation: blended oxygen titrated to preductal SpO₂ targets
ED / ICU / Transport
- Preoxygenation: before rapid sequence intubation and procedural sedation
- Acute hypoxemic respiratory failure: conventional devices, or high-flow nasal cannula (HFNC) to avoid escalation to noninvasive ventilation
- After extubation: HFNC to reduce reintubation
- Cluster headache: first-line abortive therapy with high-flow 100% oxygen
Other Uses
- Pneumothorax under observation: High-concentration oxygen speeds up reabsorption of pleural air (BTS guidance)
- Hyperbaric oxygen: selected carbon monoxide poisoning, gas embolism and decompression illness (specialist)
- Home and long-term oxygen: Outpatient criteria and assessment are separate. This page covers acute use only
Not indicated: Breathlessness without hypoxemia. Normoxemic acute coronary syndrome (ACS). Normoxemic stroke outside a thrombectomy-center protocol. Anxiety-related hyperventilation. Oxygen does not correct anemia or low cardiac output.
Dosing & Administration
Use the SpO₂ target in the tables below, and titrate to it.
Available Forms
- Compressed gas: Oxygen, Compressed USP cylinders: D and E are the portable sizes EMS carries. M and larger are for vehicles and facilities. US medical oxygen cylinders are green. Colors differ elsewhere.
- Liquid oxygen: Bulk tanks feed hospital piped systems.
- Labeling: Rx only for medical use. The label allows emergency use by trained personnel for oxygen deficiency and resuscitation.
Delivery Devices
| Device | Flow | Approx. FiO₂ | Notes |
|---|---|---|---|
| Nasal cannula | 1–6 L/min | ~24–50%; varies with breathing pattern | Most acutely ill patients; 1–2 L/min for hypercapnia risk. Humidification not needed for low-flow oxygen; consider it for high flows over 24 h, nasal dryness or sputum retention. |
| Simple face mask | 5–10 L/min | 40–60% | Never below 5 L/min (CO₂ rebreathing). Not first choice with hypercapnia risk (use a Venturi or 1–2 L/min cannula); if SpO₂ stays below 88% on a 28% Venturi, 5 L/min by simple mask is acceptable, still targeting 88–92%. |
| Nonrebreather (reservoir) mask | 15 L/min | 60–90%, seal-dependent | Critical illness, CO poisoning, SpO₂ <85%. Fill the reservoir before applying. |
| Venturi mask | Minimum flow printed on the adaptor | Fixed: 24, 28, 31, 35, 40 or 60% | Controlled oxygen in hypercapnia risk. Raise flow up to 50% if RR >30; FiO₂ does not change. |
| High-flow nasal cannula | Adults up to 60 L/min; children by weight per protocol | 21–100%, set on the blender | Heated and humidified; about 7 cm H₂O airway pressure at 50 L/min (volunteers). Moderate to severe bronchiolitis. |
| Blow-by / free-flow | Tubing or mask held near the face | Low and unpredictable | Brief use in a child who will not tolerate a mask. Never for apnea or inadequate breathing: ventilate. |
| Bag-valve mask with reservoir | 15 L/min | High with a good seal | Apnea or inadequate breathing; a PEEP valve helps preoxygenation. |
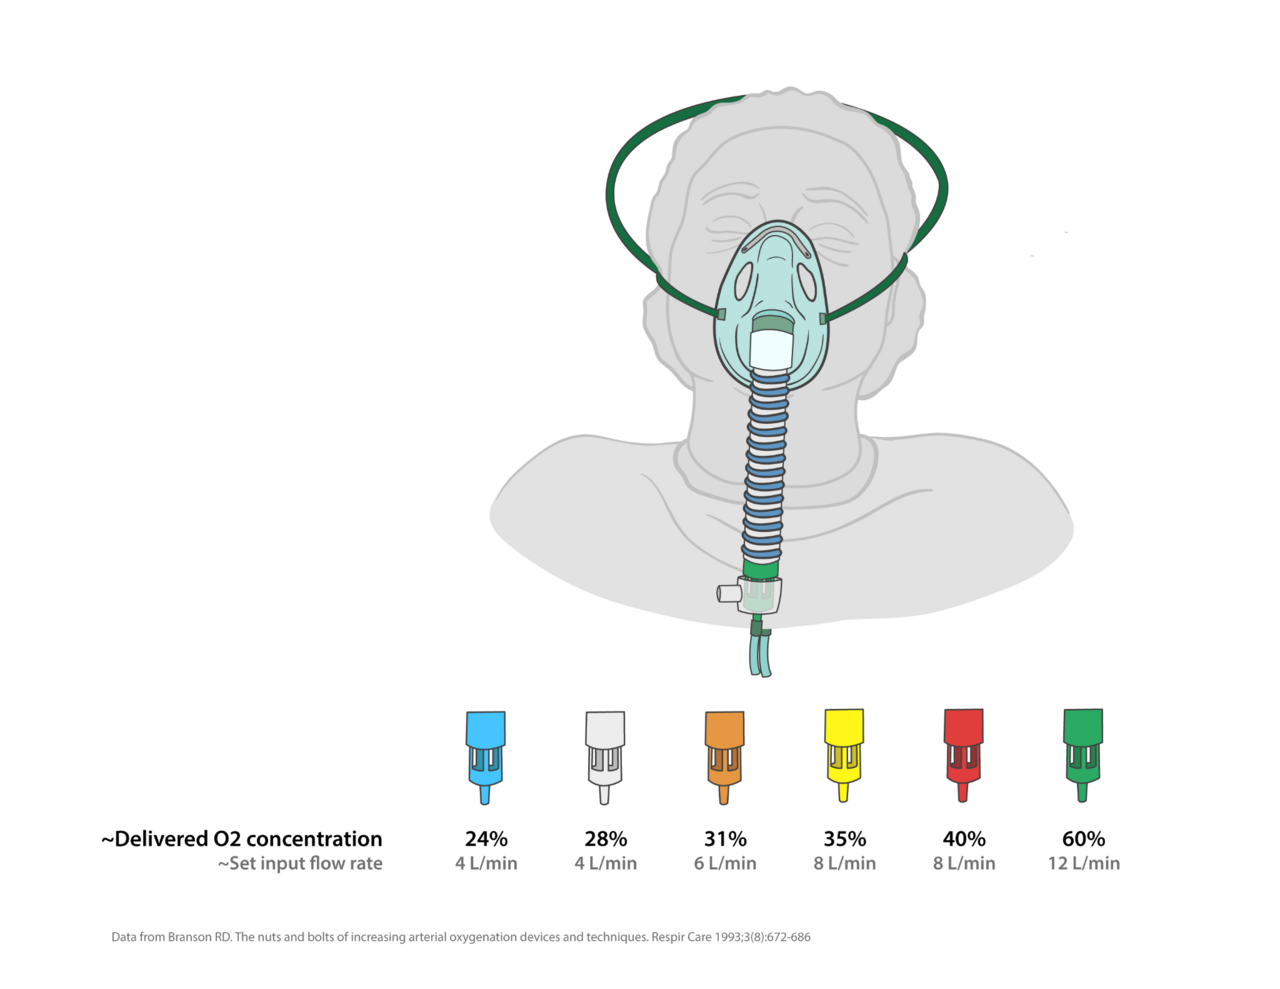
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| Hypoxemia: most acute illness | Titrate to SpO₂ 94–98%: nasal cannula 1–6 L/min or simple mask 5–10 L/min INH | No fixed max: lowest flow that holds the target; recheck SpO₂ 5 min after each change | Nonrebreather 15 L/min if SpO₂ <85%; needing one calls for urgent senior review. |
| Hypercapnia risk (COPD, obesity hypoventilation, neuromuscular or chest-wall disease, cystic fibrosis) | Titrate to SpO₂ 88–92%: 24% Venturi at 2–3 L/min, 28% Venturi at 4 L/min, or nasal cannula 1–2 L/min | Lower the flow if SpO₂ >92%; blood gas 30–60 min after any increase | Move to 94–98% if PaCO₂ is normal and there is no prior NIV or intubation. |
| Cardiac arrest | Maximal feasible FiO₂ (100% with a bag-mask or advanced airway) | Continue until ROSC | 2025 AHA Part 9, COR 2b (C-LD): when supplemental oxygen is available, maximal feasible inspired oxygen during CPR may be reasonable. |
| Post-ROSC | 100% until SpO₂ or PaO₂ is reliable, then titrate to SpO₂ 90–98% (PaO₂ 60–105 mmHg) | Avoid both hypoxemia and hyperoxemia | After ROSC, 100% oxygen is recommended until SpO₂ or PaO₂ can be reliably measured (2025 AHA Part 11, COR 1); then titrate to SpO₂ 90–98% (PaO₂ 60–105 mmHg) to avoid both hypoxemia and hyperoxemia (COR 2a). Oximetry may miss hypoxemia in darker skin (COR 2b); confirm with a blood gas. |
| Shock, sepsis, major trauma, anaphylaxis | Nonrebreather 15 L/min INH | Until reliable oximetry, then titrate to SpO₂ 94–98% | Treat the cause as well. |
| Carbon monoxide poisoning | 100% oxygen: nonrebreather 15 L/min, or bag-mask or ETT with 100% | Do not titrate to SpO₂: continue maximal FiO₂ pending carboxyhemoglobin (COHb) and toxicology advice | SpO₂ and PaO₂ read normal. Discuss hyperbaric oxygen for severe cases or pregnancy. |
| Gas embolism, decompression illness | 100% oxygen: nonrebreather 15 L/min INH | Continue until hyperbaric assessment | Hyperbaric oxygen for life-threatening cases. |
| ACS | Only if SpO₂ <90%: titrate to SpO₂ ≥90% | Not for SpO₂ ≥90% (no benefit) | — |
| Acute ischemic stroke | Only if hypoxic: keep SpO₂ >94% | Not for nonhypoxic patients ineligible for thrombectomy (no benefit) | Normobaric hyperoxia before thrombectomy in selected large-vessel occlusion may be reasonable: stroke-center protocol only. |
| Paraquat poisoning, bleomycin lung injury | Only if SpO₂ <85%: target 85–88% | Reduce or stop if SpO₂ >88% | These patients may be harmed by supplemental oxygen. |
| Cluster headache | 100% oxygen ≥12 L/min by nonrebreather INH, patient seated, for 15 min | Per attack; no fixed max | — |
| Preoxygenation | Maximal FiO₂ before induction (nonrebreather, bag-mask with PEEP valve, NIV or HFNC) for at least 3 min, or 8 vital-capacity breaths | Titrate down to the target after the airway is secured | Consider apneic oxygenation by nasal cannula during laryngoscopy. See RSI and intubation. |
Pediatric Dosing
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| Hypoxemia: acutely ill child | Not weight-based: titrate to the target SpO₂ set for the child's condition, using a device sized to the child | No fixed max: lowest FiO₂ that holds the target | No evidence-based target outside bronchiolitis; AARC 2021 calls setting one on admission best practice. |
| Bronchiolitis | Titrate to SpO₂ 90–97% | No oxygen needed if SpO₂ stays ≥90% | HFNC beats low-flow oxygen in moderate to severe disease. The 90–97% target is the AARC 2021 recommendation for bronchiolitis. |
| Asthma | Give if SpO₂ <92%: target 92–95% (6 yr and older), ≥92% (5 yr and younger) | Upper limit 95% from age 6 | GINA 2026: give oxygen only if SpO₂ below 92%; target 92–95% (5 years and younger: at least 92%). |
| Cardiac arrest | 100% oxygen by bag-mask or advanced airway | Until ROSC | 2025 AHA Part 8 synopsis: 100% oxygen is the current recommendation during cardiac arrest. See pediatric cardiac arrest. |
| Post-ROSC (infants and children) | Wean to SpO₂ 94–99%, appropriate to the underlying condition | Avoid hypoxemia and hyperoxemia | 2025 AHA Part 8, COR 2b. Adjust for the underlying condition (e.g. cyanotic heart disease). |
| Carbon monoxide poisoning | 100% oxygen by nonrebreather or bag-mask | Maximal FiO₂ pending COHb and toxicology advice | SpO₂ is unreliable. |
| Newborn: ventilation at birth, ≥35 weeks | Start with 21% oxygen (air) (2025 AHA Part 5, COR 2b) | Titrate to preductal SpO₂ targets (table below) | Pulse oximeter on the right hand or wrist as soon as possible (2025 AHA Part 5, COR 1). |
| Newborn: 32 to 34+6/7 weeks | Start with 21–30% oxygen | Titrate to preductal targets | 2025 AHA Part 5, COR 2b. |
| Newborn: <32 weeks | Start with 30–100% oxygen | Titrate to preductal targets | Failing to reach SpO₂ 80% by 5 min is associated with death in very preterm infants regardless of initial oxygen (2025 AHA Part 5 synopsis; starting range COR 2b). |
| Newborn: chest compressions | 100% oxygen | Titrate to targets once compressions stop | 2025 AHA Part 5, COR 2b (C-EO): may be reasonable during chest compressions. |
| Time After Birth | Preductal SpO₂ Target |
|---|---|
| 2 min | 65–70% |
| 3 min | 70–75% |
| 4 min | 75–80% |
| 5 min | 80–85% |
| 10 min | 85–95% |
For pediatric devices and normal ranges, go to pediatric airway and pediatric vital signs.
Cylinder Duration
Cylinder duration
Minutes = (gauge psi − 200 psi reserve) × cylinder factor ÷ flow (L/min)
- Classic factors: D 0.16 (older ~350 L D cylinder), E 0.28, M 1.56 L/psi. Newer cylinders differ. Their factor = rated liters ÷ rated full pressure (psi), both printed on the cylinder. A 415 L aluminum D rated at 2,015 psi comes out to about 0.21.
- Worked example: E cylinder at 2,000 psi on a nonrebreather at 15 L/min: (2,000 − 200) × 0.28 ÷ 15 ≈ 33 min. In the same case, a classic D lasts about 19 min and a 415 L aluminum D about 25 min.
- Plan the trip: Oxygen needed = total flow × planned minutes × 1.5 (safety margin). Carry at least that many liters.
- HFNC and ventilators: Oxygen use depends on set flow and FiO₂. Flow alone doesn't tell you. Use the device's oxygen-consumption figure.

Preparation & Administration
- Prescribe a target: Write the SpO₂ range (94–98% or 88–92%) with the device; record device, flow and SpO₂ together.
- Titrate: Increase if SpO₂ is below the range, decrease if above. If SpO₂ does not rise after 5–10 min of more oxygen, check the device, oximeter and patient, and escalate.
- Cylinder setup: Confirm the label reads Oxygen USP, open the valve slowly, keep fittings free of oil and grease, close after use.
- Nebulizers in COPD: Drive with air and give oxygen separately by nasal cannula: oxygen-driven nebulizers can raise PaCO₂. With no air compressor (most ambulances), an oxygen-driven nebulizer may be used: limit it to about 6 min, then return to controlled oxygen at 88–92%.
- Nebulizers in asthma: Drive with oxygen at more than 6 L/min, then return to the usual oxygen device.
- Weaning: Step down to 1–2 L/min nasal cannula or a 24% Venturi before stopping; watch SpO₂ on air for 5 min after stopping and, if still in range, recheck at 1 hour. If SpO₂ falls below target, restart the lowest flow that held it in range and try stopping again later.
Contraindications & Precautions
Contraindications
- Nothing is absolute when the patient is hypoxemic.
- Paraquat poisoning or prior bleomycin lung injury (relative): give only if SpO₂ <85%, target 85–88%.
- Normoxemic ACS or stroke (relative): there is no benefit. Withhold it (stroke: unless a thrombectomy-center protocol calls for it).
Precautions
- Hypercapnia risk: COPD, obesity hypoventilation, neuromuscular or chest-wall disease and cystic fibrosis: uncontrolled oxygen can push them into CO₂ narcosis and acidosis.
- Hidden hypoventilation: Oxygen can keep SpO₂ looking normal while CO₂ climbs after opioids or sedation. Capnography catches it.
- Pulse oximetry limits: Falsely normal or high in CO poisoning, because carboxyhemoglobin reads as oxyhemoglobin. May overestimate in darker skin. Unreliable with poor perfusion. Can read normal despite anemia.
- Methemoglobinemia: Watch for SpO₂ stuck near 85% that won't climb on more oxygen. The blood-gas saturation won't match it. Confirm with co-oximetry.
- Preterm newborns: Too much oxygen in a preterm infant is linked to retinopathy of prematurity and lung injury. Use a blender and titrate.
- Ductal-dependent or single-ventricle heart disease: Too much FiO₂ can hurt systemic perfusion here. Follow the cardiology target.
- FDA label: Prolonged high concentration without arterial oxygen monitoring may be harmful.
Hold / Reassess If
- SpO₂ above the target range (>98%, or >92% with hypercapnia risk): lower the flow.
- New drowsiness, headache or flap in a patient at risk of hypercapnia: blood gas now; do not stop oxygen abruptly.
- SpO₂ falls below target or needs a nonrebreather: urgent clinical review and escalation (HFNC, NIV, intubation).
Fire: Oxygen-enriched air turns ordinary materials into fuel. They light easily and burn hard. No smoking, flame or sparks near oxygen. Oil and grease never belong on cylinders or fittings, and combustibles stay well away. Electrocautery near oxygen can start a surgical fire. For defibrillation, pull free-flowing oxygen (mask or cannula) off the chest.
Adverse Effects & Toxicity
Common
- Nasal dryness, soreness and nosebleeds, especially at higher cannula flows
- Mask discomfort, claustrophobia, interference with eating and speaking
- Mild absorption atelectasis at high FiO₂
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
| Hypercapnic respiratory failure | Drowsiness, headache, flap; PaCO₂ >45 mmHg with pH <7.35 | Step oxygen down to SpO₂ 88–92%, never off (rebound hypoxemia); NIV if the acidosis persists after initial treatment |
| Hyperoxemia | Sustained SpO₂ >98% or high PaO₂ on oxygen | Titrate down; associated with higher mortality in acutely ill adults (no proven benefit from exceeding the target) |
| Absorption atelectasis and oxygen toxicity | Worsening shunt and infiltrates with prolonged high FiO₂ | Lowest FiO₂ that holds the target; PEEP and lung-protective ventilation |
| Retinopathy of prematurity | Preterm infants with prolonged high oxygen exposure | Blended oxygen and saturation targets; screening per neonatal protocol |
| Fire and burns | Flash fire at the face, cannula or mask | Stop the oxygen flow, remove the device, cool burns, assess the airway |
Overdose & Toxicity Management
- Excess oxygen: No antidote exists. Bring FiO₂ down to the target range, then reassess with a blood gas.
- Hypercapnic narcosis: Lower to SpO₂ 88–92%, support ventilation (NIV or intubation), recheck PaCO₂ in 30–60 min.
- Hyperbaric therapy: Central nervous system oxygen toxicity (seizures) is a chamber complication. The hyperbaric team manages it.
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: SpO₂ with device and flow | Continuous; record 5 min after any change | Outside the prescribed range: adjust the flow; falling despite more oxygen: escalate |
| Clinical: RR, work of breathing, mental status | With every SpO₂ check | Tachypnea, fatigue or drowsiness: blood gas and ventilatory support |
| Clinical: EtCO₂ | Sedation, opioids, intubated and transport patients | Rising EtCO₂ with normal SpO₂: hypoventilation hidden by oxygen |
| Laboratory: blood gas (ABG) | Arrival in hypercapnia risk; 30–60 min after any increase | PaCO₂ >45 mmHg with pH <7.35: step oxygen down to 88–92%; NIV if it persists after initial treatment |
| Laboratory: PaO₂ after ROSC | Once SpO₂ is reliable, then titrate to the target below | Keep PaO₂ 60–105 mmHg (SpO₂ 90–98%; 2025 AHA Part 11, COR 2a) |
| Laboratory: COHb and methemoglobin (co-oximetry) | Suspected CO, smoke or oxidant exposure | Elevated COHb: maximal oxygen, toxicology or hyperbaric consult |
| Laboratory: hemoglobin, lactate | Shock or unexplained hypoxia | Low hemoglobin or high lactate: oxygen alone will not fix delivery |
| Supply: cylinder pressure | Before departure and regularly during transport | Below the planned reserve: change cylinders before it runs out |
Interactions & Compatibility
Oxygen has no pharmacokinetic drug interactions. The ones that matter are physiologic or equipment-related.
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| Opioids, benzodiazepines, sedatives (naloxone reverses opioids) | Supplemental oxygen keeps SpO₂ normal while hypoventilation and CO₂ retention develop | Monitor RR and EtCO₂; treat the hypoventilation, not just the SpO₂ |
| Bleomycin lung injury, paraquat poisoning | Oxygen can worsen lung injury, even years after bleomycin lung injury | Give only if SpO₂ <85%; target 85–88% |
| Oxygen-driven nebulized bronchodilators (albuterol, ipratropium) in COPD | High FiO₂ during nebulization can raise PaCO₂ | Drive the nebulizer with air; oxygen by nasal cannula. No air compressor: oxygen-drive for about 6 min only, then back to 88–92% |
| Nitrites and other methemoglobin-forming drugs | Methemoglobinemia makes SpO₂ unreliable | Co-oximetry; methylene blue for life-threatening methemoglobinemia |
Equipment Compatibility
- Use regulators, flowmeters and tubing rated for oxygen service. Keep oil, grease and petroleum products off cylinders and fittings.
- MRI: only MRI-conditional cylinders and regulators. A ferromagnetic cylinder becomes a projectile.
- Not an IV drug, so there are no IV compatibility issues.
Special Populations
- Pediatrics: Outside bronchiolitis (90–97%) and asthma, no single target exists. Set the child's target on arrival. Doses sit in the Pediatric Dosing table.
- Neonates: Term infants start on air. Preterm infants start on 21–100% by gestational age. Titrate to preductal targets with a blender.
- Pregnancy: Hypoxemic or seriously ill women get standard oxygen. Target 94–98%, or 88–92% with hypercapnia risk. BTS notes that oxygen may harm the fetus when the mother is not hypoxemic. Past 20 weeks, with risk of cardiovascular compromise (trauma, bleeding), avoid aortocaval compression. Use full left lateral position, left lateral tilt or manual uterine displacement (manual left uterine displacement during CPR).
- Lactation: No effect on breastfeeding.
- Older Adults: Older adults run higher odds of hypercapnic lung disease and occult hypoxemia. The targets stay the same.
- Renal Impairment: No adjustment needed. Tachypnea may reflect metabolic acidosis, not hypoxemia.
- Hepatic Impairment: No specific adjustment established.
- Obesity / Dosing Weight: Not weight-based. Morbid obesity and obesity hypoventilation raise the hypercapnia risk, so target 88–92% until a blood gas comes back.
- Darker Skin Pigmentation: Pulse oximeters can read high and hide hypoxemia in darker skin. Check borderline readings with a blood gas.
- Sickle Cell Crisis: Aim for 94–98%, or the patient's usual saturation. If the oximetry is doubtful, check a blood gas.
Field & Transport Considerations
- Scope: Everyone from EMT up to critical-care transport gives oxygen. Blenders, HFNC and ventilator FiO₂ are typically Paramedic/RN/CCT skills. It varies by state and agency protocol.
- Storage & Stability: Secure cylinders upright or in brackets; keep away from heat and protect from sunlight above 52°C (125°F); close valves when not in use.
- Carried Supply: Work out cylinder duration before every transfer (Dosing & Administration). Carry 1.5 times the oxygen the trip needs. HFNC and ventilators use far more than a mask.
- Altitude / Environment: As cabin altitude rises, SpO₂ falls. Raise FiO₂ to hold the target, and watch the cylinder.
- Fire: Keep smoking and open flame away from oxygen, in the vehicle or at home. Cylinders can explode if heated in a fire.
- Handoff Essentials: Device and flow or FiO₂, SpO₂ target and trend, blood gas and COHb results, response to changes, time on high-flow oxygen.
Clinical Pearls
Normal SpO₂ in CO poisoning: Here's the catch: the oximeter reads carboxyhemoglobin as oxyhemoglobin, and PaO₂ looks normal too. Treat on history. Give maximal oxygen, then measure COHb by co-oximetry.
Oxygen hides hypoventilation: Sedated or post-opioid, on oxygen, the sat can sit near 100% while CO₂ rises. Stop trusting the oximeter alone. Track RR and EtCO₂ instead.
COPD and drowsy after oxygen: Step down to SpO₂ 88–92%, but never switch it off. Stopping cold brings on rebound hypoxemia. Get a blood gas. If the acidosis hangs on after first treatment, NIV.
Exam discriminator: fixed vs variable performance:
- Venturi: FiO₂ is fixed. Raising the flow does not change it.
- Nasal cannula and simple mask: FiO₂ moves with the breathing pattern.
- Nonrebreather: highest FiO₂ of the low-flow devices, 60–90% at 15 L/min.
- HFNC: set FiO₂ up to 100% with flow that meets inspiratory demand.
Conservative vs liberal oxygen: In 16,500 mechanically ventilated ICU adults, a conservative SpO₂ target of 90% (range 88–92%) did not significantly lower 90-day mortality versus usual oxygen therapy (35.4% vs 34.9%, UK-ROX, JAMA 2025). Avoid both hypoxemia and sustained hyperoxemia. Aim for the range, not 100%.
Cluster headache: First-line abortive therapy: 100% oxygen at 12 L/min or more by nonrebreather, seated, for 15 min, started early in the attack.
Pharmacology
Mechanism of Action
- Higher FiO₂ → higher alveolar and arterial PO₂ → higher hemoglobin saturation and arterial oxygen content (CaO₂ = 1.34 × Hb × SaO₂ + 0.003 × PaO₂).
- Delivery to tissue = cardiac output × CaO₂. Once hemoglobin is saturated, extra oxygen adds little content.
- Corrects hypoxic pulmonary vasoconstriction, so poorly ventilated units get perfused again. With the Haldane effect and reduced drive, this raises PaCO₂ in susceptible patients.
- Hyperoxia constricts coronary and cerebral vessels and drives oxidative stress. Nitrogen washout causes absorption atelectasis.
- Oxygen pushes carbon monoxide off hemoglobin. COHb half-life drops from about 5 hr on air to under 90 min on 100% oxygen, and to about 20–30 min with hyperbaric oxygen.
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| INH | Seconds | New steady state within minutes; record SpO₂ at 5 min | Only while inhaled; falls within minutes of stopping |
- Half-life: Not applicable. The effect tracks the inspired concentration.
- Distribution: Most oxygen rides bound to hemoglobin. A small fraction is dissolved in plasma.
- Metabolism: Consumed by mitochondrial oxidative phosphorylation.
- Elimination: Exhaled unchanged or as CO₂ and water.
Names & Classification
- Generic Name
- Oxygen (Oxygen USP; compressed or refrigerated liquid)
- Brand Names
- None: generic medical gas from many suppliers
- Pharmacologic Class
- Medical gas
- Therapeutic Class
- Treatment of hypoxemia; resuscitation; CO poisoning; cluster headache
- Controlled Substance
- Not controlled (Rx only, except emergency use by trained personnel)
- ISMP High-Alert
- No
- Look-Alike / Sound-Alike
- Gas mix-ups: other medical gases come in similar cylinders; read the label before connecting
References
- Airgas USA, LLC. (2026). Oxygen, compressed USP [label]. DailyMed, National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=7cb637af-228a-452e-ae7e-f627902be10a
- O'Driscoll, B. R., Howard, L. S., Earis, J., & Mak, V. (2017). BTS guideline for oxygen use in adults in healthcare and emergency settings (current BTS guideline). Thorax, 72(Suppl 1), ii1–ii90. https://doi.org/10.1136/thoraxjnl-2016-209729
- Napolitano, N., Berlinski, A., Walsh, B. K., Ginier, E., & Strickland, S. L. (2021). AARC clinical practice guideline: management of pediatric patients with oxygen in the acute care setting. Respiratory Care, 66(7), 1214–1223. https://doi.org/10.4187/respcare.09006
- Prabhakaran, S., Gonzalez, N. R., Zachrison, K. S., Adeoye, O., et al. (2026). 2026 guideline for the early management of patients with acute ischemic stroke: a guideline from the American Heart Association/American Stroke Association. Stroke, 57(8), e316–e436. https://doi.org/10.1161/STR.0000000000000513
- Hirsch, K. G., Amorim, E., Coppler, P. J., et al. (2025). Part 11: Post–cardiac arrest care: 2025 American Heart Association guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation, 152(16 Suppl 2), S673–S718. https://doi.org/10.1161/CIR.0000000000001375
- Lee, H. C., Strand, M. L., Finan, E., et al. (2025). Part 5: Neonatal resuscitation: 2025 American Heart Association and American Academy of Pediatrics guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation, 152(16 Suppl 2), S385–S423. https://doi.org/10.1161/CIR.0000000000001367
- Lasa, J. J., Dhillon, G. S., Duff, J. P., et al. (2025). Part 8: Pediatric advanced life support: 2025 American Heart Association and American Academy of Pediatrics guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation, 152(16 Suppl 2), S479–S537. https://doi.org/10.1161/CIR.0000000000001368
- Wigginton, J. G., Agarwal, S., Bartos, J. A., et al. (2025). Part 9: Adult advanced life support: 2025 American Heart Association guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation, 152(16 Suppl 2). https://doi.org/10.1161/CIR.0000000000001376
- Rao, S. V., O'Donoghue, M. L., Ruel, M., et al. (2025). 2025 ACC/AHA/ACEP/NAEMSP/SCAI guideline for the management of patients with acute coronary syndromes. Circulation, 151(13), e771–e862. https://doi.org/10.1161/CIR.0000000000001309
- Global Initiative for Asthma. (2026). Global strategy for asthma management and prevention, 2026. https://ginasthma.org/2026-gina-strategy-report/
- Martin, D. S., Gould, D. W., Shahid, T., et al. (2025). Conservative oxygen therapy in mechanically ventilated critically ill adult patients (UK-ROX). JAMA, 334(5), 398–408. https://doi.org/10.1001/jama.2025.9663
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.