

Bedside Snapshot
- Use It For
- Reversal of rocuronium or vecuronium block at labeled depths (T2 back, or 1–2 PTC); immediate reversal after an RSI dose of rocuronium; reversal for a neurologic exam after ED intubation (off-label)
- Adult Dose
- TOF count ≥2: 2 mg/kg IV bolus
- Deep block (1–2 PTC, TOF count 0): 4 mg/kg IV
- About 3 min after rocuronium 1.2 mg/kg: 16 mg/kg IV (max)
- Pediatric Dose
- Birth to 17 yr: 2 mg/kg IV (TOF count ≥2) or 4 mg/kg IV (1–2 PTC), actual body weight, no mg cap; under 2 yr is in the Bridion label only. 16 mg/kg immediate reversal: not studied in children
- Onset / Duration
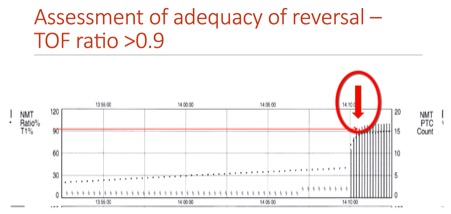
- IV: median TOF ratio ≥0.9 in about 2 min (2 mg/kg) to 3 min (4 mg/kg) / sustained, recurrence <1% at labeled doses; half-life about 2 hr
- Do Not Give / Hold If
- Known sugammadex hypersensitivity; succinylcholine, cisatracurium or atracurium block (no effect); CrCl <30 mL/min or dialysis (not recommended); no twitch check for a 2 or 4 mg/kg dose (16 mg/kg rescue dose is timed)
- Watch For
- Marked bradycardia or asystole within minutes (ECG); anaphylaxis: urticaria, hypotension, bronchospasm; recurrent weakness (TOF ratio, SpO₂, EtCO₂); bucking if sedation is light
- Reversal / Rescue
- No antidote. Bradycardia: atropine 1 mg IV (child 0.02 mg/kg, min 0.1, max 0.5 mg). Anaphylaxis: IV epinephrine if monitored with access, else IM 0.01 mg/kg (max 0.5 mg). Re-paralysis: nonsteroidal blocker or wait
- Must Remember
- Dose to the measured block on actual body weight, never below 2 mg/kg: underdosing invites recurrence. It reverses only rocuronium and vecuronium, and it does not open an obstructed airway
Indications
ED / ICU / Transport
- Immediate reversal after an RSI dose of rocuronium: the block has to end about 3 min after rocuronium 1.2 mg/kg. Picture a failed intubation. FDA-labeled in adults. Run it alongside the difficult-airway algorithm, never instead of it (see RSI)
- Reversal for a neurologic exam after ED intubation with rocuronium: traumatic brain injury is the example, once sedation is planned. Off-label, on retrospective data. Soon after RSI the block can be profound (PTC 0). Wait for PTC 1 or more, then give 4 mg/kg. Lower doses risk recurrence.
- Reversal in the ICU: the same twitch-guided doses. Off-label, since the label has not studied it.
Other Uses
- Routine reversal of rocuronium or vecuronium block after surgery: this is the FDA-labeled use, in adults and children. The 2023 American Society of Anesthesiologists (ASA) guideline prefers it over neostigmine outside minimal block. The 2023 European Society of Anaesthesiology and Intensive Care (ESAIC) guideline recommends it for deep, moderate and shallow block.
- Minimal-depth block (train-of-four (TOF) ratio 0.4 to <0.9): both sugammadex and neostigmine are options. ASA 2023 limits neostigmine to this range and sends deeper block to sugammadex. ESAIC 2023 advises neostigmine only once spontaneous TOF ratio exceeds 0.2. Monitor quantitatively until TOF ratio >0.9.
Dosing & Administration
Available Forms
- Single-dose vials: 100 mg/mL in 2 mL (200 mg) and 5 mL (500 mg); preservative-free, discard any unused portion
- Products: Bridion, plus multiple generics since 2026 at the same concentration. Some come only as 200 mg/2 mL vials or prefilled syringes.
- Pediatric labeling: the Bridion label covers children from birth, with the same 2 and 4 mg/kg doses. Generic labels start at 2 yr, so generic use under 2 yr is off-label.
- Pediatric dilution: 10 mg/mL (one 200 mg/2 mL vial in 18 mL NS); use immediately
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| TOF count 2 or more (moderate to minimal block) | 2 mg/kg IV bolus over 10 seconds (actual body weight) | Single dose; below 2 mg/kg not recommended (recurrence risk) | Labeled at T2 reappearance. |
| Deep block: 1–2 post-tetanic counts (PTC), TOF count 0 (ASA 2023 also: TOF count 1) | 4 mg/kg IV bolus over 10 seconds (actual body weight) | Single dose | Median ratio ≥0.9: 2.7 min (rocuronium), 3.3 min (vecuronium). |
| Immediate reversal: about 3 min after a single rocuronium 1.2 mg/kg dose | 16 mg/kg IV bolus (actual body weight) | Max 16 mg/kg (maximum recommended human dose) | Rocuronium only; not studied after vecuronium or in children. |
| Profound block later in a case: PTC 0 | No labeled dose | Not applicable: keep sedated and ventilated until PTC ≥1, then 4 mg/kg | The 16 mg/kg dose is labeled only for the 3-minute post-rocuronium scenario. |
Pediatric Dosing
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| T2 has reappeared (TOF count ≥2), birth to 17 yr | 2 mg/kg IV bolus | Single dose; no fixed mg cap | Bridion label from birth; no age adjustment. Median recovery 1.4 min under 2 yr. Weight-based dosing |
| Deep block (1–2 PTC), birth to 17 yr | 4 mg/kg IV bolus | Single dose; no fixed mg cap | Median recovery 1.1 min under 2 yr. |
| Immediate reversal after rocuronium 1.2 mg/kg | Not studied in children | — | Not labeled for children; specialist decision only. |
Preparation & Administration
- Grade the block first: nerve stimulator, ideally quantitative TOF at the adductor pollicis, to choose 2 or 4 mg/kg; labeled doses do not apply to eye-muscle monitoring.
- Push and flush: single IV bolus over 10 seconds into an existing line; flush between drugs.
- Inspect: do not use if particles are present.
Contraindications & Precautions
Contraindications
- Known hypersensitivity to sugammadex or any component. Reactions have happened on the first exposure.
Precautions
- Wrong blocker: it does nothing to succinylcholine, cisatracurium or atracurium. Not for pancuronium or other steroidal blockers.
- CrCl <30 mL/min or dialysis: not recommended.
- Coagulopathy or anticoagulation: expect a transient rise in aPTT and PT/INR. Monitor coagulation tests.
- Pulmonary history: bronchospasm has been reported.
Hold / Reassess If
- No twitch assessment yet, and a 2 or 4 mg/kg dose is next? Get a nerve stimulator first. The exception is 16 mg/kg about 3 min after rocuronium 1.2 mg/kg, which you choose by timing.
- TOF ratio already ≥0.9 on quantitative monitoring: no reversal needed, per ASA 2023
- Sedation inadequate in a patient who stays intubated: sedate first
- CrCl <30 mL/min: plan with anesthesia (ventilate until spontaneous recovery)
Adverse Effects & Toxicity
Common
- Nausea and vomiting: most common (nausea 23–26%, vomiting 11–15%), close to placebo after surgery; procedural pain and headache
- Hypotension: 4–5% at 2–4 mg/kg, 13% at 16 mg/kg (placebo 4%)
- Cough and airway complications of anesthesia: 8–9% at 16 mg/kg
- Hypersensitivity symptoms (nausea, pruritus, urticaria): dose-related
- Bradycardia: adults 1% at 2–4 mg/kg, 5% at 16 mg/kg; children 2 to <17 yr 10% at 2 mg/kg and 7% at 4 mg/kg; under 2 yr cardiac disorders (all types) 6.8% at 2 mg/kg (label section 6.1). Reviews report 1–7% depending on the definition. Most of it is inconsequential
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
| Anaphylaxis (about 1.6 per 10,000 in ASA 2023 pooled data; label volunteer cases all followed 16 mg/kg; post-marketing reports include lower doses and first exposure) | Within minutes: urticaria, flushing, hypotension, bronchospasm, tongue or pharyngeal swelling; ECG ST changes reported | Monitored with IV access: titrated IV epinephrine, then infusion if hypotension persists; crystalloid; stop other suspected triggers; airway support (ventilation may be prolonged); CPR and ACLS/PALS if pulseless. No IV access: IM epinephrine 0.01 mg/kg (max 0.5 mg) |
| Marked bradycardia, AV block, asystole | Falling heart rate within minutes of the dose | Atropine 1 mg IV (pediatric 0.02 mg/kg, min 0.1 mg, max 0.5 mg per dose); CPR and ACLS/PALS if pulseless |
| Recurrence of block (under 1% at labeled doses) | New weakness, hypoventilation, falling SpO₂ or TOF ratio <0.9 | Ventilate; quantitative TOF; anesthesia decides on further reversal |
| Bronchospasm, laryngospasm | Wheeze, rising airway pressure, stridor after extubation | Bronchodilator, airway support; consider anaphylaxis |
Overdose & Toxicity Management
- Overdose: in trials, one accidental 40 mg/kg dose caused no significant effects. Treat supportively.
- Extracorporeal removal: high-flux hemodialysis drops plasma levels about 70% over 3–6 hr. Low-flux filters do not.
- The antidote's own trap: it keeps grabbing any rocuronium or vecuronium you give afterward. See re-paralysis timing in Interactions.
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: quantitative TOF (adductor pollicis) | Before dosing, then until recovery | Extubate only at TOF ratio ≥0.9; not reached: keep ventilating and reassess |
| Clinical: heart rate and rhythm | Continuous ECG during and several minutes after the dose | Marked bradycardia: atropine; asystole: ACLS/PALS |
| Clinical: ventilation and sedation | SpO₂ and EtCO₂ until breathing and airway are secure; sedation checked before and after reversal if intubated | Hypoventilation: support ventilation. Movement, bucking or rising heart rate: give sedation and analgesia |
| Laboratory: creatinine / CrCl | Before dosing when renal function is uncertain | CrCl <30 mL/min or dialysis: not recommended |
| Laboratory: PT/INR and aPTT | First hour in coagulopathy or anticoagulation | Rise of up to 25% for up to 1 hr expected; bleeding: treat the bleed |
| Post-reversal observation | PACU or ICU; longer with renal impairment or block-potentiating drugs | Recurrent weakness: ventilate, recheck TOF, involve anesthesia |
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| Hormonal contraceptives (pill, implant, ring, patch, hormonal IUD) | Binds progestogen: a dose equals missed contraceptive dose(s) | Non-hormonal backup for 7 days; document the counseling |
| Toremifene | Displaces rocuronium or vecuronium; slower recovery if taken the same day | Expect delayed recovery; quantitative TOF |
| Anticoagulants (warfarin, heparin, LMWH, rivaroxaban, dabigatran) | Additive aPTT and PT/INR prolongation | Monitor coagulation; a trial with heparin or LMWH prophylaxis showed no extra bleeding |
| Block-potentiating drugs after surgery (e.g., magnesium, aminoglycosides) | Recurrence of block | Watch ventilation and TOF; ventilate if weakness recurs |
| Rocuronium or vecuronium given again | Residual sugammadex binds the new dose: slower onset, shorter block | After up to 4 mg/kg: rocuronium 1.2 mg/kg after 5 min (if given within 30 min of reversal, onset may be delayed up to about 4 min and block shortened up to about 15 min); rocuronium 0.6 mg/kg or vecuronium 0.1 mg/kg after 4 hr (24 hr with mild to moderate renal impairment, or rocuronium 1.2 mg/kg if sooner is needed). After 16 mg/kg: wait 24 hr (suggested). Sooner: nonsteroidal blocker |
| Succinylcholine after sugammadex | Onset may be slower (receptors still partly occupied) | Allow for delayed onset |
IV Compatibility
- Running infusions: you can inject it into a line running NS, D5W, 0.45% NaCl with 2.5% dextrose, D5NS, Isolyte P with D5W, lactated Ringer's or Ringer's solution.
- Incompatible: verapamil, ondansetron and ranitidine are physically incompatible with it. Don't mix it with any other product.
- Check an institutional compatibility resource.
Special Populations
- Pediatrics: the Bridion label starts at birth. Generic labels start at 2 yr. Bradycardia runs higher than in adults: 10% at 2 mg/kg and 7% at 4 mg/kg in ages 2 to <17 yr. Under 2 yr, cardiac disorders hit 6.8% at 2 mg/kg (label section 6.1). Keep the ECG running and atropine at the bedside. The 16 mg/kg dose has not been studied.
- Neonates: studied from birth. The studied group had a median age of about 100 days. No age-based dose change.
- Pregnancy: there are no clinical trial data. Sugammadex binds progesterone. The manufacturer's modeling says 4 mg/kg may lower free progesterone by about 34%. The 2019 Society for Obstetric Anesthesia and Perinatology (SOAP) statement advises avoiding it in early pregnancy and prefers neostigmine-based reversal. It supports 16 mg/kg only for a cannot-intubate, cannot-ventilate event.
- Lactation: the label has no human data. A 2026 study at cesarean (n=10) found sugammadex undetectable, or below quantification, in every breast-milk sample. SOAP 2019 says breastfeeding is likely safe once the patient has recovered. Pump-and-discard is likely unnecessary. SOAP still preferred neostigmine-based reversal in early postpartum patients.
- Older Adults: recovery runs a little slower: 3.6 min at 75 yr or older vs 2.2 min at 18–64 yr. No dose change.
- Renal Impairment: at CrCl 30–80 mL/min, no dose change. With CrCl <30 mL/min or on dialysis, it is not recommended. The half-life stretches to about 19 hr there, and exposure climbs up to 17-fold. With mild to moderate impairment, wait 24 hr before re-paralysis, or use rocuronium 1.2 mg/kg if you need it sooner (see Interactions).
- Hepatic Impairment: the liver does not clear it, so no dose change. Use caution with coagulopathy or severe edema.
- Obesity: dose on actual body weight, including at BMI ≥40 kg/m². Dosing on ideal weight halved exposure.
- Myasthenia Gravis and Other Neuromuscular Disease: these patients are very sensitive to rocuronium. Neostigmine reversal is unreliable, so SOAP favors sugammadex. Dose to the measured depth.
- Cardiac Disease and ASA Class 3–4: no dose change. Sinus bradycardia shows up in 1–2% after 2–4 mg/kg, and in 7.4% after 16 mg/kg.
Field & Transport Considerations
- Scope: anesthesia, ED, ICU and critical-care transport clinicians (RN/CCT) give it under orders. It is not an EMS drug. Scope varies by state and agency protocol.
- Reversal Is Not Airway Rescue: reversal does not open the airway. Keep moving through the failed-airway plan (supraglottic airway, front-of-neck access).
- Storage & Stability: 25 °C (77 °F), excursions 15–30 °C (59–86 °F); protect from light, and use within 5 days once out of light protection.
- Carried Concentration: 100 mg/mL: mL = (mg/kg × kg) ÷ 100. A 16 mg/kg dose for 70 kg (1,120 mg, 11.2 mL) takes more than two 5 mL vials. Check your stock.
- Paralyzed Transfers: a paralyzed patient stays sedated and ventilated. Reversal is a destination decision, unless it is ordered and monitoring is available.
- Handoff Essentials: blocker, dose and time; TOF before and after; heart rate and blood pressure response; any reaction; when rocuronium or vecuronium may be reused; contraception counseling.
Clinical Pearls
Reversal does not open an airway: Most patients improved after sugammadex in a review of published cannot-intubate, cannot-ventilate cases. But 2 of 8 still obstructed and needed a surgical airway. Keep working the airway algorithm.
Plan the rescue dose before induction: The adult immediate-reversal dose takes more than one vial. Rocuronium is your RSI paralytic? Then know where the stock is.
Exam discriminator (CCRN, CFRN, FP-C): which reversal agent?
- Sugammadex: it encapsulates rocuronium or vecuronium. It reverses deep and shallow block when dosed to depth. No anticholinergic needed.
- Neostigmine: it blocks acetylcholinesterase and has a ceiling. It needs glycopyrrolate. It also reverses cisatracurium, but only at TOF ratio 0.4 to below 0.9 per ASA 2023.
- Succinylcholine: nothing reverses it. You wait for plasma cholinesterase.
Unparalyzed is not sedated: Reversing an intubated ED patient for a neuro exam unmasks pain and agitation. In a multicenter ED cohort, the patients who woke up more often needed a new analgesic or sedative. Have both ready.
Monitor the thumb, not the eye: Labeled doses are built on adductor pollicis responses, the thumb. Facial muscles recover earlier, so they overstate recovery.
Pharmacology
Mechanism of Action
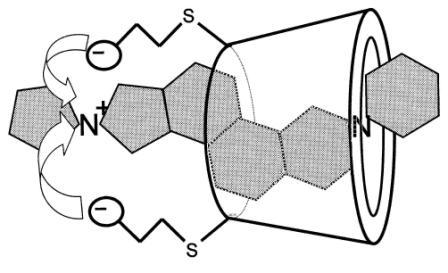
- A modified γ-cyclodextrin ring wraps around free rocuronium (highest affinity) or vecuronium, 1:1, in plasma. Free blocker falls. Transmission returns from deep as well as shallow block when the dose matches the measured depth.
- No acetylcholinesterase effect means no ceiling and no anticholinergic needed. Marked bradycardia still happens, rarely with cardiac arrest.
Pharmacokinetics
- IV: it works within minutes. Median TOF ratio reaches ≥0.9 in about 2–3 min. The effect is sustained, with recurrence under 1% at labeled doses.
- Half-life: about 2 hr in adults (1–2 hr in children); 4, 6 and 19 hr in mild, moderate and severe renal impairment.
- Metabolism: none. Elimination: the kidneys clear it, unchanged and as the complex. 96% leaves in urine, more than 90% within 24 hr.
- Distribution: volume of distribution 11–14 L; no plasma protein binding.
Names & Classification
- Generic Name
- Sugammadex (as sugammadex sodium; 100 mg sugammadex = 108.8 mg of the sodium salt)
- Brand Names
- Bridion (Merck); generic injections from multiple US manufacturers since 2026, listed on DailyMed (generic labels: 2 yr and older)
- Pharmacologic Class
- Selective relaxant binding agent (modified γ-cyclodextrin)
- Therapeutic Class
- Neuromuscular blockade reversal agent
- Controlled Substance
- Not controlled
- ISMP High-Alert
- No (the ISMP list covers the neuromuscular blockers, not their reversal agents)
- Look-Alike / Sound-Alike
- None on the ISMP confused drug names list as updated through June 2024; check your pharmacy's current list
References
- Merck Sharp & Dohme LLC. (2026). BRIDION (sugammadex) injection, for intravenous use: Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=5171d883-fe8f-482c-97ab-40b00975b64a
- Thilen, S. R., Weigel, W. A., Todd, M. M., Dutton, R. P., Lien, C. A., Grant, S. A., Szokol, J. W., Eriksson, L. I., Yaster, M., Grant, M. D., Agarkar, M., Marbella, A. M., Blanck, J. F., & Domino, K. B. (2023). 2023 American Society of Anesthesiologists practice guidelines for monitoring and antagonism of neuromuscular blockade. Anesthesiology, 138(1), 13–41. https://doi.org/10.1097/ALN.0000000000004379
- Fuchs-Buder, T., Romero, C. S., Lewald, H., Lamperti, M., Afshari, A., Hristovska, A. M., Schmartz, D., Hinkelbein, J., Longrois, D., Popp, M., de Boer, H. D., Sorbello, M., Jankovic, R., & Kranke, P. (2023). Peri-operative management of neuromuscular blockade: a guideline from the European Society of Anaesthesiology and Intensive Care. European Journal of Anaesthesiology, 40(2), 82–94. https://doi.org/10.1097/EJA.0000000000001769
- Johnson, K. B., & Chacin, R. (2023). Clarifying the grey space of sugammadex induced bradycardia. Current Opinion in Anaesthesiology, 36(4), 422–427. https://doi.org/10.1097/ACO.0000000000001282
- Mensah-Osman, E., Mukai, Y., Wang, A., Matuszczak, M., Saldien, V., Leibensperger, H., Speek, M., Locco, A., Wrishko, R., Gee, A., & Herring, W. J. (2025). Sugammadex for reversal of neuromuscular blockade in neonates and infants less than 2 years old: results from a phase IV randomized clinical trial. Anesthesiology, 143(2), 300–312. https://doi.org/10.1097/ALN.0000000000005535
- Abou Nafeh, N. G., Aouad, M. T., Khalili, A. F., Serhan, F. G., Sokhn, A. M., & Kaddoum, R. N. (2025). Use of sugammadex in "cannot intubate, cannot ventilate" scenarios: a systematic review of case reports. Anesthesia & Analgesia, 140(4), 931–937. https://doi.org/10.1213/ANE.0000000000007199
- Willett, A. W., Butwick, A., Togioka, B., Bensadigh, B., Hofer, J., & Zakowski, M. (2019). Statement on sugammadex during pregnancy and lactation. Society for Obstetric Anesthesia and Perinatology. https://www.soap.org/assets/docs/SOAP_Statement_Sugammadex_During_Pregnancy_Lactation_APPROVED.pdf
- Lawson, C., Rech, M. A., Sun, J., Celmins, L., Sindelar, M., Van Wert, E., et al. (2026). A multi-center retrospective cohort study of sugammadex for neuromuscular blockade reversal in the emergency department: SUGARED study. American Journal of Emergency Medicine, 109, 27–34. https://doi.org/10.1016/j.ajem.2026.06.021
- Hodge, A. T., Tognolini, A. R., Liu, X., Won, H., Roberts, J. A., Wallis, S. C., Woods, C. A., & Eley, V. A. (2026). Plasma levels and postpartum breastmilk concentrations of sugammadex: a pharmacokinetic study in women undergoing general anaesthesia for caesarean delivery. International Journal of Obstetric Anesthesia, 66, 104874. https://doi.org/10.1016/j.ijoa.2026.104874
- DailyMed, U.S. National Library of Medicine. Sugammadex injection labels (search results, accessed 2026-10-15). https://dailymed.nlm.nih.gov/dailymed/search.cfm?labeltype=all&query=sugammadex
- Institute for Safe Medication Practices. ISMP List of Confused Drug Names (accessed 2026-10-15). https://www.ismp.org/recommendations/confused-drug-names-list
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.