

Bedside Snapshot
- Use It For
- Acute agitation in schizophrenia (IM, labeled); severe undifferentiated ED agitation (off-label); schizophrenia and bipolar I disorder (oral)
- Adult Dose
- Agitation: 10–20 mg IM; 10 mg may repeat every 2 hr or 20 mg every 4 hr (max 40 mg/day IM, up to 3 days)
- Schizophrenia: 20 mg PO twice daily with food
- Pediatric Dose
- Age 6–11 yr: 5 mg IM (limited data)
- Age 12–18 yr: 10 mg IM
- Differs from FDA label: not established in children; the 2019 AAEP consensus does not recommend ziprasidone
- Onset / Duration
- IM: 15–30 min, plasma peak at about 60 min; labeled redosing every 2–4 hr (not a measured duration; T½ 2–5 hr). PO: peak 6–8 hr / twice-daily dosing
- Do Not Give / Hold If
- Known QT prolongation or QTc >500 ms; recent MI; uncompensated heart failure; other QT-prolonging drugs (e.g. droperidol); MAOI within 14 days; never IV
- Watch For
- QTc prolongation and torsades (ECG, K⁺, Mg²⁺); oversedation and hypoventilation (SpO₂, EtCO₂); orthostatic hypotension (BP); dystonia, NMS or serotonin syndrome (tone, temperature)
- Reversal / Rescue
- No antidote. Torsades: magnesium sulfate 2 g IV, defibrillate if unstable. Hypotension: fluids, then norepinephrine or phenylephrine (not epinephrine or dopamine). Dystonia: diphenhydramine
- Must Remember
- IM only, and check what was already given: the label contraindicates ziprasidone with droperidol and other QT-prolonging drugs. Get a 12-lead ECG as soon as it is safe
Indications
Emergency & Prehospital
- Acute agitation in adults with schizophrenia: the FDA-labeled use for the IM product. Reach for it when you need fast IM antipsychotic control
- Severe undifferentiated agitation in the ED: off-label, but the ACEP 2024 clinical policy rates an atypical alone or with midazolam as a Level B option. ACEP names no agent for the out-of-hospital setting or for patients over 65
ED / ICU / Transport
- Short-term parenteral control: IM for up to 3 consecutive days. If long-term therapy is needed, switch to oral capsules as soon as possible
Other Uses
- Schizophrenia: oral treatment and maintenance (adults)
- Bipolar I disorder, manic or mixed episodes: oral monotherapy (adults)
- Bipolar I disorder, maintenance: oral, as an adjunct to lithium or valproate (adults)
Dosing & Administration
Doses vary by protocol; follow local protocols and medical direction.
Available Forms
- IM injection (Geodon for Injection and generic ziprasidone mesylate): lyophilized powder in a single-dose vial. Reconstitute with 1.2 mL Sterile Water for Injection to get 20 mg/mL (colorless to pale pink). This is the form EDs and psychiatric units stock.
- Capsules (Geodon and generic ziprasidone hydrochloride): 20, 40, 60 and 80 mg
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| Acute agitation in schizophrenia (labeled) | 10–20 mg IM | 10 mg may repeat every 2 hr, or 20 mg every 4 hr; max 40 mg/day IM. More than 3 consecutive days of IM dosing not studied | In the label trials 10 mg beat a 2 mg control over 0–2 hr and 20 mg over 0–4 hr. Those trials enrolled mostly patients who calmed with instructions (baseline BARS 5) and few more severely agitated patients, so labeled efficacy does not apply directly to violent or undifferentiated agitation. Do not combine with oral ziprasidone (no safety data) |
| Severe undifferentiated agitation, ED (off-label) | 20 mg IM (10 mg also studied) | Same limits: max 40 mg/day IM | In a randomized ED trial only 25% (10 mg) and 35% (20 mg) were adequately sedated at 15 min, vs 64% with droperidol 5 mg. Plan reassessment and rescue. ACEP 2024: an atypical plus midazolam gives faster control |
| Schizophrenia | 20 mg PO twice daily with food | Adjust at intervals of ≥2 days up to 80 mg twice daily; above 80 mg twice daily not generally recommended; above 100 mg twice daily not evaluated | Steady state in 1–3 days. Maintenance: no added benefit above 20 mg twice daily in the label study |
| Bipolar I mania or mixed episode | 40 mg PO twice daily with food on day 1 | Increase to 60 or 80 mg twice daily on day 2; then 40–80 mg twice daily (max 160 mg/day) | Mean dose about 120 mg/day in the label trials |
| Bipolar I maintenance (with lithium or valproate) | 40–80 mg PO twice daily with food | Continue the dose on which the patient was stabilized; max 80 mg twice daily | Reassess the need for maintenance periodically |
Pediatric Dosing
| Indication | Dose & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| Acute agitation, age 6–11 yr | 5 mg IM | 5 mg single; NASEMSO gives no repeat interval or daily maximum | Limited data (NASEMSO v3.0, Agitated or Violent Patient, p. 61). Differs from FDA label: the label does not establish pediatric safety or effectiveness |
| Acute agitation, age 12–18 yr | 10 mg IM | 10 mg single; NASEMSO gives no repeat interval or daily maximum | NASEMSO v3.0, p. 61. Differs from FDA label: not established in children |
Not recommended in children: Kids are not small adults, and this is not their drug. The 2019 American Association for Emergency Psychiatry (AAEP) pediatric agitation consensus does not recommend ziprasidone. Why? It is activating, it prolongs the QT, and the oral form needs food. One 4-week trial in ages 10–17 with bipolar I disorder never landed on a safe and effective dose. If a specialist or medical-control agent is chosen instead, NASEMSO gives doses for olanzapine (5 mg IM age 6–11 yr; 10 mg IM age 12–18 yr) and haloperidol (1–3 mg IM age 6–12 yr). See weight-based dosing for safe calculation practice.
Preparation & Administration
- Reconstitution: add 1.2 mL Sterile Water for Injection to the vial and shake vigorously until all the powder dissolves (20 mg/mL). Inspect for particles.
- Volumes at 20 mg/mL: 10 mg = 0.5 mL; 20 mg = 1 mL. Discard the unused portion (no preservative).
- Diluent and mixing: Sterile Water for Injection only; do not mix with other drugs or solvents.
- Route: IM only. Never give IV.
- Capsules: swallow whole with food; do not open, crush or chew. Food increases absorption up to two-fold. Reproducible absorption takes a meal of at least 500 kcal. Fat content does not matter.
- After injection: keep a drowsy patient lying down until orthostatic hypotension and hypoventilation are excluded.
Kidney and liver considerations, the IM excipient included, are in Special Populations.
Contraindications & Precautions
Contraindications
- Known QT prolongation, including congenital long QT syndrome
- Recent acute myocardial infarction or uncompensated heart failure
- Other drugs that prolong the QT interval: the label names dofetilide, sotalol, quinidine and other class Ia and III antiarrhythmics (e.g. amiodarone, procainamide), droperidol, chlorpromazine, thioridazine, mesoridazine, pimozide, moxifloxacin, sparfloxacin, gatifloxacin, halofantrine, mefloquine, pentamidine, arsenic trioxide, levomethadyl acetate, dolasetron, probucol and tacrolimus, plus any drug whose label carries QT prolongation as a contraindication or a boxed or bolded warning (e.g. methadone)
- MAOIs, including linezolid and IV methylene blue, now or within 14 days (serotonin syndrome; added to the label in January 2025)
- Hypersensitivity to ziprasidone
Precautions
- Bradycardia, hypokalemia, hypomagnesemia or a history of arrhythmia: the label says avoid. Check K⁺ and Mg²⁺ when electrolyte loss is likely, from diuretics or diarrhea, and replete them before dosing.
- Already taking oral ziprasidone: adding IM ziprasidone is not recommended. There are no safety data for that combination.
- Cardiovascular or cerebrovascular disease, dehydration, antihypertensives: orthostatic hypotension and syncope (0.6% in trials).
- Serotonergic drugs: serotonin syndrome risk. Ziprasidone alone has caused it too.
- Seizure disorder: seizures in 0.4% of trial patients.
- Aspiration risk, heat exposure, exertion: dysphagia and impaired temperature regulation (class effects).
- History of low WBC or drug-induced neutropenia: leukopenia, neutropenia and agranulocytosis reported.
Hold / Reassess If
- QTc >500 ms or a rise of ≥60 ms from baseline: no further doses; continuous ECG, correct K⁺ and Mg²⁺, defibrillator at hand
- Palpitations, dizziness or syncope: 12-lead ECG and rhythm monitoring for torsades
- SpO₂ <90%, rising EtCO₂ or falling respiratory rate: no further sedatives; support the airway and ventilation
- Symptomatic orthostatic hypotension: keep supine, give fluids, no repeat dose
- Fever with rigidity, clonus or altered mental status: stop and evaluate for neuroleptic malignant syndrome (NMS) or serotonin syndrome
- Rash with no other cause: discontinue (label)
- Pre-existing low WBC or a history of drug-induced leukopenia or neutropenia: stop at the first sign of a WBC decline with no other cause. Any patient with an absolute neutrophil count <1,000/mm³: stop and follow the WBC until recovery (label)
FDA Boxed Warning: Older adults with dementia-related psychosis carry a higher risk of death on antipsychotics. The excess is about 1.6–1.7 times placebo, mostly from cardiovascular or infectious causes. Ziprasidone is not approved for dementia-related psychosis.
Know What Was Already Given: The label contraindicates ziprasidone with droperidol and other QT-prolonging drugs. Read the EMS and ED medication record before you dose. Find a QT-prolonging drug on board? Choose a different agent per protocol.
Adverse Effects & Toxicity
Common
- Somnolence: 20% after 20 mg IM (8% with a 2 mg control dose); 14% with oral use (7% placebo)
- Headache and nausea: headache 13% after 10 mg IM; nausea 12% after 20 mg IM
- Dizziness: 10% after 20 mg IM
- Injection-site pain: 7–9%
- Extrapyramidal symptoms (EPS): 14% vs 8% placebo in oral schizophrenia trials; akathisia and dystonia
- Rash or urticaria: about 5% in premarketing trials, dose-related
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
| QTc prolongation, torsades de pointes | Oral 160 mg/day: QTc about 10 ms longer than placebo and 9–14 ms longer than risperidone, olanzapine, quetiapine or haloperidol. IM 20 mg then 30 mg: +4.6 then +12.8 ms (IM haloperidol +6.0 then +14.7 ms). Torsades rare, with confounders | Stop dosing; magnesium sulfate 2 g IV; defibrillate if unstable or pulseless; correct K⁺; isoproterenol or overdrive pacing for recurrent pause-dependent torsades |
| Oversedation, respiratory depression | Falling RR and SpO₂, rising EtCO₂. In one small ED trial that counted any EtCO₂ change consistent with respiratory depression or SpO₂ <90%, it followed 36–39% of IM ziprasidone doses (12% with droperidol). In a 737-patient observational ED study, hypoxemia (1%) and intubation (0.5%) were uncommon and similar with midazolam, olanzapine, ziprasidone and haloperidol | Airway positioning, O₂, bag-valve-mask ventilation; intubation if needed |
| Orthostatic hypotension, syncope | Postural BP drop, dizziness, tachycardia; postural hypotension in 5% after 20 mg IM | Supine, IV fluids; no repeat dose; vasopressor choice under Overdose |
| Neuroleptic malignant syndrome | Hyperthermia, rigidity, altered mental status, autonomic instability, high CK, myoglobinuria | Stop all antipsychotics; cooling, fluids, ICU care |
| Serotonin syndrome | Agitation, tremor, myoclonus, hyperreflexia, diaphoresis, hyperthermia, labile BP | Stop ziprasidone and all serotonergic drugs; supportive care |
| DRESS, Stevens-Johnson syndrome | Rash with fever, eosinophilia, lymphadenopathy or organ involvement (drug reaction with eosinophilia and systemic symptoms) | Stop ziprasidone; sometimes fatal |
| Acute dystonia | Neck spasm, throat tightness, tongue protrusion; more common in young males | Anticholinergic such as diphenhydramine per protocol |
With Ongoing Therapy
- Tardive dyskinesia: involuntary movements that may be irreversible. Risk climbs with duration and cumulative dose, but brief, low-dose treatment can still bring it on. It shows up most in older adults, especially women
- Stroke and TIA in older adults with dementia: fatal stroke included. The signal comes from placebo-controlled trials of other atypical antipsychotics. Ziprasidone is not approved for dementia-related psychosis
- Falls: sleepiness, postural hypotension and unsteady motor or sensory control can bring on falls and fractures
- Hyperprolactinemia: galactorrhea, amenorrhea, gynecomastia, impotence
- Priapism: one case in premarketing data. It comes from alpha blockade and can need urologic or surgical treatment
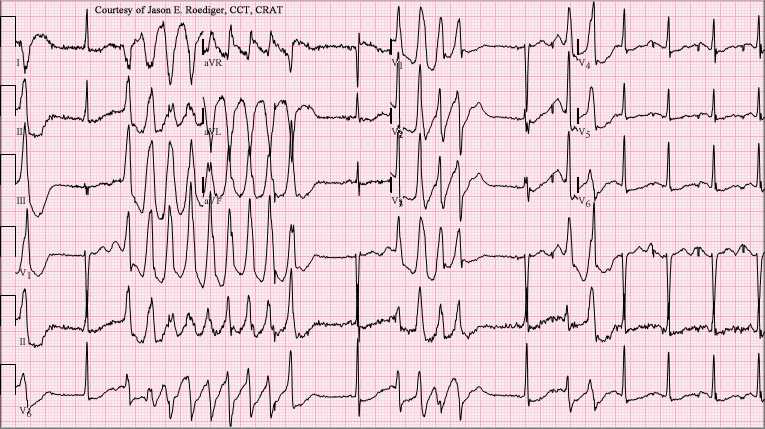
Overdose & Toxicity Management
- Signs: somnolence, EPS, tremor and anxiety. The biggest confirmed premarketing ingestion, 3,240 mg, caused only minimal sedation, slurred speech and transient hypertension (200/95 mmHg). The airway threats are obtundation, seizures and head-and-neck dystonia.
- Immediate care: airway, oxygenation and ventilation; IV access; continuous ECG monitoring from the start; consider co-ingestants; call Poison Control (1-800-222-1222).
- Decontamination: the label suggests considering activated charcoal. Give it only to an alert patient with an intact airway, or once the airway is protected, and involve Poison Control. Don't induce emesis. Obtundation, seizures or dystonia raise the aspiration risk.
- Arrhythmias: the QT effects add up, so avoid disopyramide, procainamide and quinidine. For torsades, give magnesium sulfate as above.
- Hypotension: IV fluids first, then an alpha agonist such as norepinephrine or phenylephrine. Don't use epinephrine or dopamine. Beta stimulation against alpha-1 blockade can make the hypotension worse (label).
- No antidote. Ziprasidone is not dialyzable. For severe EPS, reach for an anticholinergic. Monitor until the patient recovers.
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: sedation and agitation score | Before the dose, then every 15 min until stable | Document a score (RASS or local scale); not settling by 15–30 min: follow the rescue plan |
| Clinical: SpO₂ and waveform EtCO₂ | Continuous after any IM dose, especially with alcohol or a benzodiazepine | SpO₂ <90% or rising EtCO₂: reposition, O₂, assist ventilation |
| Clinical: 12-lead ECG and rhythm | As soon as it is safe to obtain; repeat after further doses or other QT drugs; continuous rhythm in the ED and transport | QTc >500 ms or rise ≥60 ms: no further doses, correct K⁺ and Mg²⁺ (QT interval) |
| Clinical: BP, including orthostatic | Baseline; before any repeat dose; before the patient stands | Symptomatic drop: supine, fluids, no repeat |
| Clinical: temperature, tone, reflexes | On arrival and with any deterioration | Fever with rigidity: suspect NMS; clonus or hyperreflexia: suspect serotonin syndrome |
| Laboratory: potassium and magnesium | Baseline when electrolyte loss is likely (diuretics, diarrhea); periodically if diuretics start | Low values: replete before dosing (potassium) |
| Laboratory: glucose | Point-of-care glucose in every agitated or sedated patient | Low: treat hypoglycemia; high: assess for DKA or HHS (glucose) |
| Laboratory: ethanol and co-ingestants | When intoxication or overdose is suspected | Guides airway risk and QT-drug exposure (ethanol level, toxicology panel) |
| Laboratory: CBC | Frequently in the first months if there is a history of low WBC | ANC <1,000/mm³: discontinue and follow the WBC (WBC) |
| Laboratory: metabolic monitoring on ongoing therapy | Fasting glucose, lipids and weight at the start and periodically | Rising values: review the regimen with the prescriber (lipid panel) |
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| Other QT-prolonging drugs (droperidol, amiodarone, sotalol, methadone, moxifloxacin; also haloperidol, ondansetron, macrolides) | Additive QT prolongation and torsades | Label-named drugs and drugs with a boxed or bolded QT warning: contraindicated. The label also says not to prescribe other drugs consistently shown to prolong QT; if exposure has already happened, 12-lead ECG, K⁺ and Mg²⁺, continuous monitoring |
| MAOIs (linezolid, IV methylene blue, phenelzine and others) | Serotonin syndrome | Contraindicated within 14 days of an MAOI; wait 3 days after stopping ziprasidone before a psychiatric MAOI. If linezolid or methylene blue is needed, stop ziprasidone first |
| Other serotonergic drugs (SSRIs, SNRIs, tricyclics, triptans, fentanyl, tramadol, methadone, lithium, amphetamines) | Serotonin syndrome risk | Monitor; stop ziprasidone and the serotonergic drugs if signs appear |
| Benzodiazepines, alcohol, opioids (midazolam, lorazepam) | Additive sedation and respiratory depression. No pharmacokinetic interaction with lorazepam in label analyses; ACEP endorses an atypical plus midazolam in the ED | Continuous SpO₂ and EtCO₂ with airway equipment at hand |
| CYP3A4 inhibitors (ketoconazole) | Ziprasidone AUC and peak up 35–40%; ketoconazole did not augment the QTc effect in the label study | No label dose change; watch for added sedation and hypotension |
| CYP3A4 inducers (carbamazepine) | Ziprasidone AUC down about 35%, possibly more at higher carbamazepine doses | Expect a weaker effect |
| Antihypertensives | Enhanced hypotension | Check orthostatic BP before repeat doses |
| Levodopa, dopamine agonists | Ziprasidone may antagonize their effect | Consider another agent in Parkinson disease |
IV Compatibility
- Not an IV product: IM use only; never give IV.
- Reconstitute only with Sterile Water for Injection.
- Do not mix with other drugs or solvents in the vial or syringe.
- Verify with an institutional compatibility resource.
Special Populations
- Pediatrics: the label does not establish safety or effectiveness at any age. The 2019 AAEP consensus does not recommend ziprasidone. Age-based NASEMSO doses are in the Pediatric Dosing table above.
- Neonates: exposure in the third trimester can cause extrapyramidal or withdrawal signs in the newborn: agitation, abnormal tone, tremor, somnolence, respiratory distress, feeding problems. Tell the neonatal team.
- Pregnancy: The published epidemiology has not established a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. Rabbit studies did show malformations, at 3 times the maximum human dose. Untreated schizophrenia or bipolar disorder carries its own risk for the mother. Don't hold an indicated dose for dangerous agitation. A national pregnancy registry for atypical antipsychotics exists.
- Lactation: One case report found ziprasidone in breast milk, and no infant effects were reported. Monitor the infant for sedation, irritability, poor feeding and abnormal movements.
- Older Adults: boxed warning for dementia-related psychosis. IM ziprasidone has not been systematically evaluated at 65 years and older. The label advises a lower starting dose, slower titration and close monitoring for orthostasis. A 2025 geriatric ED systematic review found only 17 older adults who had received ziprasidone. That is too few to judge its safety. The AGS Beers Criteria flag antipsychotics as potentially inappropriate in older adults, particularly for behavioral symptoms of dementia or delirium.
- Renal Impairment: no oral dose adjustment. Less than 1% leaves unchanged in urine, and hemodialysis does not remove it. The IM product contains sulfobutylether beta-cyclodextrin (SBECD). The kidneys clear it by filtration, so give IM ziprasidone with caution in renal impairment.
- Hepatic Impairment: no specific adjustment is established. In Child-Pugh A and B cirrhosis, AUC rose 13% and 34%, and the half-life was 7.1 vs 4.8 hr. Child-Pugh C and IM use in hepatic impairment have not been studied.
- Obesity / Dosing Weight: adult doses are fixed. They are not weight-based.
- Cardiac Disease: trials excluded patients with recent MI or unstable heart disease. Recent MI and uncompensated heart failure are contraindications.
- Smokers: smoking does not change its kinetics, because ziprasidone is not a CYP1A2 substrate.
Field & Transport Considerations
- Scope: not named in the National EMS Scope of Practice Model's medication lists. So it falls under paramedic-level medication administration with medical-director approval. AEMT only where a state or local protocol adds it. Few EMS agencies carry it, so check your formulary. Flight and critical-care transport, and ED and inpatient RNs, give it under protocol or order. Varies by state and agency protocol.
- Storage & Stability: dry vials at 25 °C (77 °F), excursions 15–30 °C (59–86 °F); protect from light. After reconstitution, protected from light: up to 24 hr at 15–30 °C or up to 7 days refrigerated at 2–8 °C (36–46 °F).
- Carried Concentration: 20 mg/mL after 1.2 mL Sterile Water. 10 mg is 0.5 mL and 20 mg is 1 mL. Don't mix it up with IM olanzapine, which is about 5 mg/mL after reconstitution. Say the dose in mg and mL at the cross-check.
- Preparation Time: the powder takes vigorous shaking to dissolve. Draw the dose up before the team commits to physical restraint.
- Agitation Calls: start with verbal de-escalation. Look for reversible causes like hypoglycemia and hypoxia. Once sedated, monitor SpO₂, EtCO₂ and ECG continuously.
- QT Coordination: ask whether droperidol, haloperidol, ondansetron or another QT-prolonging drug went in before ziprasidone. Write down any QTc you obtained.
- Handoff Essentials: drug, dose, route and time of each dose; other sedatives, QT drugs and alcohol; sedation score before and after; BP; airway events; glucose; QTc, K⁺ and Mg²⁺ if known.
Clinical Pearls
The Droperidol Trap: Droperidol sits on the Geodon contraindicated-combination list. EMS or triage already gave droperidol? Don't reach for ziprasidone as the second agent. Choose a non-QT-prolonging rescue per protocol.
ED Agitation Comparisons (CEN, FP-C):
- Adequate sedation at 15 min: droperidol 5 mg 64%, ziprasidone 10 mg 25%, ziprasidone 20 mg 35%, lorazepam 2 mg 29% (randomized trial)
- In a 737-patient prospective observational ED study, not randomized, IM midazolam 5 mg sedated 18% more patients at 15 min than ziprasidone 20 mg. Adverse events were uncommon and similar across agents
- Blinded trials put IM ziprasidone onset at 15–30 min. That is close to IM olanzapine and faster than IM haloperidol
Plan for a Slower Start: Most patients are not calm at 15 minutes. Keep staff and monitoring in place, reassess at 15 and 30 minutes, and agree on the rescue agent before the first dose.
Why the Label Says Consider Other Drugs First (CCRN): Ziprasidone prolongs the QTc more than several other antipsychotics. That is why the label asks prescribers to weigh it before choosing the drug. In a head-to-head study, IM doses prolonged the QTc about as much as IM haloperidol.
Pressor Choice in Hypotension (CFRN): Alpha-1 blockade leaves beta-2 vasodilation unopposed. Epinephrine or dopamine can make the hypotension worse that way. Reach for fluids and a pure alpha agonist.
Capsules Need Food: Absorption goes up as much as two-fold when oral doses come with food. A patient who takes doses without meals on the unit may look like a treatment failure.
Linezolid and Methylene Blue: The label contraindicates MAOIs, and that includes linezolid and IV methylene blue. It has done so since 2025. In the ICU, stop ziprasidone before either drug starts.
Ziprasidone vs Olanzapine (Exam Discriminator): Ziprasidone has the bigger QT signal, and it needs food when taken orally. Smoking doesn't touch it. Olanzapine brings more sedation, metabolic and anticholinergic burden, and smoking speeds its clearance.
Pharmacology
Mechanism of Action
- Dopamine D₂ and serotonin 5-HT₂A antagonism → antipsychotic and calming effect. Its affinity for 5-HT₂A is about 10 times its affinity for D₂.
- 5-HT₁A agonism and serotonin and norepinephrine reuptake inhibition → serotonergic activity, and with it the risk of serotonin syndrome alongside other serotonergic drugs.
- Alpha-1 adrenergic blockade → orthostatic hypotension. This is why epinephrine and dopamine can make hypotension worse.
- Moderate histamine H₁ affinity; no appreciable muscarinic affinity → somnolence, with few anticholinergic effects.
- Delayed ventricular repolarization → QTc prolongation that rises with dose.
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| IM | 15–30 min (fewer than 4 in 10 adequately sedated at 15 min in one randomized ED trial) | Plasma peak at about 60 min or earlier | No measured clinical duration; the label allows a repeat dose 2 hr after 10 mg or 4 hr after 20 mg (benefit shown over 0–2 and 0–4 hr) |
| PO | Slow; not for acute control | 6–8 hr | Twice-daily dosing; steady state in 1–3 days |
- Half-life: IM 2–5 hr; oral mean about 7 hr. Little builds up over 3 days of IM dosing.
- Bioavailability: IM 100%; oral about 60% with food.
- Metabolism: about two-thirds by reduction (glutathione and aldehyde oxidase), and less than one-third by CYP3A4 oxidation. The reduction route has no known clinically relevant inhibitors or inducers.
- Active metabolites: most of the activity comes from the parent drug.
- Elimination: mostly fecal, about 66%, with 20% in urine as metabolites. Less than 1% leaves unchanged in urine.
- Distribution: volume of distribution about 1.5 L/kg; more than 99% protein bound.
Names & Classification
- Generic Name
- Ziprasidone hydrochloride (capsules); ziprasidone mesylate (IM injection)
- Brand Names
- Geodon (US capsules and for injection); generics; Zeldox (some countries outside the US)
- Pharmacologic Class
- Benzisothiazolyl piperazine; second-generation (atypical) antipsychotic
- Therapeutic Class
- Antipsychotic; agent for acute agitation
- Controlled Substance
- Not controlled
- ISMP High-Alert
- No
- Look-Alike / Sound-Alike
- None on the ISMP confused drug names list (updated through June 2024). Concentration trap: IM ziprasidone 20 mg/mL vs IM olanzapine about 5 mg/mL
References
- Roerig (Pfizer) / Viatris. (2025). GEODON (ziprasidone) capsules and GEODON (ziprasidone mesylate) for injection: Prescribing information (revised January 2025; DailyMed version September 2026). U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=8326928a-2cb6-4f7f-9712-03a425a14c37
- American College of Emergency Physicians Clinical Policies Subcommittee on Severe Agitation; Thiessen, M. E. W., Godwin, S. A., Hatten, B. W., Whittle, J. A., Haukoos, J. S., & Diercks, D. B. (2024). Clinical policy: Critical issues in the evaluation and management of adult out-of-hospital or emergency department patients presenting with severe agitation. Annals of Emergency Medicine, 83(1), e1–e30. https://doi.org/10.1016/j.annemergmed.2023.09.010
- Martel, M. L., Driver, B. E., Miner, J. R., Biros, M. H., & Cole, J. B. (2021). Randomized double-blind trial of intramuscular droperidol, ziprasidone, and lorazepam for acute undifferentiated agitation in the emergency department. Academic Emergency Medicine, 28(4), 421–434. https://doi.org/10.1111/acem.14124
- Casey, M. F., Elder, N. M., Fenn, A., Niznik, J., Khoujah, D., Cole, J. B., et al. (2025). Comparative safety of medications for severe agitation: A Geriatric Emergency Department Guidelines 2.0 systematic review. Journal of the American Geriatrics Society, 73(9), 2893–2904. https://doi.org/10.1111/jgs.19485
- Zun, L. S. (2018). Evidence-based review of pharmacotherapy for acute agitation. Part 1: Onset of efficacy. Journal of Emergency Medicine, 54(3), 364–374. https://doi.org/10.1016/j.jemermed.2017.10.011
- Gerson, R., Malas, N., Feuer, V., Silver, G. H., Prasad, R., Mroczkowski, M. M., et al. (2019). Best practices for evaluation and treatment of agitated children and adolescents (BETA) in the emergency department: Consensus statement of the American Association for Emergency Psychiatry. Western Journal of Emergency Medicine, 20(2), 409–418. https://doi.org/10.5811/westjem.2019.1.41344
- Drew, B. J., Ackerman, M. J., Funk, M., Gibler, W. B., Kligfield, P., Menon, V., et al. (2010). Prevention of torsade de pointes in hospital settings: A scientific statement from the American Heart Association and the American College of Cardiology Foundation (landmark scientific statement). Circulation, 121(8), 1047–1060. https://doi.org/10.1161/CIRCULATIONAHA.109.192704
- Klein, L. R., Driver, B. E., Miner, J. R., Martel, M. L., Hessel, M., Collins, J. D., et al. (2018). Intramuscular midazolam, olanzapine, ziprasidone, or haloperidol for treating acute agitation in the emergency department. Annals of Emergency Medicine, 72(4), 374–385. https://doi.org/10.1016/j.annemergmed.2018.04.027
- National Association of State EMS Officials. (2022). National Model EMS Clinical Guidelines, Version 3.0 (March 2022): Agitated or Violent Patient/Behavioral Emergency, p. 61 (ziprasidone adult and pediatric doses). https://nasemso.org/docs.ashx?id=1444322
- National Highway Traffic Safety Administration. (2021). National EMS Scope of Practice Model 2019, including Change Notices 1.0 and 2.0 (DOT HS 813 151), Section V, Medical Director Approved Medications, pp. 29–30. https://mn.gov/oems/assets/National_EMS_Scope_of_Practice_Model_2021_%20%28002%29_tcm1221-744908.pdf
- Gandelman, K., Alderman, J., Glue, P., Lombardo, I., LaBadie, R., et al. (2009). The impact of calories and fat content of meals on oral ziprasidone absorption. Journal of Clinical Psychiatry, 70(1), 58–62. https://doi.org/10.4088/jcp.08m04104
- American Geriatrics Society Beers Criteria Update Expert Panel. (2023). American Geriatrics Society 2023 updated AGS Beers Criteria for potentially inappropriate medication use in older adults. Journal of the American Geriatrics Society, 71(7), 2052–2081. https://doi.org/10.1111/jgs.18372
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.