

Bedside Snapshot
- Indications
- Massive or pulsatile limb bleeding, or any amputation: tourniquet first
- Deep stab (3 cm or longer) or gunshot or blast wound with active bleeding: packing
- Junctional (groin or axilla) bleeding: pack and press; junctional tourniquet if stocked
- Contraindications / Abort
- No tourniquet for bleeding that direct pressure controls
- Never place a tourniquet distal to a wound you have not found
- Do not loosen if in shock, not monitorable, or for an amputation
- Failed conversion: repeat only if conditions have clearly improved
- Critical Steps
- Apply 2–3 in (5–7.5 cm) above the wound, on skin
- Tighten until bleeding stops and the distal pulse is absent
- Add a second tourniquet side by side if bleeding continues
- Pack the wound, then hold pressure at least 3 min
- Confirm & Monitor
- Bleeding stopped; no distal pulse; check sensation and motor function
- Convert within 2 h only if all three criteria are met
- Watch for rebleeding through the dressing
- TXA IV/IO within 3 h of injury, per protocol
Key Numbers
Tourniquet for life-threatening limb bleeding that pressure cannot stop in time. Convert within 2 hours only when all criteria are met; otherwise leave it on.
| Parameter | Value |
|---|---|
| Tourniquet position | 2–3 in (5–7.5 cm) above the wound, directly on skin |
| Tighten until | Bleeding stops and the distal pulse is not palpable |
| Conversion criteria | ALL met: casualty not in shock; wound can be monitored closely for rebleeding; tourniquet not controlling an amputation |
| Conversion timing | At the first opportunity, not more than 2 h after application, and only when criteria are met |
| Failed conversion | Repeated attempts not recommended (risk of incremental exsanguination); a second attempt only if conditions have clearly improved |
| Tourniquet over 6 h | Do not remove outside a closely monitored setting, preferably with lab capability |
| Ischemia risk | Muscle death and rhabdomyolysis rise after 3–4 h; high rate of irreversible damage after 6 h |
| Packing | Hemostatic gauze into the cavity, then at least 3 min of direct pressure, then a pressure dressing |
| Child tourniquet fit | Limb circumference 13 cm or more and age about 2 years or older (very low-certainty evidence) |
| TXA (Paramedic/RN/CCT, per protocol) | IV/IO only. EMS option: 1 g over about 10 min, then 1 g over 8 h in hospital; or 2 g as infusion or slow push. Within 3 h of injury |
Overview & Principles
Hemorrhage control means stopping the bleeding you can see until surgery can take over. Uncontrolled blood loss kills in the first hours after severe trauma. After severe brain injury, bleeding is the second most common early cause of death. Tourniquets, pressure dressings, hemostatic gauze and tranexamic acid (TXA) are your tools. The order you use them in, and when, decides the outcome.
How It Works
- Tourniquet first for massive limb bleeding: Pulsatile, pooling or massive limb bleeding, or any traumatic amputation? Apply a tourniquet at once.
- Pressure and packing for the rest: Compressible bleeding, and sites a tourniquet can't use, get direct pressure, hemostatic gauze and a pressure dressing.
- Packing for deep wounds: Pack hemostatic gauze down into the cavity, right onto the source. Hold direct pressure for at least 3 minutes after that.
- Time matters: A tourniquet has a clock on it. The goal is conversion to a dressing, once the criteria are met.
- Adjunct drug: TXA works only when it goes in early, by IV or IO, per protocol.
Where It Fits
Under US and military guidance (TCCC, Change 14-02), a tourniquet goes on first for life-threatening limb bleeding and for any traumatic amputation. Reserve direct pressure and packing for compressible bleeding and for sites a tourniquet can't use. The 2025 German Trauma Society guideline changes the order: manual pressure, then a pressure dressing with a hemostatic agent when one is available, then a tourniquet. Local protocol and medical direction govern. For TXA, the 2025 NAEMSP, ACEP and ACS-COT joint statement backs prehospital use in adults with clinical signs of hemorrhagic shock, after lifesaving interventions. Give it no later than 3 hours after injury.
Indications & Contraindications
Indications
- Massive or pulsatile limb bleeding that direct pressure cannot control in time, and any traumatic amputation: tourniquet
- Deep stab wounds at least 3 cm long (after any foreign body is removed), and gunshot or blast wounds with active bleeding: hemostatic packing
- Scalp wounds with active bleeding: chitosan-based dressing (per the 2025 German guideline)
- Junctional (groin or axilla) bleeding: pack and press first; a junctional tourniquet if your agency stocks one and the site suits
Absolute Contraindications
Nothing rules out the procedure when the bleeding is life-threatening and other means cannot stop it. Don't apply a tourniquet to bleeding that direct pressure controls. For TXA contraindications, see the TXA row in Medications & Settings.
Relative Contraindications & Cautions
- Minor or non-life-threatening bleeding: A tourniquet gives no benefit here. Already on? Convert it at the first opportunity.
- Unseen wound: Can't see the wound? Keep the tourniquet high and tight until you find it, then reposition it.
- Junctional sites: Pressure works less well here than on a limb. See the junctional section below.
Consider an Alternative
When a tourniquet cannot be seated, at the groin or axilla for example, pack the wound and press firmly. For vascular access during resuscitation, see IV Insertion and IO Access.
Abort / Stop Criteria
- Criteria met and bleeding stopped: Convert to a hemostatic or pressure dressing within 2 h, instead of leaving the tourniquet on.
- Any criterion not met (casualty in shock, wound cannot be monitored closely, or tourniquet controlling an amputation): keep the tourniquet on.
- Conversion fails: Don't keep retrying. Reassess at the next step of care. Try again only if conditions have clearly improved.
- Major traumatic amputation: Keep the tourniquet on until surgery. Don't attempt conversion.
Scope & Team Roles
| Provider Level | Typical Role | Notes |
|---|---|---|
| EMT | Performs | Direct pressure, pressure dressing, tourniquet and packing; confirm state scope |
| AEMT | Performs | Same skills; TXA state-dependent (per state protocol) |
| Paramedic | Performs | Adds TXA and advanced bleeding control per protocol |
| RN (ED/ICU) | Performs | Tourniquet and packing; TXA and blood products per facility protocol |
| Critical Care Transport (CFRN / CTRN / FP-C / CCP-C) | Performs | Reassessment, conversion and time tracking in transport; TXA per program protocol |
| Physician / APP | Performs | Definitive control and conversion in hospital |
Team Roles During the Procedure
- Operator: Exposes the wound, applies the tourniquet or packing, and tightens to the stop point.
- Pressure holder: Keeps pressure on the packed wound and watches for soak-through.
- Medication clinician: Gives TXA within the time window, per protocol.
- Recorder: Records the time of application, each conversion attempt, the pulse check and total TXA.
Anatomy & Landmarks
| Site | Best For | Landmark | Placement | Avoid If |
|---|---|---|---|---|
| Upper arm | Arm wounds, brachial bleeding | 2–3 in (5–7.5 cm) above the wound | On skin | Pressure controls the bleeding |
| Thigh | Leg wounds, femoral bleeding | 2–3 in above the wound | On skin; high and tight only while the wound is unseen | Pressure controls the bleeding |
| Forearm or calf | Distal limb wounds | 2–3 in above the wound | On skin | Pressure controls the bleeding |
| Groin or axilla (junctional) | Junctional wounds | Not a standard limb site | Pack and press; junctional tourniquet if the agency stocks one and the site suits | Device cannot be seated |
The wound picks the site, not your preference. The table above shows placement as TCCC and the 2025 German guideline recommend it.
Extremity Sites
- Expose the limb: Cut or remove clothing over the injury so you can see all wounds.
- Find the wound: If the wound is not visible, place the tourniquet high and tight and continue assessment.
- Position on skin: Place the band 2–3 in (5–7.5 cm) above the wound, directly on skin, not over clothing.
- Check the pulse: Tighten until bleeding stops and the distal pulse is absent.
Junctional Sites (Groin, Axilla)
- Pack the wound: Place hemostatic gauze into the cavity onto the bleeding source, as far as the wound allows.
- Press firmly: Hold direct pressure for at least 3 minutes; the 2025 German guideline notes pressure is less effective at junctional sites.
- Use a junctional tourniquet when it suits: TCCC says to apply a CoTCCC-recommended junctional tourniquet right away when the site suits it and one is ready. Use one only after training.
No tourniquet is applied to the neck. Use packing and direct pressure there.
Equipment & Preparation
Equipment
| Item | Size / Spec | Notes |
|---|---|---|
| Windlass tourniquet | CAT or SOF-T (or the agency device) | Two recommended devices in TCCC guidance; carry a second as backup |
| Hemostatic gauze | Combat Gauze (first choice); Celox Gauze or ChitoGauze if not available | Pack into the bleeding source; follow product instructions |
| Pressure dressing | Elastic or all-in-one with pressure bar | Apply over the packing |
| Junctional device | Only if on the agency list | Use a CoTCCC-recommended device where the agency stocks one; packing and pressure otherwise |
| TXA | 1 g/10 mL vial or 1 g premixed bag | See Medications & Settings |
| Marker or tape | Waterproof | Record the time of application on the device or patient |
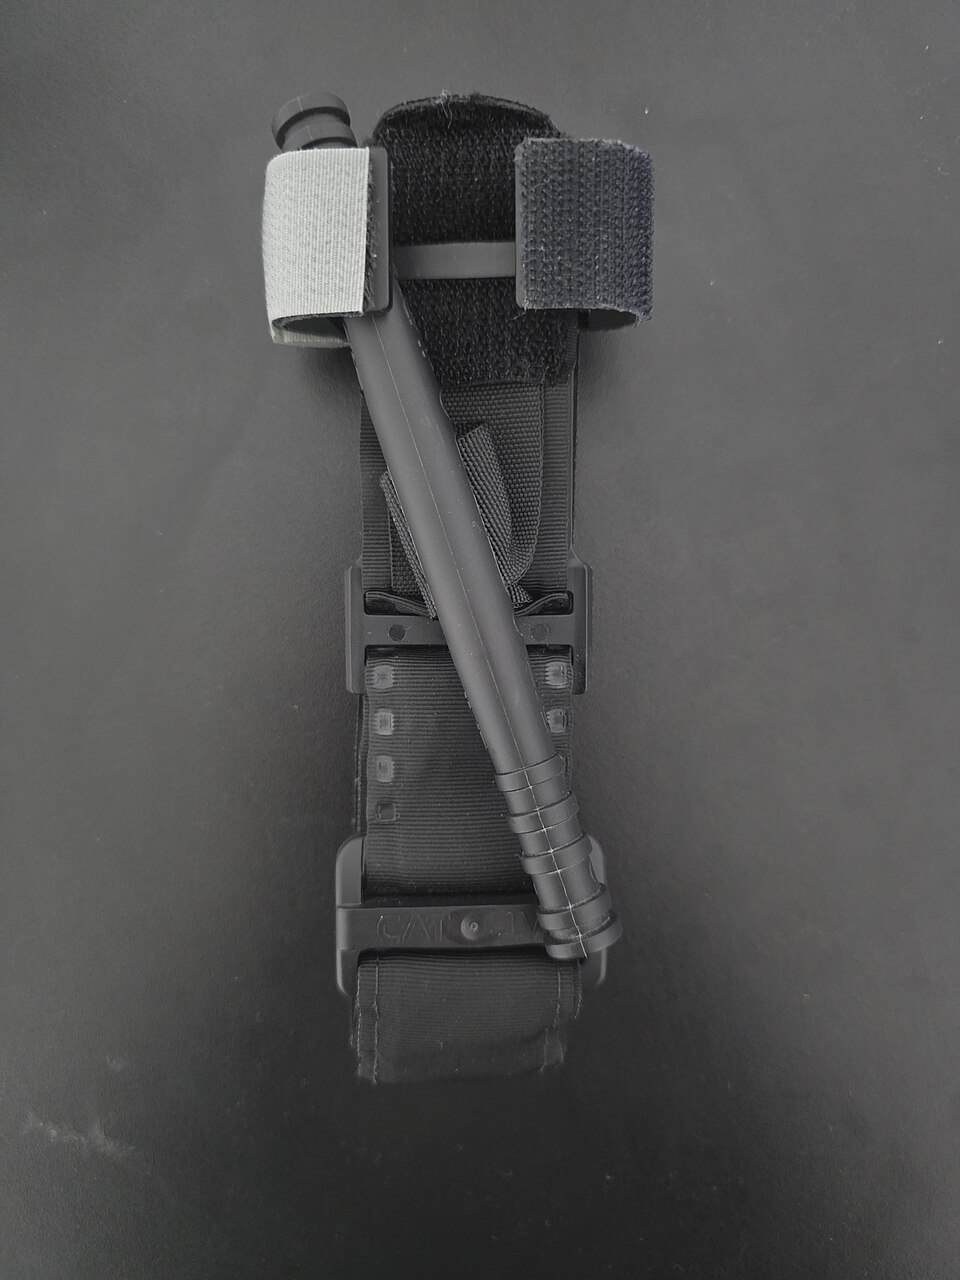
Sizing
| Patient | Device | Notes |
|---|---|---|
| Adult limb | Windlass tourniquet | Band must fit the limb; place 2–3 in above the wound |
| Child, about 2 years and older, limb 13 cm or more | CAT Gen 7 in two single-arm observational studies | Uninjured limbs, 73 children aged 2–16 years; pulses stopped in 100% of upper (71/71) and 94.5% of lower (69/73) limbs; 4 lower-limb failures (3 did not occlude after three turns, 1 withdrawn for pain); very low certainty |
Patient Positioning & Preparation
Lay the patient flat, or however the injury lets you. Open the injury up completely before you pick a site. The usual culprit is a second wound below the tourniquet. Check the limb again after each move.
Pre-Procedure Checklist
- Identify all bleeding sites and wounds
- Start direct pressure while the tourniquet is prepared
- Confirm the device and a backup are in hand
- Have hemostatic gauze and a pressure dressing open
- Note the time the bleeding started and the time of application
- Check the distal pulse, sensation and motor function before and after
Medications & Settings
Treat these doses as typical adult and pediatric references. Check them against local protocol and the current drug label.
| Drug | Adult Dose | Pediatric Dose | Onset / Duration | Notes |
|---|---|---|---|---|
| Tranexamic acid (TXA) | 1 g IV/IO over about 10 min, then 1 g infusion over 8 h in hospital EMS options (2025 joint statement): 1 g IV/IO with a hospital 1 g over 8 h; or 2 g IV/IO as infusion or slow push. Per medical direction. |
Not established (2025 joint statement); off-label regimen on the TXA page, per local protocol |
IV/IO immediate; antifibrinolytic effect about 7–8 h |
Wrong route: IV/IO ONLY. Accidental spinal or epidural injection has caused seizures, arrhythmias and death (boxed warning). Contraindications: subarachnoid hemorrhage, active intravascular clotting, hypersensitivity. Watch for seizures and thromboembolic events (label W&P 5.2). Give within 3 h of injury (Paramedic/RN/CCT, per protocol). Do not start later: no benefit, and late treatment in trauma increased bleeding deaths. |
Doses vary by protocol; follow local protocols and medical direction. Talk to the receiving facility before anyone repeats the dose. Document the time, dose and route.
Step-by-Step Procedure
Phase 1: Prepare
- Assess for all bleeding: Look for every wound before choosing a site.
- Control life-threatening limb bleeding: For pulsatile, pooling or massive limb bleeding, or any amputation, go straight to the tourniquet. For lesser bleeding, start direct pressure while the device is prepared.
- Call for help and the device: Bring the second tourniquet and packing to the patient.
Phase 2: Perform
- Apply the tourniquet: Place the band 2–3 in (5–7.5 cm) above the wound, directly on skin, and secure the strap.
- Tighten to the stop point: Turn the windlass until bleeding stops and the distal pulse is absent. Make the band as tight as possible before turning the windlass.
- Add a second tourniquet if needed: Place it side by side with the first if bleeding continues.

- Pack the wound: Open the wound and push hemostatic gauze into the cavity onto the bleeding source. Use Combat Gauze first; Celox Gauze or ChitoGauze if it is not available. Follow the product instructions.
- Hold pressure at least 3 minutes: Keep continuous direct pressure on the packing for at least 3 minutes. Do not release early to check.
- Apply a pressure dressing: Place it over the packing and wrap firmly. If blood soaks through, add a second dressing over the first rather than removing it.
Phase 3: Confirm & Secure
- Check the limb: Confirm the distal pulse is absent, and assess sensation and motor function below the device.
- Record and label: Write the time of application and device type on the patient or the device.
- Give TXA: Within 3 h of injury, IV or IO, per protocol (see Medications & Settings for the EMS options and the duplicate-dose caution).
- Check the conversion criteria: Convert within 2 h only when ALL are met: the casualty is not in shock, the wound can be monitored closely for rebleeding, and the tourniquet is not controlling an amputation. Otherwise leave it on.
Alternative Technique: Packing Without a Tourniquet
No tourniquet seats at the groin or axilla? Pack the wound with hemostatic gauze. Hold direct pressure for at least 3 minutes, then add a pressure dressing. If a junctional tourniquet is stocked and the site suits it, follow your training on use (see Anatomy & Landmarks). The 2025 German guideline found no strong recommendation for junctional devices.
Confirmation & Monitoring
Primary Confirmation
Bleeding stops and the distal pulse is not palpable. For packed wounds, bleeding does not continue through the dressing.
Secondary Confirmation
- Sensation and motor function distal to the device, checked against the other limb
- Distal blood flow, motor and sensory function assessed and monitored (2025 German guideline)
- No bleeding through the dressing
| Finding | Success | Failure / Malposition |
|---|---|---|
| Bleeding | Stopped | Bright red or spurting blood above or through the device |
| Distal pulse | Not palpable | Palpable pulse: tighten or add a second device |
| Sensation / motor | Intact or unchanged | New loss: check placement; nerve injury is possible |
| Dressing | No bleeding through | Soak-through: add a second dressing |
Ongoing Monitoring
- Every reassessment and every move: Check bleeding, pulse, sensation and motor function.
- After every move: Recheck the wound, pressure and distal findings.
- Conversion window: Start the clock at application. Convert within 2 h, and only when every criterion is met. Still on at 2 h? Document a reassessment of whether it is still needed.
Troubleshooting
| Problem | Likely Cause | Fix |
|---|---|---|
| Bleeding continues above the tourniquet | Band too loose or wrong position | Retighten; add a second tourniquet side by side |
| Pulse still palpable | Incomplete occlusion or band slipping | Retighten fully; check routing and the device instructions |
| Bleeding continues through the pressure dressing | Dressing not firm enough | Add a second pressure dressing over the first; if bleeding persists, re-pack or add a tourniquet where a limb allows; do not remove the first dressing except to re-pack |
| Bleeding returns after conversion | Dressing did not hold the wound | Re-tighten the tourniquet at once; repeat conversion only if conditions have clearly improved |
| Tourniquet is on a hidden wound | Placed before wound was found | Keep it high and tight; move it once the wound is found |
| Limb swells below the device | Venous tourniquet (band tight enough to block venous return only) | Tighten until the arterial pulse is absent |
| Junctional bleeding continues | Device cannot seal the wound | Pack deeper and press; apply a junctional tourniquet if one is available and suitable |
If Bleeding Still Continues
- Apply a second tourniquet: Side by side with the first, above the wound.
- Pack and press: Hemostatic gauze and a pressure dressing over the wound.
- Give TXA: Within 3 h of injury, per protocol.
- Move to definitive care: Keep all devices on and document the times.
Complications
| Complication | Recognition | Prevention | Management |
|---|---|---|---|
| Delayed: limb ischemia | Cold, pale or numb limb after long duration | Convert early; track time from application | Keep tourniquet on until surgery when conversion is not possible |
| Delayed: rhabdomyolysis and hyperkalemia | Rising potassium and acidosis on labs after release | Limit time; monitor after release | Treat per protocol; hospital monitoring with lab capability |
| Immediate: transient hypotension on release | Drop in blood pressure as the device is loosened | Convert in a planned, controlled step | Fluids and pressure per protocol; reassess the wound |
| Immediate: nerve palsy | New weakness or numbness at the device level | Correct position and width of the device | Document; most palsies are transient (1.7% in one series) |
| Rare: compartment syndrome | Pain out of proportion, tense limb | Limit time; avoid venous tourniquet | Hospital surgical review |
| Immediate: pain at and below the device | Severe pain, expected with a correctly tight tourniquet | Plan analgesia before application; conversion when criteria are met also reduces pain | Treat per protocol; do not loosen to relieve pain; document |
Life-Threatening Harm From a Junctional Device
Here's the trap from a 2026 case report: an abdominal aortic and junctional tourniquet came off in the trauma bay. Cardiac arrest, acidosis, compartment syndrome and organ infarcts followed. Before you take off any junctional or torso device, agree on a plan with the receiving team.
Special Populations
Pediatrics
- Tourniquet fit: Two single-arm observational studies tested uninjured limbs in 73 children aged 2–16 years. A CAT Gen 7 stopped distal pulses from about 2 years old, with limb circumference 13 cm or more (very low certainty). Four lower-limb applications failed: 3 did not occlude after three turns, and 1 was withdrawn for pain. Nothing below these ages or circumferences was tested.
- Band width: Narrow bands raise the risk of direct-pressure injury. Wider devices at lower compression pressure reduce that risk (TCCC 14-02).
- TXA: The 2025 joint statement says pediatric prehospital TXA has not been studied, and dosing is not established. Use it only per local protocol. For the off-label weight-based regimen, see the TXA page.
- Sizing and references: See Equipment Sizing, Weight-Based Dosing and Pediatric Shock.
Physiologically Difficult
- Hemorrhagic shock: Control the life-threatening bleeding first. Tourniquet for limb hemorrhage, packing and pressure elsewhere. Blood products and permissive hypotension follow protocol. TXA only within its time window.
- MARCH and xABCDE: Massive hemorrhage gets controlled first. Then airway, breathing and circulation, as in MARCH and ATLS xABCDE.
- Hypothermia: Cold worsens clotting. This is the lethal triad. Cover the patient and keep them warm. Warm fluids and blood per protocol.
- Anticoagulated or antiplatelet patients: Expect more bleeding. Tell the receiving team.
- Neck and torso: Never put a limb tourniquet on the neck or torso. Pack and press at these sites.
- Prolonged transport: Each move is a reassessment point. The tourniquet clock keeps running.
Post-Procedure Care & Transport
Immediate Aftercare
- Recheck the distal pulse, sensation and motor function after every move.
- Keep direct pressure on packed wounds for the full hold time and until surgical control. Do not lift the dressing during the hold to look; check after the hold and after every move.
Ongoing Maintenance
- Keep the tourniquet on until conversion is done in a controlled setting, or until surgery for a major traumatic amputation.
- Do not remove a tourniquet on 6 h or more outside a closely monitored setting.
- Watch for rebleeding after conversion; keep a dressing ready.
Transport Considerations
- EMS: Keep the time line running on every device; convert within 2 h only if the criteria are met.
- Transport: Reassess the limb and dressing after each move, turn or loading.
- Reassessment: Recheck pulse, sensation and motor function after each transfer.
Handoff & Documentation
Document & Hand Off
- Time of application and device type, with location
- Each conversion attempt, its criteria check and outcome; any loosening, with the reason
- Distal pulse, sensation and motor findings at each check
- Packing agent, hold time and dressing applied
- TXA time, dose and route; tell the receiving team, so no duplicate dose is given
- Total time on the device at handoff
Clinical Pearls & Pitfalls
Pearls
- Tourniquet first: Massive or pulsatile limb bleeding? Apply the tourniquet at once. Pressure and packing cover the rest.
- Convert when ready: Convert at the first opportunity once all three criteria are met. 2 hours is the limit, not the target.
- Pack deep stab wounds: Hemostatic gauze, then 3 minutes of pressure. This applies to stab wounds 3 cm or longer.
- TXA window: Within 3 h of injury, IV or IO, per protocol.
Common Pitfalls
- Tourniquet on a minor bleed: Convert at the first opportunity.
- Placed below an unseen wound: Keep it high and tight, then move it once the wound is found.
- Loosening in shock or for pain: Keep it on and treat pain per protocol.
- Repeated failed conversion: Retrying isn't recommended. Keep the device on and reassess.
- Skipping an available junctional tourniquet: Where the site suits and one is ready, apply it. Packing and pressure otherwise.
Education & Skill Maintenance
Skill Maintenance
- Practice tourniquet application: Under supervision, and regularly. An emergency shouldn't be the first time you use one.
- Timed drills: Practice a timed application and conversion with a recorder.
- Packing drills: Pack a training wound and hold direct pressure for at least 3 minutes.
- Equipment familiarization: Check the CAT or SOF-T and the backup device at every shift.
References
- Trentzsch H, Goossen K, Prediger B, Schweigkofler U, Hilbert-Carius P, Hanken H. "Stop the Bleed": prehospital bleeding control in patients with multiple and/or severe injuries: a systematic review and clinical practice guideline. Eur J Trauma Emerg Surg. 2025;51:92. https://doi.org/10.1007/s00068-024-02726-1
- Barrett WJ, Kaucher KA, Orpet RE, Campion EM, Goodloe JM, Fischer PE. Tranexamic acid in trauma: a joint position statement and resource document of NAEMSP, ACEP, and ACS-COT. J Trauma Acute Care Surg. 2025;99(3):357–363. https://doi.org/10.1097/TA.0000000000004727
- CRASH-2 Collaborators (Shakur H, Roberts I, Bautista R, et al.). Effects of tranexamic acid on death, vascular occlusive events, and blood transfusion in trauma patients with significant haemorrhage (CRASH-2). Lancet. 2010;376(9734):23–32 (landmark trial). https://doi.org/10.1016/S0140-6736(10)60835-5
- Kragh JF Jr, Walters TJ, Baer DG, Fox CJ, Wade CE, Salinas J. Survival with emergency tourniquet use to stop bleeding in major limb trauma. Ann Surg. 2009;249(1):1–7 (landmark cohort). https://doi.org/10.1097/SLA.0b013e31818842ba
- Shackelford SA, Butler FK Jr, Kragh JF Jr, et al. Optimizing the use of limb tourniquets in Tactical Combat Casualty Care: TCCC Guidelines Change 14-02. J Spec Oper Med. 2015;15(1). NAEMT TCCC change document (PDF)
- Charlton NP, Goolsby CA, Zideman DA, Maconochie IK, Morley PT, Singletary EM. Appropriate tourniquet types in the pediatric population: a systematic review. Cureus. 2021;13(4):e14474. https://doi.org/10.7759/cureus.14474
- Gerstner G, Rizzo J, Kieffer C, Lowe J. Between hemorrhage and harm: complications of the Abdominal Aortic and Junctional Tourniquet-Stabilized. Prehosp Emerg Care. 2026 (online ahead of print). https://doi.org/10.1080/10903127.2026.2725890
- Deaton TG, Drew B, Montgomery HR, Butler FK Jr. Tactical Combat Casualty Care (TCCC) guidelines: 25 January 2024. J Spec Oper Med. 2024;24(1):100–108. https://doi.org/10.55460/QT3B-XK5B
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.