

Bedside Snapshot
- Indications
- Symptomatic bradycardia with poor perfusion, not responding to atropine 1 mg
- Symptomatic high-degree AV block (Mobitz II, third-degree): atropine may fail; if it does, pacing or a drug infusion may be effective (2025 AHA Part 9, COR 2b, LOE C-LD)
- Bridge while transvenous pacing or a drug infusion is arranged
- Contraindications / Abort
- Established cardiac arrest (asystole/PEA): routine pacing not recommended (2025 AHA Part 9, COR 3: No Benefit)
- Conscious patient: give analgesia or sedation; do not delay pacing if unstable
- Pads over medication patches or skin breakdown
- No capture at 200 mA: change pads, then escalate
- Critical Steps
- Pads on, patches removed, ECG leads separate
- Rate 60–80/min; output up in steps until capture
- Set output above threshold by the protocol margin (often about 10%)
- Start infusion while pacing is set up
- Confirm & Monitor
- Wide QRS after each spike, plus a pulse at the paced rate
- BP and mental status improving
- Recheck capture after every move or sedation change
Key Numbers
Pacing has worked only when every paced spike is followed by a pulse at the paced rate. Time-critical when bradycardia is causing hypotension, altered mental status or ischemic chest pain.
| Parameter | Value |
|---|---|
| First drug | Atropine 1 mg IV/IO, repeat every 3–5 min Max 3 mg total; if ineffective, start pacing or the infusion (2025 AHA Part 9, COR 2b, LOE C-LD) |
| Infusion bridge | Dopamine 5–20 mcg/kg/min IV or epinephrine 2–10 mcg/min IV |
| Pacing rate | 60–80/min, set by protocol |
| Starting output | Lowest setting (device-dependent; the 2008 PrePACE protocol started at 5 mA), then increase in steps until capture |
| Typical capture threshold | 40–140 mA Device maximum 200 mA |
| Safety margin | Protocol-dependent; many protocols use about 10% above the mechanical-capture threshold |
| Capture check | Palpable pulse at every paced beat ECG spike plus wide QRS is not enough |
Overview & Principles
Transcutaneous pacing (TCP) sends timed current through pads on the chest to depolarize the ventricles. It holds the line for a patient with symptomatic bradycardia until a drug response or a transvenous pacemaker is in place.
How It Works
- Pacing spike: The device fires a pulse at the set rate (fixed). In demand mode, it fires only when it senses no intrinsic beat.
- Capture: Current has to beat the myocardial threshold. Thresholds usually sit at 40–140 mA, and the device tops out at 200 mA.
- Skeletal muscle: That same current also contracts the chest wall. Expect pain and twitching. Sedation is part of the procedure.
- Threshold drivers: Pad contact, beta-blockers (higher thresholds in a 2026 study) and low myocardial mass all change how much current it takes.
Where It Fits
The 2025 AHA adult bradycardia algorithm puts atropine first for bradycardia with poor perfusion (Part 9, COR 2a, LOE B-NR). Atropine may be ineffective in Mobitz II or complete heart block, and when it fails, escalation should not wait. If the bradycardia still does not respond, TCP and/or a dopamine or epinephrine infusion can bridge the gap while transvenous pacing and expert help are arranged (Part 9, COR 2b, LOE C-LD). Transvenous pacing is reasonable for persistent unstable bradycardia that is refractory to medical therapy (COR 2a, LOE C-LD). In a denervated transplanted heart, atropine is likely to be ineffective, so if it fails, don't hold up pacing or the infusion.
The 2008 PrePACE feasibility trial was not powered for survival. Survival to discharge or 30 days was 70% with dopamine and 69% with TCP.
Indications & Contraindications
Indications
- Symptomatic bradycardia with poor perfusion: hypotension, altered mental status, ischemic chest pain, acute heart failure or shock, unresponsive to atropine
- Symptomatic high-degree AV block: Mobitz II or third-degree block with poor perfusion. Atropine may be ineffective. When it fails, escalate without delay. No IV/IO access and an unstable patient? Immediate pacing may be considered (2025 AHA Part 9, COR 2b, LOE C-EO)
- Bridge: Use it while transvenous pacing, a drug infusion or definitive treatment is being arranged
- Bradycardia from toxic exposure: A bridge only. Toxin-specific therapy comes first (see Special Populations)
Absolute Contraindications
- Asystole or pulseless electrical activity (PEA): Routine pacing is not recommended in an established adult cardiac arrest (2025 AHA Part 9, COR 3: No Benefit, LOE B-R). For pediatric pacing, see Special Populations
Relative Contraindications & Cautions
- Conscious patient without analgesia or sedation: pacing is painful
- Hypotension and sedation: Use the lowest effective sedative dose. Keep airway support ready
- Implanted pacemaker or ICD: Keep pads away from the generator. Follow device guidance and local protocols
- Skin damage or medication patches under pad sites: Skin damage, or a patch under a pad site, raises burn risk. Remove the patch
Consider an Alternative
- Atropine: It is the first drug for bradycardia with poor perfusion (2025 AHA Part 9, COR 2a, LOE B-NR). If atropine fails, don't hold up pacing or the infusion. It is likely to be ineffective in a denervated transplanted heart. See the atropine page
- Infusions: dopamine or epinephrine, used as a bridge while pacing is set up
Scope & Team Roles
| Provider Level | Typical Role | Notes |
|---|---|---|
| EMT | Not in scope | Assists with pads and monitoring only if the agency protocol allows |
| AEMT | Not in scope | State and agency scope varies; confirm locally |
| Paramedic | Performs (protocol/credentialing required) | Pacing is a protocol skill; confirm credentialing and recertification |
| RN (ED/ICU) | Performs (protocol/credentialing required) | Often ACLS-trained RN with physician order; sedation support per policy |
| Critical Care Transport (CFRN / CTRN / FP-C / CCP-C) | Performs (protocol/credentialing required) | Reassess capture after every move; the flight environment adds noise and vibration |
| Physician / APP | Performs | Directs sedation, infusion choice and transvenous pacing |
Team Roles During the Procedure
- Operator: sets mode, rate and output; calls each step
- Pulse checker: palpates the pulse at every paced beat and calls it aloud
- Sedation and airway clinician: titrates analgesia and sedation; watches SpO₂ and airway
- Monitor reader: watches the ECG for spike-to-QRS pairs and sensing problems
- Recorder: notes time, current at capture, rate, BP, sedation and drugs
Pre-Procedure Assessment
Physiologic Risk
- Poor perfusion: SBP under 90 mmHg (the stability cut-off used in a 2026 pacing study), altered mental status, ischemic chest pain or acute heart failure
- Rhythm: confirm the bradycardia on a rhythm strip and look for high-degree AV block or sinus arrest; confirm that the rhythm is not asystole
- Airway and breathing: Check SpO₂ and work of breathing. Hypoxia and acidosis raise the risk of failure
Site / Device Check
- Skin: dry, intact skin at both pad sites; clip excess hair (do not shave)
- Patches: identify and remove medication patches (for example nitroglycerin or fentanyl)
- Implanted device: ask about a pacemaker or ICD; keep pads away from the generator
- Pads: check the expiration date and that the pads are compatible with the device
Anatomy & Landmarks
Pad position follows the pad package and your local protocol. Two positions are in common use: anteroposterior (AP) and anterolateral (AL). A 2026 study found no significant difference in capture thresholds between them (median 125 mA AP versus 140 mA AL). No guideline gives an evidence-based preference. Polarity is device-specific too, so check the pad package and the device manual.
| Position | Placement | Use When |
|---|---|---|
| Anteroposterior (AP) | Anterior pad over the left precordium, away from the sternum; posterior pad on the back under the heart | Often the first choice for pacing; a common protocol default |
| Anterolateral (AL) | Anterior pad right infraclavicular; apex pad on the left lateral chest | Use if AP is not possible or pads are already in place for defibrillation |
Equipment & Preparation
Equipment
- IV/IO access: at least one line, two large-bore preferred, for atropine, infusion and sedation
- Pacing-capable monitor or defibrillator: pacing mode, rate and current display
- Pacing/defibrillation pads: adult or pediatric size per device guidance; check expiration
- ECG leads: separate from the pads for a clean rhythm trace
- Monitoring: SpO₂, non-invasive BP (cycled every few minutes), EtCO₂ if available; arterial line if already placed
- Sedation and analgesia: per local protocol (see Medications & Settings)
- Airway: bag-mask, suction, oxygen and intubation supplies ready
- Infusion: dopamine or epinephrine infusion prepared and labeled
Patient Positioning & Preparation
Lay the patient supine or semi-recumbent. Dry and clip the chest, and remove medication patches. Expose both pad sites and keep clothing off the chest.
Pre-Procedure Checklist
- Indication: bradycardia with poor perfusion, confirmed
- Atropine 1 mg IV/IO given or underway (2025 AHA Part 9). If it fails, don't hold up pacing or the infusion
- Pads on in the chosen position, patches off
- ECG leads separate, SpO₂ and BP cuff on
- Sedation and analgesia planned, airway equipment at hand
- Dopamine or epinephrine infusion prepared
- Transvenous pacing or cardiology notified as needed
Medications & Settings
Pediatric doses come from three sources, checked in this order: AHA/AAP 2025 if it states a dose, then the NASEMSO National Model EMS Clinical Guidelines v3.0 (2022), then the US label. If none of them gives a dose, this page shows none. A pediatric maximum never goes above the adult maximum dose (NASEMSO Universal Care Guideline, p. 13). Unless a dose is marked labeled, it is off-label.
| Drug | Adult Dose | Pediatric Dose | Onset / Duration | Notes |
|---|---|---|---|---|
| Atropine | 1 mg IV/IO, every 3–5 min Max 3 mg | 0.02 mg/kg IV/IO (minimum 0.1 mg; max single dose 0.5 mg; may repeat once) for increased vagal tone or AV block (2025 AHA PALS bradycardia algorithm) Over 40 kg or over 14 yr: adult dose, 1 mg IV every 3–5 min, max 3 mg (NASEMSO Universal Care p. 13; Bradycardia p. 36) | IV/IO: onset within minutes; duration not defined in labeling | First drug in adults (2025 AHA Part 9 algorithm). Atropine 0.5 mg steps are outdated. May be ineffective in Mobitz II or complete block; if so, do not delay pacing. A denervated transplanted heart does not respond. Response is poor in some toxic bradycardia. |
| Dopamine | 5–20 mcg/kg/min IV infusion, titrated to heart rate and BP Infusion only | Not established in children in the sources reviewed; specialist use only | IV infusion: onset within about 5 min; effect ends within about 10 min of stopping | High-alert Dose per the 2025 AHA Part 9 adult bradycardia algorithm. Infusion only: no push-dose form. Confirm mcg/kg/min, not mcg/min. Give into a large vein (central or large proximal line preferred) and check the site often. Extravasation causes tissue ischemia and necrosis: infiltrate phentolamine 5–10 mg in 10–15 mL saline (adult label dose) as soon as possible. |
| Epinephrine infusion | 2–10 mcg/min IV infusion, titrated to response | Not established in children; no pediatric infusion dose in the 2025 AHA PALS algorithm. Specialist use only | IV infusion: titrate to response; effect wears off soon after stopping | High-alert Dose per the 2025 AHA Part 9 adult bradycardia algorithm. Titrated infusion, not a bolus. Push-dose epinephrine is a separate hypotension technique and is not the bradycardia dose. Needs a secure line; use the protocol's standard concentration and confirm pump settings in mcg/min. |
| Isoproterenol | Specialist or cardiology-directed infusion only. No numeric dose on this page: the current US label covers shock (0.5–5 mcg/min) and bronchospasm, not heart block | Not established in children: specialist use only | IV: immediate; effect fades within minutes | High-alert Off-label for bradycardia. Label contraindications: tachycardia, ventricular arrhythmias, angina. Can induce arrhythmias and ischemia; use only when these are absent and ischemia is unlikely. |
| Midazolam | Titrate in small increments per protocol. The 2008 PrePACE trial protocol used 0.03 mg/kg as the initial dose (trial protocol, not a standard dose) | Per pediatric sedation protocol | See the midazolam page | High-alert Boxed warning: with opioids, profound sedation, respiratory depression, coma and death. Hypotension and airway depression: monitor continuously. |
| Fentanyl | Small IV increments titrated to effect per protocol. Label adjunct dose when more analgesia is needed: 50–100 mcg IV over 1–2 min (labeled for anesthesia adjunct use) | Per pediatric protocol | See the fentanyl page | High-alert Opioid: respiratory depression, worse with midazolam (boxed warning). Titrate slowly, reassess breathing after each dose, and keep bag-mask and an opioid reversal agent ready. |
| Ketamine | Analgesic or sedative dose titrated per protocol | Per pediatric protocol | See the ketamine page | Label: increases BP, HR and cardiac output, but decreases in BP and HR and arrhythmias have also been seen. Label doses are induction doses, not TCP doses. |
Pacing Settings
| Setting | Adult | Pediatric | Notes |
|---|---|---|---|
| Mode | Demand if an intrinsic rhythm is present; fixed if no intrinsic rhythm or if oversensing | Same principle | Set on the device |
| Rate | 60–80/min (a 2008 prehospital protocol used 80) | Per pediatric protocol | Set by protocol and perfusion response |
| Output | Start at the lowest setting (the minimum varies by device; the 2008 PrePACE protocol started at 5 mA); increase until capture; typical threshold 40–140 mA; max 200 mA | Per device and pediatric protocol | Threshold rises with beta-blockers and low myocardial mass |
| Safety margin | Protocol-dependent; many protocols use about 10% above the mechanical-capture threshold | Per protocol | Keeps capture through movement |
Step-by-Step Procedure
Phase 1: Prepare
- Confirm the indication: bradycardia with poor perfusion. Give atropine 1 mg IV/IO while pads are placed (2025 AHA Part 9). If it fails, start pacing and the infusion without delay. With no IV/IO access and instability, immediate pacing may be considered in high-degree AV block (COR 2b, LOE C-EO).
- Apply monitoring: ECG leads separate from the pads; SpO₂, BP cuff and EtCO₂ if available.
- Place pads: choose AP or AL per the pad package and protocol. Remove patches first; press the pads down firmly so there is no air under them.
- Sedate and analgesia: if the patient is conscious, give analgesia and sedation per protocol. Ketamine is a common option and can raise BP; midazolam and fentanyl can lower BP and depress breathing. Keep airway support ready.
Phase 2: Perform
- Select mode and rate: demand if an intrinsic rhythm is present, fixed if not. Set the rate to 60–80/min per protocol.
- Increase output: start at the lowest setting and raise it in steps until each spike is followed by a wide QRS.
- Confirm mechanical capture: palpate a pulse at every paced beat (site per your protocol) and confirm it matches the paced rate. Check BP.
- Set the safety margin: once capture is confirmed, raise output above the threshold by the protocol margin (often about 10%).
- Start the infusion: if capture is not achieved, or while pacing is being set up, start dopamine (5–20 mcg/kg/min) or epinephrine (2–10 mcg/min) per protocol.
Phase 3: Confirm & Secure
- Reassess: BP, mental status, perfusion and SpO₂ within minutes of capture.
- Secure pads and leads: tape or hold the pads; keep the patient still and sedated enough to limit muscle artifact.
- Hand off: request transvenous pacing or cardiology, and record the settings (see Confirmation & Monitoring).
Confirmation & Monitoring
Primary Confirmation
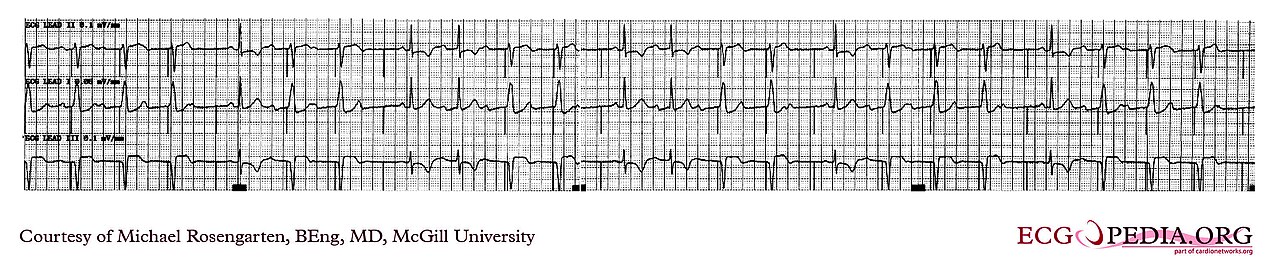
A palpable pulse at the paced rate, on every paced beat, confirms mechanical capture. Improving BP and mental status back it up. An ECG spike followed by a wide QRS is electrical capture, and nothing more.
Electrical capture often does not hold. In a 2026 multicenter cohort of 299 prehospital patients (about a third post-ROSC; median pre-TCP rate 38/min), 9.7% had sustained electrical capture. Sustained meant a wide QRS with a T wave after each pacer impulse for at least 90% of 60 seconds. The pulse check is the endpoint you can count on.
Secondary Confirmation
- SpO₂ or arterial waveform: pulsatile at the paced rate
- BP: higher systolic pressure after capture
- Mental status and skin: improved alertness and warmer, better-perfused skin
| Finding | Success | Failure / Malposition |
|---|---|---|
| ECG | Spike followed by wide QRS and T wave | Spike with no QRS |
| Pulse | Present at every paced beat, matching rate | Absent, or not matching the paced rate |
| Blood pressure | Improving or stable | Remains low |
| Mental status | Improving | Unchanged or worse |
| Muscle twitching | Present with capture | Present without capture; not a capture sign |
Ongoing Monitoring
- Continuous ECG: watch for spike-to-QRS pairs and sensing problems
- Pulse and BP: recheck at least every few minutes, per local protocol
- Capture check: after every move, sedation dose, rate change or pad change
- Skin under pads: check for burns or blistering
Troubleshooting
| Problem | Likely Cause | Fix |
|---|---|---|
| Spikes with no QRS | Output below threshold; poor pad contact | Increase output in steps; press pads down; check skin and patches; reposition to AP or AL |
| Wide QRS but no pulse | False electrical capture or PEA | Check the pulse at each paced beat; if no pulse, treat as PEA with CPR per ACLS |
| Intermittent capture | Output near threshold; movement; sedation level | Raise output above threshold; secure pads; reduce movement with sedation |
| No capture at 200 mA | Pad or cable fault; high threshold | New pads; check cable connections; reposition; start infusion; prepare transvenous pacing |
| Oversensing (pacer inhibits) | Artifact or noise sensed as beats | Switch to fixed mode; improve lead placement; reduce movement |
| Undersensing (competes with native beats) | Native beats not sensed | Increase sensitivity; reposition ECG leads; watch for spikes landing on the T wave |
| High threshold | Acidosis, hypoxia, hyperkalemia, pericardial effusion or tamponade, pneumothorax, ischemia, beta-blockers | Treat the cause per protocol: oxygenation and ventilation, correct acidosis and hyperkalemia, drain tamponade or tension pneumothorax; then re-check capture |
If Capture Cannot Be Achieved
- Infusion: start dopamine 5–20 mcg/kg/min or epinephrine 2–10 mcg/min per protocol
- Transvenous pacing: request it now; TCP is a bridge, not the end of care
- Expert help: notify cardiology or the medical director per protocol
Complications
| Complication | Recognition | Prevention | Management |
|---|---|---|---|
| Immediate: pain and agitation | Chest wall contraction, movement, distress | Analgesia and sedation before pacing | Titrate sedation per protocol; keep airway support ready |
| Immediate: hypotension from sedation | BP falls after a sedative dose | Lowest effective dose; choose the agent per protocol (ketamine raises BP in most patients but can lower it) | Stop titration; support BP per protocol; airway support |
| Delayed: skin burn or blistering | Red, blistered or burned skin under pads | Remove patches; dry and clip the skin; firm pad contact | Move pads to fresh skin; wound care per local protocol |
| Delayed: arrhythmia or R-on-T | Pacing spike on the T wave; new ventricular ectopy | Check sensing; avoid high output | Adjust sensing; treat arrhythmia per ACLS |
| Rare: device interference | Device malfunction after pacing near a generator | Keep pads away from the generator | Device clinic check per local protocol |
Pulseless Patient During Pacing
Electrical activity with no pulse is PEA. Begin CPR and run the ACLS PEA pathway. Spikes do not count as cardiac output.
Special Populations
Pediatrics
- Indication: if HR is under 60/min with cardiopulmonary compromise despite effective ventilation with oxygen, start CPR (2025 AHA Part 8, COR 1, LOE C-EO). Emergency transcutaneous pacing may be considered for infants and children with bradycardia and cardiopulmonary compromise due to complete heart block or sinus node dysfunction unresponsive to CPR (2025 AHA Part 8, COR 2b, LOE C-EO). Data are limited
- Asystole and PEA: AHA makes no pacing recommendation for pediatric cardiac arrest (2025 AHA Part 8). Treat hypoxia and other correctable causes first (2025 AHA Part 8). In adult arrest, routine pacing is not recommended (2025 AHA Part 9, COR 3: No Benefit, LOE B-R)
- Parameters: The 2025 AHA pediatric guidance cites limited data and gives no pad size, rate or output. Follow the pediatric protocol and device guidance
- Drugs: atropine 0.02 mg/kg IV/IO (minimum 0.1 mg, max single dose 0.5 mg, may repeat once) for increased vagal tone or AV block (COR 1, LOE C-LD). Over 40 kg or over 14 yr: adult dose, 1 mg IV every 3–5 min, max 3 mg (NASEMSO Universal Care p. 13; Bradycardia p. 36). Epinephrine 0.01 mg/kg IV/IO (0.1 mL/kg of 1:10,000; max 1 mg) if bradycardia with compromise persists after correction of other factors such as hypoxia (COR 1, LOE C-EO). Source: 2025 AHA PALS bradycardia algorithm and Part 8
Go deeper on the pediatric side: Pediatric Cardiac Arrest, Weight-Based Dosing, Broselow and Vascular Access.
Implanted Devices
- Keep pads away from the implanted generator
- Notify the device clinic after pacing, per local protocol
Obesity
- Capture may take higher output
- If you can, press the pads down firmly
Hypothermia
- Hypothermia is a reversible cause of bradycardia. For life-threatening hypothermia, full resuscitation with concurrent rewarming is recommended (2025 AHA Part 10, COR 1, LOE C-LD adults; C-EO children)
- Severe hypothermia (core below 30 °C): pulse and respiratory rates may be slow or hard to find, and the ECG can show asystole. AHA gives no pacing advice for hypothermic bradycardia. Follow the hypothermia protocol
Toxicology
- Beta-blocker, calcium channel blocker, digoxin: atropine and pacing have variable effectiveness in cardiac glycoside (digoxin) poisoning (2025 AHA Part 10). AHA Part 10 gives no atropine or pacing recommendation specific to beta-blocker or CCB poisoning. Calcium is reasonable in life-threatening CCB poisoning (2025 AHA Part 10, COR 2a, LOE C-EO) and may be reasonable in life-threatening beta-blocker poisoning (COR 2b, LOE C-EO); dose per the calcium chloride page. Give other toxin-specific therapy early per toxicology protocol: digoxin immune Fab for life-threatening digoxin poisoning (COR 1, LOE B-NR); high-dose insulin for hypotension in CCB poisoning (COR 1, LOE B-NR) and for vasopressor-refractory hypotension in beta-blocker poisoning (COR 1, LOE C-LD); glucagon for symptomatic bradycardia or hypotension in beta-blocker poisoning (COR 2a, LOE C-LD). Contact the regional poison center. Other doses are not given here.
- Isoproterenol is specialist-only for bradycardia; see the isoproterenol page
Post-Procedure Care & Transport
Immediate Aftercare
- Leave the pads on and the leads connected. Keep the pacing mode and output as they are unless you find a problem
- After sedation, and again after any change to the infusion, recheck pulse and BP
- Keep airway support on hand until the sedation wears off, per protocol
Ongoing Maintenance
- Recheck capture at each reassessment. Drugs such as beta-blockers can raise the threshold
- Watch the skin under the pads. Move or remove pads only with a fresh capture check
Transport Considerations
- Secure pads and leads before moving the patient
- Recheck capture after every move. Movement can change pad contact and sensing
- In the aircraft or ambulance, trust the pulse check and BP over the spike alone. Noise and vibration can hide the QRS
Document & Hand Off
- Log when pacing started and stopped, and each atropine dose with its time
- Mode, rate and output at capture, the threshold, and the safety-margin output
- How capture was confirmed (pulse at the paced rate), and the BP response
- Each sedative and analgesic, with dose and time
- Infusion drug, rate and start time
- Complications, skin under the pads included, and the transvenous pacing request
Clinical Pearls & Pitfalls
Pearls
- Pulse is the endpoint: A pulse on every paced beat, matching the rate, is what defines capture
- Atropine first (adult): give 1 mg IV/IO and repeat every 3–5 min, max 3 mg, while pads go on (2025 AHA Part 9 algorithm); if it fails, pace without delay
- Infusion bridge: dopamine 5–20 mcg/kg/min or epinephrine 2–10 mcg/min can be running while TCP is set up
- Plan for transvenous pacing: TCP is a bridge from the start
- Sedation before the first spike: Pacing hurts, and movement breaks capture
Common Pitfalls
- Muscle twitching taken as capture → Capture is not proven until you feel a pulse on every paced beat
- Wide QRS on the monitor with no pulse → It is PEA. Start CPR per ACLS
- Pacing asystole → Not indicated. Routine pacing in an established adult cardiac arrest is not recommended (2025 AHA Part 9, COR 3: No Benefit, LOE B-R)
- Dopamine given as a push dose → Dopamine is infusion only. Use the infusion pathway
- Waiting on atropine after it has failed → Once atropine has failed, start TCP or the infusion now
- Pads over medication patches → Take the patches off first. Burn risk
Education & Skill Maintenance
Skill Maintenance
- Practice capture recognition: spike-to-QRS pairs versus spikes without QRS
- Rehearse the pulse-check call at every paced beat with a partner
- Run the mode, rate and output sequence on a simulator at least once per quarter, per agency policy
- Debrief each real or simulated case: time to capture, sedation and infusion timing
References
- Wigginton JG, Agarwal S, Bartos JA, et al. Part 9: Adult Advanced Life Support: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16_suppl_2):S538–S577. https://doi.org/10.1161/CIR.0000000000001376; 2025 AHA Guidelines for CPR and ECC, Part 9 online: https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/adult-advanced-life-support
- Deep V, Vinayak PS, Ramachandra K. Anesthetic considerations for non-cardiac surgeries in orthotopic heart transplant recipients. Saudi Journal of Anaesthesia. 2023;17(1):104–106. https://doi.org/10.4103/sja.sja_474_22
- Smida T, Kimbrell JM, Kreinbrook JA, et al. The prevalence of sustained electrical capture during prehospital transcutaneous pacing: a multicenter observational study. Resuscitation. 2026;219:110934. https://doi.org/10.1016/j.resuscitation.2025.110934
- Goldschmied A, Sigle M, Toskas I, et al. Anteroposterior versus anterolateral pacer pad position in patients with symptomatic bradycardia. Int J Cardiol Heart Vasc. 2026. https://doi.org/10.1016/j.ijcha.2025.101857
- Morrison LJ, Long J, Vermeulen M, et al. A randomized controlled feasibility trial comparing safety and effectiveness of prehospital pacing versus conventional treatment: PrePACE (feasibility RCT). Resuscitation. 2008 Mar. https://doi.org/10.1016/j.resuscitation.2007.08.008
- 2025 American Heart Association Guidelines for CPR and ECC, Part 8: Pediatric Advanced Life Support, including the 2025 PALS Bradycardia With a Pulse algorithm. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/pediatric-advanced-life-support
- KETALAR (ketamine hydrochloride) injection, prescribing information. U.S. Food and Drug Administration; revised 03/2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/016812s057lbl.pdf
- 2025 American Heart Association Guidelines for CPR and ECC, Part 10: Adult and Pediatric Special Circumstances of Resuscitation (poisoning and hypothermia). https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/adult-and-pediatric-special-circumstances-of-resuscitation
- NASEMSO National Model EMS Clinical Guidelines, Version 3.0. National Association of State EMS Officials; March 2022 (Cardiovascular: Bradycardia, pp. 35–37; Universal Care Guideline, p. 13). https://nasemso.org/docs.ashx?id=1444322
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.