

Bedside Snapshot
- Indications
- Stable, regular, narrow-complex tachycardia (AVNRT, AVRT)
- Adults first; the trial excluded AF and flutter
- Before adenosine, when the patient is stable
- Contraindications / Abort
- Unstable: hypotension, altered mental status, chest pain, heart failure. Cardiovert.
- Irregular or wide-complex rhythm
- Patient deteriorates during the maneuver: stop
- Critical Steps
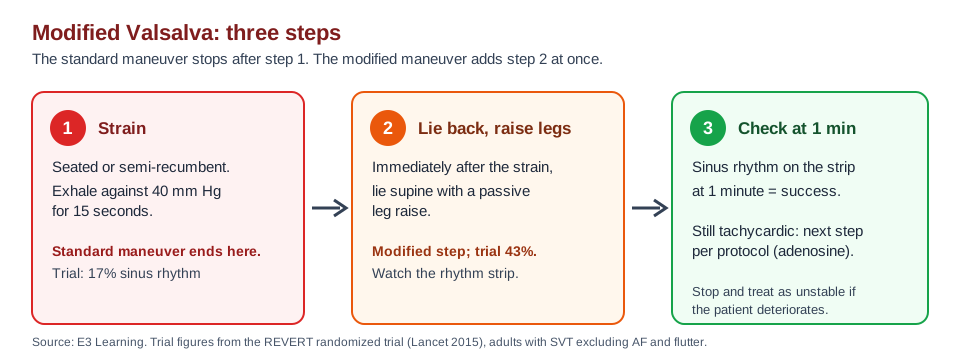
- Strain 15 s at 40 mm Hg
- Lie supine, legs raised, immediately after the strain
- Read the strip at 1 min
- Confirm & Monitor
- Sinus rhythm on the strip at 1 min
- BP and SpO₂ before, during and after
- Adenosine 6 mg, then 12 mg if still SVT
Key Numbers
Vagal maneuvers slow AV-node conduction and can end AVNRT or AVRT. In the REVERT trial, the modified maneuver returned sinus rhythm in 43% of adults vs 17% with the standard maneuver at 1 minute.
| Parameter | Value |
|---|---|
| Strain | 15 s at 40 mm Hg, as tested in REVERT. Use the pressure device or method your protocol specifies. |
| Position change | Immediately after the strain: lie supine and raise the legs (passive leg raise) |
| Success check | Sinus rhythm on a rhythm strip at 1 min after the maneuver (the REVERT primary outcome) |
| Conversion (REVERT) | Modified 43% (93 of 214) vs standard 17% (37 of 214); adjusted OR 3.7 |
| Eligible rhythm | Stable, regular narrow-complex tachycardia. Not AF or flutter (excluded from REVERT) |
| Adult adenosine if no conversion | 6 mg rapid IV/IO push, then 12 mg in 1–2 min (max 12 mg per dose; label allows one more 12 mg) |
| Unstable tachycardia | Synchronized cardioversion, not vagal maneuvers: initial energy per protocol (commonly 100 J for narrow-complex tachycardia) |
| Infants and children | PALS SVT technique and pathway per protocol; see Pediatric Tachycardia and SVT |
Overview & Principles
A vagal maneuver pushes up parasympathetic (vagal) tone at the AV node, and the node slows down. In AVNRT or AVRT, that can break the re-entry circuit (AVRT here includes orthodromic AVRT in WPW). Use it as a first step in a stable patient. It is not a treatment for AF or flutter.
How It Works
- Strain: the patient breathes out hard against a closed airway. Intrathoracic pressure climbs, and that reflex slows AV conduction.
- Release: pressure drops and the vagal brake comes off. The modified version raises the legs at that same moment to boost venous return.
- Result: if it works, the re-entry rhythm stops. You see an abrupt return to sinus rhythm on the strip.
Where It Fits
Stable and regular, narrow complex: vagal maneuver first, then adenosine. Still in SVT? Move to the AV-nodal blockers on their own pages. Unstable? Cardiovert.
| Maneuver | Strain | After the strain | Sinus rhythm at 1 min |
|---|---|---|---|
| Standard Valsalva | 15 s at 40 mm Hg, semi-recumbent | Remain semi-recumbent | 17% (37 of 214) |
| Modified Valsalva | 15 s at 40 mm Hg, semi-recumbent | Lie supine, passive leg raise immediately | 43% (93 of 214) |
Indications & Contraindications
Indications
- Stable regular narrow-complex tachycardia: AVNRT or orthodromic AVRT on a regular rhythm with a narrow QRS.
- Adults first: REVERT enrolled adults with SVT. AF and flutter were left out.
Absolute Contraindications
- Unstable patient: hypotension, altered mental status, ischemic chest pain or acute heart failure with the tachycardia. Cardiovert instead.
- Irregular or wide-complex tachycardia: don't use the maneuver on it. Wide and regular is VT until proven otherwise.
Relative Contraindications & Cautions
- Cannot follow the strain instruction: use the protocol's alternative for that patient.
- Pre-excited rhythm (WPW) with AF: no AV-nodal blockers. A vagal maneuver doesn't treat pre-excited AF.
Scope & Team Roles
| Provider Level | Typical Role | Notes |
|---|---|---|
| EMT | Performs (protocol/credentialing required) | Often taught as a stable-patient maneuver; some systems keep it with ALS. Confirm local scope. |
| AEMT | Performs (protocol/credentialing required) | Pairs with adenosine decisions under the local protocol. |
| Paramedic | Performs | Owns the 12-lead, the drug decision and the cardioversion decision. |
| RN (ED/ICU) | Assists | Monitor, time, and prepare the drug under order. |
| Critical Care Transport | Performs (protocol/credentialing required) | Same drug and cardioversion decisions in transport; watch for hypotension. |
| Physician / APP | Performs | Sets the order set and handles refractory or unusual rhythms. |
Team Roles During the Procedure
- Operator: explains the maneuver, coaches the strain and leads the leg raise.
- Monitor reader: watches the rhythm strip and calls the time of the release.
- Medication clinician: prepares adenosine with a flush and a second check of the dose.
- Recorder: documents the time, pressure and response.
Pre-Procedure Assessment
Rhythm Check
- Regular and narrow: the usual target. Confirm with a 12-lead where the protocol allows it.
- Irregular: not a vagal maneuver candidate. Treat per the atrial fibrillation pathway.
- Wide: treat it as VT unless proven otherwise. Adenosine only for a regular monomorphic rhythm, under expert guidance or protocol. No other AV-nodal blocker (verapamil, diltiazem, beta-blocker).
Physiologic Risk
- Hypotension: SBP <90 mmHg with the tachycardia is an unstable pattern. Cardiovert.
- Mental status and chest pain: either one pushes you toward cardioversion.
- Baseline: record SpO₂ and blood pressure before the maneuver. Without them, a later change is hard to see.
Equipment & Preparation
Equipment
- Cardiac monitor: continuous ECG with a rhythm strip you can save or print.
- 12-lead ECG: when the protocol allows, before the maneuver.
- Pulse oximeter and blood pressure cuff: baseline and during the maneuver.
- Defibrillator with pads: set for synchronized cardioversion and ready for the unstable path.
- Adenosine: 6 mg and 12 mg rapid-bolus vials with a saline flush, per your stock.
- Pressure device: the manometer or other method your protocol uses to hold the strain near 40 mm Hg.
Patient Positioning & Preparation
- Start semi-recumbent: sitting up, upper body reclined, so the leg raise can be done immediately.
- Explain the sequence: blow out against the closed mouth and nose for 15 seconds, then lie back as directed.
Pre-Procedure Checklist
- Monitor on and rhythm strip running
- Stable: confirm no hypotension, altered mental status, chest pain or heart failure
- Regular narrow-complex rhythm confirmed on the strip or 12-lead
- Baseline heart rate, BP and SpO₂ recorded with the time
- Patient instructed; cannot-strain alternative known
- Defibrillator and pads in reach
- Adenosine drawn up or in reach with a flush
- Time of maneuver start written down
Medications & Settings
Typical adult and pediatric references only. Verify them against local protocol and current drug labeling. Doses vary by protocol; follow local protocols and medical direction.
| Drug | Adult Dose | Pediatric Dose | Onset / Duration | Notes |
|---|---|---|---|---|
| Adenosine | 6 mg rapid IV/IO push over 1–2 s, then a rapid NS flush; if no conversion in 1–2 min, 12 mg; may repeat 12 mg once max 12 mg per dose |
0.1 mg/kg rapid IV/IO push, then 0.2 mg/kg max 6 mg, then max 12 mg |
Seconds / under 1 min |
Rapid push: use a flush and run a rhythm strip during every push. Transient asystole and flushing are expected. |
| Synchronized cardioversion (unstable only) | Narrow-complex tachycardia: initial energy per protocol (commonly 100 J synchronized) |
0.5–1 J/kg, then 2 J/kg |
Immediate |
See Synchronized Cardioversion. Re-engage SYNC before each shock. |
| Second-line AV-nodal blockers | Diltiazem, verapamil or metoprolol per their pages if adenosine fails |
Not established or specialist use in infants: see the medication pages |
See each page |
Only for a regular narrow tachycardia without pre-excitation. Avoid in hypotension, decompensated heart failure or reduced EF (diltiazem and verapamil; metoprolol is contraindicated in decompensated HF). Do not give a beta-blocker and a calcium channel blocker together or within a few hours. Check BP after the dose. |
Adenosine Cautions
- Contraindicated: second- or third-degree AV block, or sick sinus syndrome, without a pacemaker (FDA label).
- Avoid: asthma or bronchospasm (FDA label).
- Central line or heart transplant: the label dosing is for peripheral IV. Central venous use has not been systematically studied. Some protocols start lower, at 3 mg here. Follow your protocol.
- Interactions: caffeine and theophylline blunt the effect. Dipyridamole boosts it, so a smaller dose may be enough. Carbamazepine can deepen heart block (FDA label).
Full list: Adenosine.
Step-by-Step Procedure
Phase 1: Prepare
- Confirm the rhythm and stability: regular, narrow, and no hypotension, altered mental status, chest pain or heart failure.
- Record the baseline: rate, BP, SpO₂ and the time on the strip.
- Position the patient: sitting semi-recumbent, with the legs ready to lift.
- Explain the maneuver: one long, forced breath out for 15 seconds, then lie back as you direct.
Phase 2: Perform
- Start the strain: the patient exhales against a closed airway, holding about 40 mm Hg for 15 seconds.
- Lie back and raise the legs immediately: do not wait after the strain ends.
- Watch the strip: keep the rhythm running through the minute.
Phase 3: Confirm & Secure
- Read the rhythm at 1 minute: sinus rhythm is success. Record the time.
- If still tachycardic: go to adenosine per protocol (6 mg, then 12 mg in adults).
- Reassess after each step: rate, BP and rhythm, and stop for any new hypotension.
Alternative Technique: Infants and Children
Many children and infants can't perform the strain. This page doesn't give a pediatric vagal technique. Use the protocol-approved maneuver in your PALS SVT algorithm (see Pediatric Tachycardia and SVT). REVERT tested the maneuver in adults only.
Confirmation & Monitoring
Primary Confirmation
Sinus rhythm on the strip at 1 minute is success. It is the outcome REVERT used. Confirm with a 12-lead when the protocol allows.
Secondary Confirmation
- Heart rate drops and stays steady after the return to sinus rhythm.
- Blood pressure recovers once the leg raise is released.
- No new ectopy or pauses on the strip.
| Finding | Success | Failure / Next Step |
|---|---|---|
| Rhythm at 1 min | Sinus rhythm | Still SVT: adenosine per protocol |
| Blood pressure | Stable | Hypotension: lie flat, reassess, go to the unstable pathway |
| Rate | Slows and stays slow | Rate falls then the tachycardia returns: recurrence, not success |
| Rhythm type | Regular sinus | Irregular: AF or flutter; do not repeat the maneuver as treatment |
Ongoing Monitoring
- Continuous ECG: until the rhythm has held and the patient is handed off.
- BP and SpO₂: at baseline, after the maneuver and after each drug push.
Troubleshooting
| Problem | Likely Cause | Fix |
|---|---|---|
| No conversion | Strain too short or no leg raise | Repeat if the protocol allows, then adenosine |
| Rate slows, then returns | Transient AV-nodal effect | Watch the strip; adenosine per protocol |
| Patient cannot strain | Illness, age or instruction | Use the protocol alternative; go to adenosine |
| Irregular rhythm appears | AF or flutter with the SVT | Not a success; follow the AF pathway |
| Lightheadedness or hypotension | Vagal response or leg raise on a fragile patient | Lie flat, monitor, reassess; cardiovert if unstable |
| Pauses on the strip | Vagal effect or adenosine | Expected briefly; confirm return of rhythm |
If It Still Fails
- Adenosine: per protocol, 6 mg then 12 mg in adults.
- Second-line: diltiazem, verapamil or metoprolol per their pages, for a stable regular narrow tachycardia.
- Unstable at any point: synchronized cardioversion now.
Complications
| Complication | Recognition | Prevention | Management |
|---|---|---|---|
| Immediate: hypotension | BP falls during or after the strain or leg raise | Check baseline BP; stable patients only | Lie flat, monitor, cardiovert if the patient is unstable |
| Immediate: brief pause | Pause on the strip, usually after adenosine | Run the strip during every push | Expect return of rhythm; treat per protocol if it persists |
| Delayed: recurrence | SVT returns after a conversion | Reassess at intervals; document | Re-treat per protocol; arrange ongoing care |
| Rare: injury from strain | Chest or head discomfort after the strain | Stop when the patient reports discomfort | Assess; treat per protocol. Not reported in REVERT. |
Special Populations
Pediatrics
- Scope: This page covers adults. The REVERT trial enrolled adults only. For infants and children, use the protocol-approved vagal technique in your PALS SVT algorithm and the Pediatric Tachycardia and SVT page.
- Adenosine by weight: 0.1 mg/kg (max 6 mg), then 0.2 mg/kg (max 12 mg), per the PALS dosing on the adenosine page. Use the weight-based dosing and pediatric vital signs references.
- Unstable child: synchronized cardioversion at 0.5–1 J/kg, then 2 J/kg. See the pediatric shock page.
Older Adults
- Baseline BP matters: A lower baseline makes hypotension from the strain or leg raise more likely. Monitor closely.
Pregnancy
- Protocol and obstetric input: The trial did not study pregnancy. Follow the local protocol. Bring in obstetric and cardiology care as the situation requires.
- Adenosine: the FDA label says no pregnancy studies were done. Use it in pregnancy only if clearly needed.
Post-Procedure Care & Transport
Immediate Aftercare
- Keep monitoring: the rhythm can recur after the maneuver.
- Document the response: time, pressure, rhythm and any drug given.
Ongoing Maintenance
- Rhythm strip: keep it through transfer of care.
- Recurrence plan: a repeat maneuver or drug per protocol; ongoing care for recurrent SVT.
Transport Considerations
- Reassess after each move: the leg raise and position change can drop BP.
- Movement and noise: rely on the monitor, not on feel, for rhythm.
Document & Hand Off
- Rhythm and the 12-lead if taken: before and after
- Stability at baseline and during the maneuver
- Time of strain, pressure and leg raise
- Rhythm at 1 minute and the response
- Adenosine doses, times and flush
- Complications and the recurrence plan
Clinical Pearls & Pitfalls
Pearls
- Modified beats standard: the leg raise after the strain converted 43% vs 17% in REVERT.
- Regular and narrow only: aim it at the rhythm it can break. Not AF, not wide complexes.
- Time the release: write the clock time on the strip. Then the one-minute check is a fact, not a guess.
- Stable first, shock if not: a maneuver never delays cardioversion for an unstable patient.
Common Pitfalls
- Standard strain only, no leg raise: use the modified sequence when the patient is stable.
- Pausing the strip for the drug: keep the rhythm running through the push.
- Calling a brief slowing a success: confirm sinus rhythm at 1 minute.
- Repeating the maneuver on an unstable patient: cardiovert.
Education & Skill Maintenance
Skill Maintenance
- Practice the 15-second strain and the leg raise on a simulator or a partner.
- Rehearse the one-minute strip check and the time documentation.
- Review the adenosine dosing and the rapid-push technique once a year.
References
- Appelboam A, Reuben A, Mann C, Gagg J, Ewings P, Barton M, et al. Postural modification to the standard Valsalva manoeuvre for emergency treatment of supraventricular tachycardias (REVERT): a randomised controlled trial. Lancet. 2015;386(10005):1747–1753. https://doi.org/10.1016/S0140-6736(15)61485-4
- Wigginton JG, Agarwal S, Bartos JA, Coute RA, Drennan IR, Haamid A, et al. Part 9: Adult Advanced Life Support: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16 suppl 2):S538–S577. https://doi.org/10.1161/cir.0000000000001376
- Brugada J, Katritsis DG, Arbelo E, et al. 2019 ESC Guidelines for the management of patients with supraventricular tachycardia. Eur Heart J. 2020;41(5):655–720. https://doi.org/10.1093/eurheartj/ehz467
- Michaud A, Lang E. Leg lift Valsalva maneuver for treatment of supraventricular tachycardias. CJEM. 2017;19(3):235–237. https://doi.org/10.1017/cem.2016.341
- Chen C, Tam TK, Sun S, Guo Y, Teng P, Jin D, Xu L, Liu X. A multicenter randomized controlled trial of a modified Valsalva maneuver for cardioversion of supraventricular tachycardias. Am J Emerg Med. 2020;38(6):1077–1081. https://doi.org/10.1016/j.ajem.2019.158371
- Lasa JJ, Dhillon GS, Duff JP, Hayes J, Kamath-Rayne BD, Levy A, Mahgoub M, Morgan RW, McCormick T, Roberts JS, Ross CE, Schexnayder SM, Sweberg T, Valdés SO, Topjian AA. Part 8: Pediatric Advanced Life Support: 2025 American Heart Association and American Academy of Pediatrics Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16 suppl 2):S479–S537. https://doi.org/10.1161/cir.0000000000001368
- U.S. Food and Drug Administration. Adenosine injection, USP [prescribing information]. DailyMed; set ID 1809fc7e-f5d8-18d8-e063-6394a90a7713; label effective 2024-05-09. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=1809fc7e-f5d8-18d8-e063-6394a90a7713
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.