

Bedside Snapshot
- Use It When
- No measured or recent caregiver weight. Measure head to heel, then read the zone.
- Key Numbers
- 9 zones, Gray (3–5 kg) to Green (30–36 kg).
Heel, not toes. - Formulas
- Dose = per-kg dose × zone weight.
Epinephrine 0.01 mg/kg = 0.1 mL/kg of 0.1 mg/mL. - Action Thresholds
- Between two zones: lower zone, per protocol
- Taller than the tape: adult or measured-weight dosing
- Watch Out
- Underestimates weight in overweight and obese children. Use measured weight when possible.
Overview & Pediatric Differences
The Broselow Pediatric Emergency Tape turns a length into a weight, then hands you a color zone. Each zone carries pre-set drug doses. No scale? One measurement sets every dose. The tape is widely used, but the weight it gives is still an estimate, and that estimate is least reliable in children whose build is far from typical.
Why Kids Are Different
- Doses are per kilogram: most pediatric resuscitation drugs, fluid boluses and shock energies come from weight. Get the weight wrong once and every dose downstream is wrong too.
- Appearance is not a reliable guide: even experienced providers may not get a child's weight right by looking at them (2025 Korean PALS guideline, reference 6; not in the AHA text).
- Length tracks size, not body composition: length-based estimates assume a typical weight-for-length ratio. Obesity and malnutrition break that ratio.
- Length is quick to measure, yet the weight it yields is approximate. Part 8 puts the Broselow, PAWPER XL and Mercy tapes within 10% to 20% of measured total body weight (2025 AHA Part 8, section 7.3, supportive text).
How to Use
- Lay the child supine on a flat, firm surface with the legs straight.
- Align the tape's head end with the top of the child's head.
- Extend the tape along the body to the heel. Measure to the heel, not the toes: measuring to the toes overstates length.
- Read the color zone where the heel falls.
- Use that zone's weight range and printed doses, and record the zone and the weight used.
This page covers the zone, its weight range and the doses listed here. Tube, blade and mask sizes by length are covered on ETT & Equipment Sizing.
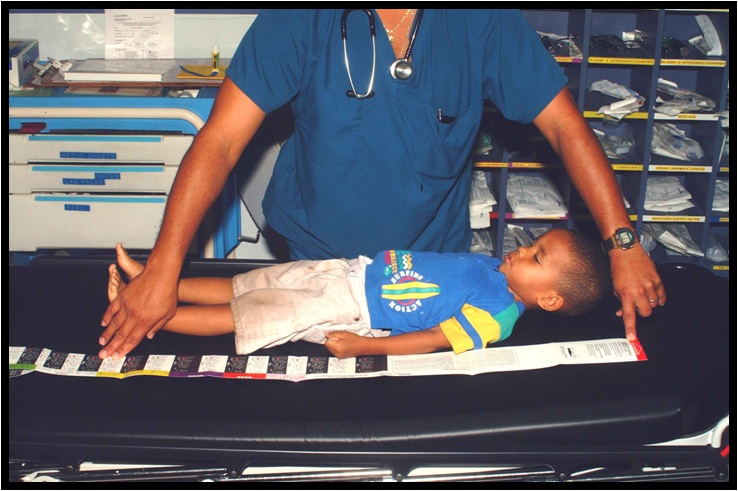
Color Zones & Weight Ranges
Gray is the smallest zone and green the largest. The bands below come from a 2022 EMS field study of the classic nine-zone tape, the Broselow 2007 edition (version B). Other editions and manufacturers can differ at the Blue/Orange boundary. Confirm them against the edition your service uses.
| Color Zone | Weight Range |
|---|---|
| Gray | 3–5 kg |
| Pink | 6–7 kg |
| Red | 8–9 kg |
| Purple | 10–11 kg |
| Yellow | 12–14 kg |
| White | 15–18 kg |
| Blue | 19–22 kg |
| Orange | 23–29 kg |
| Green | 30–36 kg |

Key Doses by Zone
These ranges apply each per-kilogram dose to the lower and upper weight of each zone. They show how the printed doses relate to weight. They are not lifted from any tape.
| Zone (Weight) | Epinephrine 0.01 mg/kg (0.1 mg/mL) | Amiodarone 5 mg/kg | Defibrillation 2 J/kg |
|---|---|---|---|
| Gray (3–5 kg) | 0.03–0.05 mg (0.3–0.5 mL) | 15–25 mg | 6–10 J |
| Pink (6–7 kg) | 0.06–0.07 mg (0.6–0.7 mL) | 30–35 mg | 12–14 J |
| Red (8–9 kg) | 0.08–0.09 mg (0.8–0.9 mL) | 40–45 mg | 16–18 J |
| Purple (10–11 kg) | 0.10–0.11 mg (1.0–1.1 mL) | 50–55 mg | 20–22 J |
| Yellow (12–14 kg) | 0.12–0.14 mg (1.2–1.4 mL) | 60–70 mg | 24–28 J |
| White (15–18 kg) | 0.15–0.18 mg (1.5–1.8 mL) | 75–90 mg | 30–36 J |
| Blue (19–22 kg) | 0.19–0.22 mg (1.9–2.2 mL) | 95–110 mg | 38–44 J |
| Orange (23–29 kg) | 0.23–0.29 mg (2.3–2.9 mL) | 115–145 mg | 46–58 J |
| Green (30–36 kg) | 0.30–0.36 mg (3.0–3.6 mL) | 150–180 mg | 60–72 J |
Interpretation & Action Thresholds
Check the measurement against the situation in front of you before you trust the zone.
| Finding | Meaning | Action |
|---|---|---|
| Heel falls between two zone bands | Weight estimate is uncertain | Use the lower zone unless local protocol says otherwise |
| Child taller than the tape's top zone | The tape cannot estimate weight | Use measured-weight or adult dosing per protocol |
| Measured weight available | Removes the estimation error | Dose from the measured weight and update the zone |
| Recent, confident caregiver weight | Pooled accuracy was higher than the tape's (69.8% vs 55.6% within 10%) | Use it and document the source and date |
| Overweight or obese child | The tape underestimates weight | Use measured weight, or a habitus-adjusted tool per protocol |
| Thin or malnourished child | The tape may overestimate weight and cause overdosing | Use measured weight; check each dose against the per-kilogram rule |
Limitations & Alternatives
- Accuracy: across pooled studies, only 55.6% of tape estimates landed within 10% of actual weight, and 81.2% landed within 20%. A proposed benchmark for an accurate system asks for 70% within 10% and 95% within 20%.
- Field performance: a 2022 EMS study of 509 children under 13 found 51.3% of tape estimates within 10% of the ED scale weight.
- Body habitus: the tape underestimates weight in overweight and obese children. One 2025 single-center PICU study found it within 10% in just 9.8% of overweight children.
- Population: accuracy shifts from one population to the next. In low- and middle-income settings, overestimation was often extreme.
- Tape alone: a 2024 systematic review found harmful dosing errors when the tape stood alone. Still, it beat having no dosing aid. A drug dosing guide or a color-coded medication system did better.
- Upper limit: taller than the top zone means adult or measured-weight dosing. Some tape editions add a Black zone (37–49 kg) above Green.
Weight Estimation Hierarchy
- Measured weight
- Recent, confident caregiver or chart weight
- Habitus-adjusted tool (PAWPER XL, Mercy method) per protocol
- Length-based tape (Broselow)
- Age-based formula (last resort; poor accuracy)
| Alternative | Method | Evidence |
|---|---|---|
| Measured weight | Scale or stretcher scale | Removes estimation error; always preferred |
| Caregiver weight | Recent, confident report | Pooled: 69.8% within 10%, 87.1% within 20% |
| PAWPER XL | Length plus habitus assessment | Single-center PICU study (2025, n=100): 83.5% within 10% vs 61.2% for the Broselow tape; 98.7% vs 87.9% within 20% |
| PAWPER tape (original) | Length-based, habitus-modified (original version, not XL) | Not reported here; see the PAWPER XL row for the newer version |
| Mercy method | Two-dimensional (habitus-adjusted) | Pooled: 70.9% within 10%, 95.3% within 20% |
| Handtevy | Age-based application (length and age originally) | EMS field study: 43.7% within 10% vs 51.3% for the tape |
| Age-based formulas | Age only | Poor accuracy in published studies; last resort only |
Medications & Dosing
Doses run per kilogram of the zone weight, or of the measured weight when you have one. Sourcing goes in this order: AHA/AAP 2025 PALS where it states a dose, then the NASEMSO National Model EMS Clinical Guidelines v3.0 (2022), then the US label. If none of them gives a dose, this page shows none. No pediatric maximum ever exceeds the adult maximum dose (NASEMSO Universal Care Guideline, p. 13). Treat any dose not marked labeled as off-label.
Resuscitation
| Drug | Dose & Route | Max | Notes |
|---|---|---|---|
| Epinephrine 0.1 mg/mL (formerly labeled 1:10,000) High-alert | 0.01 mg/kg IV/IO = 0.1 mL/kg of 0.1 mg/mL | 1 mg per dose | Nonshockable rhythms: give the first dose as early as possible (2025 AHA Part 8, section 7.2, rec 1, COR 2a, LOE C-LD). Shockable VF/pVT: give the first dose after 2 shocks, or sooner only if rapid defibrillation is not possible (rec 2, COR 2b, LOE C-LD). Every 3–5 min until ROSC (rec 3, COR 2b, LOE C-LD; PALS cardiac arrest algorithm). |
| Amiodarone High-alert | 5 mg/kg IV/IO Push during arrest; with a pulse, infusion is specialist use only (no pediatric rate established) | 300 mg first dose; 150 mg each later dose; up to 3 doses | Shock-refractory VF or pVT (2025 AHA Part 8, section 7.2, COR 2b, LOE C-LD). Watch blood pressure and QT interval. |
| Lidocaine High-alert | 1 mg/kg IV/IO bolus Infusion: not established in children; specialist use only | None established | Alternative to amiodarone for shock-refractory VF or pVT (2025 AHA Part 8, section 7.2, COR 2b, LOE C-LD). The 1 mg/kg bolus is in the AHA PALS cardiac arrest algorithm. No pediatric infusion rate is established here; specialist use only. |
| Calcium chloride (10%) | 20 mg/kg IV/IO slowly = 0.2 mL/kg of 10%; over 5 min for arrest or hyperkalemia, over 10 min for calcium channel blocker overdose | 1 g per dose | Not routine in arrest: 2025 AHA Part 8 (section 7.2, rec 6) gives COR 3: No Benefit, LOE B-NR for routine use. Use for documented hypocalcemia (label dose below), hyperkalemia or calcium channel blocker overdose. Differs from FDA label: the US calcium chloride label gives a pediatric dose only for hypocalcemia, 2.7–5 mg/kg slow IV, no faster than 1 mL/min, central or deep vein (DailyMed setid c4c65e48-85f8-4dcf-6281-06e40959cc79, sections 2.1–2.2). Use that label dose for hypocalcemia; the 20 mg/kg dose here is for arrest, hyperkalemia and calcium channel blocker overdose. Central line preferred; extravasation injures tissue. The 20 mg/kg dose and 1 g maximum are the NASEMSO figures (Cardiac Arrest p. 119; Crush Injury p. 223; Calcium Channel Blocker Poisoning p. 296); AHA Part 8 gives no calcium mg/kg dose. |
| Sodium bicarbonate | 1 mEq/kg IV/IO slowly = 1 mL/kg of 8.4% (1 mEq/mL) | 50 mEq per dose | Not routine: 2025 AHA Part 8 (section 7.2, rec 5) gives COR 3: No Benefit, LOE B-NR for routine use in children. Use only for special circumstances: hyperkalemia or sodium channel blocker toxicity (same rec). NASEMSO gives the same 1 mEq/kg, max 50 mEq, for crush injury with hyperkalemia on the ECG (p. 223); for a known hyperkalemic patient in arrest it gives 1 mEq/kg with no maximum (p. 119). Raises PCO₂. The 4.2% (0.5 mEq/mL) solution may be used in neonates. NASEMSO (p. 162) finds no evidence for routine bicarbonate in newborn resuscitation. |
Bradycardia and Tachycardia
| Drug | Dose & Route | Max | Notes |
|---|---|---|---|
| Epinephrine (first-line) | 0.01 mg/kg IV/IO = 0.1 mL/kg of 0.1 mg/mL | 1 mg per dose | Start CPR if HR is below 60/min with cardiopulmonary compromise despite effective oxygenation and ventilation (2025 AHA Part 8, section 18, COR 1, LOE C-EO). Give IV/IO epinephrine when bradycardia with compromise persists after correcting other causes such as hypoxia (COR 1, LOE C-EO). Check the pulse every 2 minutes (PALS bradycardia algorithm, Box 7). |
| Atropine (second-line) | 0.02 mg/kg IV/IO (minimum 0.1 mg) For bradycardia with cardiopulmonary compromise from increased vagal tone or AV block, not from hypoxia | 0.5 mg per dose | May repeat once. Not first-line for bradycardia with poor perfusion, and not an arrest drug (2025 AHA Part 8, section 18, COR 1, LOE C-LD). Minimum 0.1 mg and maximum single dose 0.5 mg (PALS bradycardia algorithm sidebar). Part 8 notes the 0.1 mg minimum is historical for intubation premedication, where 0.02 mg/kg with no minimum may be considered (COR 2b). |
| Adenosine (first dose) | 0.1 mg/kg IV rapid push, then at least 5 mL saline flush | 6 mg per dose | Stable regular narrow or wide QRS tachycardia. In SVT with cardiopulmonary compromise, give adenosine if IV/IO access is already in place, or perform synchronized cardioversion. Do not delay cardioversion for access. For wide-complex tachycardia, adenosine is for a regular monomorphic rhythm only (2025 AHA PALS tachyarrhythmia algorithm, Boxes 9, 15 and 17). |
| Adenosine (second dose) | 0.2 mg/kg IV rapid push, then at least 5 mL saline flush | 12 mg per dose | Give if the first dose does not work. |
Fluids and Dextrose
| Drug | Dose & Route | Max | Notes |
|---|---|---|---|
| Crystalloid bolus | 10–20 mL/kg IV/IO, reassess after each bolus | Up to 40–60 mL/kg in the first hour where intensive care is available; up to 40 mL/kg if hypotensive without intensive care (2020 Surviving Sepsis Campaign pediatric guideline) | Stop and reassess for signs of fluid overload. |
| Dextrose 10% (D10W) newborn | 2 mL/kg IV (0.2 g/kg) | 25 g total (adult maximum) | Hypoglycemia with altered mental status. NASEMSO v3.0, Hypoglycemia guideline (p. 85): newborns 2 mL/kg of 10%. Check glucose after treatment. 10% is safe and effective at all ages (p. 86). |
| Dextrose 10% (D10W) infants and children | 5–10 mL/kg IV (0.5–1 g/kg) | 25 g total (adult maximum) | Hypoglycemia with altered mental status (NASEMSO p. 85). Give in incremental doses until mental status improves. Under 8 years: no more than 25% concentration; 10% is preferred (NASEMSO p. 85-86). |
| Dextrose 25% (D25W) children over 8 years High-alert | 2–4 mL/kg IV (0.5–1 g/kg) | 25 g total (adult maximum) | Hypoglycemia (NASEMSO p. 85, dosing for children over 8 years). For children under 8, 10% is preferred over 25%. Concentrated dextrose is high-alert (20% or more). |
| Dextrose 50% (D50W) adolescents High-alert | No pediatric 50% dose shown; use 25% (row above) | None established | NASEMSO p. 86: 50% carries risk of extravasation and hyperglycemia with little clinical gain. For children under 8, use no more than 25%. |
Electrical Therapy
| Drug | Dose & Route | Max | Notes |
|---|---|---|---|
| Defibrillation (VF or pVT) | 2 J/kg first shock 4 J/kg second shock At least 4 J/kg for each later shock | 10 J/kg or adult dose | Resume CPR immediately after each shock (2025 AHA PALS cardiac arrest algorithm). |
| Synchronized cardioversion (unstable tachycardia) | 0.5–1 J/kg, then 2 J/kg if no effect | 2 J/kg | Sedate if needed, but do not delay cardioversion (2025 AHA PALS tachyarrhythmia algorithm). |
The high-alert drugs here are epinephrine, amiodarone, lidocaine and concentrated dextrose.
Pitfalls & Safety Checks
| Pitfall | Consequence | Prevention |
|---|---|---|
| Measuring to the toes | Overstated length moves the child up a zone | Read the tape at the heel |
| Using the tape for a child taller than its top zone | Weight and doses fall outside the tape's range | Switch to adult or measured-weight dosing per protocol |
| Using the zone for an overweight or obese child | Weight underestimated, so doses are too low | Use measured weight or a habitus-adjusted tool |
| Using the zone for a thin or malnourished child | Weight overestimated, so doses are too high | Use measured weight; check each dose against the per-kilogram rule |
| Epinephrine concentration confusion | 10-fold dosing error | Read the label: 0.1 mg/mL for IV/IO arrest, 1 mg/mL for IM |
| Tape edition not checked | Printed doses or zone bands may not match your service | Confirm the tape edition and printed values against local protocol |
| Tape used alone for drug doses | Harmful dosing errors were common in the 2024 review | Pair the tape with a dosing guide or pre-drawn color-coded syringes |
Special Populations
Neonates and Young Infants
- Many term newborns fall in the Gray zone (3–5 kg). Some drugs are dosed differently in neonates.
- The 2025 AHA guidelines, Part 5 (neonatal resuscitation), recommend intravascular epinephrine (1:10,000) at 0.01–0.03 mg/kg for a heart rate that stays below 60/min after ventilation and chest compressions (COR 1, LOE B-NR). For hypoglycemia, NASEMSO sets 2 mL/kg of 10% dextrose for newborns (Hypoglycemia guideline, p. 85). That is the same figure as in Medications & Dosing.
- Infants under 3 kg sit below the tape's lowest zone (3 kg), and many preterm infants land in that group. For them, use a measured weight and a neonatal protocol.
- Neonatal dosing beyond that is outside this page. Follow neonatal resuscitation guidance.
Obesity and Higher Body Weight
- Part 8, section 7.3 of the 2025 AHA guidelines (Weight-Based Dosing of Resuscitation Medications, supportive text) makes no recommendation on obesity dosing, and that section has not been re-reviewed since 2020. It warns of high variability. Total body weight tends to be underestimated, while ideal body weight is closely approximated.
- That same section says there are no data on the safety or efficacy of adjusting doses for obesity. Any adjustment, then, is a protocol decision.
- Measure the weight whenever you can. No scale? Use a habitus-adjusted tool per protocol.
Adolescents and Children Taller Than the Tape
- Taller than the tape's top zone? Move to adult or measured-weight dosing per local protocol. The length limit decides this, not age.
Prehospital & Transport Considerations
| Level | Typical Role With This Tool |
|---|---|
| EMT | Measures head to heel and reports the zone (commonly; per agency protocol) |
| AEMT | Reads the zone and gives protocol-approved doses from it (commonly; per state and agency protocol) |
| Paramedic | Uses the zone for drug and equipment selection, and checks it against any measured or caregiver weight |
| RN (ED/ICU) | Confirms the zone against a measured weight where available; uses pre-made color-coded syringes where stocked |
| Critical Care Transport | Updates doses when a measured weight becomes available (per protocol) |
- Carry the tape edition your protocol names in every kit. Check its printed doses against local protocol.
- Once the child is stable enough, a measured or recent chart weight beats the tape.
- Write the zone and the weight used on the run sheet, and say both in the handoff.
- Pre-drawn color-coded syringes cut down on calculation. The 2024 review found them more accurate than the tape alone.
Clinical Pearls
References
- Wells M, Goldstein LN, Bentley A, Basnett S. The accuracy of the Broselow tape as a weight estimation tool and a drug-dosing guide: a systematic review and meta-analysis. Resuscitation. 2017;121:9-33. https://doi.org/10.1016/j.resuscitation.2017.09.026
- Wells M, Yende P. Is there evidence that length-based tapes with precalculated drug doses increase the accuracy of drug dose calculations in children? A systematic review. Clin Exp Emerg Med. 2024;11(2):145-160. https://doi.org/10.15441/ceem.23.110
- Knudsen-Robbins C, Pham PK, Zaky K, et al. Weighty matters: a real-world comparison of the Handtevy and Broselow methods of prehospital weight estimation. Prehosp Disaster Med. 2022;37(5):616-624. https://doi.org/10.1017/S1049023X22001248
- Singh TK, Khan K, Thomas SRJ. Accuracy of Paediatric Advanced Weight Prediction in the Emergency Room-eXtra Length (PAWPER XL) tape in estimation of body weight in pediatric emergencies. Cureus. 2025;17(8):e89775. https://doi.org/10.7759/cureus.89775
- American Heart Association and American Academy of Pediatrics. Part 8: Pediatric Advanced Life Support: 2025 American Heart Association and American Academy of Pediatrics Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16 suppl 2):S479-S537. https://doi.org/10.1161/CIR.0000000000001368
- Kim DK, et al. 2025 Korean Guidelines for Cardiopulmonary Resuscitation: Part 8. Pediatric advanced life support. Clin Exp Emerg Med. 2026;13(Suppl 1):S115-S141. https://doi.org/10.15441/ceem.26.103
- American Heart Association and American Academy of Pediatrics. Part 5: Neonatal Resuscitation: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. 2025. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/neonatal-resuscitation
- Weiss SL, Peters MJ, Alhazzani W, et al. Surviving Sepsis Campaign International Guidelines for the Management of Septic Shock and Sepsis-Associated Organ Dysfunction in Children. Pediatr Crit Care Med. 2020;21(2):e52-e106. https://doi.org/10.1097/PCC.0000000000002198
- National Association of State EMS Officials. NASEMSO National Model EMS Clinical Guidelines, Version 3.0. March 2022. https://nasemso.org/content.aspx?page_id=22&club_id=157064&module_id=701974
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.