

Bedside Snapshot
- Use It When
- Every child at first contact, before touching. Repeat it after each intervention to track response.
- Key Numbers
- About 1 min, hands-off
3 components: Appearance, Work of Breathing, Circulation to Skin
Normal capillary refill 2 s or less, checked centrally - Formulas
- None. The PAT is observational. Tube and weight formulas are on ETT and Equipment Sizing.
- Action Thresholds
- Any abnormal: hands-on ABCDE now
- Two abnormal: escalate; treat the dominant problem
- All three abnormal: team to bedside; prepare for arrest
- Watch Out
- A quiet, limp child after distress is in respiratory failure, not recovery. Mottled skin with an abnormal appearance is shock until proven otherwise.
Overview & Pediatric Differences
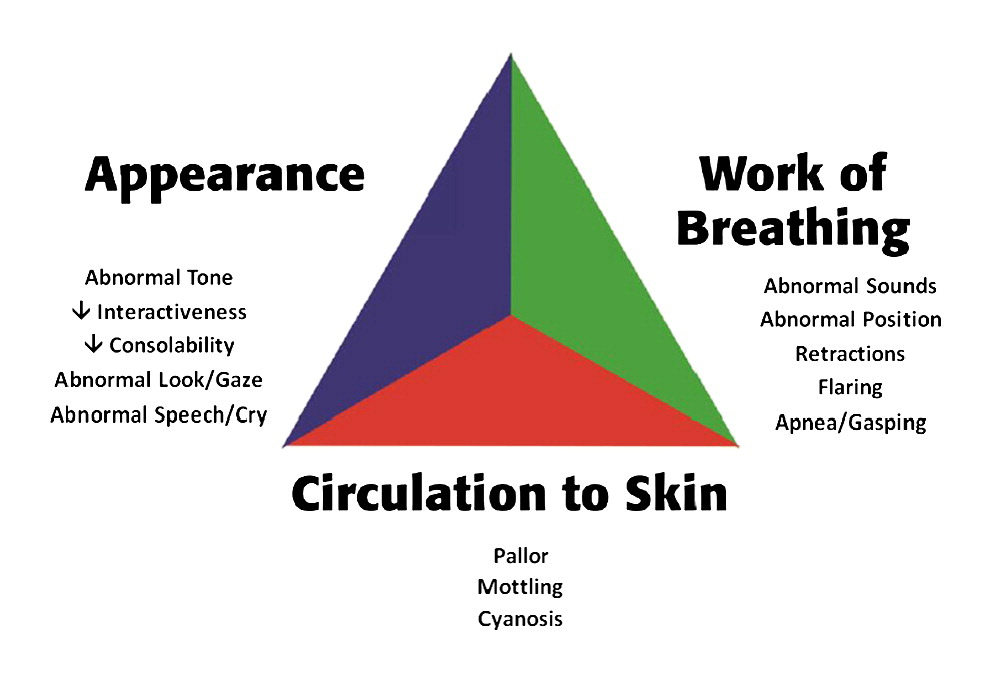
The Pediatric Assessment Triangle (PAT) is a hands-off look from across the room. It takes about a minute. Before any monitor, stethoscope or hands-on exam, it sorts the child into a physiologic category. Three things get rated: Appearance, Work of Breathing and Circulation to Skin. The PAT anchors the AAP-sponsored Pediatric Education for Prehospital Professionals (PEPP) course. Most standardized American life support courses have built it in, including PALS, APLS and ENPC.
Why Kids Are Different
- Compensation hides shock: kids hold their blood pressure up by raising heart rate and clamping down peripheral vessels. Hypotension shows up late.
- Vital signs lag: the PAT can go abnormal before the numbers do. Don't wait for the monitor to confirm what the child is showing you.
- Handling provokes agitation: touch an infant or toddler and the assessment gets harder. Watch first.
- Breathing drives most events: most pediatric cardiac arrests follow progressive respiratory failure or shock. Catch failing breathing or circulation early. That is the priority. See Pediatric Cardiac Arrest (PALS).
The PAT is a screen, not a diagnosis. It sorts the child. The hands-on primary assessment confirms and refines that impression.
How to Use
- Stand back and watch: observe from the doorway or the foot of the bed for about a minute, with the child in the caregiver's arms if possible.
- Rate Appearance: use TICLS (see the Appearance table).
- Rate Work of Breathing: look, listen and watch the chest and abdomen, including sounds heard from across the room.
- Rate Circulation to Skin: check colour, pallor, mottling and central cyanosis on the trunk, lips and tongue.
- Assign the category: use the Putting the Triangle Together table and record it before the numbers.
- Move to hands-on ABCDE: begin the primary assessment once the impression is recorded.
Appearance (TICLS)
Appearance comes first, because it is the most important component. One look tells you how ventilation, oxygenation, brain perfusion and CNS function are doing, all at once. That makes an abnormal appearance the most sensitive sign that a child is seriously ill. Use the TICLS mnemonic: Tone, Interactiveness, Consolability, Look/Gaze and Speech/Cry.
| Letter | Component | Normal | Abnormal |
|---|---|---|---|
| T | Tone | Moves spontaneously, resists examination | Limp, floppy, motionless |
| I | Interactiveness | Alert, watches and reaches for people and objects | Uninterested, no engagement with surroundings |
| C | Consolability | Settles with caregiver comfort | Inconsolable, or paradoxically quiet when distress is expected |
| L | Look/Gaze | Makes eye contact, tracks faces and objects | Glassy-eyed, vacant stare, does not fix on faces |
| S | Speech/Cry | Strong, age-appropriate cry or speech | Weak, high-pitched, hoarse, muffled or absent cry |
Work of Breathing
Posture and sounds give you the fastest clues. Work of Breathing (WOB) is visible effort, judged from across the room. Effort is not adequacy. A hard-working child can still oxygenate. A quiet-looking one can be failing.
| Sign | Type | What It Suggests |
|---|---|---|
| Nasal flaring | Visual | Increased work of breathing; common in infants |
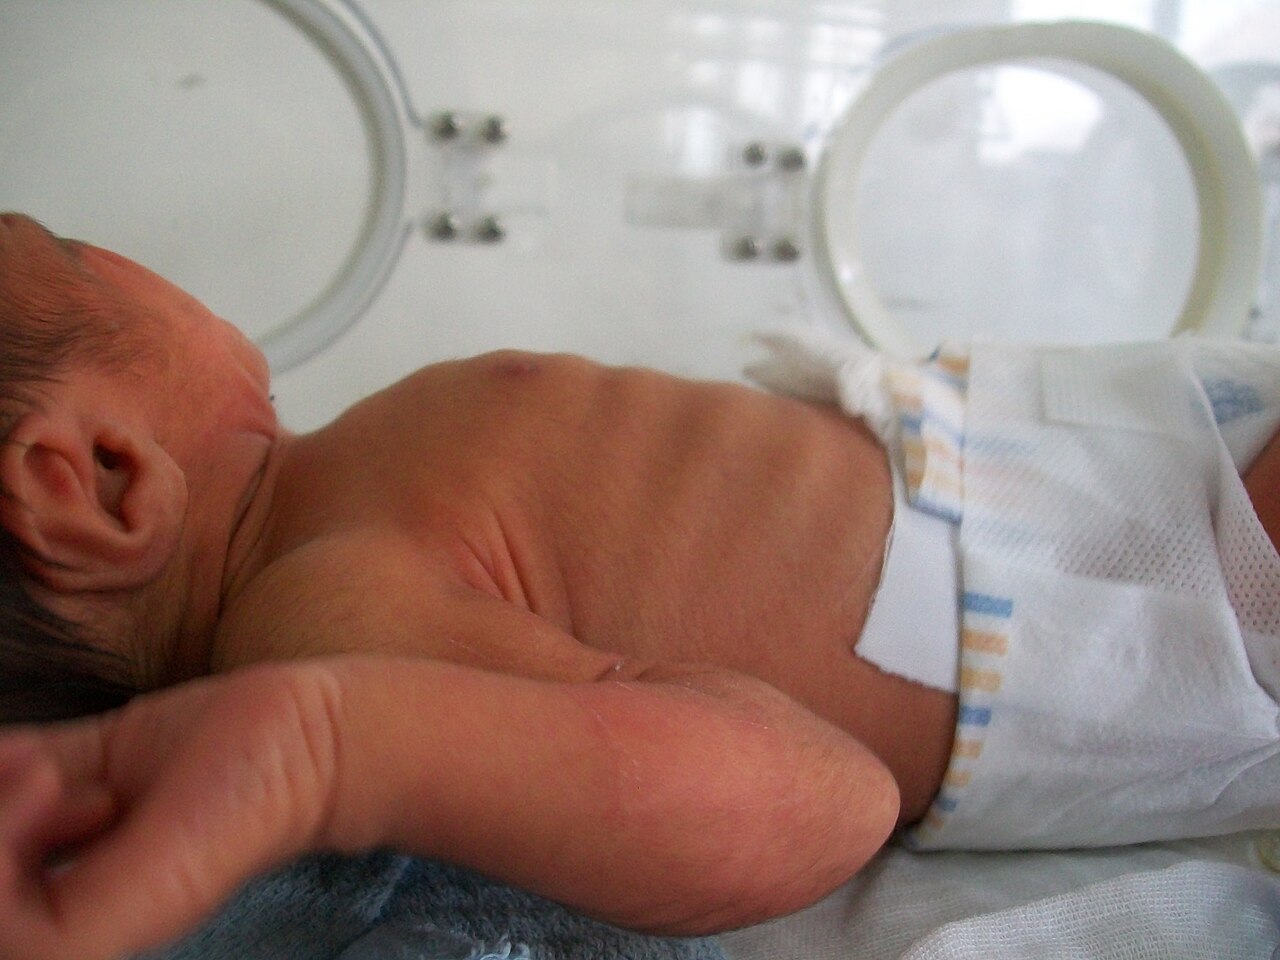
| Retractions | Visual | Accessory muscles pull in at the suprasternal, supraclavicular, intercostal, subcostal or sternal sites. More sites means more severe distress |
| Head bobbing | Visual | Accessory muscle use in infants; head extends on inspiration and flexes on expiration |
| Tripod or sniffing position | Visual | Child leans forward with neck extended, which opens the airway |
| Seesaw (paradoxical) breathing | Visual | Chest and abdomen move in opposite directions; diaphragm fatigue and severe distress |
| Stridor | Audible | Harsh inspiratory sound from upper airway obstruction (croup, foreign body, epiglottitis) |
| Wheezing | Audible | Musical expiratory sound from lower airway obstruction (asthma, bronchiolitis) |
| Grunting | Audible | Expiratory sound from a partly closed glottis (auto-PEEP); significant distress, with alveolar disease in mind |
| Snoring or gurgling | Audible | Upper airway obstruction from soft tissue or secretions |
| Apnea or gasping | Pattern | Late sign; imminent respiratory arrest |
Circulation to Skin
The skin is an early tell. When cardiac output falls, the body pulls blood away from the skin to protect the brain and heart. Circulation to Skin reflects cardiovascular adequacy, so skin changes show up early and visibly.
| Sign | What It Suggests | Where to Look |
|---|---|---|
| Pallor | Vasoconstriction from shock, anemia or cold | Lips, mucous membranes, trunk |
| Mottling | Patchy, uneven perfusion; an early sign of shock | Trunk and proximal limbs |
| Peripheral cyanosis (acrocyanosis) | Blue hands and feet; can be normal in newborns and in cold environments | Hands and feet |
| Central cyanosis | Blue lips, tongue or trunk; always abnormal and needs an immediate breathing and oxygenation assessment | Lips, tongue, trunk |
Interpretation & Action Thresholds
Put the three components together and you get one general impression. The categories below follow the PAT teaching convention. Triage validation studies report these pathophysiology groups: respiratory distress, respiratory failure, shock, CNS or metabolic dysfunction, and cardiopulmonary failure.
| Appearance | Breathing | Circulation | General Impression |
|---|---|---|---|
| Normal | Normal | Normal | Stable |
| Normal | Abnormal | Normal | Respiratory distress (still compensating) |
| Abnormal | Abnormal | Normal | Respiratory failure (decompensating) |
| Normal | Normal | Abnormal | Compensated shock |
| Abnormal | Normal | Abnormal | Decompensated shock |
| Abnormal | Normal | Normal | CNS or metabolic dysfunction (check glucose; consider seizure, ingestion, sepsis, head injury) |
| Abnormal | Abnormal | Abnormal | Cardiopulmonary failure: treat as imminent arrest |
Other combinations are not named categories. Treat the most abnormal component. Escalate. Reassess.
- Any abnormal component: move to the hands-on ABCDE now and raise urgency. Run the primary assessment on every PAT, normal ones included. Repeat it after each intervention.
- Two abnormal components: escalate. Treat the dominant problem.
- All three abnormal: call for help and bring the team to the bedside. Treat as imminent arrest.
Next: Primary Assessment (ABCDE)
- A, Airway: patent, maintainable or at risk; secretions, stridor, position.
- B, Breathing: rate, SpO₂, effort, chest movement, lung sounds, EtCO₂ where available.
- C, Circulation: heart rate, blood pressure, capillary refill (normal 2 seconds or less; more than 2 seconds is prolonged), checked centrally on the sternum or forehead, skin temperature and pulse quality.
- D, Disability: AVPU or GCS, pupils, blood glucose, posturing.
- E, Exposure: undress the child. Look for rash (petechiae or purpura), injury, deformity and temperature. Apply local protocols for suspected maltreatment.
Where to Go Next by Abnormal Component
- Abnormal breathing: Pediatric Airway Anatomy for airway anatomy and obstruction.
- Abnormal circulation: Pediatric Shock.
- Breathing stopped or three abnormal components: Pediatric Cardiac Arrest (PALS).
- Vital-sign ranges by age: Pediatric Vital Signs by Age.
Limitations & Alternatives
- Observer variation: reviews report inter-observer variability and inconsistent training. The category depends on who is doing the assessing.
- Neonates and complex chronic conditions: the evidence is thinner. It applies less well here.
- Validation: most studies are observational and single-centre. The psychometric evidence is still limited. The PAT is a structured screen. It is not a validated score for disposition.
| Tool | Use | Limitation |
|---|---|---|
| Full ABCDE (primary assessment) | Required next step after the PAT | Requires hands-on contact, which may upset the child |
| Vital signs by age | Confirms a derangement once the PAT raises concern | Needs equipment and handling; ranges are age-specific |
| Structured triage score, per local protocol | Standardizes triage across staff | Needs local validation and vital signs |
Pitfalls & Safety Checks
| Pitfall | Consequence | Prevention |
|---|---|---|
| Touching the child before observing | Crying and agitation hide the signs you need | Observe for about a minute before any hands-on contact |
| Calling a quiet child improved | Missed respiratory failure or sepsis | Compare with the caregiver's baseline; quiet after distress is a warning sign |
| Relying on normal vital signs | Late recognition of compensated shock | Record the PAT before the numbers and repeat it after each change |
| Reading capillary refill from a cold fingertip | False abnormal or false normal result | Check centrally (sternum or forehead) |
| Dismissing the caregiver's concern | Missed change from the child's baseline | Ask what is different from usual, and weigh the answer |
| Using adult colour rules on darker skin | Missed pallor or cyanosis | Check mucous membranes, nail beds, palms and soles |
Special Populations
Neonates and Young Infants
- The PAT is less proven in neonates. Newborn resuscitation follows the Neonatal Resuscitation Program, not this tool.
- In a newborn, grunting, retractions and central cyanosis are never normal. Escalate early.
Children With Chronic Conditions or Devices
- Tracheostomy, shunts, feeding tubes and home ventilation all move the baseline. Ask the caregiver what normal looks like for this child.
- Looking stable on the PAT does not rule out deterioration in a child with a complex condition. Reassess more often.
Injured Children
- The PAT works for injury as well as medical illness. Check the mechanism and look for external hemorrhage alongside it. A normal PAT does not exclude significant injury.
- The PAT does not measure pain or fever. Record them separately. Reassess after analgesia or antipyresis.
Suspected Maltreatment
- Injuries that do not match the history need escalation. So does an unexplained change in appearance. Document per local protocol.
Prehospital & Transport Considerations
Prehospital crews use the PAT in the field, not only in the ED. A single-center retrospective cohort tracked pediatric EMS transports to a quaternary pediatric emergency department. Scores of 1 or more were linked to advanced life support transport (odds ratio 67.9). Scores of 2 or more were linked to higher odds of ICU-level care, direct to surgery or death (odds ratio 4.9). Most children (65.9%) scored 0, so the signal sits in the minority with abnormal components. The authors call it a promising adjunct to ED assessment, not a validated disposition score.
| Level | Typical Role in This Topic |
|---|---|
| EMT | Performs the PAT on every pediatric patient and reports the category; provides oxygen and basic airway support per protocol |
| AEMT | Performs the PAT and acts on the category within protocol |
| Paramedic | Assigns the category and directs advanced airway, access and medication per protocol |
| RN (ED/ICU) | Uses the PAT at triage and for serial reassessment; escalates to the physician per local protocol |
| Critical care transport | Reassesses the PAT en route; a change in category guides ventilation and drug support per protocol |
- Equipment: have a pediatric length-based reference and pre-calculated or colour-coded doses ready, per local protocol.
- Destination: a pediatric-capable emergency department, PICU or pediatric trauma centre, per the regional plan.
- Restraint: use a child-sized restraint on the stretcher. Never restrain a child on a caregiver's lap.
- Caregiver: keep the caregiver with the child and treat their description of baseline as data.
- Heat loss: cover the head and trunk of an infant and warm the compartment.
- Handoff: report the PAT category first, then the trend across reassessments.
Clinical Pearls
References
- Dieckmann RA, Brownstein D, Gausche-Hill M. The pediatric assessment triangle: a novel approach for the rapid evaluation of children. Pediatr Emerg Care. 2010;26(4). doi:10.1097/PEC.0b013e3181d6db37. https://doi.org/10.1097/PEC.0b013e3181d6db37
- Horeczko T, Enriquez B, McGrath NE, Gausche-Hill M, Lewis RJ. The pediatric assessment triangle: accuracy of its application by nurses in the triage of children. J Emerg Nurs. 2013;39. doi:10.1016/j.jen.2011.12.020. https://doi.org/10.1016/j.jen.2011.12.020
- American Heart Association and American Academy of Pediatrics. Part 8: Pediatric Advanced Life Support: 2025 American Heart Association and American Academy of Pediatrics Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16 suppl 2). doi:10.1161/CIR.0000000000001368. General further reading. https://doi.org/10.1161/CIR.0000000000001368
- Rath S, Alsabri M, Alhaddad J, Patel A, Chacko MM, Bucciarelli B. Clinical accuracy and applications of the Pediatric Assessment Triangle in emergency care: a narrative review. Int J Emerg Med. 2026;19. doi:10.1186/s12245-026-01169-2. https://doi.org/10.1186/s12245-026-01169-2
- Heyming T, Knudsen-Robbins C, Kain A, Morphew T, Ta-Perez Z, Darabpour A. Prehospital Pediatric Assessment Triangle-Real World Data: Emergency Medical Services Use of the Pediatric Assessment Triangle in the Prehospital Environment. Prehosp Emerg Care. 2026;30:828-836. doi:10.1080/10903127.2025.2581753. https://doi.org/10.1080/10903127.2025.2581753
- Torisen TAG, Glanville JM, Loaiza AF, Bidonde J. Emergency pediatric patients and use of the pediatric assessment triangle tool (PAT): a scoping review. BMC Emerg Med. 2024;24:158. doi:10.1186/s12873-024-01068-w. https://doi.org/10.1186/s12873-024-01068-w
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.