

Bedside Snapshot
- Recognize
- Sudden dyspnea, pleuritic pain, tachycardia or hypoxemia, syncope or leg swelling. Estimate pretest probability (Wells, PERC) before the D-dimer or CTPA. Do not rule out on normal vitals.
- Red Flags
- Persistent hypotension (SBP under 90 mmHg, or a 40 mmHg drop for over 15 min) or cardiogenic shock (Category E1); refractory shock or arrest (E2); transient hypotension or normotensive shock (D); falling SpO₂ on oxygen
- First Actions
- Oxygen; IV or IO access and ECG; anticoagulate when PE is likely and bleeding risk allows; activate the PERT for shock; treat hypotension per protocol
- Key Doses
- Heparin 80 units/kg IV, then 18 units/kg/hr; enoxaparin 1 mg/kg subcut every 12 hr; alteplase 100 mg IV over 2 hr for massive PE
- Don't Miss
- Normal vitals do not exclude PE; PERC and negative D-dimer apply only at low probability; tenecteplase is not labeled for PE; check for lytic contraindications
- Escalate & Transport
- Shock or arrest: PERT-capable center, catheter-directed therapy, mechanical thrombectomy or VA-ECMO per PERT; monitor for bleeding in transit
Definition & Pathophysiology
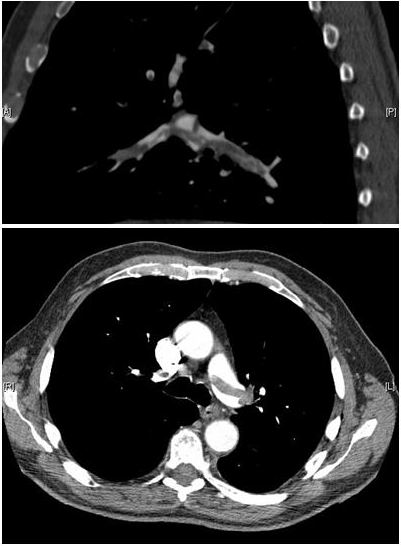
Pulmonary embolism (PE) is a blockage in the pulmonary arteries. Most often the clot has traveled from a deep vein in the legs or pelvis. The blockage raises right ventricular (RV) afterload: the RV now pumps against a clogged pipe. When the RV can't compensate, it dilates. The septum shifts toward the left ventricle, and left ventricular filling falls. Cardiac output drops, and so does systemic pressure. Hypoxemia comes from ventilation-perfusion mismatch. Ventilation and perfusion no longer match.
- Severity classes: The 2026 AHA/ACC guideline sorts patients into categories A to E. A is subclinical. B is symptomatic with low clinical severity. C is symptomatic with elevated clinical severity: raised biomarkers or RV dysfunction. D1 and D2 are the early-failure categories, transient hypotension or normotensive shock. E is cardiopulmonary failure. E1 is recurrent or persistent hypotension with cardiogenic shock. E2 is refractory cardiogenic shock, often ending in cardiac arrest.
- PERC items: age 50 or older, heart rate 100 or higher, SpO₂ 94% or lower, recent surgery or trauma, prior DVT or PE, unilateral leg swelling, hormone use and hemoptysis (see Assessment).
- Clinical course: Many small emboli cause no symptoms. A large one can cause sudden collapse or cardiac arrest. Some patients die before they reach hospital.
Recognition & Red Flags
Typical Presentation
- Symptoms: sudden dyspnea, pleuritic chest pain, cough, hemoptysis, syncope or presyncope, and leg pain or swelling on one side
- Signs: tachycardia, tachypnea, hypoxemia, signs of right heart strain, and clinical signs of DVT
Red Flags
- Shock: persistent hypotension (systolic BP under 90 mmHg, or a fall of 40 mmHg or more for over 15 min, or vasopressors needed) or cardiogenic shock (Category E1), or transient hypotension or normotensive shock (D1 and D2)
- Refractory shock or arrest: cardiogenic shock that does not respond to treatment, or cardiac arrest (Category E2)
- Hypoxemia: SpO₂ that falls on supplemental oxygen, or a rising work of breathing
- Syncope or altered mental status with dyspnea or tachycardia
Assessment & Diagnostics
Start with pretest probability. In the emergency department, the Wells score and PERC rule decide whether you need a D-dimer or a CT pulmonary angiogram (CTPA). In shock, don't wait for imaging before you resuscitate. Confirm the diagnosis and risk category once the patient is stable.
| Check | Why | Act If |
|---|---|---|
| 12-lead ECG and rhythm | Sinus tachycardia is most common. S1Q3T3, right bundle branch block and T-wave inversion in V1 to V4 suggest right heart strain; each has low sensitivity, and no pattern is diagnostic of PE | Tachyarrhythmia or new right heart strain with hypotension: treat as a shock presentation (12-lead ECG acquisition) |
| SpO₂ and work of breathing | Hypoxemia is common and can be severe with a normal chest film | SpO₂ below target on room air: oxygen per protocol; reassess SpO₂ after each change |
| BP, HR and perfusion | Hypotension sets the risk category and the treatment path | Persistent hypotension or shock: Category E. Syncope raises concern and needs a full risk-category assessment; it is not a Category E label on its own. Activate the PERT and the ED or ICU team now for persistent hypotension or shock |
| Point-of-care ultrasound and capnography | Bedside echo may show RV dilation (RV-to-LV ratio over 1), septal flattening or McConnell sign. A sudden fall in ETCO₂ with a stable airway suggests reduced pulmonary perfusion. Neither excludes PE | RV strain with hypotension, or a sudden ETCO₂ fall: treat as a shock presentation and activate the PERT |
| Wells score | Pretest probability. Points: clinical signs of DVT 3; PE most likely diagnosis 3; heart rate over 100 1.5; immobilization or surgery in 4 weeks 1.5; prior DVT or PE 1.5; hemoptysis 1; malignancy 1 | Score over 4 (PE likely): CTPA. Score 4 or lower (PE unlikely): D-dimer first |
| PERC rule | Eight items: age under 50; heart rate under 100; SpO₂ above 94%; no unilateral leg swelling; no hemoptysis; no recent trauma or surgery; no prior PE or DVT; no hormone use | Use only when pretest probability is low. All eight negative: no D-dimer or imaging needed. Any positive: continue the workup |
| D-dimer | Rules out PE only when pretest probability is low or unlikely. Age over 50: cutoff is age × 10 ng/mL FEU (see D-dimer) | Negative: PE excluded in unlikely patients. Positive: CTPA |
| PESI or sPESI | Early mortality. The simplified PESI scores one point each for age over 80, cancer, chronic cardiopulmonary disease, heart rate 110 or higher, systolic BP under 100 mmHg, and SpO₂ under 90% | Any positive sPESI item: not low risk; hospital care per protocol |
| Troponin and RV imaging | Positive troponin with RV dysfunction on echo or CT marks intermediate-high risk. See troponin | Both positive in a normotensive patient: hospital admission and PERT review |
Differential & Mimics
- Acute coronary syndrome: Ischemic chest pain with ST changes in a coronary territory points to MI. Here's the catch: PE can raise troponin and cause ST-T changes too, so check both. See Acute Coronary Syndrome
- Pneumonia or pleural disease: fever, productive cough, focal findings on chest exam or film
- Pneumothorax: unilateral absent breath sounds, with tracheal deviation if tension is present
- Heart failure or arrhythmia: crackles, edema, orthopnea, or a known rhythm disorder without a pleuritic pattern
- Asthma or COPD: diffuse wheeze that improves with bronchodilators and has no leg findings
- Aortic dissection: tearing pain, a BP or pulse difference between arms, or a widened mediastinum
BLS Management
- Scene safety and first impression: assess airway, breathing and circulation. Treat a collapsed patient as an arrest until the pulse and breathing are confirmed.
- Oxygen for hypoxemia or distress, titrated to SpO₂ per protocol.
- Position: a position of comfort if breathing is hard and the blood pressure is normal. Supine, with legs raised if tolerated, for hypotension or syncope.
- Activity: stop exertion. Do not let the patient walk to the stretcher.
- Monitor SpO₂, heart rate, BP and mental status. Repeat at each reassessment.
- Collect history: recent surgery, immobility, travel, pregnancy or postpartum status, cancer, hormone use, prior clots, and anticoagulant or antiplatelet use.
- Call for ALS early and transport without delay. Start CPR and standard ACLS if the patient arrests; PE-specific changes are in ED & ICU Management (2025 AHA Guidelines for CPR and ECC, Part 10, section 20).
ALS Management
Doses vary by protocol; follow local protocols and medical direction. Once PE is likely and bleeding risk allows, anticoagulate, per local protocol. Get oxygen going and secure access early.
- IV or IO access and monitoring (Paramedic/RN/CCT): two large-bore lines when possible; continuous ECG and SpO₂. See IO Access
- Unfractionated heparin (Paramedic/RN/CCT, per protocol): 80 units/kg IV bolus, then 18 units/kg/hr, dosed on actual body weight. Titrate to anti-Xa or aPTT; no fixed maximum. See Heparin
- Enoxaparin (inpatient or per protocol): 1 mg/kg subcut every 12 hours, or 1.5 mg/kg subcut once daily, on actual body weight. See Enoxaparin
- Oral anticoagulation for stable patients: apixaban 10 mg by mouth twice daily for 7 days, then 5 mg twice daily; or rivaroxaban 15 mg by mouth twice daily with food for 21 days, then 20 mg once daily with food. DOACs are not used in pregnancy or breastfeeding, and are avoided or adjusted in severe renal impairment, antiphospholipid syndrome (not recommended in triple-positive APS), and with combined strong CYP3A4 and P-gp inhibitors or inducers. Selection is a prescriber or hospital decision.
- Systemic thrombolysis (ED/ICU, PERT decision): alteplase 100 mg IV over 2 hours is the labeled PE regimen, for massive PE with instability. Label timing: give heparin near the end of the infusion or immediately after it, once the partial thromboplastin time or thrombin time is twice normal or less. Heparin timing and regimens vary by protocol; accelerated regimens are protocol-dependent. See Fibrinolytics
- Vasopressor for hypotension (Paramedic/RN/CCT, per protocol): norepinephrine is the first-line agent. Titrate to MAP per protocol. See Norepinephrine
- Airway (Paramedic/RN/CCT): Sedation and intubation are a last resort here, so skip them unless they're required. Positive-pressure ventilation can drop RV preload and BP, so if you do intubate, plan for peri-intubation hypotension. See RSI
- Safety and reversal (high-alert): Heparin, LMWH and thrombolytics all sit on the ISMP high-alert list. Enoxaparin and DOACs carry boxed warnings for spinal or epidural hematoma with neuraxial procedures. DOACs carry a second boxed warning: stop them early and thrombotic risk climbs. Protamine reverses heparin. For LMWH and DOAC reversal, go to Anticoagulant Reversal.
ED & ICU Management
- Diagnosis and risk category: CTPA, echo for RV size and function, troponin and BNP (see BNP). Assign the AHA/ACC category and document it for handoff.
- Categories A and B (low severity): Outpatient care is reasonable for the right low-risk patient: one with a DOAC and early follow-up. Catheter-directed therapy is not recommended.
- Categories C (elevated clinical severity, with or without RV dysfunction): Hospitalize them. Use LMWH over UFH in almost all patients. Catheter-directed therapy plus anticoagulation has uncertain benefit. Reserve it for clinical progression, a call the PERT makes.
- Incipient failure (D1 and D2): Thrombolysis may be considered when bleeding risk is acceptable. If they deteriorate, catheter-directed therapy or mechanical thrombectomy may be considered.
- Category E1 (persistent hypotension or cardiogenic shock): Systemic thrombolysis is recommended if bleeding risk is acceptable. Catheter-directed therapy plus anticoagulation, or mechanical thrombectomy, is reasonable. Norepinephrine is the first-line vasopressor. Dobutamine can be added for low output.
- Category E2 (refractory shock or arrest): Escalate to VA-ECMO when the resources and expertise are there. See ECMO
- Cardiac arrest with suspected or confirmed PE: for confirmed PE, systemic fibrinolysis is reasonable (2025 AHA Guidelines for CPR and ECC, Part 10, COR 2a, LOE B-NR). Surgical and percutaneous mechanical embolectomy are also reasonable. For suspected PE, systemic fibrinolysis may be considered (COR 2b, LOE B-NR). ECLS is reasonable for confirmed or suspected PE (COR 2a, LOE B-NR). How long to keep CPR going after a fibrinolytic is unclear (COR 2b, LOE C-EO). The 2019 ESC guideline that AHA cites suggests at least 60 to 90 minutes. Weigh benefit against bleeding risk.
- Disposition: Every patient in Categories C to E gets PERT review. D and E go to the ICU. Start anticoagulation before any procedure, with the PERT setting the timing.
Transport Considerations
- Destination: D and E need a PERT-capable hospital, and so does anyone who needs advanced therapy. Categories A and B may not need admission. Transfer to the closest appropriate facility per protocol.
- Infusions: continue the running heparin infusion at the same units/kg/hr; confirm the bag concentration at handoff. Check the next anti-Xa or aPTT draw time.
- Thrombolysis in transit: Monitor for bleeding at every line site and for neurologic change. For any major bleed, stop the infusion and notify the receiving team, per the lytic protocol.
- Hemodynamic support: Norepinephrine or dobutamine, per protocol. Give fluid only when the patient clearly responds. In RV failure, excess volume worsens septal shift and output.
- Handoff essentials: category, last vitals, SpO₂ and oxygen, anticoagulant with dose and time, lytic time, weight, allergies, and any bleeding history.
Special Populations
- Pediatrics: PE is uncommon in children. Risk factors include central venous catheters, recent surgery, immobility and prior thrombosis. Outside cardiac arrest, systemic lytics are not established in children, so use specialist care. For a child in cardiac arrest from confirmed PE, AHA 2025 Part 10 rates systemic fibrinolysis reasonable (COR 2a, LOE C-LD). For suspected PE it may be considered (COR 2b, LOE C-EO). Both rest on case series and adult data. ECLS is reasonable for a child in cardiac arrest from confirmed or suspected PE (COR 2a, LOE C-LD). Surgical and percutaneous mechanical embolectomy are also reasonable for confirmed PE (COR 2a, LOE C-LD). Anticoagulant doses are weight-based and set by the specialist. See weight-based dosing
- Pregnancy: Per the guideline summaries, LMWH or UFH are preferred during pregnancy and breastfeeding. DOACs and warfarin are avoided in pregnancy. Pregnancy alone is not an absolute lytic contraindication when PE is life-threatening, and that call belongs to the PERT. Pregnancy needs a modified diagnostic pathway, run by obstetric and imaging teams. Wells and PERC are less validated in pregnancy. Heparins are not expected in milk
- Older Adults: Bleeding risk is higher, especially on heparin and lytics. Age alone does not exclude treatment
- Renal Impairment: When CrCl is under 30 mL/min, UFH is preferred over LMWH. Pull the renal function from the chart
- Obesity: Heparin and enoxaparin dose on actual body weight, per protocol. Anti-Xa is how you titrate
- Patients on Anticoagulants: A DOAC throws off anti-Xa results, so titrate heparin by aPTT until the DOAC has cleared. Lytics given with a current oral anticoagulant raise bleeding risk
Pitfalls & Safety Checks
- Error: Swapping in tenecteplase for PE. Tenecteplase is not labeled for PE. Alteplase is the labeled lytic for massive PE. Any other use is off-label and driven by protocol.
- Error: Starting heparin early in the alteplase infusion. Label timing puts heparin near the end of the infusion or right after it, once the partial thromboplastin time or thrombin time is twice normal or less. Heparin already running? Follow PERT or protocol. Some protocols pause it during the infusion and some continue it.
- Error: Giving a lytic without a contraindication check. Ask about active internal bleeding, bleeding diathesis, uncontrolled severe hypertension, a history of recent stroke, intracranial or intraspinal surgery or serious head trauma within 3 months, intracranial conditions that raise bleeding risk (for example neoplasm, arteriovenous malformation or aneurysm), any prior intracranial hemorrhage, and suspected aortic dissection. The label lists the first six. Prior intracranial hemorrhage and aortic dissection come from guideline contraindication tables. The protocol makes the final call.
- Error: Using PERC or a negative D-dimer when pretest probability is high. Both work only at low or unlikely probability.
- Error: Treating hypotension with fluid or sedation alone. Activate the PERT and start vasopressor support per protocol.
- Error: Mixing up heparin concentrations (1,000, 5,000 and 10,000 units/mL). Name the product, the units/mL and the total units. Have a second clinician check the bolus and rate.
- Error: A missed mimic, such as ACS or aortic dissection, when the story doesn't fit PE. Re-examine before you commit to a lytic.
Clinical Pearls
References
- Creager MA, Barnes GD, Giri J, et al. 2026 AHA/ACC/ACCP/ACEP/CHEST/SCAI/SHM/SIR/SVM/SVN guideline for the evaluation and management of acute pulmonary embolism in adults. Circulation. 2026;153(12):e977–e1051. https://doi.org/10.1161/CIR.0000000000001415
- Kline JA, Mitchell AM, Kabrhel C, et al. Clinical criteria to prevent unnecessary diagnostic testing in emergency department patients with suspected pulmonary embolism. J Thromb Haemost. 2004;2(8):1247–1255 (landmark derivation study). https://doi.org/10.1111/j.1538-7836.2004.00790.x
- Wells PS, et al. Derivation of a simple clinical model to categorize patients probability of pulmonary embolism: increasing the model's utility with the SimpliRED D-dimer. Thromb Haemost. 2000;83:416–420 (landmark derivation study). https://pubmed.ncbi.nlm.nih.gov/10744147/
- Douma RA, et al. Potential of an age adjusted D-dimer cut-off value to improve the exclusion of pulmonary embolism in older patients: a retrospective analysis of three large cohorts. BMJ. 2010;340:c1475 (landmark derivation study). https://pubmed.ncbi.nlm.nih.gov/20354012/
- van der Hulle T, et al. Simplified diagnostic management of suspected pulmonary embolism (the YEARS study): a prospective, multicentre, cohort study. Lancet. 2017;390:289–297. https://doi.org/10.1016/S0140-6736(17)30885-1
- Meyer G, Vicaut E, Danays T, et al. Fibrinolysis for patients with intermediate-risk pulmonary embolism. N Engl J Med. 2014;370:1402–1411 (landmark trial). https://doi.org/10.1056/NEJMoa1302097
- Cao D, Arens AM, Chow SL, et al. Part 10: Adult and pediatric special circumstances of resuscitation: 2025 American Heart Association guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation. 2025;152. https://doi.org/10.1161/CIR.0000000000001380. Full text: https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/adult-and-pediatric-special-circumstances-of-resuscitation
- Genentech, Inc. ACTIVASE (alteplase) prescribing information. U.S. Food and Drug Administration label via DailyMed; revised 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=c669f77c-fa48-478b-a14b-80b20a0139c2
- ELIQUIS (apixaban) tablets prescribing information. U.S. Food and Drug Administration label via DailyMed; revised 2026 (repackager listing). https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=41a133ef-e461-48ad-8221-b735bdd0ec25
- XARELTO (rivaroxaban) tablets prescribing information. Janssen Pharmaceuticals; U.S. Food and Drug Administration label via DailyMed; revised 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=10db92f9-2300-4a80-836b-673e1ae91610
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.