

Bedside Snapshot
- Normal / Therapeutic
- Not detected without recent use. Therapeutic: 10–30 mcg/mL (66–199 µmol/L); this range does not rule toxicity in or out
- Toxic Thresholds
- Acute: ≥150 mcg/mL (993 µmol/L) at 4 h, plotted 4–24 h
- Repeated ingestion: >20 mcg/mL or abnormal AST/ALT
- High risk: ≥300 line or ≥30 g
- Critical: ≥900 mcg/mL with acidosis or altered consciousness
- Toxicity Looks Like
- Early: nothing, or nausea, vomiting, sweating, malaise. Liver injury at 48–72 h: right upper quadrant pain, rising AST/ALT and INR, then encephalopathy, kidney injury, hypoglycemia. Massive dose: early coma, lactic acidosis
- Antidote / Definitive Care
- N-acetylcysteine (NAC) IV or PO, best started within 8 h but still useful late. Activated charcoal if early and airway protected. Hemodialysis for massive levels; transplant center for liver failure
- Act Now If
- Level on or above the line, >200 mg/kg or >10 g reported, unknown time, or AST/ALT up: start NAC (never wait past 8 h for a result); call Poison Control 1-800-222-1222
- Watch Out For
- Hidden acetaminophen in combination products: send a level in every intentional overdose, even when the patient denies taking it
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult, no recent use | Not detected | Not detected | Below the assay's reporting limit, which varies by laboratory |
| Adult, therapeutic dosing | 10–30 mcg/mL | 66–199 µmol/L | Typical level during usual dosing. It describes therapy, not overdose risk |
| Pregnancy | Same as adult | Same as adult | Same overdose thresholds and treatment |
| Children | Same as adult | Same as adult | Same nomogram and overdose thresholds |
Severity & critical values
| Level | Concentration | When to draw | Meaning |
|---|---|---|---|
| Not detected | Below the reporting limit | 4 h or later after ingestion; nondetectable at 2–4 h typically excludes a significant ingestion, but not with extended-release, opioid or anticholinergic co-ingestion (repeat at 4 h or later) | No significant acute ingestion if the time is reliable. After a late or repeated ingestion, AST/ALT still decides |
| Below the treatment line | Under 150 mcg/mL at 4 h (37.5 at 12 h) | 4–24 h after an acute ingestion | NAC not indicated by the nomogram. Extended-release or anticholinergic/opioid co-ingestion with a level >10 mcg/mL: repeat |
| Repeated ingestion threshold | >20 mcg/mL (132 µmol/L), or abnormal AST/ALT | At presentation | Give NAC. The nomogram does not apply |
| Treatment line | ≥150 mcg/mL (993 µmol/L) at 4 h, halving every 4 h to 4.7 at 24 h | 4–24 h after an acute ingestion | Give a full N-acetylcysteine (NAC) course |
| High risk | ≥300 mcg/mL (1,986 µmol/L) at 4 h (high-risk line), or ≥30 g ingested | 4–24 h after an acute ingestion | Above 300 at 4 h was linked to liver damage in 90% of patients. Toxicologist: increased NAC dose, late charcoal |
| Critical | ≥900 mcg/mL (5,960 µmol/L) with acidosis or altered consciousness | Any time | Massive ingestion: hemodialysis plus NAC. Lower-level dialysis with severe acidosis is a toxicologist decision |
Conversion: mcg/mL = mg/L; mcg/mL × 6.62 = µmol/L (150 mcg/mL = 993 µmol/L; Australia and New Zealand round the 4 h line to 1,000 µmol/L)
Causes of Abnormal Results
A detectable level tells you there was exposure. The harder question is whether the dose, the timing and the pattern put the liver in danger. Hepatotoxicity means AST or ALT above 1,000 U/L.
Sources & routes of exposure
| Source | Examples | Bedside clue |
|---|---|---|
| Combination products | Opioid combinations (hydrocodone or oxycodone with acetaminophen); cold, flu, sleep and headache remedies | Patients often do not know the product contains acetaminophen. Opioid or anticholinergic effects can delay absorption |
| Single-agent oral products | Immediate-release and extended-release tablets, liquids | Ask specifically about extended-release products: absorption and peak can be delayed |
| Repeated therapeutic-intent dosing | Several products at once, or doses above the label for pain or fever over days | Toothache, headache or fever treated for days; nausea, vomiting, abdominal pain |
| IV acetaminophen | Dosing errors, mostly in small children (mg vs mL, weight errors) | Hospital-acquired. The nomogram is not validated for IV exposures |
| Pediatric exploratory ingestion | Liquid formulations in children under 6 | Unwitnessed; time and amount uncertain |
Risk factors for toxicity
| Factor | Why it matters | Practical point |
|---|---|---|
| Large dose | Acute ≥10 g or ≥200 mg/kg (whichever is less) needs risk assessment; ≥30 g is high risk | The reported dose is often wrong: the level and AST/ALT decide. IV labeling maximum for adults 50 kg and over is 4 g/day (75 mg/kg/day under 50 kg) |
| Delay to NAC beyond 8 h | Protection is greatest when NAC starts 0–8 h after ingestion | Start NAC empirically rather than wait past 8 h for a result |
| Extended-release product | Prolonged absorption; a level can cross the line later | Repeat the level if the first is above 10 mcg/mL but below the line |
| Anticholinergic or opioid co-ingestion | Slowed gastric emptying delays the peak | Repeat if >10 mcg/mL and the patient shows anticholinergic or opioid effects |
| Repeated supratherapeutic ingestion (RSI) | Australia/New Zealand thresholds: ≥10 g or ≥200 mg/kg in 24 h; ≥12 g or ≥300 mg/kg in 48 h; or therapeutic doses for >48 h with abdominal pain, nausea or vomiting | Nomogram does not apply; use the level plus AST/ALT |
| Chronic alcohol use, malnutrition or fasting, CYP2E1 inducers (e.g. isoniazid) | May increase toxic metabolite formation or deplete glutathione | Current US/Canada and Australia/New Zealand guidelines keep the same 150 line; discuss borderline cases with a toxicologist |
Acute vs acute-on-chronic vs chronic
| Pattern | Definition | How to assess | Treat with NAC if |
|---|---|---|---|
| Acute (single or staggered) | All ingestion within a period of less than 24 h | Level 4–24 h after the earliest possible ingestion time; plot it | On or above the treatment line |
| Unknown or unreliable time | History lacks dose or time, conflicts, or does not fit the labs | No nomogram; level plus AST/ALT | Start NAC; the level and AST/ALT decide whether to continue |
| Late presentation | Level drawn more than 24 h after ingestion | Level, AST/ALT, INR | Signs or symptoms of toxicity: start while results are pending |
| Repeated supratherapeutic (acute-on-chronic or chronic) | Multiple ingestions over more than 24 h | Level plus AST/ALT; no nomogram | APAP >20 mcg/mL or abnormal AST/ALT |
Low or undetectable
Not detected is the normal result. A low or undetectable level cannot clear liver injury after a late presentation or a repeated ingestion. AST/ALT and INR decide.
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Line up the draw time against the ingestion time. Confirm the units (mcg/mL vs µmol/L) and the tube. A level drawn before 4 h cannot be plotted.
- How sick is the patient? Early coma, metabolic acidosis or high lactate points to a massive ingestion (mitochondrial toxicity) or a co-ingestant. Check glucose, blood gas, lactate, AST/ALT, INR and creatinine.
- Define the ingestion: Sort it into acute (any ingestion period under 24 h, timed from the earliest possible ingestion), repeated supratherapeutic (over 24 h) or unknown time. If you are in doubt, treat the history as unreliable.
- Plot or apply the rule: Acute with a reliable time: plot a level drawn 4–24 h on the revised Rumack-Matthew nomogram (Figure 1). RSI: APAP >20 mcg/mL or abnormal AST/ALT. Unknown time: start NAC, then let the level and AST/ALT decide.
- Look for reasons to repeat: An extended-release product, or an anticholinergic or opioid co-ingestion, changes the plan. With a level above 10 mcg/mL but below the line, repeat 4–6 h after the first (2023 US/Canada consensus).
- Escalate or dispose: Call Poison Control (1-800-222-1222) for every treated patient. Call a toxicologist for high-risk ingestions and a transplant center for progressive liver injury. Below the line, with a reliable history and normal AST/ALT, acetaminophen needs no NAC.
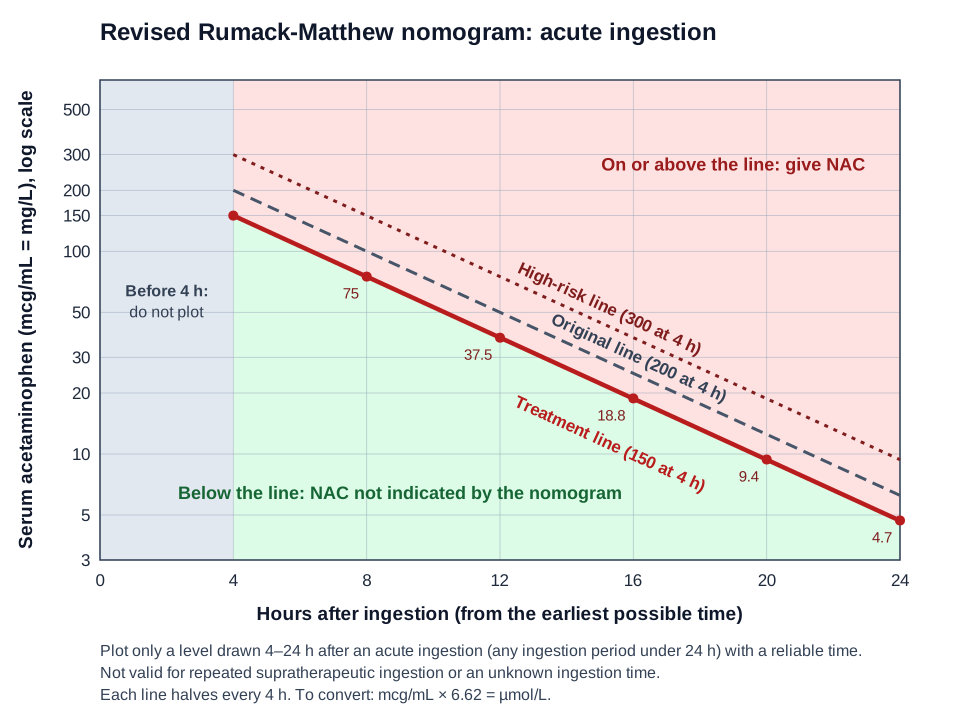
Read the line off these points: 150 at 4 h, 75 at 8 h, 37.5 at 12 h, 18.8 at 16 h, 9.4 at 20 h, 4.7 at 24 h.
Decision table
| Situation | Level or finding | Action |
|---|---|---|
| Acute, 4–24 h | On or above the treatment line | Full NAC course |
| Acute, 4–24 h, immediate-release, no co-ingestant | Below the line | No NAC for acetaminophen |
| Extended-release product | Level 4–12 h after ingestion above 10 mcg/mL but below the line | Repeat 4–6 h after the first; treat if any level is on or above the line (Acetadote label: second level 8–10 h after ingestion) |
| Anticholinergic or opioid co-ingestion | 10 mcg/mL or less at 4–24 h | No repeat and no NAC. Above 10 but below the line with anticholinergic or opioid effects: repeat 4–6 h later |
| Level drawn 2–4 h after ingestion | Not detected | Typically excludes a significant ingestion; not with extended-release, opioid or anticholinergic co-ingestion, which delay absorption: repeat at 4 h or later. Confirm with Poison Control |
| Reported >200 mg/kg or >10 g | Result not back by 8 h after ingestion | Start NAC before the result |
| IV acetaminophen error | Any level | Nomogram not validated. Children under 6: Poison Control after a single IV dose ≥90 mg/kg or >150 mg/kg in 24 h |
Management Priorities
Emergency: Suspected acetaminophen overdose
- Assess and send labs: Airway, breathing, circulation, glucose, ECG and co-ingestants come first. Then the labs: an acetaminophen level 4 h or more after ingestion (or on arrival if later), AST/ALT, creatinine and electrolytes. Add INR if AST/ALT are raised or liver injury is suspected, plus a pregnancy test when relevant.
- Decontaminate: consider single-dose activated charcoal for a potentially toxic acute ingestion, as long as the airway is protected. Late charcoal may still help after 4 h in a high-risk or extended-release ingestion.
- Start the antidote: Give NAC when the level sits on or above the line. Give it too for a reported >200 mg/kg or >10 g when the result will not return by 8 h, for an unknown or unreliable time, for late presentation with toxicity, or for RSI criteria.
- Do not stop on the clock: Before the last bag ends, check APAP, AST/ALT and INR again. Stop only when the stopping criteria say so. Until then, NAC keeps running.
- Call: Phone Poison Control at 1-800-222-1222 for every treated patient.
Emergency: Massive ingestion (APAP ≥900 mcg/mL with acidosis or altered consciousness)
- Remove: Hemodialysis goes on top of NAC. Under 900 mcg/mL with severe acidosis, dialysis is a call for the toxicologist or nephrology. Phone Poison Control early.
- Protect the antidote: Dialysis strips out NAC, so keep IV NAC at 12.5 mg/kg/hr or more for the whole run.
- Dose up with expert input: A toxicologist can raise the NAC dose for ≥30 g or a level above the 300 line. Fomepizole is a toxicologist-only call, since the data do not back a standard recommendation.
- Monitor and repeat: Keep the patient in ICU care. Track glucose, blood gas, lactate, AST/ALT, INR and repeat levels.
Medications
Doses vary by protocol; follow local protocols and medical direction.
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Acetylcysteine (NAC) IV, two-bag | 200 mg/kg IV over 4 hr, then 100 mg/kg IV over 16 hr (dosing weight capped at 100 kg: max 20 g, then 10 g) | 41 kg and up: adult dose. 40 kg or less: not used; give the three-bag regimen | FDA-labeled. Total 300 mg/kg in 20 hr; fewer anaphylactoid reactions than three-bag |
| Acetylcysteine (NAC) IV, three-bag | 150 mg/kg IV over 1 hr, then 50 mg/kg over 4 hr, then 100 mg/kg over 16 hr (max 15 g, 5 g, 10 g at the 100 kg cap) | Same mg/kg from 5 kg; reduced fluid volumes at 40 kg or less (hyponatremia risk); adult maximums | Never run the load over less than 1 hr. Total 300 mg/kg in 21 hr |
| Acetylcysteine (NAC) IV, continued | 6.25 mg/kg/hr IV (the final-bag rate) until stopping criteria are met; 12.5 mg/kg/hr or more during hemodialysis | Same mg/kg/hr; no fixed max, toxicologist-directed | Higher-dose regimens for high-risk ingestion only with a toxicologist |
| Acetylcysteine (NAC) PO | 140 mg/kg PO, then 70 mg/kg PO every 4 hr for 17 doses (dosing weight capped at 100 kg) | Same mg/kg; adult maximums | Dilute to 5%. Repeat a dose vomited within 1 hr. Use when IV is unavailable |
| Activated charcoal | 50–100 g PO, single dose | 25–50 g PO, single dose (max 50 g) | Only with a protected airway. Australia/New Zealand: within 2 h of a toxic dose, within 4 h for >30 g. Adsorbs oral NAC |
Pediatric fluid volumes and diluents: see the NAC page and weight-based dosing.
Definitive care & disposition
- Stopping criteria: per the ACMT 2026 practice statement, APAP <10 mcg/mL; AST/ALT at the patient's baseline or down 25–50% from peak; INR <2.0; creatinine, lactate, pH and phosphate improving. Criteria vary by protocol.
- Hepatotoxicity (AST or ALT >1,000 U/L): continue NAC; ICU for encephalopathy, rising INR, acidosis or hypoglycemia. Give plasma or clotting factors only for bleeding or after discussion with the liver unit: INR is a prognostic marker.
- Transplant referral: progressive AST/ALT rise with coagulopathy, or encephalopathy or multisystem failure despite NAC. King's College Criteria (acetaminophen): arterial pH <7.30, or all three of PT >100 s (INR >6.5), creatinine >3.4 mg/dL (300 µmol/L) and grade III–IV encephalopathy. Australia/New Zealand referral triggers include INR >3.0 at 48 h or >4.5 at any time, or creatinine >200 µmol/L (2.3 mg/dL).
- Medically clear: acute ingestion below the line with a reliable history and normal AST/ALT, or stopping criteria met; then assess co-ingestants and psychiatric safety.
These doses are typical references. Stick to local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
There is no prehospital acetaminophen test. The level comes from the hospital lab. Your field tools still matter, though. Use a glucometer for hypoglycemia. On critical-care transport, a cartridge blood-gas analyzer covers acidosis and lactate.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| EMS scene | Bring every container. Record the product (extended-release, combination), amount, earliest possible ingestion time and co-ingestants. Poison Control: 1-800-222-1222 |
| Sending facility | Send levels with draw times, AST/ALT, INR, creatinine, glucose and lactate; NAC start time, regimen, bag number and rate; charcoal time |
| En route | Keep NAC running; transfer must not delay the first dose past 8 h after ingestion. Watch for reactions during the loading bag. Recheck glucose when the liver is injured |
| Destination | Encephalopathy, rising INR or acidosis: a center with toxicology and liver transplant. Massive level: hemodialysis capability |
Timing & Kinetics
| Parameter | Value | Clinical implication |
|---|---|---|
| First plottable level | 4 h after ingestion | Earlier levels may be misleading because absorption is incomplete |
| Nomogram window | 4–24 h | Beyond 24 h, use AST/ALT, INR and the clinical picture |
| Treatment line decay | Halves every 4 h (150 at 4 h to 4.7 mcg/mL at 24 h) | A low-looking late level can still be above the line |
| Half-life, therapeutic dose | About 2–3 hr | Prolonged after overdose and with liver injury |
| Extended-release or co-ingestion | Delayed peak | Repeat 4–6 h after a first level above 10 mcg/mL (Acetadote label: 8–10 h after ingestion) |
| NAC window | Greatest protection when started 0–8 h | Efficacy falls after 8 h, but NAC still helps late and in liver failure |
| Early course | None, or nausea, vomiting, diaphoresis and malaise | A well patient early on is not reassurance |
| Liver injury | May not be apparent until 48–72 h | Repeat AST/ALT every 24 h while monitoring; recheck APAP, AST/ALT and INR before stopping NAC |
| Massive ingestion | Early coma, metabolic acidosis and high lactate | Mitochondrial toxicity before liver injury; check dialysis criteria |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Limited data; NAC dosing below 5 kg has not been studied | Poison Control or a toxicologist for every exposure |
| Children & adolescents | Same nomogram and thresholds. Under 6 yr, IV errors: single dose ≥90 mg/kg or >150 mg/kg in 24 h | Australia/New Zealand guideline only: liquid ingestion >200 mg/kg under 6 yr, level at 2 h; under 150 mcg/mL needs no NAC. US/Canada consensus manages children under 6 the same as older patients, using the 4 h level. NAC volumes are reduced at 40 kg or less |
| Pregnancy | Same thresholds and treatment; acetaminophen and NAC cross the placenta | Pregnancy test in every patient who could be pregnant. Do not delay NAC; oral NAC has not been shown to be less effective than IV. Involve obstetrics |
| Older adults | No different thresholds | Review every prescription and over-the-counter product for hidden acetaminophen |
| Obesity | NAC dosing weight capped at 100 kg | Apply the cap to every bag |
| CKD / dialysis | Nomogram unchanged; hemodialysis removes NAC | Raise the NAC rate during dialysis (Management Priorities) |
| Liver disease, chronic alcohol use, malnutrition | May increase susceptibility | Same 150 line per the 2023 US/Canada consensus and 2020 Australia/New Zealand guideline; discuss borderline levels with a toxicologist |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Level drawn before 4 h | False − | Absorption incomplete | Repeat at 4 h or later |
| Wrong time zero | Misplotted | Staggered or uncertain ingestion times | Use the earliest possible time; if unreliable, do not plot |
| Gel-barrier tube | ↓ | Gel can absorb the drug | Red-top or green-top (heparin) tube, per lab |
| Hemolysis, gross lipemia, icterus | Unreliable (sample may be rejected) | Interference with enzymatic (colorimetric) assays | Recollect; ask the lab about another method |
Assay & device-specific
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Units mix-up | 6.6-fold ↑ or ↓ | µmol/L reported where mcg/mL is expected, or the reverse | Confirm units before plotting |
| Reporting limit | “Not detected” cutoff differs | Assay-specific | Know your laboratory's limit |
Common misinterpretations
- “Therapeutic range means safe”: 10–30 mcg/mL describes dosing, not safety. After an overdose, plot the level or apply the RSI rule.
- Plotting the wrong patient: An RSI, an unknown time or an IV error cannot go on the nomogram.
- One level and done: Extended-release or anticholinergic/opioid co-ingestion with a level above 10 mcg/mL needs a repeat. Do not stop at one level.
- Undetectable after a late presentation: The drug may be gone, but liver injury can still progress. AST/ALT and INR decide.
Physiology & Test Basics
What it measures
You are measuring the parent drug in serum or plasma: acetaminophen (APAP, paracetamol). Not the toxic metabolite, and not liver injury. So every overdose level travels with AST/ALT and INR.
Physiology & regulation
- Usual metabolism: Most of it goes through hepatic glucuronidation and sulfation.
- Toxic pathway: A small fraction is oxidized, mainly by CYP2E1, into NAPQI (N-acetyl-p-benzoquinone imine). Glutathione detoxifies it.
- Overdose: Conjugation saturates. Glutathione runs out. Free NAPQI injures hepatocytes.
- Antidote: NAC restores glutathione, which helps detoxify NAPQI.
- Massive ingestion: Mitochondrial dysfunction shows up early. It causes coma, acidosis and high lactate.
- Other organs: Renal tubular necrosis, hypoglycemic coma and thrombocytopenia may also occur.
How it is measured
- Specimen: serum or plasma; red-top or green-top (heparin) tube. Avoid gel-barrier tubes.
- Method: enzymatic (colorimetric) assays on hospital chemistry analyzers; immunoassays also exist.
- Units: US laboratories report mcg/mL (= mg/L); others use mg/L or µmol/L.
- Timing: Record the draw time. The first plottable level comes 4 h or more after an acute ingestion.
Why it matters
Early toxicity gives no warning. NAC protects best when started within 8 h. Get the timing right, because a correctly timed and plotted level drives a decision that cannot wait.
Clinical Pearls
References
- Dart, R. C., Mullins, M. E., Matoushek, T., Ruha, A. M., Burns, M. M., Simone, K., et al. (2023). Management of acetaminophen poisoning in the US and Canada: A consensus statement. JAMA Network Open, 6(8), e2327739. https://doi.org/10.1001/jamanetworkopen.2023.27739
- American College of Medical Toxicology; Meadows, J., Hendrickson, R., & Stolbach, A. (2026). ACMT practice statement: Duration of intravenous acetylcysteine therapy following acetaminophen overdose (2026 update). https://www.acmt.net/wp-content/uploads/2026/01/ACMT-Duration-of-IV-NAC-STATEMENT-1_21_26.pdf
- Chiew, A. L., Reith, D., Pomerleau, A., Wong, A., Isoardi, K. Z., Soderstrom, J., & Buckley, N. A. (2020). Updated guidelines for the management of paracetamol poisoning in Australia and New Zealand. Medical Journal of Australia, 212(4), 175–183. https://doi.org/10.5694/mja2.50428
- Cumberland Pharmaceuticals. (2025). Acetadote (acetylcysteine) injection, for intravenous use [prescribing information] (revised July 2025). DailyMed, National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=472f158a-5ab9-4308-8e49-1116e6ea3d39
- Mylan Institutional LLC. (2026). Acetaminophen injection, for intravenous use [prescribing information] (revised March 2026; Overdosage section). DailyMed, National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=1d456d07-fca2-4d43-92c0-f3b3c8b54420
- Labcorp. (2026). Acetaminophen (test 007740): specimen requirements and reference interval. Labcorp test menu. https://www.labcorp.com/tests/007740/acetaminophen
- Rumack, B. H., & Matthew, H. (1975). Acetaminophen poisoning and toxicity. Pediatrics, 55(6), 871–876 (landmark derivation of the nomogram). https://doi.org/10.1542/peds.55.6.871
- O'Grady, J. G., Alexander, G. J., Hayllar, K. M., & Williams, R. (1989). Early indicators of prognosis in fulminant hepatic failure. Gastroenterology, 97(2), 439–445 (landmark derivation of the King's College Criteria). https://doi.org/10.1016/0016-5085(89)90081-4
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.