

Bedside Snapshot
- Normal (Adult)
- 25–35 s (25–35 s SI); typical, reagent-specific. On UFH: the lab's heparin range, calibrated to anti-Xa 0.3–0.7 units/mL
- Critical Values
- No critical low. ≥100 s (typical; lab-specific). Argatroban: 1.5–3× baseline, never above 100 s
- High Suggests
- Heparin, argatroban, bivalirudin, dabigatran
- DIC, massive transfusion, liver failure
- Hemophilia A/B, acquired factor VIII inhibitor
- Lupus anticoagulant; line-contaminated draw
- Low Suggests
- Rarely clinically significant: high factor VIII (inflammation, pregnancy) or emicizumab. It can mask heparin effect, so dose by anti-Xa
- Act Now If
- Bleeding with a long aPTT, or ≥100 s on an anticoagulant: stop the infusion, assess for bleeding, send CBC, PT/INR, fibrinogen; reverse by cause (protamine for UFH). Hemophilia with head injury: factor first
- Watch Out For
- A draw through a heparinized line or an underfilled blue top gives a falsely long aPTT; redraw correctly before holding or cutting a heparin drip
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult | 25–35 s | 25–35 s | Typical; each reagent and analyzer has its own interval |
| Pregnancy | Same as adult | Same as adult | Often at the low end: factor VIII and fibrinogen rise |
| Older adult | Same as adult | Same as adult | — |
| Neonate, term | Lab-specific, gestation-specific; longer than adult | Lab-specific | Use the lab's gestation-specific range; preterm infants run longest. The system matures over the first months |
| Infant and child | Lab age-specific range | — | Close to adult after infancy |
Severity & critical values
| Level | Conventional | SI | What it means / typical findings |
|---|---|---|---|
| Short | <25 s | <25 s | Usually high factor VIII (inflammation, pregnancy) or emicizumab; can hide heparin effect |
| Normal | 25–35 s | 25–35 s | Does not exclude mild hemophilia, von Willebrand disease, a platelet disorder or an apixaban/rivaroxaban effect |
| Prolonged, no anticoagulant | >35 s | >35 s | Repeat on a clean sample; if still long, mixing study and factor assays |
| Therapeutic UFH | Lab heparin range | Lab heparin range | Calibrated locally to anti-Xa 0.3–0.7 units/mL; label wording 1.5–2× normal |
| Argatroban (HIT) | 1.5–3× baseline | 1.5–3× baseline | Not above 100 s |
| Critical | ≥100 s | ≥100 s | Typical; lab-specific. Bleeding risk on heparin or a direct thrombin inhibitor; consumptive or severe factor deficiency if unexplained |
Conversion: No conversion needed. The aPTT is in seconds in both conventional and SI units.
Normal is about 1.0. Labels state their targets as ratios: UFH 1.5–2× normal, argatroban 1.5–3× baseline.
Causes of Abnormal Results
High (prolonged aPTT >35 s)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Anticoagulant drug | Unfractionated heparin (UFH), argatroban, bivalirudin, dabigatran; less reliably rivaroxaban, apixaban, LMWH, warfarin at a high INR | Medication list; time of the last dose or rate change |
| Consumption | Disseminated intravascular coagulation (DIC): sepsis, trauma, obstetric catastrophe, malignancy | PT also long; low platelets and fibrinogen, high D-dimer; oozing lines |
| Dilution and blood loss | Massive hemorrhage resuscitated with red cells and crystalloid | PT also long; fibrinogen falls early |
| Reduced synthesis | Liver failure, vitamin K deficiency, warfarin | PT/INR rises first and further than the aPTT |
| Inherited factor deficiency | Hemophilia A (factor VIII) or B (factor IX); factor XI deficiency; von Willebrand disease with low factor VIII | Joint or muscle bleeds, family history, bleeding after surgery or dental work; normal PT |
| Acquired factor inhibitor | Acquired hemophilia (autoantibody against factor VIII) | New extensive bruising or muscle bleeds with no prior bleeding history |
| Phospholipid antibody | Lupus anticoagulant (antiphospholipid syndrome) | History of clots or pregnancy loss; no bleeding |
| Contact factor deficiency or specimen error | Factor XII, prekallikrein or high-molecular-weight kininogen deficiency; heparinized-line draw; underfilled tube; hematocrit >55% | Long aPTT in a well patient with no bleeding history |
Hemophilia severity (factor activity)
| Severity | Factor VIII or IX | Bleeding pattern |
|---|---|---|
| Severe | <1 IU/dL (<1% of normal) | Spontaneous joint and muscle bleeds |
| Moderate | 1–5 IU/dL | Occasional spontaneous bleeds; prolonged bleeding after minor trauma or surgery |
| Mild | 5–40 IU/dL | Severe bleeding with major trauma or surgery; spontaneous bleeding rare. The aPTT can be normal |
Low (shortened aPTT <25 s)
A short aPTT rarely matters clinically. It is usually high factor VIII from inflammation or pregnancy, or emicizumab, which shortens the aPTT whatever the factor VIII level. The real danger is that it hides heparin effect and looks like heparin resistance. Dose by anti-Xa instead.
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Confirm a full light-blue top drawn away from heparin. Redraw an unexpected result in a well patient before acting on it.
- How sick is the patient? Bleeding, a falling hemoglobin, hypotension or a new neurologic deficit makes any prolonged aPTT an emergency. See Management Priorities.
- Is a drug expected to prolong it? Heparin (including flushes and ECMO, dialysis or Impella circuits), argatroban, bivalirudin, dabigatran.
- Read it with the PT/INR. Read the pair together. The pattern narrows the problem (table below).
- Mixing study if unexplained. Mix patient plasma 1:1 with normal plasma. Test it right away and again after 1–2 hours at 37 °C (98.6 °F).
- Targeted tests. Let the mix and history choose: factor VIII, IX, XI and XII assays, von Willebrand studies, lupus anticoagulant or factor VIII inhibitor (Bethesda) testing.
- Escalate or dispose. Bleeding with an unexplained long aPTT, or a suspected inhibitor, means hematology now. Otherwise, outpatient workup comes before any elective procedure.
PT/INR and aPTT pattern
| PT/INR | aPTT | Suggests |
|---|---|---|
| Normal | Prolonged | Heparin, argatroban, bivalirudin or dabigatran; factor VIII, IX, XI or XII deficiency; von Willebrand disease; lupus anticoagulant; acquired hemophilia |
| Prolonged | Normal | Early warfarin effect or vitamin K deficiency, early liver disease, factor VII deficiency |
| Prolonged | Prolonged | DIC, massive transfusion, severe liver disease, high-INR warfarin, high-level anticoagulant, factor X, V, II or fibrinogen deficiency |
| Normal | Normal, but bleeding | Platelet disorder or thrombocytopenia, von Willebrand disease, mild hemophilia, factor XIII deficiency, apixaban or rivaroxaban |
Mixing study
| Pattern | Suggests |
|---|---|
| Corrects immediately and stays corrected | Factor deficiency |
| Does not correct immediately | Lupus anticoagulant or a drug in the sample (heparin, direct thrombin inhibitor) |
| Corrects at first, prolongs after 1–2 h incubation | Time-dependent factor VIII inhibitor (acquired hemophilia or an inhibitor in treated hemophilia) |
aPTT as an anticoagulant monitor
- UFH: anti-Xa is the preferred test (2026 ISTH guidance, 0.3–0.7 units/mL for most indications). If you use the aPTT, the lab sets a local heparin range for its reagent. A fixed 1.5–2.5× control ratio is outdated.
- Argatroban (HIT): Target 1.5–3× baseline, never above 100 s. Check it 2 hr after the start and after each change.
- Dabigatran: a long aPTT suggests the drug is present. A normal aPTT rules out relevant levels only with a sensitive reagent. For apixaban, rivaroxaban, edoxaban and LMWH, use anti-Xa.
Management Priorities
Doses vary by protocol; follow local protocols and medical direction.
Emergency: Bleeding with a prolonged aPTT
- Stop the source: shut off heparin, argatroban or bivalirudin infusions and any heparin flushes. Write down the last dabigatran dose. Press directly on the bleed, get large-bore access, type and crossmatch.
- Labs: CBC, PT/INR, aPTT and fibrinogen, plus anti-Xa on heparin or thrombin time on dabigatran. Repeat them after each intervention.
- Reverse by cause: UFH gets protamine. Dabigatran gets idarucizumab. For apixaban or rivaroxaban, reverse per the 2020 ACC pathway and local protocol (4F-PCC or andexanet, depending on availability). Argatroban and bivalirudin have no antidote, so stop and support (argatroban effect fades over 2–4 h, longer in liver disease). Hemophilia gets factor concentrate. Mild hemophilia A or type 1 von Willebrand disease with minor bleeding gets desmopressin, directed by hematology (no effect in hemophilia B or severe hemophilia A, and watch for hyponatremia and tachyphylaxis). DIC, dilution or liver disease gets blood products per the massive transfusion protocol.
- Monitor & repeat: Repeat the aPTT or anti-Xa after reversal. Heparin can rebound after protamine. The aPTT can climb again 12–24 h after idarucizumab.
Emergency: Known hemophilia with head injury or major bleed
- Factor first: For significant head trauma or suspected intracranial bleeding, infuse factor concentrate at once. Don't wait for symptoms, labs or imaging. Use the patient's own product and plan when available.
- Dose to a target: Aim for factor VIII at 80–100 IU/dL in hemophilia A and factor IX at 60–80 IU/dL in hemophilia B (table below).
- Inhibitor or emicizumab: Bypassing agents only as the hemophilia treatment center directs. aPCC given with emicizumab carries a thrombotic microangiopathy and thrombosis risk (Hemlibra boxed warning). On emicizumab, the aPTT is off the table.
- Call and transfer: Call the hemophilia treatment center or hematology, order a head CT, and admit to a center with factor and coagulation lab support.
Medications
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Protamine sulfate | UFH reversal: 1 mg per 100 units of heparin still circulating (infusion: heparin given in the last 2–3 hr), very slow IV; no more than 50 mg in any 10 min | Same ratio, not weight-based; max 50 mg per dose | Neutralizes within 5 min. Boxed warning: severe hypotension, cardiovascular collapse, noncardiogenic pulmonary edema, catastrophic pulmonary vasoconstriction; higher risk with high dose or rapid injection, fish allergy, prior protamine exposure, NPH insulin, vasectomy. Give slowly with resuscitation equipment ready; not for bleeding without prior heparin. Partial for LMWH; no effect on dabigatran, argatroban or bivalirudin |
| Idarucizumab | Dabigatran reversal: 5 g IV (two 2.5 g/50 mL vials); single 5 g dose; repeat only for recurrent bleeding with prolonged tests (limited data) | Not established in children: consult | Immediate; dabigatran only. aPTT may rise again at 12–24 h |
| Factor VIII concentrate | Hemophilia A, intracranial or life-threatening bleed: about 50 units/kg IV (each unit/kg raises factor VIII about 2 IU/dL); target peak 80–100 IU/dL; repeat per level and treatment plan | Same weight-based calculation and target; half-life shorter in young children, so redosing may be sooner | Standard half-life about 12 hr in adults; check a peak level 15–30 min after the dose |
| Factor IX concentrate | Hemophilia B, intracranial or life-threatening bleed: plasma-derived 60–80 units/kg IV (each unit/kg raises factor IX about 1 IU/dL); standard recombinant needs about 1.25× that; target peak 60–80 IU/dL | Same target; standard recombinant about 1.43× the plasma-derived dose under 15 years; repeat per level | Standard half-life 18–24 hr; extended half-life products differ: follow the patient's plan |
| Heparin (UFH) infusion | VTE: 80 units/kg IV bolus, then 18 units/kg/hr (actual body weight); titrate by nomogram to the lab aPTT range or anti-Xa 0.3–0.7 units/mL: no fixed max | 75–100 units/kg IV bolus over 10 min, then 25–30 units/kg/hr (infants; under 2 months average 28) or 18–20 units/kg/hr (over 1 yr); bolus not above the adult bolus; aPTT 60–85 s (anti-Xa 0.35–0.7). Pediatric dosing is based on clinical experience and is protocol-dependent | High-alert Level 6 hr after start and each change; hold or reduce for a level above range |
Definitive care & disposition
- Unexplained prolonged aPTT with bleeding: hematology consult; mixing study, factor assays and inhibitor testing.
- Treat the cause, not the number: Plasma does not correct a lupus anticoagulant, a heparin effect or factor XII deficiency. A non-bleeding patient with an isolated long aPTT needs a diagnosis, not a transfusion.
- Suspected HIT on heparin: Stop all heparin and switch to a non-heparin anticoagulant. For argatroban, take a baseline aPTT, wait for the heparin effect to fall, then titrate to 1.5–3× baseline (not above 100 s).
- ICU criteria: intracranial or airway bleeding, ongoing transfusion need, reversal with hemodynamic instability, or a hemophilia patient with a major bleed.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
In most settings the aPTT is a lab test. Some cath labs, ORs and ECMO programs run whole-blood point-of-care clotting devices (aPTT or activated clotting time, ACT). Their results can't be swapped for the lab plasma aPTT. Trend one method and compare like with like.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Handoff (Paramedic/RN/CCT) | Record the last aPTT or anti-Xa with draw time, the infusion rate in units/kg/hr, bag concentration, last bolus and rate change, and when the next level is due |
| Running heparin infusion | Run at the ordered rate on a pump per local protocol; no titration without a new, correctly timed level and an order |
| New bleeding en route | Stop the anticoagulant infusion, apply pressure, notify medical control and the receiving team; reversal per protocol |
| Hemophilia patient | Bring the patient's factor product and treatment plan; give factor per protocol before or during transport for head injury |
| When to delay or redirect | Intracranial or airway bleeding on anticoagulation, or hemophilia with a major bleed: go to a center with hematology, blood bank and neurosurgery |
Timing & Kinetics
| Parameter | Value | Clinical implication |
|---|---|---|
| UFH IV | Immediate effect; half-life 0.5–2 hr (dose-dependent) | Effect wanes over hours after stopping; for protamine math, assume a half-life of about 30 min |
| UFH: when to draw | About 6 hr after the start and after each rate change (label: about every 4 hr early in therapy); daily once 2 consecutive levels are in range | A level drawn too soon after a change does not reflect the new rate |
| Argatroban | Steady state 1–3 hr; half-life 39–51 min; back to baseline 2–4 hr after stopping | Check the aPTT 2 hr after start and each change; slower in hepatic impairment |
| Idarucizumab | Reverses dabigatran immediately | Re-check the aPTT; it can rise again 12–24 hr later |
| Factor VIII / IX concentrate | Peak 15–30 min; standard half-life about 12 hr (VIII) and 18–24 hr (IX) | Peak factor levels, not the aPTT, guide redosing |
| Heparin-monitoring sample | Centrifuge within 1 hr of collection; test promptly | Delay lets platelets release factor 4, which neutralizes heparin and falsely lowers the result |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | aPTT longer than adult at birth, longest in preterm infants; the system matures over the first months | Use the lab's age- and gestation-specific range; a heparin draw from an umbilical or central line is a common cause of a long result |
| Children & adolescents | Close to adult values; lab age-specific intervals | Heparin target on the label: aPTT 60–85 s, assuming it reflects anti-Xa 0.35–0.7 units/mL |
| Pregnancy | Factor VIII and fibrinogen rise; aPTT normal or slightly short | Can under-read heparin effect; lupus anticoagulant testing in pregnancy may be misleading, so confirm after delivery |
| Older adults | No clinically meaningful difference | A new long aPTT with bleeding and no anticoagulant raises concern for acquired hemophilia |
| CKD / dialysis | Dabigatran accumulates; dialysis circuits are heparinized | Draw coagulation tests before the run or away from the circuit; prolonged dabigatran effect in renal failure |
| Liver disease | Reduced factor synthesis prolongs PT and aPTT; argatroban clearance falls | Lower argatroban starting dose and slower titration; a long aPTT can also come from DIC |
| Other: emicizumab, ECMO | Emicizumab shortens the aPTT to normal or below; ECMO patients often have inflammation and high factor VIII | Do not use the aPTT or one-stage factor VIII assays on emicizumab; anti-Xa preferred for heparin on ECMO |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Draw from a heparinized line | ↑ (False +) | Heparin from flushes or locks in the sample | Opposite-arm venipuncture, or a line without heparin and an adequate discard per policy |
| Underfilled citrate tube | ↑ (False +) | Too much citrate for the plasma volume | Fill to the line; tubes under 80% full are rejected, 80–90% may read slightly long |
| Hematocrit >55% | ↑ (False +) | Less plasma, so relatively excess citrate | Lab supplies a tube with adjusted citrate volume |
| Delayed processing on heparin | ↓ (False −) | Platelet factor 4 neutralizes heparin in the tube | Centrifuge within 1 hr |
| Clotted or hemolyzed sample | Unreliable | Factors consumed or activated; optical interference | Reject and redraw |
Medications
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| UFH, argatroban, bivalirudin, dabigatran | ↑ | Inhibit thrombin or factor Xa | Interpret against the dose and timing |
| Rivaroxaban, apixaban, edoxaban, LMWH | ↑ variable or none | Reagent-dependent sensitivity | Use a calibrated anti-Xa level |
| Emicizumab | ↓ (False −) | Factor VIII mimetic shortens intrinsic clotting tests | Do not use aPTT-based tests; chromogenic assays per hematology |
Physiologic / biologic
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Lupus anticoagulant | ↑ (no bleeding) | Antibodies interfere with the test phospholipid | Monitor heparin by anti-Xa; LA testing off anticoagulants and outside acute thrombosis |
| High factor VIII (inflammation, pregnancy) | ↓ | Speeds intrinsic clotting | Anti-Xa for heparin dosing |
| Factor XII deficiency | ↑ (no bleeding) | Contact factor needed only in the test tube | aPTT and ACT cannot monitor heparin; use anti-Xa |
Assay & device-specific
Reagents differ in how sensitive they are to heparin, lupus anticoagulant and factor deficiencies. Normal and heparin ranges shift with the reagent or the lot. Whole-blood point-of-care devices don't match the lab aPTT.
Common misinterpretations
- High aPTT with in-range anti-Xa: Suggests factor deficiency, lupus anticoagulant or another drug, not excess heparin. Titrate to the anti-Xa.
- "Lupus anticoagulant means bleeding risk": It's the opposite. It marks thrombotic risk.
- "Normal aPTT, so no hemophilia": Mild hemophilia A or B can still have a normal aPTT.
- "Normal aPTT, so no DOAC effect": Wrong for apixaban and rivaroxaban. It's also wrong for dabigatran with an insensitive reagent.
Physiology & Test Basics
What it measures
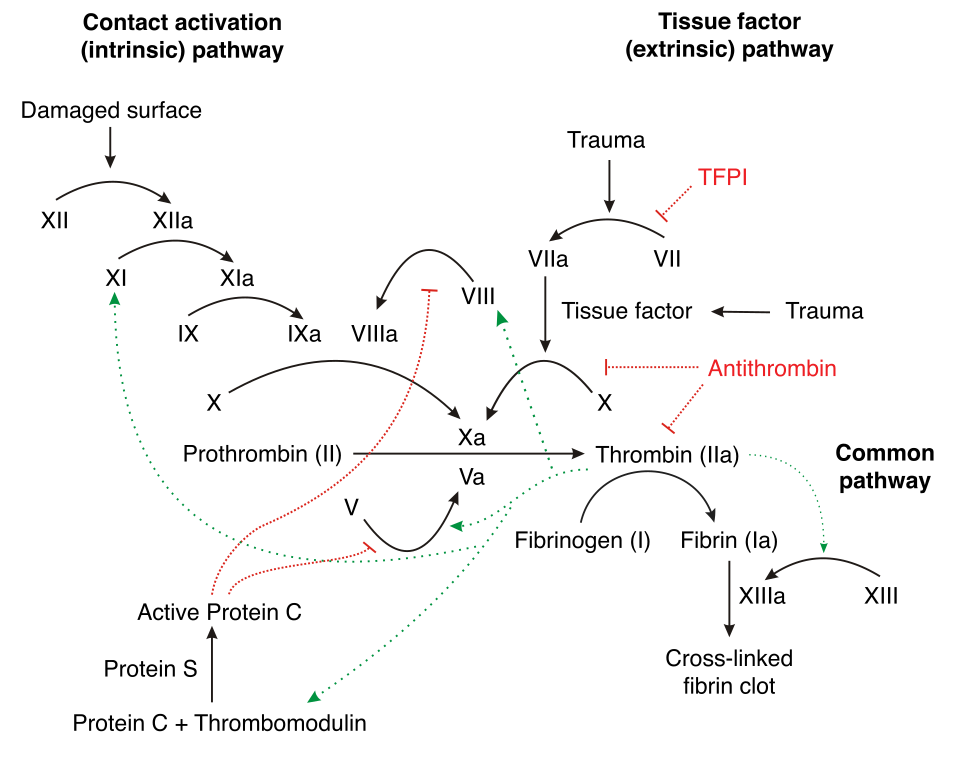
The activated partial thromboplastin time (aPTT) is the number of seconds citrated plasma takes to clot once a contact activator, phospholipid and calcium go in. It tests the intrinsic (contact) and common pathways: factors XII, XI, IX and VIII, then X, V, II (prothrombin) and fibrinogen. It doesn't test factor VII, which the PT covers, or factor XIII. It doesn't test platelets either.
Physiology & regulation
- Lab pathways vs the body: The intrinsic/extrinsic split describes the test tube. In the body, tissue factor starts clotting, and thrombin amplifies it through factors XI, IX and VIII.
- Contact factors: Low factor XII, prekallikrein or high-molecular-weight kininogen prolongs the aPTT. None of them is needed for hemostasis.
- Factors VIII and IX: These are the hemophilia factors. Both sit on the aPTT side, which is why hemophilia prolongs the aPTT and not the PT.
- Heparin: Heparin speeds up antithrombin. Antithrombin shuts down thrombin and factor Xa, and that lengthens the aPTT.
- Liver: The liver makes most clotting factors. When it fails, both the PT and the aPTT get longer.
How it is measured
- Specimen: light-blue top (3.2% sodium citrate), filled to the line (9 parts blood to 1 part citrate); platelet-poor plasma after centrifugation.
- Method: Automated clot detection, optical or mechanical, runs after a contact activator such as silica, kaolin or ellagic acid. It's a lab test. Whole-blood point-of-care devices exist, but they read differently.
- Timing: No fasting required. On heparin, centrifuge within 1 hour of collection, then test promptly.
Why it matters
The aPTT screens for hemophilia A and B. It monitors argatroban and, where anti-Xa isn't used, UFH. Alongside the PT, fibrinogen and platelets, it flags DIC and massive-transfusion coagulopathy. Misread it, and you get dangerous heparin changes or miss a bleeding disorder.
Clinical Pearls
References
- Gouin-Thibault, I., Frere, C., Castellucci, L. A., Connors, J. M., Cuker, A., Levy, J. H., Lecompte, T., Mullier, F., & UFH working group. (2026). How to monitor and manage unfractionated heparin in practice (Part 1)? Guidance from the SSC of the ISTH. Journal of Thrombosis and Haemostasis, 24(8), 3051–3062. https://doi.org/10.1016/j.jtha.2026.05.013
- Pfizer Laboratories. (2025). Heparin Sodium Injection, USP: Prescribing information (revised September 2025). DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=56dc3074-f1c5-45a3-b923-f1d14858e06d
- Novartis Pharmaceuticals Corporation. (2026). Argatroban Injection: Prescribing information (revised June 2026). U.S. Food and Drug Administration. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/020883s021lbl.pdf
- Tomaselli, G. F., Mahaffey, K. W., Cuker, A., et al. (2020). 2020 ACC expert consensus decision pathway on management of bleeding in patients on oral anticoagulants. Journal of the American College of Cardiology, 76(5), 594–622. https://doi.org/10.1016/j.jacc.2020.04.053
- Srivastava, A., Santagostino, E., Dougall, A., et al. (2020). WFH guidelines for the management of hemophilia, 3rd edition. Haemophilia, 26(Suppl 6), 1–158. https://doi.org/10.1111/hae.14046
- Genentech, Inc. (2025). Hemlibra (emicizumab-kxwh) injection: Prescribing information (revised July 2025). https://www.gene.com/download/pdf/hemlibra_prescribing.pdf
- ARUP Consult. (2026). Antiphospholipid syndrome (APS): Lupus anticoagulant testing (updated August 2026). ARUP Laboratories. https://arupconsult.com/node/1525
- Nielsen, S. T., Strandkjær, N., Juul Rasmussen, I., et al. (2022). Coagulation parameters in the newborn and infant: The Copenhagen Baby Heart and COMPARE studies. Clinical Chemistry and Laboratory Medicine, 60(2), 261–270. https://doi.org/10.1515/cclm-2021-0967
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.