

Bedside Snapshot
- Normal (Adult)
- Blood gas HCO₃⁻: 22–26 mEq/L (22–26 mmol/L)
Serum total CO₂: 22–29 mEq/L (22–29 mmol/L) - Critical Values
- <10 or >40 mEq/L (<10 or >40 mmol/L); typical, lab-specific
- High Suggests
- Vomiting or NG suction
- Diuretics, low K⁺
- Alkali load or mineralocorticoid excess
- Compensation for chronic CO₂ retention
- Low Suggests
- Lactic acidosis (shock, sepsis)
- DKA, including euglycemic
- Toxic alcohols, salicylate, kidney failure
- Diarrhea or large-volume saline (normal AG)
- Act Now If
- HCO₃⁻ <10 or >40 mEq/L, pH <7.20 or ≥7.55, or altered mental status: monitor, 12-lead ECG, blood gas, K⁺, glucose and anion gap; protect ventilation; notify receiving/medical control
- Watch Out For
- Intubating severe metabolic acidosis: apnea or a normal ventilator rate removes compensation and the pH can crash. Keep minute ventilation high.
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult: arterial HCO₃⁻ (blood gas) | 22–26 mEq/L | 22–26 mmol/L | Calculated by the analyzer from pH and PaCO₂ |
| Adult: serum total CO₂ (chemistry panel) | 22–29 mEq/L | 22–29 mmol/L | Measured; includes dissolved CO₂, so slightly above calculated HCO₃⁻ |
| Pregnancy | Mildly lower: typically about 18–21 mEq/L | About 18–21 mmol/L | Compensation for the lower PaCO₂ of pregnancy |
| Older adult (60 years and over) | 23–31 mEq/L in some labs | 23–31 mmol/L | Upper limit may run slightly higher (23–31 mEq/L in one laboratory's manual); use your lab's interval |
| Neonate (0–14 days) | 5–20 mEq/L (one pediatric lab) | 5–20 mmol/L | Wide, method-specific interval; use the pediatric laboratory's own range |
| Infant (15 days to 1 year) | 10–24 mEq/L | 10–24 mmol/L | Same laboratory and method |
| Child (1–4 years / 5–14 years) | 14–24 / 17–26 mEq/L | 14–24 / 17–26 mmol/L | Rises toward adult values through childhood |
| Adolescent (15–18 years) | Male 18–28, female 17–26 mEq/L | Same numbers in mmol/L | Adult interval applies from about 19 years |
Severity & critical values
| Level | Conventional | SI | What it means / typical findings |
|---|---|---|---|
| Low | 18–21 mEq/L | 18–21 mmol/L | Metabolic acidosis or compensation for chronic respiratory alkalosis; read with pH |
| Low, significant | 10–17 mEq/L | 10–17 mmol/L | Meets the DKA criterion (<18): mild DKA 15–18, moderate 10 to <15; CKD treatment threshold |
| Critical (low) | <10 mEq/L | <10 mmol/L | Severe acidosis (severe DKA band): Kussmaul breathing, shock, dysrhythmia |
| High | >26 (blood gas) or >29 (serum) to 40 mEq/L | Same in mmol/L | Metabolic alkalosis or compensation for chronic respiratory acidosis |
| Critical (high) | >40 mEq/L | >40 mmol/L | Severe alkalosis: low K⁺ and ionized Ca²⁺, dysrhythmia, hypoventilation |
Conversion: For bicarbonate, mEq/L and mmol/L are the same number. It is a monovalent ion, so the factor is 1.
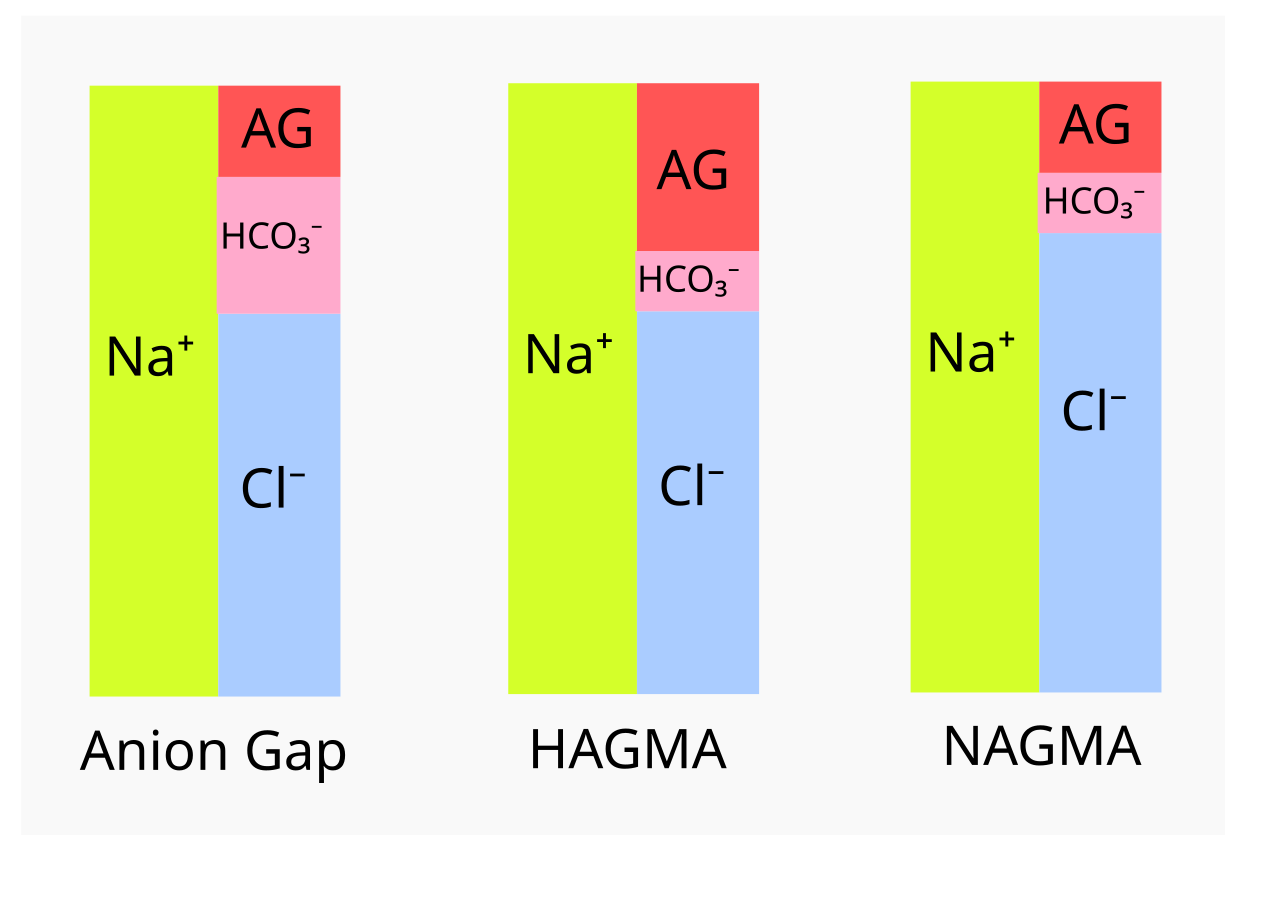
The normal gap depends on the analyzer. You will see it quoted near 12 mEq/L, but your lab's range beats a number you memorized.
Low albumin hides a real gap. For every 1 g/dL that albumin falls below 4 g/dL, add 2.5 mEq/L. Do that before you call the gap normal.
A measured PaCO₂ above the range means a respiratory acidosis has been added. Below the range, a respiratory alkalosis has been added.
Causes of Abnormal Results
Low (metabolic acidosis, HCO₃⁻ <22 mEq/L)
Is the pH low? Then this is a primary metabolic acidosis. Is the pH normal or high, with a low PaCO₂? Then it is compensation for chronic respiratory alkalosis. Sort it out, then calculate the albumin-corrected anion gap.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| High AG: lactic acidosis | Shock, sepsis, hypoxia, seizures, metformin with AKI, cyanide, CO | Poor perfusion, high lactate |
| High AG: ketoacidosis | DKA (including euglycemic on SGLT2 inhibitors), alcoholic, starvation | High ketones; glucose may be <200 mg/dL |
| High AG: toxic ingestion | Methanol, ethylene glycol, salicylate, propylene glycol, iron, isoniazid | Osmolal gap >10; salicylate: tinnitus, low PaCO₂ |
| High AG: kidney failure | AKI, advanced CKD | Rising creatinine |
| High AG: 5-oxoproline | Chronic acetaminophen use with malnutrition or sepsis | Normal lactate and ketones |
| Normal AG: GI loss | Diarrhea, ileostomy, enteric or pancreatic fistula | High Cl⁻; negative urine AG |
| Normal AG: kidney | Renal tubular acidosis, acetazolamide, ureteral diversion, hypoaldosteronism | Positive urine AG |
| Normal AG: chloride load | Large-volume 0.9% saline; DKA recovery | Cl⁻ rises as the AG closes |
| Compensation for chronic respiratory alkalosis | Pregnancy, high altitude, chronic hyperventilation (liver disease, CNS disease) | Low PaCO₂ with pH near normal; the low HCO₃⁻ is appropriate, not a second disorder |
High-AG mnemonic (GOLDMARK): Glycols (ethylene and propylene), Oxoproline, L-lactate, D-lactate, Methanol, Aspirin, Renal failure, Ketoacidosis. You will still hear MUDPILES. It is the older version.
High (metabolic alkalosis, HCO₃⁻ >26 mEq/L)
High pH with a metabolic cause is a primary metabolic alkalosis. Low or normal pH with a high PaCO₂ is compensation for chronic respiratory acidosis. The alkalosis persists only when something stops the kidney from dumping HCO₃⁻: volume, Cl⁻ or K⁺ depletion, low GFR or mineralocorticoid excess.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Chloride-responsive: gastric loss | Vomiting, NG suction, gastric outlet obstruction (pyloric stenosis in infants) | Low Cl⁻ and K⁺; urine Cl⁻ <20 mEq/L |
| Chloride-responsive: kidney loss | Loop or thiazide diuretics, laxatives, cystic fibrosis, contraction alkalosis from volume loss | Urine Cl⁻ high while the diuretic acts |
| Posthypercapnic | Chronically high PaCO₂ lowered too fast on a ventilator | Alkalemia once PaCO₂ is normal |
| Alkali load | Sodium bicarbonate, citrate (massive transfusion), calcium-alkali syndrome | High Ca²⁺ and AKI with antacids |
| Chloride-resistant | Primary aldosteronism, Cushing syndrome, renal artery stenosis, licorice | Hypertension, low K⁺; urine Cl⁻ >20 mEq/L |
| K⁺ or Mg²⁺ depletion | Hypokalemia, hypomagnesemia | Saline fails until replaced |
| Compensation | Chronic respiratory acidosis: COPD, obesity hypoventilation | High PaCO₂, pH low or normal |
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? The measured total CO₂ and the blood-gas HCO₃⁻ usually agree within a few mEq/L. When they don't, trust the measured value. Look for an underfilled tube or lipemia.
- How sick is the patient? Look at mental status, perfusion and breathing pattern. Kussmaul breathing is the body compensating. Then check K⁺, glucose and the ECG.
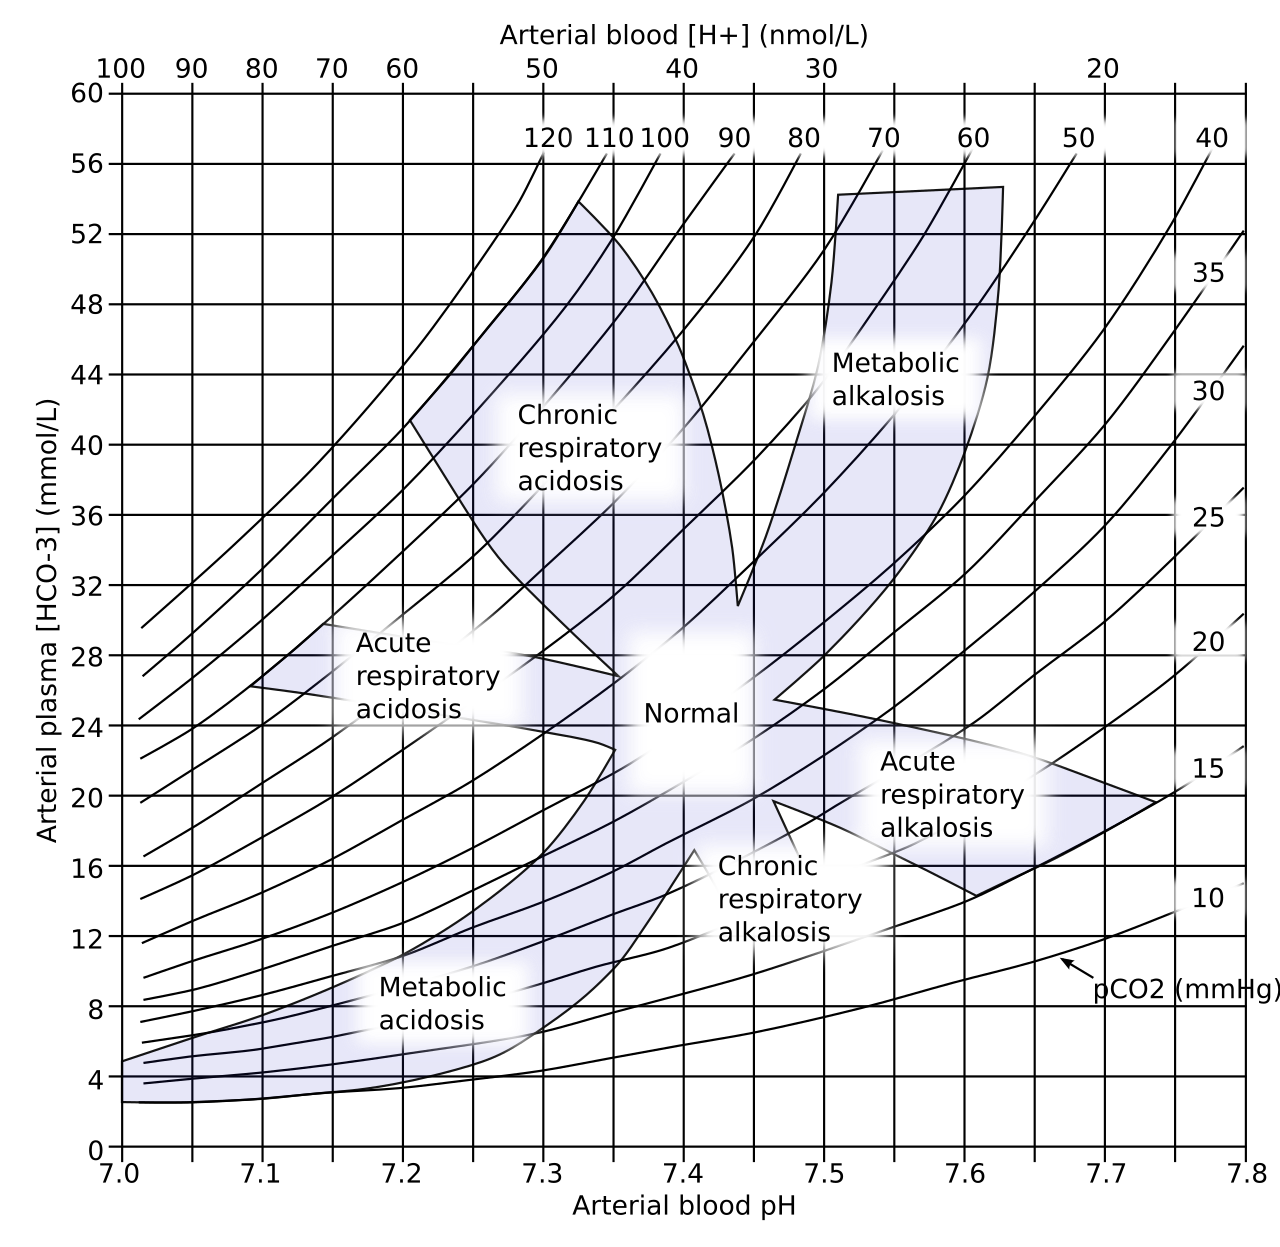
- Read it with pH and PaCO₂. When HCO₃⁻ moves the same way as the pH, the disorder is a primary metabolic one. When it moves the opposite way, the body is compensating for a respiratory disorder. Trends beat a single value.
- Check compensation and derived values. Use Winter's formula or the table below. Calculate the albumin-corrected anion gap and the delta gap. Order an osmolal gap if toxic alcohols are possible. In alkalosis, check urine Cl⁻.
- Classify with named criteria. DKA (2024 ADA/EASD/JBDS/AACE/DTS consensus): glucose ≥200 mg/dL or known diabetes, β-hydroxybutyrate ≥3.0 mmol/L or urine ketones ≥2+, and pH <7.3 and/or HCO₃⁻ <18 mEq/L; resolved at venous pH ≥7.3 or HCO₃⁻ ≥18 mEq/L with ketones <0.6 mmol/L.
- Escalate. Severe DKA (pH <7.0 or HCO₃⁻ <10 mEq/L), refractory acidemia, suspected toxic alcohol or salicylate, or HCO₃⁻ >40 mEq/L: ICU-level care, nephrology or toxicology.
Pattern recognition
| Pattern | Suggests | Next step |
|---|---|---|
| ↓ HCO₃⁻, ↑ AG | High-AG acidosis (GOLDMARK): ketoacidosis, lactate, toxic alcohols, salicylate, kidney failure | Glucose, β-hydroxybutyrate, lactate, creatinine, osmolal gap, salicylate level |
| ↓ HCO₃⁻, normal AG, ↑ Cl⁻ | Normal-AG acidosis: diarrhea, RTA, saline load, DKA recovery | Review fluids and stool output; K⁺; urine anion gap if unclear |
| ↓ HCO₃⁻, low PaCO₂, pH ≥7.40 | Compensation for respiratory alkalosis (pregnancy, altitude, hyperventilation) | Find the cause of hyperventilation: hypoxemia, sepsis, PE, pain, salicylate |
| ↑ HCO₃⁻, ↓ Cl⁻, ↓ K⁺ | Metabolic alkalosis from vomiting, NG suction or diuretics | Blood gas; spot urine Cl⁻; replace K⁺ |
| ↑ HCO₃⁻, high PaCO₂, pH ≤7.40 | Compensation for chronic respiratory acidosis | Compare with baseline; look for an acute rise in PaCO₂ |
Expected compensation
| Primary disorder | Primary change | Expected compensation |
|---|---|---|
| Metabolic acidosis | ↓ HCO₃⁻ | PaCO₂ = (1.5 × HCO₃⁻) + 8 ± 2 mmHg |
| Metabolic alkalosis | ↑ HCO₃⁻ | PaCO₂ rises 0.6–0.75 mmHg per 1 mEq/L rise; not above 55 mmHg from compensation alone |
| Respiratory acidosis, acute | ↑ PaCO₂ | HCO₃⁻ rises 1–2 mEq/L per 10 mmHg rise in PaCO₂ |
| Respiratory acidosis, chronic (3–5 days) | ↑ PaCO₂ | HCO₃⁻ rises 3–4 mEq/L per 10 mmHg rise in PaCO₂ |
| Respiratory alkalosis, acute | ↓ PaCO₂ | HCO₃⁻ falls 1–2 mEq/L per 10 mmHg fall in PaCO₂ |
| Respiratory alkalosis, chronic (2–3 days) | ↓ PaCO₂ | HCO₃⁻ falls 4–5 mEq/L per 10 mmHg fall in PaCO₂ |
A result inside the normal HCO₃⁻ range fits a pure high-gap acidosis. Above that range, a metabolic alkalosis has been added, as in DKA with vomiting. Below it, a normal-gap acidosis has been added.
Management Priorities
Emergency: Severe metabolic acidosis (HCO₃⁻ <10 mEq/L or pH <7.20)
- Protect the compensation: avoid oversedation. If intubation is unavoidable, minimize apnea and set a high minute ventilation at once, matched to the pre-intubation PaCO₂ or EtCO₂ (Paramedic/RN/CCT, per local protocol).
- Treat the cause: perfusion for lactic acidosis; fluids, insulin and K⁺ for DKA; poison center and dialysis planning for toxic alcohols or salicylate.
- Watch the K⁺: Insulin pushes K⁺ down. So does bicarbonate. Get an ECG, a K⁺ and a glucose now, then repeat all three often.
- Bicarbonate only for a specific reason (table): it is not a routine fix for lactic acidosis or cardiac arrest. The real indications, including hyperkalemic cardiac arrest, sodium-channel-blocker toxicity (wide QRS) and salicylate poisoning, are on the sodium bicarbonate page, with their doses.
- Kidney replacement therapy: refractory acidemia (AKI trials used pH ≤7.20 or HCO₃⁻ <12 mEq/L), toxic alcohols, salicylate.
Emergency: Severe metabolic alkalosis (HCO₃⁻ >40 mEq/L or pH ≥7.55)
- Monitor: ECG; K⁺, ionized Ca²⁺, Mg²⁺, phosphate; SpO₂ (compensatory hypoventilation).
- Stop the source: alkali (bicarbonate, citrate), diuretics where possible; replace gastric losses.
- Urine Cl⁻ <20 mEq/L: 0.9% sodium chloride plus KCl.
- Chloride-resistant or volume overloaded: replace K⁺; spironolactone or amiloride for mineralocorticoid excess; acetazolamide if kidney function allows.
- Refractory or pH >7.6: ICU: dilute hydrochloric acid via central line, or dialysis.
Medications
Doses vary by protocol; follow local protocols and medical direction.
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Sodium bicarbonate 4.2%: severe ICU acidemia | pH ≤7.20 with PaCO₂ ≤45 mmHg and AKI stage 2–3: IV infusion titrated to pH ≥7.30 in limited doses, reassessed after each dose (ICU, protocol-dependent; no unbounded infusion) | Neonates and infants: 4.2% preferred, infused slowly (label); otherwise Not routinely used (consult) | SSC 2021: weak suggestion in septic shock with pH ≤7.2 and AKI 2–3; suggested against use to improve hemodynamics in lactic acidemia. Watch Na⁺, ionized Ca²⁺, volume status and pH after each dose |
| Sodium bicarbonate 8.4%: DKA | pH <7.0 only, adults (2024 consensus): 100 mmol (100 mL of 8.4%) in 400 mL sterile water IV, every 2 hr, to pH >7.0. Replace K⁺ per protocol; check K⁺ before and during | Not routinely used (consult) | Fluids and insulin clear DKA acidosis. If K⁺ <3.5 mmol/L, replace first (2024 consensus: 10 mmol/h) and delay insulin until K⁺ >3.5. Bicarbonate adds hypokalemia risk. Linked to cerebral injury in children |
| Sodium bicarbonate: normal-AG acidosis | Bicarbonate loss: 2–5 mEq/kg IV over 4–8 hr, then reassess the blood gas (do not fully correct in 24 hr) | Older children: same. Under 2 yr: specialist order, slowly (max 8 mEq/kg/day) | Treat the cause. CKD: oral alkali (KDIGO 2024: consider when HCO₃⁻ <18 mEq/L) |
| 0.9% sodium chloride: chloride-responsive alkalosis | IV at 50–100 mL/hr above ongoing losses; titrate to volume status: no fixed max | Isotonic fluid per pediatric fluid protocol; titrate to effect | Restores volume and Cl⁻ so the kidney excretes HCO₃⁻. Avoid in volume overload |
| Potassium chloride | Replace to normal K⁺ per institutional protocol (titrate to K⁺: no fixed max) | Weight-based per institutional protocol | High-alert (concentrated IV). Alkalosis persists while K⁺ is low |
| Acetazolamide | Alkalosis with volume overload: 250–375 mg IV or PO once or twice daily (max twice daily); protocol- and ICU-dependent | Not routinely used (consult) | Contraindicated with sulfonamide hypersensitivity (cross-sensitivity possible), in cirrhosis (hepatic encephalopathy risk), in hyperchloremic acidosis, and with low Na⁺ or K⁺. Can cause metabolic acidosis: check HCO₃⁻ and K⁺. Weak with volume depletion; avoid in kidney failure |
Definitive care & disposition
- ICU: severe DKA (pH <7.0, HCO₃⁻ <10 mEq/L or stupor), refractory acidemia, HCO₃⁻ >40 mEq/L with dysrhythmia, or any bicarbonate or acid infusion. Refractory alkalosis: 0.1–0.2 N hydrochloric acid at 0.1–0.2 mmol/kg/hr via central line, or dialysis.
- Nephrology and toxicology: Dialysis decisions go through nephrology. Any unexplained high-gap or osmolal-gap acidosis gets a call to the poison center.
- Follow-up: Hypokalemic alkalosis with hypertension? That patient needs a renin and aldosterone work-up.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
Cartridge analyzers calculate HCO₃⁻ from the measured pH and PaCO₂. Some also measure total CO₂. Stay inside the cartridge's temperature and hematocrit limits, and trend on one device. Waveform EtCO₂ tracks ventilation, not bicarbonate. A rising EtCO₂ after you intubate an acidotic patient means compensation is slipping away.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Before departure | Timed pH, PaCO₂, HCO₃⁻, anion gap, K⁺, glucose, lactate or ketones; pre-intubation PaCO₂ or EtCO₂ and ventilator settings |
| Running infusions | Insulin, bicarbonate and KCl change HCO₃⁻ and K⁺ en route: confirm drug, concentration and rate |
| Ventilated acidotic patient | Match the sending minute ventilation; blood gas after the switch if available |
| Re-check cadence | DKA: electrolytes and venous pH every 2–4 hr until stable |
| Scope | EMS: recognize Kussmaul breathing and report EtCO₂ trends. ED/ICU and transport (Paramedic/RN/CCT): interpret the trend and escalate per local protocols and medical direction |
| Redirect | Toxic alcohol, salicylate or acidemia needing dialysis: go to a center that can start hemodialysis |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Lower and wider reference intervals (neonates 5–20 mEq/L, infants 10–24); pyloric stenosis causes hypochloremic, hypokalemic alkalosis | Use age-specific ranges; check Cl⁻ and K⁺ in the vomiting infant |
| Children & adolescents | DKA: venous pH <7.3 or HCO₃⁻ <18 mEq/L; severe at pH <7.1 or HCO₃⁻ <5 mEq/L per ISPAD 2022. CKD acidosis impairs growth | Bicarbonate avoided in pediatric DKA except exceptional cases. Bicarbonate is not routine in pediatric arrest; its specific indications are on the sodium bicarbonate page. See weight-based dosing |
| Pregnancy | Lower PaCO₂ (progesterone) with compensatory lower HCO₃⁻; DKA can occur with glucose <200 mg/dL | Mildly low HCO₃⁻ is not acidosis without a low pH; check ketones in unwell diabetic patients |
| Older adults | Upper limit runs slightly higher in some labs (23–31 mEq/L); diuretic use and chronic CO₂ retention are common | Diuretic alkalosis with low K⁺ is common; review medications |
| CKD / dialysis | Low HCO₃⁻ common as GFR falls | KDIGO 2024: consider treatment to prevent HCO₃⁻ <18 mEq/L; do not overshoot normal |
| Chronic CO₂ retention | Compensatory high HCO₃⁻ at baseline | Correct PaCO₂ slowly to avoid posthypercapnic alkalosis |
| Other: altitude, SGLT2 inhibitors | Altitude causes chronic hypocapnia with a compensatory fall in HCO₃⁻; SGLT2 inhibitors can cause ketoacidosis with near-normal glucose | Do not label altitude-related low HCO₃⁻ a primary acidosis; check ketones when HCO₃⁻ is low in a patient on an SGLT2 inhibitor |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Underfilled or uncapped tube | ↓ | CO₂ escapes to air | Fill fully, keep capped, process promptly |
| Draw near an IV infusion | ↓ or ↑ | Dilution, or bicarbonate contamination | Use the other arm |
| Excess liquid heparin or an underfilled syringe | Shifts pH and HCO₃⁻ | Heparin dilutes the sample | Use a dry or correctly filled heparin syringe |
| Air bubbles in the syringe | ↓ PaCO₂ and HCO₃⁻ | CO₂ equilibrates with air | Expel air; cap at once |
| Delayed processing | Variable; pH drifts | Cells keep metabolizing (CO₂, lactate) | Analyze promptly, per lab policy |
| Tourniquet or fist clenching | ↓ pH; ↑ lactate and K⁺ | Local acidosis and K⁺ release | Limit tourniquet time; no fist clenching |
| Venous instead of arterial sample | pH lower; PaCO₂ higher | Tissue CO₂ uptake | Use the sample type the protocol names |
Medications & supplements
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Salicylate, bromide | AG falsely low | Read as chloride by some electrodes | Salicylate level; re-measure Cl⁻ |
| Acetazolamide, topiramate | ↓ (true) | Carbonic anhydrase inhibition causes renal bicarbonate loss | Expected effect; check whether the drug explains a normal-gap acidosis |
| SGLT2 inhibitors, metformin | ↓ (true) | Euglycemic ketoacidosis; lactic acidosis in overdose or kidney failure | Check ketones, lactate and creatinine |
| Loop and thiazide diuretics, corticosteroids | ↑ (true) | Chloride and potassium loss; mineralocorticoid effect | Check K⁺ and Cl⁻; read with volume status |
| Sodium bicarbonate, citrate (massive transfusion), antacids | ↑ (true) | Alkali load | Review recent infusions and blood products |
Physiologic / biologic
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Severe lipemia (triglycerides >1,000 mg/dL) | False − | Turbidity in enzymatic assays | Compare with blood-gas HCO₃⁻ |
| Low albumin | AG falsely normal | Main unmeasured anion | Albumin-corrected AG |
| Lithium, paraproteinemia, hypercalcemia, hypermagnesemia | AG falsely low | Unmeasured cations lower the calculated gap | Albumin-corrected AG; check lithium level and protein studies |
Assay & device-specific
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Calculated vs measured | Values differ | Blood gas HCO₃⁻ is calculated; total CO₂ is measured | Trust measured if discordant; trend one method |
Common misinterpretations
- "CO₂ 18 means CO₂ retention": On a chemistry panel, CO₂ is bicarbonate. Low means metabolic acidosis, not hypoventilation.
- "Low HCO₃⁻ means DKA is not resolving": Once the AG closes, the low HCO₃⁻ that remains is usually hyperchloremic acidosis.
- "High HCO₃⁻ always needs treatment": In chronic CO₂ retention, that high HCO₃⁻ is protective compensation.
Physiology & Test Basics
What it measures
Bicarbonate (HCO₃⁻) is the metabolic half of acid–base balance. You meet it two ways: calculated HCO₃⁻ on a blood gas, and measured total CO₂ (TCO₂) on a chemistry panel. Total CO₂ is about 95% bicarbonate plus a little dissolved CO₂. So the "CO₂" on a chemistry panel reads as serum bicarbonate. PaCO₂ is the respiratory half. Base excess is another metabolic index.
Physiology & regulation
- Buffer: CO₂ + H₂O ⇌ H₂CO₃ ⇌ H⁺ + HCO₃⁻. The lungs set PaCO₂ and the kidneys set HCO₃⁻. Their ratio sets the pH.
- Kidney: It takes back the HCO₃⁻ it filtered. It makes new HCO₃⁻ as it excretes acid. Normally, it dumps any excess quickly.
- Chloride and potassium: Low Cl⁻ or low K⁺ makes the kidney hang on to bicarbonate. That keeps an alkalosis going.
- Electroneutrality: Charges have to balance. When HCO₃⁻ falls, either Cl⁻ rises (normal gap) or an unmeasured anion shows up (high gap).
- Timing: Breathing starts to compensate within minutes. The kidneys take days.
How it is measured
- Chemistry panel: serum (gold top, gel) or lithium-heparin plasma (green top); measured total CO₂. Fill the tube and keep it capped.
- Blood gas: heparinized syringe, air expelled, analyzed promptly; HCO₃⁻ is calculated from pH and PaCO₂ (Henderson–Hasselbalch).
- Fasting: not required.
Why it matters
DKA, shock, toxic ingestions and severe vomiting show up here first. Add Na⁺ and Cl⁻ and you get the anion gap. Add pH and PaCO₂ and you see whether breathing is compensating. That matters most when you take over a patient's ventilation.
Clinical Pearls
References
- Lewis, J. L., III. (2025). Metabolic alkalosis. In Merck Manual Professional Version. Merck & Co., Inc. https://www.merckmanuals.com/professional/endocrine-and-metabolic-disorders/acid-base-regulation-and-disorders/metabolic-alkalosis
- Do, C., Vasquez, P. C., & Soleimani, M. (2022). Metabolic alkalosis pathogenesis, diagnosis, and treatment: Core Curriculum 2022. American Journal of Kidney Diseases, 80(4), 536–551. https://doi.org/10.1053/j.ajkd.2021.12.016
- Umpierrez, G. E., Davis, G. M., ElSayed, N. A., Fadini, G. P., Galindo, R. J., Hirsch, I. B., et al. (2024). Hyperglycemic crises in adults with diabetes: a consensus report. Diabetes Care, 47(8), 1257–1275. https://doi.org/10.2337/dci24-0032
- Glaser, N., Fritsch, M., Priyambada, L., Rewers, A., Cherubini, V., Estrada, S., Wolfsdorf, J. I., & Codner, E. (2022). ISPAD Clinical Practice Consensus Guidelines 2022: Diabetic ketoacidosis and hyperglycemic hyperosmolar state. Pediatric Diabetes, 23(7), 835–856. https://doi.org/10.1111/pedi.13406
- Evans, L., Rhodes, A., Alhazzani, W., Antonelli, M., Coopersmith, C. M., French, C., et al. (2021). Surviving Sepsis Campaign: international guidelines for management of sepsis and septic shock 2021. Intensive Care Medicine, 47(11), 1181–1247. https://doi.org/10.1007/s00134-021-06506-y
- Kidney Disease: Improving Global Outcomes (KDIGO) CKD Work Group. (2024). KDIGO 2024 clinical practice guideline for the evaluation and management of chronic kidney disease. Kidney International, 105(4S), S117–S314. https://doi.org/10.1016/j.kint.2023.10.018
- Jaber, S., et al. (2018). Sodium bicarbonate therapy for patients with severe metabolic acidaemia in the intensive care unit (BICAR-ICU). The Lancet, 392, 31–40 (landmark trial). https://doi.org/10.1016/S0140-6736(18)31080-8
- Long Grove Pharmaceuticals. (2024). Sodium bicarbonate injection, solution (8.4%) [Prescribing information, revised 07/2024]. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=a26d709b-b294-4b02-9a88-7e840f099a33
- Children's Minnesota Laboratory. (2021). CO2 total: laboratory test manual (reference ranges, critical values and limitations; updated April 7, 2021). https://www.childrensmn.org/Manuals/Lab/chemistry/co2-total.pdf
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.