

Bedside Snapshot
- Normal / Therapeutic
- Not detected without digoxin. Heart failure: 0.5–0.9 ng/mL (0.6–1.2 nmol/L). AF rate control: <1.2 ng/mL (1.5 nmol/L). Draw 6 h or more after the last dose
- Toxic Thresholds
- >2.0 ng/mL (2.6 nmol/L): toxic range; toxicity also occurs lower
- Chronic level >6 ng/mL (>4 child): antidote
- Ingested ≥10 mg adult, ≥4 mg or >0.1 mg/kg child
- K⁺ >5.5 mEq/L (>6 child) with progressing toxicity
- Toxicity Looks Like
- Nausea, vomiting, anorexia, confusion, yellow-green vision. PVCs, bradycardia, AV block, atrial tachycardia with block, accelerated junctional rhythm, bidirectional VT, VF
- Antidote / Definitive Care
- Digoxin immune Fab (DigiFab) IV; Digibind is discontinued. Atropine, pacing and lidocaine only bridge. Dialysis does not remove digoxin. Poison center 1-800-222-1222
- Act Now If
- VT/VF, high-grade AV block or bradycardia with poor perfusion, K⁺ >5.5 mEq/L, or a potentially fatal ingestion: monitor, pads on, draw level and K⁺, give Fab without waiting for results
- Watch Out For
- A level in the target range does not exclude toxicity: low K⁺ or Mg²⁺, high Ca²⁺ or falling renal function make normal levels toxic
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Not taking digoxin | Not detected | Not detected | Some immunoassays read low levels (usually 0.2–0.4 ng/mL) from digoxin-like substances; see Interfering Factors |
| Adult, heart failure | 0.5–0.9 ng/mL | 0.6–1.2 nmol/L | Usual laboratory reference interval and the target used in current heart failure trials. Below 0.5 ng/mL: less effect |
| Adult, AF rate control | <1.2 ng/mL | <1.5 nmol/L | 2023 ACC/AHA/ACCP/HRS AF guideline: a reasonable target when a level is indicated |
| Traditional range (legacy) | 0.8–2.0 ng/mL | 1.0–2.6 nmol/L | Older teaching. Adverse effects and mortality rise above 1.2 ng/mL, so most patients are now kept lower |
| Pregnancy | Same targets | Same targets | Dose needs may rise in pregnancy and fall postpartum; monitor levels in both periods |
| Older adults | Same targets | Same targets | Lower renal clearance and lean mass: toxicity at doses that are safe in younger adults |
| Children | Same as adult | Same as adult | No separate pediatric range is defined. Neonates often carry digoxin-like substances that raise immunoassay results |
Severity & critical values
| Level | Concentration | When to draw | Meaning |
|---|---|---|---|
| Subtherapeutic | <0.5 ng/mL (<0.6 nmol/L) | Just before the next dose, or 6 h or more after the last | Less effect. Check adherence, absorption and interacting drugs before raising the dose |
| Target | HF 0.5–0.9 ng/mL; AF <1.2 ng/mL | Same | Toxicity is still possible with low K⁺ or Mg²⁺, high Ca²⁺, hypothyroidism or renal failure |
| Above target | 1.2–2.0 ng/mL (1.5–2.6 nmol/L) | Same | Adverse effects become more likely above 1.2. Review dose, creatinine, electrolytes and interactions |
| Toxic range | >2.0 ng/mL (>2.6 nmol/L) | Any time toxicity is suspected; repeat 6 h or more after the last dose | Toxicity usually present; >3.0 ng/mL in an adult strongly suggests overdose |
| Critical | Chronic: >6 ng/mL (>7.7 nmol/L) adult, >4 ng/mL (>5.1 nmol/L) child | Steady state, 6 h or more after the last dose | DigiFab label criterion for antidote treatment |
| Potentially fatal ingestion | ≥10 mg adult; ≥4 mg or >0.1 mg/kg child; or an amount expected to give ≥10 ng/mL (12.8 nmol/L) at steady state | On arrival, then again 6 h or more after ingestion | Treat on history and clinical findings. Early levels overstate tissue load but a high one is still dangerous |
Conversion: ng/mL × 1.28 = nmol/L (1 ng/mL = 1 mcg/L)
Causes of Abnormal Results
Any measurable digoxin means exposure. The real question is whether the level, the electrolytes, the kidneys and the rhythm add up to toxicity. Most toxicity is chronic: older patients on long-term therapy whose renal function has fallen.
Sources & routes of exposure
| Source | Examples | Bedside clue |
|---|---|---|
| Prescribed digoxin (chronic) | Heart failure and AF rate control: 62.5, 125 and 250 mcg tablets, oral solution, IV injection | Older adult with dehydration, AKI or a new interacting drug; insidious fatigue, anorexia, confusion |
| Intentional overdose | Own or a family member's tablets | Early vomiting, then bradycardia and AV block. Ask about co-ingestants |
| Pediatric exploratory ingestion | Grandparent's or parent's tablets, liquid formulation | Unwitnessed; time and amount uncertain. AV block or sinus bradycardia rather than vomiting in infants |
| Plant and animal cardiac glycosides | Foxglove, oleander, yellow oleander; Bufo toad venom and remedies containing it (Chan Su) | Same toxidrome. The digoxin assay cross-reacts only partly, so the level confirms exposure but not severity |
Risk factors for toxicity
| Factor | Why it matters | Practical point |
|---|---|---|
| Renal impairment (AKI, CKD, dehydration) | 50–70% of a dose leaves unchanged in urine; half-life rises from 1.5–2 days to 3.5–5 days in anuria | Send creatinine with every level. Toxicity lasts longer in renal failure |
| Hypokalemia | K⁺ and digoxin compete for the Na⁺/K⁺-ATPase; low K⁺ increases digoxin binding and arrhythmia risk | Diuretics, vomiting and diarrhea are common triggers |
| Hypomagnesemia, hypercalcemia | Both increase myocardial sensitivity to digoxin | Check Mg²⁺ and Ca²⁺ with every suspected case |
| Older age, low body weight | Less lean mass and lower clearance | Most toxicity cases are older adults |
| Hypothyroidism, hypoxemia, ischemia, amyloid heart disease | Lower dose needs or higher sensitivity; amyloid binds digoxin and causes toxicity at usual levels | A level in range does not clear these patients |
Drug interactions that raise the level
| Drug | Typical rise | Action |
|---|---|---|
| Amiodarone | About 70% | Label: reduce digoxin 30–50% and recheck the level |
| Quinidine; erythromycin; tetracycline | About 100% | Antibiotics also kill gut bacteria that inactivate digoxin in some patients |
| Verapamil | 50–75% | Additive AV block; diltiazem raises the level about 20% |
| Dronedarone, propafenone, clarithromycin, itraconazole, ritonavir | About 60–270% (level or AUC) | Check a level before and after starting; reduce the dose |
| NSAIDs, ACE inhibitors, ARBs, diuretics | Variable | Lower GFR (and K⁺ or Mg²⁺ with diuretics): toxicity without a dose change |
Acute vs acute-on-chronic vs chronic
| Feature | Acute | Acute-on-chronic | Chronic |
|---|---|---|---|
| Typical patient | Intentional overdose or child exploratory ingestion | Patient on digoxin who takes extra tablets | Older adult on therapy with falling renal function or a new interacting drug |
| Digoxin level | Often very high; early levels (under 6 h) overstate tissue load | High | Often only mildly raised, or within the target range |
| Potassium | Hyperkalemia common; a marker of severity | Variable | Often low or normal (diuretics); high with renal failure |
| Symptoms | Early nausea and vomiting | Features of both | Insidious: malaise, weakness, anorexia, confusion, visual change |
| Rhythm | Bradycardia and AV block; peak 3–6 h after ingestion, can last 24 h or more | Features of both | Any arrhythmia: PVCs, atrial tachycardia with block, junctional rhythms, VT |
Low (subtherapeutic, <0.5 ng/mL)
Low levels have their own causes: missed doses, malabsorption (short bowel, chronic diarrhea), drugs that lower absorption or speed clearance (cholestyramine, antacids, kaolin-pectin, sulfasalazine, rifampin, St John's wort), high-bran meals, and hyperthyroidism and other hypermetabolic states, which also make AF resistant to digoxin. Here's the catch: a level drawn just before a once-daily dose runs 10–25% lower than one drawn at 8 h.
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Check the draw time against the last dose. A draw under 6 h reads falsely high. Ask about Fab, spironolactone, herbal remedies and biotin. Then check for states that carry digoxin-like substances: newborn, pregnancy, renal or liver failure.
- How sick is the patient? Look first at the rhythm, the perfusion and the mental status. Get a 12-lead, K⁺, Mg²⁺, Ca²⁺, creatinine and glucose. A life-threatening arrhythmia, or hypotension with end-organ dysfunction, needs the antidote now. The level does not change that.
- Acute, acute-on-chronic or chronic? Pin down the time and amount of any ingestion, and the usual dose. In acute poisoning, K⁺ tells you more about severity than an early level does.
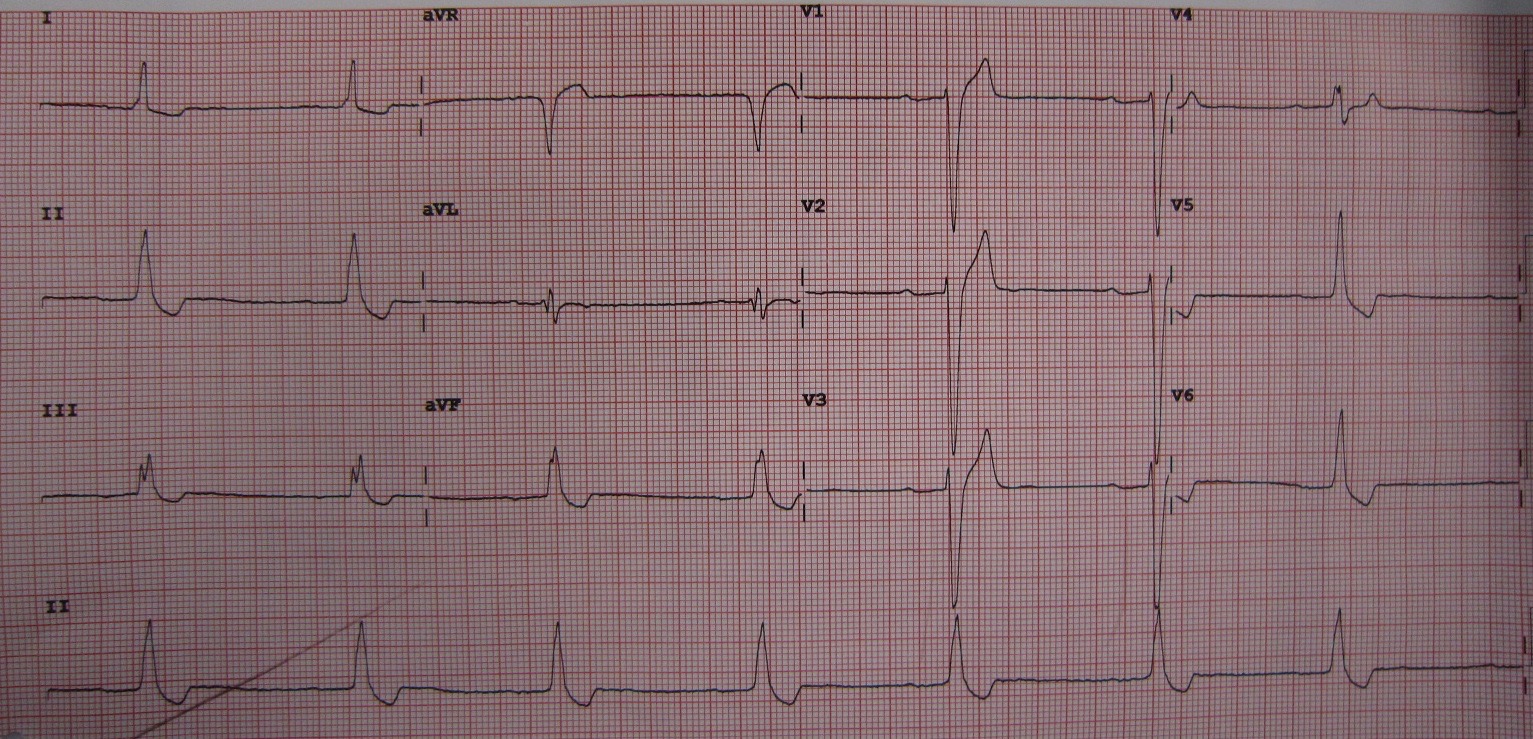
- Read the ECG for effect vs toxicity: Use the pattern table below. Scooped ST segments alone mean the drug is present. They do not mean toxicity.
- Apply the antidote criteria: DigiFab label triggers (life-threatening arrhythmia, progressive bradycardia or second- or third-degree AV block not responsive to atropine, K⁺ >5.5 mEq/L with progressing toxicity, potentially fatal ingestion, chronic level >6 ng/mL).
- Escalate or dispose: Call the poison center at 1-800-222-1222 and the cardiology team. Monitor continuously. Mild chronic toxicity without ECG changes: hold or reduce digoxin, correct electrolytes and recheck.
ECG patterns
| Pattern | Suggests |
|---|---|
| Scooped (sagging) ST depression, flattened or inverted T waves, larger U waves, shortened QT interval, mild PR prolongation | Digoxin effect at therapeutic levels. Not toxicity on its own |
| Frequent PVCs, bigeminy or trigeminy | Common in toxicity |
| Atrial tachycardia with AV block | Characteristic of toxicity (increased automaticity plus slowed conduction) |
| New Mobitz I, accelerated junctional rhythm, AV dissociation | Characteristic of toxicity; in AF, a ventricular rate that becomes slow and regular suggests AV dissociation with a junctional rhythm |
| Bidirectional VT (beat-to-beat QRS axis alternation) | Digoxin toxicity is the most common identified cause; also CPVT, Andersen-Tawil syndrome, myocarditis and aconite poisoning |
| Sinus bradycardia, high-grade AV block, asystole, VT/VF | Life-threatening toxicity: antidote now |
Management Priorities
Emergency: Life-threatening digoxin toxicity
- Monitor and draw labs: Hook up continuous ECG, defibrillator pads and IV access. Draw a digoxin level, K⁺, Mg²⁺, Ca²⁺ and creatinine before the antidote if you can. Stop digoxin and the interacting drugs.
- Give the antidote: Digoxin immune Fab for VT/VF, progressive bradycardia or second- or third-degree AV block not responsive to atropine, K⁺ >5.5 mEq/L (>6 in children) with progressing toxicity, hypotension with end-organ dysfunction, or a potentially fatal ingestion. Never wait for the level in an unstable patient. For life-threatening toxicity without arrest, start with 1–2 vials IV. Then reassess heart rate, rhythm and K⁺ at the bedside. Repeat until toxicity resolves. This differs from the FDA label, which calculates the full neutralizing dose from the amount ingested or the serum level. AHA 2025 Part 10: digoxin-Fab is COR 1, LOE B-NR for life-threatening digoxin or digitoxin poisoning.
- Bridge the rhythm until Fab works: For bradycardia, atropine and transcutaneous pacing both give variable results. Neither may delay Fab. For ventricular arrhythmias: lidocaine, or phenytoin with toxicologist dosing (AHA 2025 Part 10: may be reasonable, COR 2b, LOE C-EO, until Fab can be given). The European consensus also lists magnesium sulfate. Where possible, it advises avoiding epinephrine or isoproterenol infusions for bradycardia.
- Manage potassium: Fab is what treats digoxin hyperkalemia. When K⁺ is life-threatening and Fab is delayed, insulin with dextrose can bridge. AHA 2025 Part 10 makes no recommendation on calcium for digoxin. Calcium must not delay Fab. Low K⁺: replace cautiously toward 4.0–5.5 mEq/L. Avoid potassium with bradycardia or AV block unless directed. Correct low Mg²⁺.
- Electricity: Defibrillate VF or pulseless VT as usual. Suspected toxicity? Elective cardioversion waits. If it can't wait, go with the lowest effective energy.
Emergency: Cardiac arrest or acute massive ingestion
- Resuscitate: Run standard ACLS/PALS, defibrillation included. Give Fab 10 vials IV push once arrest is imminent or present, and repeat once (10 vials) if there is no response. AHA 2025 Part 10 says the ideal empiric arrest dose is unknown and there are no RCTs. Observational survival with Fab in arrest was 54% (30 of 56).
- Dose for the worst case: For arrest, or arrest that is imminent, push 10 vials IV now. Repeat 10 if there is no response, for a total of 10–20. The label's 20 vials can be split as 10 then 10. The 2023 European consensus uses 5 vials, repeated once after 30 min.
- Decontaminate: Activated charcoal is worth considering, with a protected airway. The European consensus puts the window at 2 h after ingestion. The Lanoxin label allows it after a massive ingestion at any time, because digoxin recirculates through the gut.
- Call: Call the poison center at 1-800-222-1222. Ask how many Fab vials the hospital has on hand.
Medications
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Digoxin immune Fab (DigiFab): cardiac arrest or arrest imminent | 10 vials IV push now; repeat 10 vials if no response (total 10–20) | Same as adult (Table 4). No fixed max; watch for volume overload under 20 kg | Give as a bolus. Table 4: acute overdose, critically ill, ingested dose unknown, 10–20 vials; the ideal empiric arrest dose is unknown. 2023 European consensus: 5 vials, repeat 5 after 30 min |
| Digoxin immune Fab (DigiFab): life-threatening toxicity, not in arrest | 1–2 vials IV, titrated to rhythm, heart rate and K⁺; repeat until toxicity resolves | Same vial range; no separate pediatric titration source. Watch for volume overload under 20 kg | Reassess at the bedside after each dose. Arrhythmia usually resolves in 30–45 min. Differs from FDA label: the label calculates the full neutralizing dose from the amount ingested or the serum level. Full-neutralization formulas are below |
| Digoxin immune Fab (DigiFab): acute ingestion, amount unknown (label full dose) | 20 vials IV (label full-neutralization option). Alternative: 10 vials, then 10 more if needed, to limit febrile reaction or volume overload; no fixed max | Same: 20 vials IV, or 10 then 10 if needed; no fixed max. Watch for volume overload under 20 kg | Infuse over at least 30 min; bolus if arrest is imminent (see arrest row). First response usually within 1 hr |
| Fab: chronic toxicity, level unknown (label full dose) | 6 vials IV (label full-neutralization option); redose by response, no fixed max | Under 20 kg: 1 vial IV; 20 kg or more: 6 vials IV; redose by response | For life-threatening toxicity without arrest, the titrated 1–2 vial approach above is the lead dose |
| Fab: level known (steady state) | Vials = level (ng/mL) × kg ÷ 100, rounded up; redose by response | 20 kg or more: same. Under 20 kg: mg = (level × kg ÷ 100) × 40 mg; redose by response | Use a level drawn 6 h or more after the last dose. Convert nmol/L to ng/mL first (÷ 1.28) |
| Fab: acute ingestion, amount known | Vials = mg ingested × 0.8 ÷ 0.5 (tablets), rounded up; redose by response | Same formula; redose by response | 1 vial (40 mg) binds about 0.5 mg digoxin. Example: 25 × 0.25 mg tablets = 10 vials |
| Atropine | 1 mg IV every 3–5 min (max 3 mg) | 0.02 mg/kg IV/IO (min 0.1 mg, max 0.5 mg/dose); may repeat once | Bradycardia or AV block while Fab is prepared. Response is variable. AHA 2025 Part 8 (general pediatric bradycardia, not digoxin-specific): atropine is recommended for bradycardia with cardiopulmonary compromise from increased vagal tone or AV block not due to factors such as hypoxia (COR 1, LOE C-LD) |
| Lidocaine | 1–1.5 mg/kg IV at 25–50 mg/min; repeat once after 5 min (max 200–300 mg in 1 hr) | 1 mg/kg IV/IO (never above the adult dose) | Ventricular arrhythmias until Fab is given; AHA 2025 Part 10: may be reasonable (COR 2b, LOE C-EO). High-alert |
| Regular insulin with dextrose | 5–10 units IV with dextrose 25 g IV | 0.1 units/kg IV with dextrose 0.5 g/kg (max 10 units) | Only to bridge life-threatening hyperkalemia until Fab acts. Check glucose before the dose and often for at least 6 hr. High-alert |
Definitive care & disposition
- Antidote: Digoxin immune Fab (DigiFab). Digibind is no longer available. AHA 2025 Part 10: digoxin-Fab is reasonable for life-threatening Bufo toad and yellow oleander poisoning (COR 2a, LOE C-LD). The dose is 1,200 mg, or 30 vials (Part 10 Table 4).
- No extracorporeal removal: Dialysis, hemoperfusion and plasmapheresis do not remove digoxin effectively. AHA 2025 Part 10 does not recommend them for life-threatening digoxin poisoning (COR 3: No Benefit, LOE B-NR).
- Non-life-threatening toxicity: Hold or reduce digoxin, correct K⁺ and Mg²⁺, and monitor. The European consensus also gives Fab, at half the neutralizing dose, for a level >12 ng/mL or troublesome symptoms.
- After Fab: Move to ICU or telemetry. Check K⁺ often in the first 6 h. As the drug effect is lost, watch for heart failure or fast AF. Monitor longer with renal failure, because toxicity can rebound. Restart digoxin only after Fab has cleared, at a reassessed dose.
- Consults: Call the poison center or a toxicologist for every Fab decision. Call cardiology for the underlying AF or heart failure.
Fab doses follow AHA 2025 Part 10 (Table 4) and the DigiFab label. Confirm Fab dosing with the poison center (1-800-222-1222).
Field & Transport Considerations
Point-of-care testing
There is no field digoxin test. Your monitor and 12-lead are the field tools. On critical-care transport, a cartridge blood-gas or chemistry analyzer can track K⁺ over time. That matters most before and after Fab.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| EMS scene | Bring every pill bottle and the medication list. Record the usual dose, last dose time and any ingestion time and amount. Pads on for bradycardia or AV block |
| Sending facility | Send the pre-Fab level with draw time and last-dose time, K⁺, Mg²⁺, creatinine, ECGs, and Fab vials given with times |
| En route | Continuous ECG; atropine and pacing ready. Run Fab on a pump on its own line. Recheck K⁺ during long transports after Fab |
| Destination | A hospital with Fab on hand; European consensus: an ED should be able to get at least 5 vials within 1 hour. Confirm stock before diverting an unstable patient |
Timing & Kinetics
| Parameter | Value | Clinical implication |
|---|---|---|
| Onset of effect | Oral 0.5–2 h; IV 5–30 min | Peak effect oral 2–6 h; IV 1–4 h |
| Peak serum level (oral) | 1–3 h | A level at this time is falsely high |
| Distribution phase | 6–8 h | Draw 6 h or more after the last dose; after an acute ingestion, ideally 8–12 h, but send a level on arrival |
| Trough vs 8 h level | Trough 10–25% lower (once-daily dosing) | Pick one timing and keep it for trends |
| Half-life | 1.5–2 days (36–48 h); 3.5–5 days in anuria | Toxicity resolves slowly without Fab, especially in renal failure |
| Time to steady state | About 7 days (normal renal function) to 19 days (CrCl 10 mL/min) without a loading dose | Recheck the level after any dose change or new interacting drug |
| Acute overdose | Cardiac effects peak 3–6 h, may last 24 h or more | Observe with continuous ECG even if the first ECG is normal |
| After Fab | Total level rises and misleads for days; Fab can persist up to 3 weeks | Use the pre-Fab level; free digoxin and the clinical picture afterward |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Premature and young infants are especially sensitive; digoxin-like substances in up to half of neonates; vomiting is uncommon | Sinus bradycardia can be the first sign. Interpret low readings cautiously |
| Children & adolescents | AV conduction problems and sinus bradycardia predominate. Potentially fatal: ≥4 mg or >0.1 mg/kg | Any new arrhythmia in a child on digoxin is toxicity until proven otherwise. Fab K⁺ trigger >6 mEq/L |
| Pregnancy | Crosses the placenta (newborn level about equal to the mother's); needs may rise, then fall postpartum; digoxin-like substances in some pregnancies | Monitor levels through pregnancy and postpartum; monitor the newborn. Breast milk exposure is small |
| Older adults | Lower GFR and lean mass; most toxicity cases | Dose by renal function; check creatinine with every level |
| CKD / dialysis | Half-life 3.5–5 days in anuria; not removed by dialysis; digoxin-like substances raise results | Smaller doses; after Fab, slow clearance of Fab-digoxin can let toxicity recur |
| Liver disease | Little effect on kinetics (about 13% metabolized) | Digoxin-like substances in liver failure can raise immunoassay results |
| Thyroid disease, amyloid | Hypothyroidism lowers dose needs; hyperthyroidism causes resistance; amyloid causes toxicity at usual levels | Check thyroid function in unexpected toxicity or poor response |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Drawn under 6 h after a dose | ↑ | Distribution phase | Record dose time; redraw 6 h or more after the dose |
| Drawn after Fab | ↑ (total level) | Assay counts Fab-bound digoxin | Use the pre-Fab sample; free digoxin where available |
| Citrate plasma | Rejected | Wrong specimen type | Serum in a gel-barrier or red-top tube |
Medications & supplements
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Spironolactone, canrenone, potassium canrenoate | False + (up to 0.5 ng/mL) | Cross-reactivity in some immunoassays | Ask the lab; free (ultrafiltrate) or LC-MS/MS methods are less affected |
| Chan Su, Siberian or Asian ginseng, ashwagandha, danshen | False + or − | Cross-reacting compounds | Ask about herbal remedies; an LC-MS/MS method may help |
| High-dose biotin | Unreliable | Interference in some immunoassays | Ask about biotin; Labcorp advises stopping 72 h before an elective draw |
Physiologic / biologic
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Digoxin-like immunoreactive substances | False + (usually 0.2–0.4 ng/mL; sometimes higher), occasionally ↓ | Endogenous compounds in neonates, pregnancy, renal or liver failure, hypertrophic cardiomyopathy, volume expansion | Baseline level before starting digoxin; subtract it, or use free or LC-MS/MS testing |
Assay & device-specific
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Digitoxin or plant/toad glycosides | Variable | Partial cross-reactivity | A positive level confirms exposure but not dose; treat clinically |
| Units | 1.28-fold error | nmol/L reported where ng/mL is expected | Confirm units before using the Fab formula |
Common misinterpretations
- “Therapeutic level, so not toxic”: Hypokalemia, hypomagnesemia, hypercalcemia and renal failure all cause toxicity at target levels. A number in range does not clear the patient.
- “Scooped ST means toxicity”: It is drug effect. Toxicity shows up as arrhythmias, AV block and symptoms.
- “The level went up after Fab”: That is expected. Fab binds the drug, and bound digoxin is inactive.
- “Fab will bring K⁺ down, so replace now”: Recheck first. After Fab, K⁺ can fall quickly.
Physiology & Test Basics
What it measures
The test measures total digoxin in serum, both protein-bound and free. About 25% of plasma digoxin is protein-bound. The test does not measure tissue digoxin, and tissue digoxin is what causes the effect. So the level only means something once distribution is complete.
Physiology & regulation
- Mechanism: Digoxin inhibits Na⁺/K⁺-ATPase. Intracellular Ca²⁺ rises as a result. That raises contractility and automaticity, and it slows conduction.
- Vagal effect: It slows the sinus node and the AV node. That is the basis for AF rate control and for toxic bradycardia.
- Potassium: At high concentrations, blocked pumps let K⁺ leak out of cells. That is why acute poisoning causes hyperkalemia.
- Distribution: The volume of distribution is large, about 475–500 L in adults. Digoxin concentrates in muscle and heart. It tracks lean body weight, not total body weight.
- Elimination: Mostly renal. Digoxin leaves unchanged, by filtration and P-glycoprotein secretion. About 13% is metabolized.
How it is measured
- Specimen: Serum, in a gel-barrier tube (preferred by Labcorp) or a red-top tube. Citrate plasma is rejected.
- Timing: Draw just before the next dose, or 6 h or more after the last. Record both times.
- Method: The usual method is immunoassay on hospital chemistry analyzers. LC-MS/MS and free (ultrafiltrate) digoxin testing are less affected by interference, but they are less widely available.
- Turnaround: Reference laboratories report within 1 day. Ask your own lab for its in-house time.
Why it matters
Digoxin has a narrow therapeutic index. Adverse effects rise above 1.2 ng/mL. Levels above 2 ng/mL add toxicity without adding benefit, and toxicity can be fatal. In heart failure trial data, higher levels tracked with higher mortality. A correctly timed level, read with K⁺, creatinine and the ECG, decides between dose adjustment, observation and the antidote.
Clinical Pearls
References
- Advanz Pharma (US) Corp. (2025). Lanoxin (digoxin) tablets, for oral use [prescribing information] (DailyMed version 12, January 2025). DailyMed, National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d91e3646-4c63-4512-ab22-db39c085c4dc
- BTG International. (2017). DigiFab (digoxin immune fab [ovine]) for injection [prescribing information] (revised June 2017). DailyMed, National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=c05ee6a5-c98b-45f4-83fd-40781639d653
- Cao, D., Arens, A. M., Chow, S. L., Easter, S. R., Hoffman, R. S., Lagina, A. T., Lavonas, E. J., et al. (2025). Part 10: Adult and pediatric special circumstances of resuscitation: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation, 152(suppl 2), S578–S672. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/adult-and-pediatric-special-circumstances-of-resuscitation. https://doi.org/10.1161/CIR.0000000000001380
- Andrews, P., Anseeuw, K., Kotecha, D., Lapostolle, F., & Thanacoody, R. (2023). Diagnosis and practical management of digoxin toxicity: A narrative review and consensus. European Journal of Emergency Medicine, 30(6), 395–401. https://doi.org/10.1097/MEJ.0000000000001065
- Joglar, J. A., Chung, M. K., Armbruster, A. L., Benjamin, E. J., Chyou, J. Y., Cronin, E. M., et al. (2024). 2023 ACC/AHA/ACCP/HRS guideline for the diagnosis and management of atrial fibrillation. Circulation, 149(1), e1–e156. https://doi.org/10.1161/CIR.0000000000001193
- van Veldhuisen, D. J., Rienstra, M., Mosterd, A., Alings, M., Voors, A. A., Damman, K., et al. (2026). Low-dose digoxin in patients with heart failure with reduced or mildly reduced ejection fraction: A randomized controlled trial (DECISION). Nature Medicine, 32(7), 2647–2653. https://doi.org/10.1038/s41591-026-04406-6
- Rathore, S. S., Curtis, J. P., Wang, Y., Bristow, M. R., & Krumholz, H. M. (2003). Association of serum digoxin concentration and outcomes in patients with heart failure (landmark trial analysis, DIG trial). JAMA, 289(7), 871–878. https://doi.org/10.1001/jama.289.7.871
- Labcorp. (2026). Digoxin (test 007385): specimen requirements, reference range and limitations. Labcorp test menu. https://www.labcorp.com/tests/007385/digoxin
- Lasa, J. J., Dhillon, G. S., Duff, J. P., Hayes, J., Kamath-Rayne, B. D., Levy, A., et al. (2025). Part 8: Pediatric advanced life support: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation, 152(suppl 2), S479–S537. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/pediatric-advanced-life-support. https://doi.org/10.1161/CIR.0000000000001368
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.