

Bedside Snapshot
- Normal (Adult)
- 200–400 mg/dL (2–4 g/L); typical, lab-specific. Higher in pregnancy (third trimester 373–619 mg/dL) and inflammation
- Critical Values
- <100 mg/dL (<1 g/L) (typical; lab-specific). No critical high
- High Suggests
- Acute-phase response (infection, inflammation, recent surgery or trauma, cancer), pregnancy, estrogen therapy. Needs no treatment of its own
- Low Suggests
- Massive hemorrhage and dilution (trauma, PPH)
- DIC (abruption, amniotic fluid embolism, APL)
- Fibrinolytics; liver failure
- Congenital deficiency; sample artifact
- Act Now If
- Bleeding with fibrinogen ≤150 mg/dL (PPH <200), or any value <100: replace with cryoprecipitate or concentrate, give tranexamic acid early, recheck after each dose; notify receiving/medical control
- Watch Out For
- A "normal" value in late pregnancy or sepsis, where fibrinogen usually runs high, can already mean consumption. Trend it during bleeding
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult | 200–400 mg/dL | 2–4 g/L | Typical Clauss range; labs quote limits from about 150 to 450 mg/dL by method and analyzer |
| Pregnancy | 1st trimester 244–510 mg/dL 2nd trimester 291–538 mg/dL 3rd trimester 373–619 mg/dL | 2.4–5.1 g/L 2.9–5.4 g/L 3.7–6.2 g/L | Rises each trimester. A value that is normal for a nonpregnant adult can be low at term |
| Older adult | Same as adult | Same as adult | — |
| Children | Same as adult | Same as adult | Use the lab's age-specific range for neonates |
Severity & critical values
| Level | Conventional | SI | What it means / typical findings |
|---|---|---|---|
| High | >400 mg/dL | >4 g/L | Acute-phase response or pregnancy. Not a bleeding problem; treat the cause |
| Normal | 200–400 mg/dL | 2–4 g/L | Adequate for clotting. In late pregnancy or sepsis, where levels usually run high, a low-normal value may mean consumption |
| Low | 151–199 mg/dL | 1.51–1.99 g/L | Postpartum hemorrhage (PPH): below 200 mg/dL with ongoing bleeding is a replacement trigger and predicts severe bleeding |
| Low, trauma trigger | 100–150 mg/dL | 1–1.5 g/L | Major traumatic bleeding: ≤150 mg/dL is the replacement trigger |
| Critical | <100 mg/dL | <1 g/L | Typical; lab-specific. Clot formation is impaired; scores in the ISTH overt DIC score. Replace now if bleeding |
Conversion: mg/dL × 0.01 = g/L (200 mg/dL = 2 g/L)
Causes of Abnormal Results
High (hyperfibrinogenemia >400 mg/dL)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Acute-phase response | Infection and sepsis, inflammatory disease, the days after surgery or trauma, myocardial infarction, cancer | Fever, raised C-reactive protein and white count; the liver makes more fibrinogen during inflammation |
| Pregnancy | Normal rise through each trimester | Gestational age; compare with the pregnancy range |
| Estrogen | Combined oral contraceptives, hormone therapy | Medication history |
Don't treat a high fibrinogen. It needs nothing of its own. The danger is what it covers up: a septic or pregnant patient with a merely normal level may already be burning through it.
Low (hypofibrinogenemia <200 mg/dL)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Loss and dilution | Major trauma, postpartum hemorrhage, surgical or GI bleeding, large-volume crystalloid or red-cell-only resuscitation | Shock and ongoing transfusion; fibrinogen is usually the first clotting factor to reach a critical level |
| Consumption: hemorrhagic DIC | Placental abruption, amniotic fluid embolism, acute promyelocytic leukemia, severe trauma | Oozing from lines and wounds, very high D-dimer, falling platelets, prolonged PT |
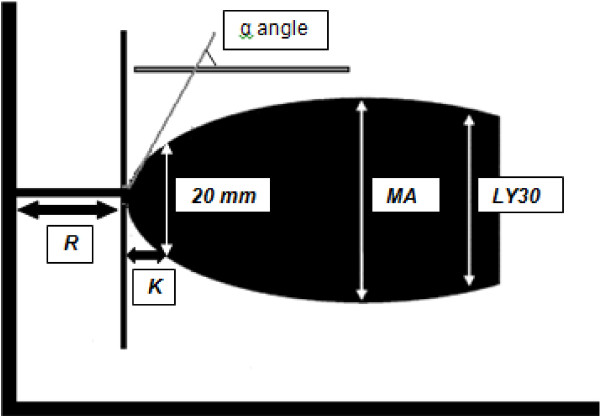
| Fibrinolysis | Fibrinolytics (alteplase, tenecteplase), hyperfibrinolysis after major trauma | Recent lytic; bleeding at puncture sites; high lysis on viscoelastic testing |
| Low synthesis | Acute liver failure, advanced cirrhosis | High INR, low albumin; D-dimer less striking than in DIC |
| Drug effect | Asparaginase (leukemia chemotherapy) | Current chemotherapy; usually found on routine monitoring |
| Congenital | Afibrinogenemia, hypofibrinogenemia, dysfibrinogenemia | Lifelong bleeding (umbilical stump, joints, after surgery) or a family history; dysfibrinogenemia can also cause clots |
| Spurious | Clotted sample, heparin from a line, direct thrombin inhibitors | Unexpected low value in a patient who is not bleeding |
Thresholds used on this page: low <200 mg/dL; trauma replacement trigger ≤150 mg/dL; PPH replacement trigger <200 mg/dL with bleeding; critical <100 mg/dL.
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Check the method (Clauss is the reference; a PT-derived value can overestimate), a clotted tube, a draw from a heparinized line, and direct thrombin inhibitors (dabigatran, argatroban, bivalirudin). Repeat an unexpected value.
- How sick is the patient? Active bleeding, shock, a massive transfusion protocol (MTP), obstetric hemorrhage or head injury make a low value an emergency. An isolated low value in a well patient needs a repeat and a workup. Not products.
- Read it against what is expected. Fibrinogen normally runs high in late pregnancy and inflammation. In those settings a normal-looking value may already mean consumption. While someone bleeds, watch the trend over hours. It counts for more than any single result.
- Look at the whole coagulation picture. Read it with the PT/INR, aPTT, platelets, D-dimer, ionized calcium and, where available, a viscoelastic test.
- Classify. Hemorrhage with a level at or below the replacement trigger, DIC by the ISTH 2025 overt DIC score, liver failure, drug effect, or a congenital disorder.
- Escalate. Replace fibrinogen in the bleeding patient, activate or continue the MTP, and involve hematology for DIC, unexplained values or a congenital disorder.
Patterns
| Pattern | Suggests |
|---|---|
| Low fibrinogen, very high D-dimer, falling platelets, prolonged PT | Hemorrhagic DIC or major trauma coagulopathy |
| Low fibrinogen, high INR, low albumin, modest D-dimer | Liver failure (low synthesis) |
| Low fibrinogen after large-volume fluid or red cells without plasma or cryoprecipitate | Dilution |
| Low fibrinogen soon after alteplase or tenecteplase | Fibrinolytic effect; the drug also keeps working in the tube |
| Normal or high fibrinogen, low platelets, high D-dimer in sepsis | Thrombotic (sepsis) DIC: fibrinogen is often preserved |
| Low Clauss fibrinogen with a normal fibrinogen antigen | Dysfibrinogenemia, or direct thrombin inhibitor interference |
Fibrinogen in the ISTH 2025 overt DIC score
Apply the score only to a patient with a condition known to cause DIC. A total of 5 or more fits overt DIC.
| Component | Points |
|---|---|
| Fibrinogen | <100 mg/dL (<1 g/L): 1 |
Only the fibrinogen row appears in this table. The platelet, D-dimer and PT rows are not on this page. Score them from the ISTH 2025 table (Iba et al., in References) before you apply the total of 5 or more.
Management Priorities
Doses vary by protocol; follow local protocols and medical direction.
Emergency: Major bleeding with fibrinogen ≤150 mg/dL (or a viscoelastic fibrinogen deficit)
- Control the source: Use direct pressure, a tourniquet, surgery or interventional radiology, and get the MTP moving.
- Tranexamic acid early: Start it inside 3 hours of injury. Don't hold it for fibrinogen or viscoelastic results.
- Replace fibrinogen: cryoprecipitate 10 units or fibrinogen concentrate 3–4 g IV. Ten units is a common US pool dose and supplies at least 1.5 g. Concentrate at 3–4 g delivers more, so the two are not equals dose for dose. Protocol sets the dose. Expect to redose by level in a large adult. Plasma does not replace either product if either one is on hand.
- Correct the rest: Hold ionized calcium in the normal range (1.1–1.3 mmol/L). Prevent hypothermia. Correct acidosis.
- Monitor & repeat: Recheck Clauss fibrinogen or the viscoelastic test after every dose. Redose to hold fibrinogen above 150 mg/dL for as long as the bleeding continues.
Emergency: Postpartum hemorrhage with fibrinogen <200 mg/dL
- Tranexamic acid: Give 1 g IV as soon as PPH is diagnosed, and within 3 hours of birth. Uterotonics and source control follow the obstetric protocol.
- Replace fibrinogen: Cryoprecipitate 10 units or fibrinogen concentrate, per protocol. Aim for at least 150–200 mg/dL.
- Look for DIC: Abruption and amniotic fluid embolism use up fibrinogen quickly. Check platelets, PT and D-dimer.
- Monitor & repeat: Recheck the level after each dose. Set further doses by the measured value.
Medications
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Cryoprecipitate | 10 units IV (for example two 5-unit pools) for fibrinogen ≤150 mg/dL in trauma or <200 mg/dL in PPH; redose by level: no fixed max | 1–2 units per 10 kg IV (or 2–3 mL/kg), a typical blood-bank dose; redose by level: no fixed max | Each unit holds at least 150 mg fibrinogen plus factor VIII, factor XIII and von Willebrand factor. 10 units raise fibrinogen about 50–100 mg/dL in an adult; children about 60–100 mg/dL. No crossmatch needed; thaw takes up to 15 min. Ten units is a US convention and may under-replace in a large adult, so redose by level |
| Fibrinogen concentrate (Fibryga, RiaSTAP) | Trauma: 3–4 g IV. Fibryga acquired deficiency: 4 g IV; redose 4 g if fibrinogen ≤200 mg/dL or FIBTEM A10 ≤10 mm; no fixed max | Fibryga: 70 mg/kg IV (<12 yr) or 50 mg/kg IV (≥12 yr); same redose triggers; no fixed max | Known dose in grams; reconstituted to 20 mg/mL, so 4 g is 200 mL. Children under 12 have lower recovery and may need more. Only Fibryga is labeled for acquired deficiency. Thrombosis warning: monitor for signs and symptoms of thrombosis; infuse at no more than 20 mL/min in acquired deficiency (5 mL/min in congenital deficiency) |
| Tranexamic acid | Trauma: 1 g IV/IO over 10 min, then 1 g over 8 hr. PPH: 1 g IV over 10 min; repeat 1 g if bleeding continues at 30 min; max 2 g | Trauma (off-label, per local protocol): 15 mg/kg IV/IO over 10–20 min, then 2 mg/kg/hr for 8 hr; max 1 g per dose | Within 3 hours of injury or birth only. Protects the new clot from breakdown; does not raise fibrinogen |
| Calcium chloride 10% | Ionized calcium below 1.1 mmol/L during massive transfusion: 1 g (10 mL) IV via a large or central vein; repeat by ionized calcium | 20 mg/kg (0.2 mL/kg) IV; max 1 g per dose | Citrate in blood products binds calcium; low calcium worsens clotting |
Definitive care & disposition
- Trauma and massive transfusion: trauma center, damage-control surgery or embolization; viscoelastic- or lab-guided replacement; ICU.
- Obstetric hemorrhage: obstetrics, anesthesia and blood bank together; continue fibrinogen-guided replacement; ICU for DIC or massive transfusion.
- DIC: treat the cause (delivery or evacuation, antibiotics and source control, leukemia therapy). Replace fibrinogen when the patient is bleeding; hematology consult.
- Fibrinolytic bleeding: stop the lytic, check fibrinogen, and give cryoprecipitate to keep fibrinogen at 150 mg/dL or higher per the stroke or STEMI bleeding protocol.
- Congenital deficiency: Hematology directs the concentrate. Neither product is indicated for dysfibrinogenemia.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
No field device measures fibrinogen. In the ED, the operating room and some transport-capable centers, viscoelastic analyzers (ROTEM, TEG and cartridge-based systems) report a fibrinogen-specific clot strength within minutes. The Clauss level comes from the central lab. In the field, EMS runs on clinical grounds. What you actually have: hemorrhage control, tranexamic acid inside 3 hours, and blood products if your service carries them.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Before departure | Last fibrinogen or FIBTEM with its time, PT/INR, platelets, ionized calcium; products given (units or grams) and times; tranexamic acid dose and time |
| Blood products en route | Thawed cryoprecipitate expires 6 hr after thawing as an unentered unit, 4 hr once the bag is entered or pooled open: confirm thaw and spike times against transport time |
| Re-check | After each fibrinogen dose and with each massive-transfusion lab set at the receiving center |
| Redirect | Ongoing hemorrhage with a low fibrinogen needs a center that can give cryoprecipitate or concentrate and definitive hemostasis |
Scope: Starting and continuing blood products and fibrinogen concentrate is a skill set for critical care transport, flight or RN crews (RN/CCT), per local protocol.
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | The coagulation system is still maturing; ranges are age-specific | Use the lab's age-specific range; ABO-compatible cryoprecipitate may be preferred in neonates |
| Children & adolescents | Same range as adults. Under 12 years, concentrate has lower recovery and a shorter half-life | Weight-based dosing; under 12 may need higher concentrate doses (see Management). No pediatric fibrinogen trigger is established: adult thresholds are extrapolated, and the pediatric cryoprecipitate dose in Medications is a typical blood-bank dose |
| Pregnancy | Rises every trimester to 373–619 mg/dL in the third | A value of 200 mg/dL or less early in PPH predicts severe bleeding; do not reassure with a nonpregnant normal |
| Older adults | No clinically meaningful difference | Interpret with the adult range |
| Liver disease | Low synthesis; acquired dysfibrinogenemia possible | Clauss can read lower than the antigen; PT-derived methods overestimate; replace only for bleeding |
| Congenital fibrinogen disorders | Absent, low or dysfunctional fibrinogen | Bleeding from birth or after minor procedures; some dysfibrinogenemias cause thrombosis; hematology-directed care |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Clotted sample | ↓ | Fibrinogen is used up in the clot in the tube | Reject and redraw; mix the citrate tube gently right after the draw |
| Draw from a heparinized line | ↓ (Clauss) | High heparin concentrations slow the thrombin-clotting endpoint | Draw from a fresh venipuncture or after an adequate discard |
| Wrong tube or short fill | Unreliable | The test needs citrated plasma at the right blood-to-citrate ratio | Light-blue top (3.2% citrate) filled to the line |
Medications
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Direct thrombin inhibitors (dabigatran, argatroban, bivalirudin) | False − | They inhibit the thrombin reagent; reagent-dependent | Note the drug on the request; the lab can confirm with an antigen or another method |
| Fibrinolytics | True ↓ and in-tube breakdown | Plasmin keeps cleaving fibrinogen after the draw | Read with the clinical picture; follow the lytic bleeding protocol |
| Asparaginase, estrogen | True ↓ / true ↑ | Lower or raise liver synthesis | Medication history |
Physiologic & assay-specific
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Lipemia, high bilirubin | False − (optical) | Turbidity interferes with optical clot detection | Tell the lab; it can use another method |
| PT-derived fibrinogen | False + | Calculated from the PT clot curve; overestimates in liver disease, DIC and anticoagulation | Ask for a Clauss fibrinogen in bleeding or DIC |
| Dysfibrinogenemia | Clauss ↓, antigen normal | Normal amount, abnormal function | Fibrinogen antigen and hematology referral |
| Viscoelastic tests | Device-specific | Measure whole-blood clot strength, not a plasma level | Use device-specific cut-offs; do not convert directly to mg/dL |
Common misinterpretations
- "Normal" in late pregnancy or sepsis: These patients usually run high. A normal value can already mean consumption.
- Normal PT and aPTT exclude low fibrinogen: Neither one rules it out. Order fibrinogen in every major bleed.
- Low fibrinogen always means DIC: Don't assume DIC. Dilution, liver failure, lytics and lab artifact are common.
- Plasma will fix it: Plasma carries little fibrinogen, and the amount varies. Use cryoprecipitate or concentrate.
Physiology & Test Basics
What it measures
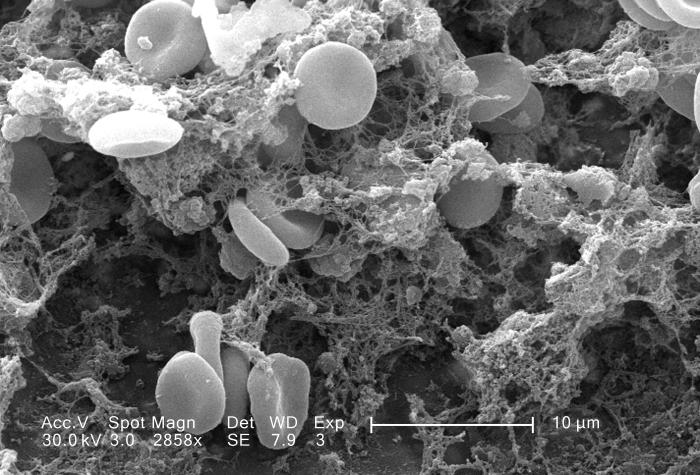
Fibrinogen (factor I) is the plasma protein that thrombin turns into fibrin, the mesh that holds a clot together. This page is about the plasma fibrinogen level. Read it next to the coagulation panel, which holds the PT/INR, aPTT and D-dimer. Fibrinogen is the most abundant clotting factor. In major bleeding it is usually the first one to run out.
Physiology & regulation
- Source: The liver makes it. Liver failure drives it low.
- Clot formation: Thrombin cuts fibrinogen into fibrin monomers, and those monomers join into chains. Factor XIIIa cross-links them into a stable clot.
- Platelets: Fibrinogen also bridges activated platelets. That supports clot strength as well as clot volume.
- Breakdown: Plasmin breaks down fibrinogen and fibrin. The cross-linked fragments are what D-dimer measures.
- Acute-phase reactant: Production climbs with inflammation and in pregnancy.
- Persistence: Without bleeding or consumption, a replaced dose lasts days. In active hemorrhage or DIC, it is used up much faster.
How it is measured
- Specimen: light-blue top (3.2% sodium citrate), filled to the line and mixed gently; platelet-poor plasma.
- Clauss assay (reference): Diluted plasma is clotted with a high thrombin concentration. The clotting time gives the functional level.
- PT-derived fibrinogen: Some analyzers calculate it from the PT. Those results are not interchangeable with Clauss.
- Fibrinogen antigen: An immunologic measure of the amount. Pair it with Clauss to diagnose dysfibrinogenemia.
- Viscoelastic tests: Whole blood, read at the bedside. The fibrinogen-specific clot strength comes out in mm.
Why it matters
In trauma and postpartum hemorrhage, a low fibrinogen means a coagulopathy that keeps the bleeding going. It guides the choice of cryoprecipitate or concentrate. In DIC it is one of the scored markers. In liver failure it shows synthetic function.
Clinical Pearls
References
- Iba, T., Levy, J. H., Maier, C. L., Helms, J., Umemura, Y., Moore, H., et al. (2025). Updated definition and scoring of disseminated intravascular coagulation in 2025: Communication from the ISTH SSC Subcommittee on Disseminated Intravascular Coagulation. Journal of Thrombosis and Haemostasis, 23(7), 2356–2362. https://doi.org/10.1016/j.jtha.2025.03.038
- Rossaint, R., Afshari, A., Bouillon, B., Cerny, V., Cimpoesu, D., Curry, N., et al. (2023). The European guideline on management of major bleeding and coagulopathy following trauma: Sixth edition. Critical Care, 27, 80. https://doi.org/10.1186/s13054-023-04327-7
- Escobar, M. F., Nassar, A. H., Theron, G., Barnea, E. R., Nicholson, W., Ramasauskaite, D., et al. (2022). FIGO recommendations on the management of postpartum hemorrhage 2022. International Journal of Gynecology & Obstetrics, 157(Suppl 1), 3–50. https://doi.org/10.1002/ijgo.14116
- Charbit, B., Mandelbrot, L., Samain, E., Baron, G., Haddaoui, B., Keita, H., et al. (2007). The decrease of fibrinogen is an early predictor of the severity of postpartum hemorrhage (landmark study). Journal of Thrombosis and Haemostasis, 5(2), 266–273. https://doi.org/10.1111/j.1538-7836.2007.02297.x
- AABB, American Red Cross, America's Blood Centers, & Armed Services Blood Program. (2024). Circular of information for the use of human blood and blood components (June 2024). AABB. https://www.aabb.org/docs/default-source/default-document-library/resources/circular-of-information-watermark.pdf
- Octapharma USA Inc. (2025). Fibryga (fibrinogen, human) lyophilized powder for reconstitution, for intravenous use: Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=e3422d2a-2cb6-6f49-0be7-cb960b3d5bd5
- Mackie, I., Casini, A., Pieters, M., Pruthi, R., Reilly-Stitt, C., & Suzuki, A. (2024). International Council for Standardisation in Haematology recommendations on fibrinogen assays, thrombin clotting time and related tests in the investigation of bleeding disorders. International Journal of Laboratory Hematology, 46(1), 20–32. https://doi.org/10.1111/ijlh.14201
- Abbassi-Ghanavati, M., Greer, L. G., & Cunningham, F. G. (2009). Pregnancy and laboratory studies: A reference table for clinicians (landmark reference-interval study). Obstetrics & Gynecology, 114(6), 1326–1331. https://doi.org/10.1097/AOG.0b013e3181c2bde8
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.