

Bedside Snapshot
- Normal (Adult)
- Adults 41–50% (0.41–0.50 L/L), a textbook range that is not sex-specific
Women 35–47% (0.35–0.47 L/L)
For a men's range use the interval on your report. About hemoglobin × 3 - Critical Values
- <20% or >60% (<0.20 or >0.60 L/L), typical; lab-specific
- High Suggests
- Dehydration or plasma loss (burns, dengue)
- Chronic hypoxia: lung or cyanotic heart disease, altitude, smoking
- Polycythemia vera
- Testosterone or epoetin
- Low Suggests
- Bleeding (may lag)
- Hemolysis
- Low production: iron, B12, kidney disease, marrow failure
- Dilution: IV fluids, pregnancy
- Act Now If
- Hct <20%, a falling trend, or bleeding with shock: control hemorrhage, large-bore IV access, notify receiving/medical control, prepare blood per protocol. Hct >60%: check hydration, neurologic symptoms, thrombosis
- Watch Out For
- A normal first Hct in acute hemorrhage: it falls only after fluid shifts or IV fluids dilute the blood. Treat the patient, not the number
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adults (Critical Care Transport; sex not stated) | 41–50% | 0.41–0.50 L/L | Single adult range, sex not stated. Men run higher than women (testosterone drives red cell production); the textbook range is not sex-specific, so use your lab's men's interval |
| Adult women (nonpregnant, Rosen's Table 121-1) | 35–47% | 0.35–0.47 L/L | — |
| Pregnancy | Anemia if <33% (1st and 3rd trimester) or <32% (2nd trimester) | <0.33 / <0.32 L/L | Plasma volume expands more than red cell mass, so Hct falls; lowest in the second trimester |
| Older adult | Same as adult | — | No age-specific range; a low value needs a cause, not an age explanation |
| Neonate (0–30 days, term) | 42–64% | 0.42–0.64 L/L | Highest at birth. Heel-stick (capillary) samples read higher than venous |
| Infant 1–<2 months | 33–54% | 0.33–0.54 L/L | Falling as fetal red cells are replaced |
| Infant 2–<3 months | 28–41% | 0.28–0.41 L/L | Physiologic nadir around 2–3 months in term infants |
| Infant 3–<6 months | 29–41% | 0.29–0.41 L/L | — |
| Infant 6–12 months | 31–41% | 0.31–0.41 L/L | — |
| Child 1–5 years | 31–44% | 0.31–0.44 L/L | — |
| Child 5–11 years | 35–44% | 0.35–0.44 L/L | — |
| Adolescent 11–18 years | Male 37–48%; female 34–44% | Male 0.37–0.48; female 0.34–0.44 L/L | Sexes diverge after puberty |
Severity & critical values
| Level | Conventional | SI | What it means |
|---|---|---|---|
| Normal | 41–50% on the single adult range (sex not stated); women 35–47%, so a woman between 35% and 41% is within her range | 0.41–0.50 / 0.35–0.47 L/L | — |
| Low (anemia) | Below the limit that applies: <41% on the single adult range; <35% for women | <0.41 / <0.35 L/L | Find the cause: bleeding, hemolysis, low production or dilution. Use hemoglobin and MCV to classify |
| Transfusion range (stable adult) | About <21% (hemoglobin <7 g/dL) | <0.21 L/L | Transfusion triggers are hemoglobin-based; Hct is an estimate (hemoglobin × 3). Higher triggers apply in some groups (see Interpretation) |
| High | Above the limit that applies: >50% on the single adult range; >47% for women | >0.50 / >0.47 L/L | Hemoconcentration until proven otherwise; repeat when euvolemic. A persistent Hct above 49% (men) or 48% (women) when euvolemic meets the WHO/ICC polycythemia-vera trigger even when it sits inside a lab's normal range |
| Critical | <20% or >60% | <0.20 or >0.60 L/L | Typical panic values (lab-specific; the Univ. of Iowa handbook lists ≤18% and ≥55% for adults). Low: poor oxygen-carrying capacity, ischemia. High: hyperviscosity and thrombosis risk |
Conversion: Hct % × 0.01 = L/L (SI volume fraction). Hct (%) ≈ hemoglobin (g/dL) × 3
Does the rule always hold? Only for normal-sized, normally filled red cells. A bigger gap points to a sample or analyzer problem, or to hypochromic cells.
Normal runs about 32–36 g/dL. Above about 36 g/dL, the number is rarely real. Suspect cold agglutinins, lipemia or another artifact.
Causes of Abnormal Results
High (Hct above the limit that applies: >50% on the single adult range, >47% in women)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Hemoconcentration (plasma loss) | Dehydration (vomiting, diarrhea, poor intake, heat, DKA or HHS), diuretics, major burns, dengue plasma leakage, relative polycythemia (Gaisbock syndrome: stress, smoking, obesity, hypertension) | Dry mucosa, tachycardia, high BUN; Hct falls with fluids. In dengue, a rising Hct in the critical phase signals plasma leakage |
| Hypoxia-driven (appropriate erythropoietin) | Cyanotic congenital heart disease, COPD, obstructive sleep apnea, high-altitude residence, smoking | Low SpO₂, cyanosis, clubbing; smokers run higher (carboxyhemoglobin) |
| Primary bone-marrow disease | Polycythemia vera (JAK2 mutation) | Persistent Hct >49% (men) or >48% (women), high WBC or platelets, splenomegaly, itching after bathing, unusual thrombosis |
| Inappropriate erythropoietin | Renal cell carcinoma, hepatocellular carcinoma, cerebellar hemangioblastoma, other erythropoietin-secreting tumors, erythrocytosis after kidney transplant | Hematuria or flank mass; normal SpO₂ |
| Drugs and hormones | Testosterone and anabolic steroids, erythropoiesis-stimulating agents (epoetin), blood doping | Medication history; testosterone labeling requires Hct checks before and during therapy |
| Neonatal polycythemia | Maternal diabetes, fetal growth restriction, delayed cord clamping (normal, small rise) | Venous Hct >65%: jaundice, low glucose, low platelets, breathing or neurologic signs |
Low (anemia: below the limit that applies, <41% on the single adult range, <35% in women)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Acute blood loss | Trauma, GI bleeding, ruptured ectopic pregnancy or aortic aneurysm, postpartum hemorrhage, surgery | Tachycardia, hypotension, visible or occult loss. First Hct may be normal |
| Hemolysis | Autoimmune hemolysis, sickle cell crisis, microangiopathy (TTP, HUS, DIC), G6PD deficiency, transfusion reaction | Jaundice, dark urine, high bilirubin and LDH, low haptoglobin, schistocytes |
| Low production | Iron, vitamin B12 or folate deficiency; hypothyroidism; chronic kidney disease (low erythropoietin); inflammation; marrow failure or infiltration (aplastic anemia, leukemia, myelodysplasia) | Low reticulocyte count; MCV low (iron) or high (B12, folate); other cell lines low in marrow disease |
| Sequestration | Acute splenic sequestration in sickle cell disease, hypersplenism | Enlarging spleen, abrupt fall in Hct, shock in a young child |
| Dilution | Large crystalloid volumes, pregnancy, SIADH, volume overload (heart failure, cirrhosis) | Recent fluids; hemoglobin, albumin and platelets fall together |
| Iatrogenic | Repeated blood sampling in ICU patients and neonates | Steady fall without bleeding; count the draws |
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Run the rule of three (Hct ≈ hemoglobin × 3 ±3) and the MCHC. Where did the sample come from? An arm with a running IV, a heel stick, a point-of-care conductivity cartridge, or an old or clotted tube.
- How sick is the patient? A low Hct with shock, ongoing bleeding, chest pain, dyspnea or syncope is the picture to look for. A high Hct brings its own list: headache, visual change or thrombosis.
- Acute or chronic, and the trend: Chronic anemia is often tolerated at levels that would cause shock if they came on over hours. Compare with the baseline and the fluid balance. The trend outranks any single value.
- Calculate: In a patient who is not bleeding, the expected transfusion rise is worth working out. One adult unit lifts hemoglobin about 1 g/dL (Hct about 3%). A child gets 10 mL/kg, which lifts hemoglobin about 2–3 g/dL (Hct about 6–9%). Do the hemoglobin × 3 and MCHC math too. Confirm pediatric volumes against the local protocol.
- Classify: For anemia, sort by MCV and reticulocyte count. A high Hct gets sorted by volume status first. When euvolemic, if Hct stays >49% (men) or >48% (women), the 2022 WHO and International Consensus Classification criteria call for JAK2 testing. A serum erythropoietin level helps separate primary from secondary causes.
- Escalate or dispose: Hematology handles suspected polycythemia vera or hyperviscosity. A symptomatic neonate with a venous Hct >65% goes to neonatology. Transfusion, though, follows hemoglobin and the clinical picture, never the Hct alone.
Transfusion thresholds (hemoglobin-based)
| Setting | Hemoglobin trigger | ≈ Hct | Notes |
|---|---|---|---|
| Stable hospitalized adults | <7 g/dL | About 21% | AABB 2023, strong recommendation |
| Cardiac surgery | <7.5 g/dL | About 22–23% | AABB 2023: threshold clinicians may choose, per the trials |
| Orthopedic surgery or preexisting cardiovascular disease | <8 g/dL | About 24% | AABB 2023 |
| Acute myocardial infarction (hospitalized) | <10 g/dL (liberal) | About 30% | AABB 2025, conditional: restrictive 7–8 g/dL may increase mortality in MI |
| Critically ill children, stable | <7 g/dL | About 21% | Not for hemoglobinopathy, cyanotic heart disease or severe hypoxemia |
| Children with congenital heart disease | 7 g/dL (biventricular repair); 9 g/dL (single-ventricle palliation); 7–9 g/dL (uncorrected) | About 21–27% | AABB 2023, conditional |
| Hemorrhagic shock or massive bleeding | No numeric trigger | — | Thresholds assume hemodynamic stability; transfuse for shock and ongoing loss per hemorrhage protocol |
Pattern recognition
| Pattern | Suggests |
|---|---|
| High Hct, high BUN, dry mucosa | Hemoconcentration from dehydration; repeat after fluids |
| High Hct with high WBC or platelets, splenomegaly | Polycythemia vera; JAK2 testing |
| High Hct with low SpO₂ or cyanosis | Secondary (hypoxic) erythrocytosis: lung, sleep apnea, cyanotic heart disease |
| Rising Hct in a patient with dengue | Plasma leakage: watch for shock |
| Low Hct with high bilirubin and LDH | Hemolysis |
| Hct far below hemoglobin × 3, MCHC >36 g/dL | Artifact: cold agglutinins or lipemia; warm the sample or rerun |
Field & Transport Considerations
Point-of-care testing
- Cartridge blood-gas and chemistry analyzers: Many report Hct from electrical conductivity, corrected with the measured sodium. Low total protein reads falsely low, as after large crystalloid volumes, bypass or critical illness. Very high protein or a very high WBC count reads falsely high.
- Co-oximetry blood gas analyzers: They measure total hemoglobin and report a calculated Hct. Trust the hemoglobin. The Hct is derived from it.
- Trend on one device: A surprising value deserves a laboratory CBC before you act on it alone.
Before and during interfacility transport
- Hand off: the latest Hct and hemoglobin with draw times and source (lab or point of care), the trend, units of blood given and when, and ongoing losses.
- Re-check: Repeat it after transfusion or large fluid volumes, and whenever vital signs change. A bleeding patient never waits on a lab value before transport.
Altitude and flight
- Anemia: Oxygen content falls with hemoglobin, and cabin altitude lowers PaO₂ on top of that. A normal SpO₂ does not mean oxygen delivery is adequate. Give oxygen and watch mental status, heart rate and lactate.
- Erythrocytosis: Patients with cyanotic heart disease or polycythemia tolerate dehydration poorly. Keep them hydrated on long transports.
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Hct is highest at birth (42–64%), then falls to a nadir around 2–3 months (28–41%) | Use age-specific ranges. Venous Hct >65% is neonatal polycythemia; confirm a high heel-stick value with a venous sample |
| Children & adolescents | Ranges rise through childhood; boys exceed girls after puberty | Acute splenic sequestration and aplastic crisis in sickle cell disease cause rapid falls. Stable critically ill children: consider transfusion at hemoglobin <7 g/dL |
| Pregnancy | Plasma volume expands more than red cell mass; Hct lowest in the second trimester | Anemia if <33% (1st and 3rd trimester) or <32% (2nd). Iron deficiency is the most common cause after dilution |
| Older adults | Same adult ranges | A low Hct is a sign of disease (bleeding, kidney disease, nutrition, marrow); chronic anemia may present as fatigue, dyspnea or worsening heart failure |
| CKD / dialysis | Low erythropoietin causes chronic anemia; ultrafiltration concentrates blood | Compare pre- and post-dialysis values carefully; epoetin therapy raises Hct over weeks |
| Other: altitude, smoking, testosterone | Long-term residence at altitude and smoking raise Hct; testosterone raises Hct into the male range | Interpret against the right baseline; CDC anemia cutoffs are adjusted for altitude and smoking; testosterone users need Hct monitoring |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Prolonged tourniquet | ↑ | Water leaves the occluded vein; cells concentrate | Release promptly; redraw if prolonged |
| Draw from or above a running IV | ↓ | Dilution with infusate | Draw from the other arm or follow line-sampling policy |
| Heel-stick (capillary) sample in neonates | ↑ | Capillary samples read higher than venous | Confirm a high value with a venous sample |
| Clotted or poorly mixed sample | Unreliable | Cells trapped in clots; uneven distribution | Invert the EDTA tube as directed; reject and redraw clotted samples |
| In vitro hemolysis | ↓ | Lysed cells are not counted | Gentle collection; redraw |
| Delayed processing at room temperature (1–4 days) | ↑ | Red cells swell; MCV rises | Run promptly, or refrigerate per lab policy |
Physiologic / biologic
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Cold agglutinins | ↓ | Red cells clump and are counted as fewer, larger cells; MCHC high | Warm the sample to 37 °C and rerun, or use a spun Hct |
| Severe hyperglycemia (≥600 mg/dL) | ↑ | Cells swell in the analyzer diluent; MCV high, MCHC low | Use a spun Hct, or interpret with caution |
| Hyperleukocytosis (very high WBC) | ↑ | White cells counted in the red cell channel | Spun Hct or manual review |
| Posture (supine) | ↓ | Plasma volume is higher lying down, so Hct runs a few points (about 3%) lower than upright | Draw in the same posture when trending |
| Lipemia | Hct reliable; hemoglobin ↑ | Turbidity raises measured hemoglobin, not the Hct | Expect a high MCHC; trust the Hct |
Assay & device-specific
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Conductivity Hct with low total protein | ↓ | Plasma conducts more when protein is low | Use co-oximetry hemoglobin or a lab CBC |
| Conductivity Hct with high protein or a very high WBC count | ↑ | Protein lowers plasma conductivity; white cells insulate like red cells | Confirm with a lab CBC |
| Calculated Hct (co-oximeter, from hemoglobin) | Varies | Assumes a normal MCHC | Use the measured hemoglobin for decisions |
Common misinterpretations
- "Normal Hct, so no major bleed": Early hemorrhage leaves the ratio unchanged. Treat the mechanism and the vital signs.
- "High Hct means polycythemia": Most high values are hemoconcentration. Repeat it once the patient is euvolemic.
- "Hct fell after fluids, so new bleeding": Dilution lowers Hct too. Still, rule out bleeding clinically before you call it dilution.
- "Small cells always mean a lower Hct than expected": Iron deficiency runs the other way. A low MCHC pushes the Hct above hemoglobin × 3.
Physiology & Test Basics
What it measures
Hematocrit (Hct), also called packed cell volume (PCV), is the share of whole blood volume that red cells take up. Hemoglobin, the oxygen-carrying protein concentration, and the red cell count each have their own page. A Hct of 45% means red cells fill 45% of the blood volume. Plasma fills the rest.
Physiology & regulation
- Erythropoietin: The kidneys release it when tissue oxygen runs low. It drives red cell production in the marrow.
- Two levers: Hct moves with red cell mass: production, loss or destruction. It also moves with plasma volume: dehydration, fluids, pregnancy.
- Sex and hormones: Testosterone drives red cell production. That is why men run higher after puberty.
- Viscosity: Viscosity climbs steeply as Hct rises. Very high values slow microcirculatory flow and push toward thrombosis.
- Oxygen content: Oxygen content rides on hemoglobin and its saturation. Hct itself does not set it.
How it is measured
- Specimen: Whole blood goes in a lavender-top (EDTA) tube, as part of the CBC. Infants get a microtainer. Don't centrifuge it for a CBC. Fasting isn't needed.
- Automated analyzer: The analyzer counts red cells and measures their size. Then it calculates Hct = RBC count (×10⁶/µL) × MCV (fL) ÷ 10.
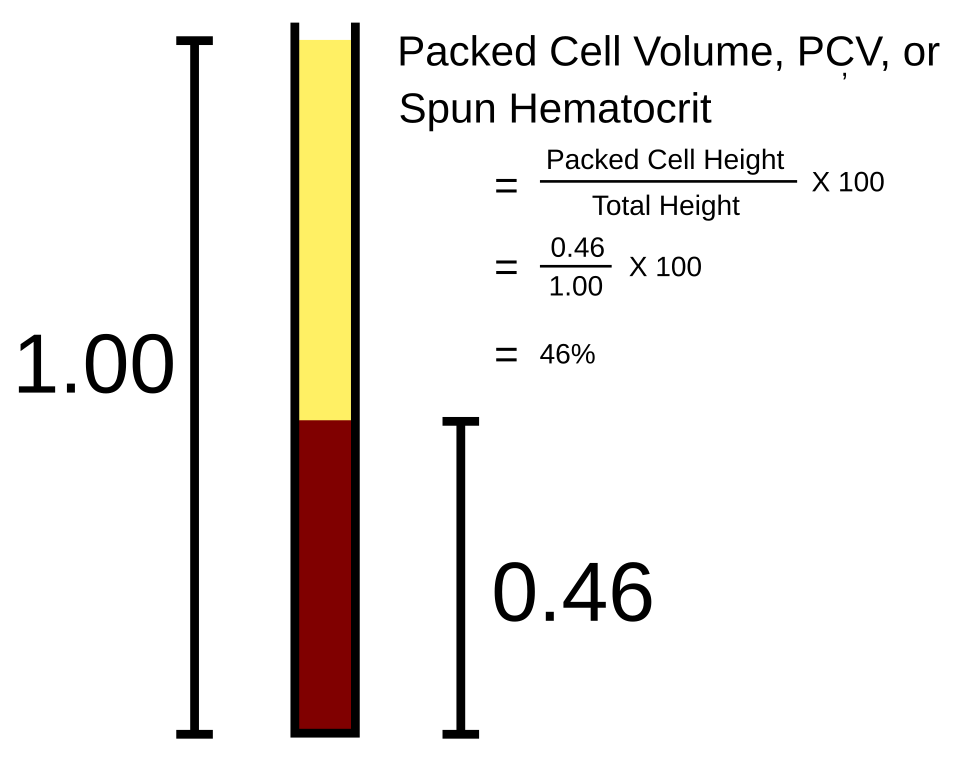
- Spun (micro) Hct: A capillary tube is spun down. You measure the packed red cell column against the total column (Figure 1). It checks for analyzer artifacts.
- Point of care: Conductivity cartridges and co-oximeters answer in minutes. Lab turnaround runs about 1 hour after receipt.
Why it matters
Hct is one of the fastest numbers you can get for blood loss, hemoconcentration and erythrocytosis, and many point-of-care devices report it. It is a volume ratio. It moves with plasma volume as much as with red cells. Read it with hemoglobin, vital signs and fluid balance.
Clinical Pearls
References
- Carson, J. L., Stanworth, S. J., Guyatt, G., Valentine, S., Dennis, J., Bakhtary, S., et al. (2023). Red blood cell transfusion: 2023 AABB international guidelines. JAMA, 330(19), 1892–1902. https://doi.org/10.1001/jama.2023.12914
- Pagano, M. B., Stanworth, S. J., Dennis, J., Bakhtary, S., Callum, J., Carson, J. L., et al. (2025). Red cell transfusion in acute myocardial infarction: AABB international clinical practice guidelines. Annals of Internal Medicine, 178(10), 1469–1477. https://doi.org/10.7326/ANNALS-25-00706
- Tefferi, A., & Barbui, T. (2023). Polycythemia vera: 2024 update on diagnosis, risk-stratification, and management. American Journal of Hematology, 98(9), 1465–1487. https://doi.org/10.1002/ajh.27002
- Gulati, G., Uppal, G., & Gong, J. (2022). Unreliable automated complete blood count results: Causes, recognition, and resolution. Annals of Laboratory Medicine, 42(5), 515–530. https://doi.org/10.3343/alm.2022.42.5.515
- University of Iowa Health Care, Department of Pathology. (2025). Hematocrit (packed cell volume, PCV): Reference range and critical values. Laboratory Services Handbook. https://www.healthcare.uiowa.edu/path_handbook/handbook/test955.html
- University of Chicago Medicine Clinical Laboratories. (2021). Critical value list. https://edge.sitecorecloud.io/unichicagomc-81nbqnb3/media/pdfs/adult-pdfs/research/critical_value_list.pdf
- US Food and Drug Administration. (2020). 510(k) decision summary K183680: i-STAT CHEM8+ cartridge with the i-STAT 1 System (hematocrit by conductivity; interfering substances). https://www.accessdata.fda.gov/cdrh_docs/reviews/K183680.pdf
- Centers for Disease Control and Prevention. (1998). Recommendations to prevent and control iron deficiency in the United States (source of the hemoglobin and hematocrit anemia cutoffs by age, sex and trimester, with altitude and smoking adjustments; still the US reference). MMWR Recommendations and Reports, 47(RR-3), 1–29. https://www.cdc.gov/mmwr/preview/mmwrhtml/00051880.htm
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.