

Bedside Snapshot
- Normal (Adult)
- Arterial: pH 7.35–7.45 ([H⁺] 35–45 nmol/L)
Venous: about 0.04 lower (7.31–7.41) - Critical Values
- pH <7.20 or >7.60 ([H⁺] >63 or <25 nmol/L); typical, lab-specific
- High Suggests
- Hyperventilation: hypoxemia, PE, sepsis, early salicylate
- Overventilation by bag or ventilator
- Vomiting or NG suction
- Diuretics, low K⁺, alkali load
- Low Suggests
- Hypoventilation: opioids, COPD, exhaustion
- Lactic acidosis: shock, sepsis, seizures
- DKA, including euglycemic
- Toxic alcohols, salicylate, kidney failure
- Act Now If
- pH <7.20 or >7.60, PaCO₂ rising as pH falls, or altered mental status: support ventilation, monitor and 12-lead ECG, check K⁺, glucose and ionized Ca²⁺; notify receiving/medical control
- Watch Out For
- A normal pH does not mean a normal acid–base state: two opposing disorders can cancel out. Read PaCO₂, HCO₃⁻ and the anion gap every time.
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adult: arterial | pH 7.35–7.45 | [H⁺] 35–45 nmol/L | Mean about 7.40 ([H⁺] 40 nmol/L) |
| Adult: peripheral venous | pH 7.31–7.41 | [H⁺] about 39–49 nmol/L | About 0.04 lower than arterial (Critical Care Transport); read against venous norms |
| Pregnancy | Upper end of normal (third-trimester mean about 7.44) | [H⁺] about 36 nmol/L | Compensated respiratory alkalosis: PaCO₂ near 30 mmHg, HCO₃⁻ lower |
| Older adult | Same as adult | Same as adult | — |
| Children | Same as adult | Same as adult | Neonates: use the lab's age-specific range; cord and first-day values differ |
Severity & critical values
| Level | Conventional | SI | What it means / typical findings |
|---|---|---|---|
| Critical (low) | pH <7.20 | [H⁺] >63 nmol/L | Severe acidemia: falling contractility and BP, poor vasopressor response, dysrhythmia. Below 7.00 ([H⁺] >100 nmol/L) is the severe DKA band |
| Acidemia | pH 7.20–7.34 | [H⁺] 46–63 nmol/L | Find the cause: PaCO₂ high (respiratory) or HCO₃⁻ low (metabolic). DKA criterion is pH <7.30 |
| Normal | pH 7.35–7.45 | [H⁺] 35–45 nmol/L | Does not exclude a mixed disorder: check PaCO₂, HCO₃⁻ and the anion gap |
| Alkalemia | pH 7.46–7.60 | [H⁺] 25–34 nmol/L | Hyperventilation or metabolic alkalosis; expect low K⁺ and ionized Ca²⁺ |
| Critical (high) | pH >7.60 | [H⁺] <25 nmol/L | Severe alkalemia: low ionized Ca²⁺ with tetany, seizures, delirium; dysrhythmia; arteriolar and coronary constriction |
Conversion: [H⁺] in nmol/L = 10(9 − pH). pH 7.40 gives 40 nmol/L. Every 0.1 drop in pH adds about 25% to [H⁺].
Plug in normal values: HCO₃⁻ 24 mEq/L and PaCO₂ 40 mmHg give a 20:1 ratio and a pH of 7.40. The analyzer works out HCO₃⁻ from the measured pH and PaCO₂ using this equation.
Try it at normal values: 24 × 40 ÷ 24 = 40 nmol/L (pH 7.40). When the answer and the reported pH disagree, suspect a transcription or sampling error.
Causes of Abnormal Results
Low (acidemia, pH <7.35)
Ask which value pulled the pH down. Was it a high PaCO₂ (respiratory acidosis) or a low HCO₃⁻ (metabolic acidosis)? Both at once is the most dangerous pattern.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Respiratory: low drive | Opioids, sedatives, alcohol, head injury, stroke | Slow shallow breathing, rising EtCO₂, pinpoint pupils |
| Respiratory: lungs and airway | COPD exacerbation, tiring asthma, pneumonia, pulmonary edema, airway obstruction | Wheeze, accessory muscles, fatigue, confusion |
| Respiratory: pump failure | Guillain–Barré, myasthenia, high spinal cord injury, flail chest, obesity hypoventilation | Weak cough, paradoxical breathing, falling vital capacity |
| Metabolic, high anion gap: lactate | Shock, sepsis, hypoxia, seizures, CO or cyanide, metformin with AKI | Poor perfusion, high lactate |
| Metabolic, high anion gap: ketoacids | DKA (including euglycemic on SGLT2 inhibitors), alcoholic, starvation | Kussmaul breathing, vomiting, ketones |
| Metabolic, high anion gap: toxins and kidney | Methanol, ethylene glycol, salicylate; advanced AKI or CKD | Osmolal gap; tinnitus; rising creatinine |
| Metabolic, normal anion gap | Diarrhea, large-volume 0.9% saline, renal tubular acidosis, acetazolamide | High Cl⁻ |
High-anion-gap mnemonic (GOLDMARK): Glycols, Oxoproline, L-lactate, D-lactate, Methanol, Aspirin, Renal failure, Ketoacidosis. MUDPILES is the older version. The anion gap and delta gap formulas are on the bicarbonate page.
High (alkalemia, pH >7.45)
Is the PaCO₂ low (respiratory alkalosis) or the HCO₃⁻ high (metabolic alkalosis)? Metabolic alkalosis is the most common acid–base disorder in ICU patients. Treatment is often the cause.
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Respiratory: hypoxemia and lung | Pulmonary embolism, pneumonia, pulmonary edema, altitude | Tachypnea, low SpO₂ (PE may have a normal SpO₂) |
| Respiratory: central drive | Sepsis, early salicylate toxicity, stroke, fever, pain, anxiety, pregnancy | Tachypnea out of proportion; paresthesias |
| Respiratory: iatrogenic | Bag-valve-mask or ventilator overventilation | Low EtCO₂ on the monitor |
| Metabolic: acid loss | Vomiting, NG suction | Low Cl⁻ and K⁺ |
| Metabolic: kidney and volume | Loop or thiazide diuretics, mineralocorticoid excess, low K⁺ or Mg²⁺ | Low K⁺; hypertension if mineralocorticoid |
| Metabolic: alkali or posthypercapnic | Sodium bicarbonate, citrate in massive transfusion; chronic CO₂ retainer ventilated down fast | Alkalemia after treatment or intubation |
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? Arterial or venous? Air bubbles, delay or a line sample with flush can all move the result. If pH, PaCO₂ and HCO₃⁻ fail the [H⁺] check, repeat the sample.
- How sick is the patient? Check mental status, breathing rate and depth, EtCO₂, perfusion, ECG and K⁺. A tiring patient can show a normal-looking pH and still be minutes from arrest.
- Read the pH first. Under 7.35 is acidemia. Over 7.45 is alkalemia. The primary disorder is the one that pushes the pH in that direction.
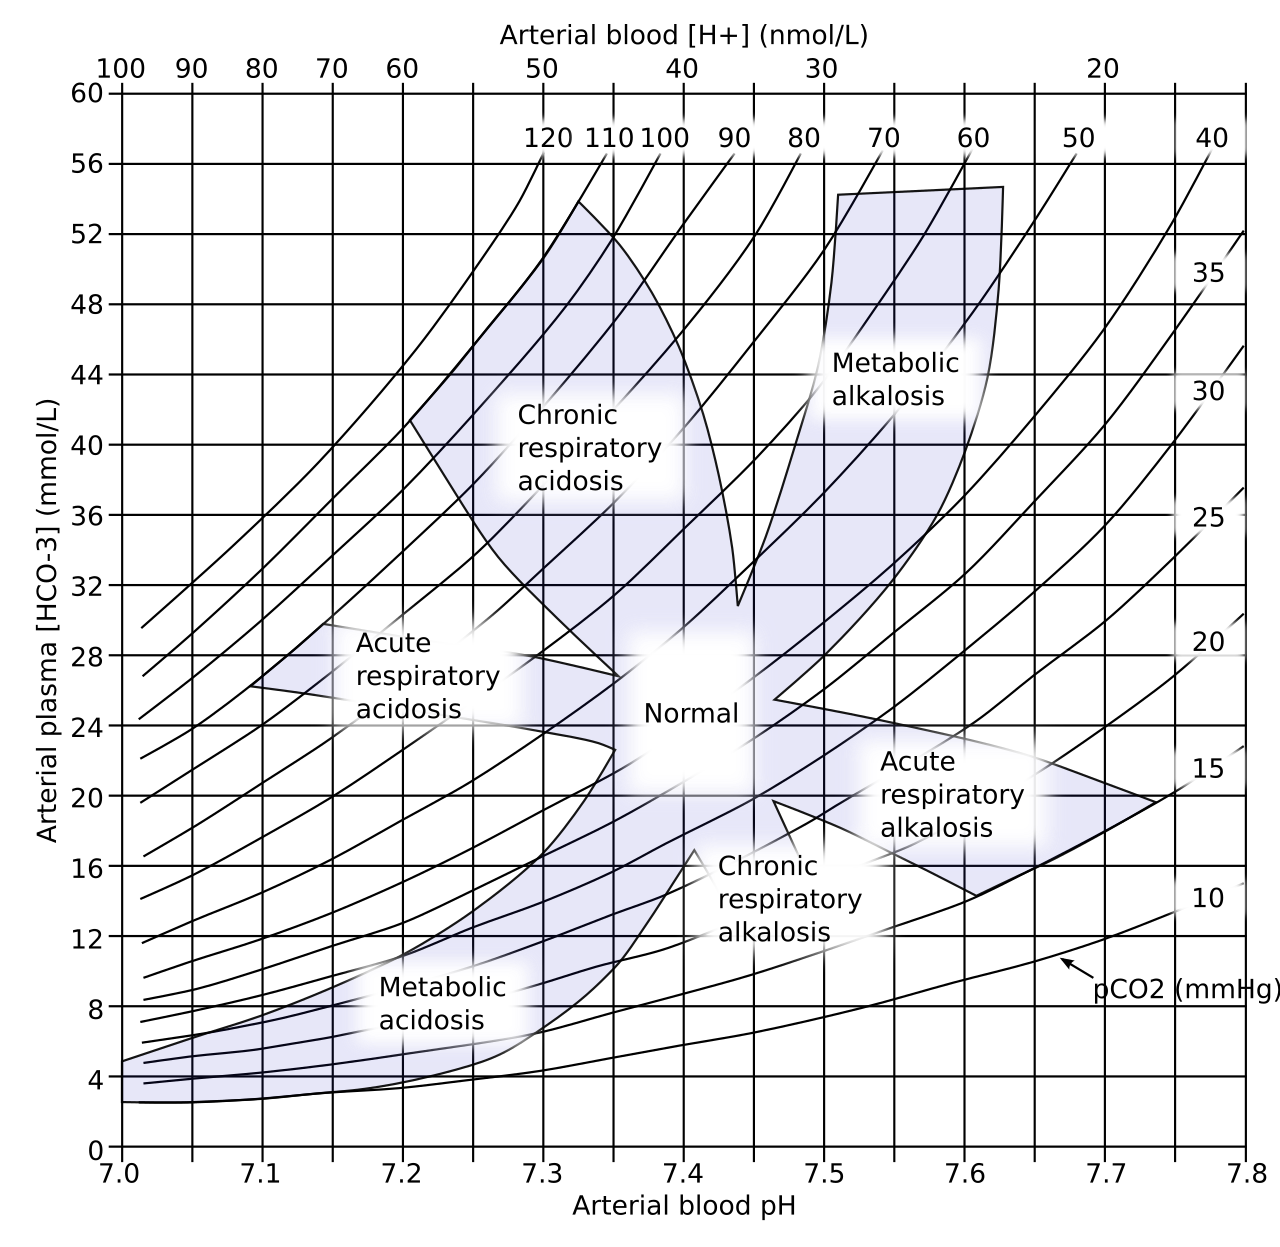
- Find the cause in PaCO₂ and HCO₃⁻. PaCO₂ moving opposite the pH points to respiratory. HCO₃⁻ moving with the pH points to metabolic. Acute or chronic? Compare with the patient's baseline. The trend tells you more than any single value.
- Check compensation and derived values. Use the table below. Compensation that falls short or overshoots means a second disorder. In any metabolic acidosis, calculate the albumin-corrected anion gap and delta gap.
- Name it and escalate. By the 2024 ADA/EASD/JBDS/AACE/DTS consensus, DKA is pH <7.30 and/or HCO₃⁻ <18 mEq/L with ketonemia. It is severe at pH <7.00. In a COPD exacerbation, the GOLD 2026 report treats PaCO₂ >45 mmHg with pH <7.35 as acute hypercapnic respiratory failure. Acidosis to pH ≤7.25 with PaCO₂ >60 mmHg or above baseline marks ventilatory failure (Rome classification).
Expected compensation
| Primary disorder | Primary change | Expected compensation |
|---|---|---|
| Metabolic acidosis | ↓ HCO₃⁻ | PaCO₂ = (1.5 × HCO₃⁻) + 8 ± 2 mmHg (Winter's formula) |
| Metabolic alkalosis | ↑ HCO₃⁻ | PaCO₂ rises 0.6–0.75 mmHg per 1 mEq/L rise; not above 55 mmHg from compensation alone |
| Respiratory acidosis, acute | ↑ PaCO₂ | HCO₃⁻ rises 1–2 mEq/L per 10 mmHg rise |
| Respiratory acidosis, chronic (3–5 days) | ↑ PaCO₂ | HCO₃⁻ rises 3–4 mEq/L per 10 mmHg rise |
| Respiratory alkalosis, acute | ↓ PaCO₂ | HCO₃⁻ falls 1–2 mEq/L per 10 mmHg fall |
| Respiratory alkalosis, chronic (2–3 days) | ↓ PaCO₂ | HCO₃⁻ falls 4–5 mEq/L per 10 mmHg fall |
Compensation brings the pH back toward normal, but only partway. It never overshoots.
Patterns
| Pattern | Suggests |
|---|---|
| pH low, PaCO₂ high, HCO₃⁻ normal or slightly high | Acute respiratory acidosis (opioids, tiring asthma) |
| pH low, HCO₃⁻ low, PaCO₂ low and within Winter's range | Compensated metabolic acidosis |
| pH low, HCO₃⁻ low, PaCO₂ normal or high | Metabolic plus respiratory acidosis: ventilation is failing |
| pH high, PaCO₂ low, HCO₃⁻ low | Respiratory alkalosis; HCO₃⁻ lower than predicted means an added metabolic acidosis (sepsis, salicylate) |
| pH near normal, PaCO₂ and HCO₃⁻ both abnormal | Mixed disorder until proven otherwise |
| pH, PaCO₂ and HCO₃⁻ normal, anion gap high | Hidden high-gap acidosis offset by metabolic alkalosis (DKA with vomiting) |
Management Priorities
Emergency: Severe acidemia (pH <7.20)
- Ventilation first if PaCO₂ is high: airway, bag-valve-mask, naloxone for opioid toxicity, and NIV for a COPD exacerbation (the initial mode for acute hypercapnic failure). Intubate if NIV fails or is contraindicated (Paramedic/RN/CCT, per local protocol).
- Protect compensation if PaCO₂ is low: Do not oversedate. If intubation is unavoidable, keep apnea as brief as you can and set a high minute ventilation right away, matched to the pre-intubation PaCO₂ or EtCO₂.
- Treat the cause: Restore perfusion and control the source in shock or sepsis. Give fluids, insulin and K⁺ for DKA. For toxic alcohols or salicylate, involve the poison center and plan for dialysis.
- Watch K⁺ and glucose: Get the ECG, K⁺ and glucose now, and keep checking them. Treat hyperkalemia directly. Do not wait for the pH to be corrected before you lower it.
- Bicarbonate only for a specific reason: the table lists the common indications, but it is not the full list. Sodium-channel-blocker toxicity with wide QRS or arrhythmia, and hyperkalemia with ECG changes, are also indications, per poison center and protocol. Do not use it to raise blood pressure in lactic acidosis, routinely in cardiac arrest, or (almost never) for respiratory acidosis. Salicylate toxicity calls for alkalinization under toxicology direction.
Emergency: Severe alkalemia (pH >7.60)
- Monitor: Put the patient on an ECG. Check K⁺, ionized Ca²⁺, Mg²⁺ and phosphate. Start seizure precautions.
- Respiratory cause: bring the bag or ventilator rate or tidal volume down toward the patient's baseline PaCO₂. Treat hypoxemia, pain and the cause (PE, sepsis, salicylate).
- Metabolic cause: Where possible, halt alkali, citrate and diuretics. For chloride-responsive alkalosis (vomiting, NG loss), give 0.9% saline with K⁺. Replace K⁺ and Mg²⁺.
- Refractory: ICU care only: acetazolamide, or dialysis. Dilute hydrochloric acid (0.1–0.2 N, 0.1–0.2 mmol/kg/h) is the last line. Pharmacy prepares it as an infusion for pH >7.6 when dialysis is not possible. It has to go through a central catheter, with frequent blood gas and electrolyte checks, per institutional protocol.
Medications
Doses vary by protocol; follow local protocols and medical direction.
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Sodium bicarbonate: septic shock with severe metabolic acidemia | pH ≤7.20 with AKI stage 2–3: IV infusion per ICU protocol, titrated to pH (titrate to effect: no fixed max) | Not routinely used (consult) | SSC 2021 suggests it here; recommends against it to improve hemodynamics in lactic acidosis. Ventilation must clear the extra CO₂; watch Na⁺, ionized Ca²⁺ |
| Sodium bicarbonate: DKA | pH <7.0 only, per DKA protocol (titrate to pH >7.0: no fixed max) | Not routinely used (consult) | Fluids and insulin clear DKA acidosis; bicarbonate adds hypokalemia risk and is linked to cerebral injury in children |
| Naloxone: opioid hypoventilation | 0.2–2 mg IV/IO/IM or 2–4 mg IN, every 2–3 min, titrated to breathing (no fixed max). In opioid-dependent patients give cautiously in small increments: abrupt full reversal can precipitate acute withdrawal | 0.01 mg/kg IV/IO initial dose (label), then 0.1 mg/kg for later doses if no response, every 2–3 min; protocol-dependent. Use the low end for opioid-dependent or chronically exposed children (risk of acute withdrawal and pulmonary edema). No fixed max in the label | IV onset within 2 min. Ventilate first; titrate to breathing, not alertness; may wear off before the opioid |
| Sodium bicarbonate: salicylate toxicity | Alkalinizing infusion per toxicology protocol (urine alkalinization, after volume and electrolyte correction) | Per toxicology protocol | Potassium chloride is added to support urinary alkalinization; keep K⁺ replete and watch for fluid overload. Avoid drugs that depress respiratory drive, which blunt the hyperventilation holding up the pH |
| Acetazolamide: metabolic alkalosis | 250–375 mg IV or PO once daily (label edema dose). Off-label for metabolic alkalosis; dose per ICU protocol | Not routinely used (consult) | Increases HCO₃⁻ excretion; for posthypercapnic alkalosis or when saline is unsuitable (volume overload). Raises urine K⁺ and phosphate losses: recheck them. Avoid with hypokalemia, hyponatremia, sulfonamide allergy or significant hepatic or renal failure. Correct K⁺ first |
Definitive care & disposition
- ICU: pH <7.20 or >7.60, rising PaCO₂ despite NIV, severe DKA (pH <7.00), any bicarbonate or acid infusion.
- Lung-protective ventilation (ARDSNet protocol): pH goal 7.30–7.45. If pH is 7.15–7.30, raise the rate (max 35/min). If pH is below 7.15, raise the rate to 35/min; if pH stays below 7.15, tidal volume may rise in 1 mL/kg steps until pH exceeds 7.15 (the plateau pressure target of 30 cm H₂O may then be exceeded). Above 7.45, lower the rate if possible.
- Dialysis: refractory acidemia, toxic alcohols, salicylate, or alkalosis with kidney failure and volume overload. Involve nephrology and toxicology early.
- Chronic CO₂ retainers: correct PaCO₂ slowly, over hours, toward the patient's baseline to avoid posthypercapnic alkalosis.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
Cartridge analyzers measure pH and PaCO₂, then calculate HCO₃⁻. Respect the cartridge temperature and hematocrit limits, and trend on one device. For pH, a venous gas will do in most patients who are not in shock. EtCO₂ on the waveform tracks ventilation. It says nothing direct about pH. Pair it with one blood gas, because the PaCO₂–EtCO₂ gap widens with shock, PE and lung disease.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Before departure | Timed pH, PaCO₂, HCO₃⁻, lactate, K⁺ and glucose with the ventilator settings and EtCO₂ at the time of the draw |
| Ventilator switch | Match the sending minute ventilation, especially in metabolic acidosis; recheck a gas after changes if a POC analyzer is carried |
| Running infusions | Insulin, bicarbonate and K⁺ change pH and K⁺ en route: confirm drug, concentration and rate |
| Altitude and flight | Hypoxemia at cabin altitude drives hyperventilation in spontaneously breathing patients; keep SpO₂ at target |
| Redirect | Toxic alcohol, salicylate or refractory acidemia: go to a center that can start hemodialysis |
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Transitional values after birth; use the lab's neonatal range | Interpret cord and first-day gases with neonatal norms, not adult cutoffs |
| Children & adolescents | Adult pH range. DKA per ISPAD 2022: venous pH <7.3; severe at pH <7.1 | Bicarbonate is avoided in pediatric DKA except in exceptional cases; see weight-based dosing |
| Pregnancy | Progesterone drives ventilation: PaCO₂ near 30 mmHg, lower HCO₃⁻, pH at the upper end of normal | A PaCO₂ of 40 mmHg is relatively high in late pregnancy and may signal tiring or ventilatory failure |
| Older adults | No clinically meaningful difference in pH | Review diuretics and other drugs that change acid–base status |
| Chronic CO₂ retainers | Baseline chronic respiratory acidosis with high HCO₃⁻ | Target the patient's baseline PaCO₂, not 40 mmHg |
| CKD / dialysis | Chronic metabolic acidosis is common as GFR falls | Compare with the patient's baseline; refractory acidemia in kidney failure needs dialysis |
| Hypothermia (including TTM) | Analyzer reports at 37 °C (98.6 °F); in-body pH is higher, about 0.015 per 1 °C below 37 °C | Most adult practice reads uncorrected values against 37 °C norms (alpha-stat); give the lab the patient's temperature |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Air bubbles | ↑ (usually slight) | CO₂ escapes into the bubble; PaCO₂ falls | Expel air at once, cap, mix gently |
| Delay at room temperature | ↓ | Cells keep producing CO₂ and acid | Plastic syringe: analyze within 30 min (15 min if PaO₂ matters) |
| Icing a plastic syringe | PaO₂ artifact | Plastic is gas-permeable when cold | Keep plastic at room temperature; ice only glass syringes for delays |
| Excess liquid heparin | PaCO₂ and HCO₃⁻ falsely ↓ | Dilution | Use dry-heparin blood-gas syringes; fill to the stated volume |
| Vigorous mixing | ↓ | Hemolysis | Roll and invert gently |
| Line sample with flush | Variable | Saline or drug contamination | Discard enough dead space before drawing |
Physiologic / patient factors
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Painful or anxious puncture | ↑ | Hyperventilation lowers PaCO₂ | Local anesthetic; calm the patient; note the breathing pattern |
| Venous sample read as arterial | ↓ (about 0.03) | Venous blood carries more CO₂ | Label the sample type; check PaO₂ and SaO₂ fit |
| Hypothermia | In-body pH higher than reported | Gas solubility changes with temperature | Report the temperature; follow local alpha-stat or pH-stat practice |
Assay & device-specific
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Calculated HCO₃⁻ | Inherits pH and PaCO₂ errors | Derived by the analyzer, not measured | Compare with serum total CO₂; trust measured if discordant |
| POC cartridge outside limits | Unreliable | Temperature or hematocrit outside the operating range | Follow the device limits; send to the lab |
Common misinterpretations
- "pH 7.37 is acidemia": 7.35–7.45 is normal. Read PaCO₂ and HCO₃⁻ before you name a disorder.
- "A normal pH means a normal acid–base state": Opposing disorders can cancel each other out. Check the components and the anion gap.
- "Compensation brought the pH to normal": It does not. A fully normal pH with abnormal components is a mixed disorder.
- "Fix the pH and the K⁺ will follow": The K⁺ shift that comes with pH correction is unpredictable. Treat a dangerous K⁺ directly.
Physiology & Test Basics
What it measures
Blood pH is the net acid–base result. It is the negative logarithm of the free hydrogen-ion concentration. PaCO₂ is the respiratory half, bicarbonate and base excess the metabolic ones. The scale is logarithmic, so a small change in pH is a large change in [H⁺].
Physiology & regulation
- Buffers: CO₂ + H₂O ⇌ H₂CO₃ ⇌ H⁺ + HCO₃⁻. Hemoglobin, protein and phosphate buffers also absorb acid, within seconds.
- Lungs: move PaCO₂ within minutes.
- Kidneys: Over days, they reclaim and regenerate HCO₃⁻ and excrete acid.
- Potassium: Acidemia tends to push K⁺ up. Alkalemia tends to push it down.
- Oxygen and calcium: Alkalemia shifts the oxyhemoglobin curve left, so less O₂ is released. It also lowers ionized Ca²⁺.
- Heart: Severe acidemia blunts contractility and the response to catecholamines.
How it is measured
- Specimen: whole blood in a pre-heparinized (dry heparin) blood-gas syringe; arterial (usually radial) or venous. Expel air, cap, mix gently, label the sample type, time, FiO₂ and temperature.
- Method: pH electrode at 37 °C on a laboratory or point-of-care blood-gas analyzer; results in minutes.
- Fasting: not required.
Why it matters
pH tells you how dangerous the problem is right now. Add PaCO₂ and HCO₃⁻, and you learn whether breathing or metabolism caused it. That answer decides whether you ventilate, resuscitate, give insulin or call for dialysis.
Clinical Pearls
References
- Cao, D., Arens, A. M., Chow, S. L., et al. (2025). Part 10: Adult and pediatric special circumstances of resuscitation: 2025 American Heart Association guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation, 152(16 suppl 2), S578–S672. https://doi.org/10.1161/CIR.0000000000001380
- Umpierrez, G. E., Davis, G. M., ElSayed, N. A., Fadini, G. P., Galindo, R. J., Hirsch, I. B., et al. (2024). Hyperglycemic crises in adults with diabetes: a consensus report. Diabetes Care, 47(8), 1257–1275. https://doi.org/10.2337/dci24-0032
- Glaser, N., Fritsch, M., Priyambada, L., Rewers, A., Cherubini, V., Estrada, S., Wolfsdorf, J. I., & Codner, E. (2022). ISPAD Clinical Practice Consensus Guidelines 2022: Diabetic ketoacidosis and hyperglycemic hyperosmolar state. Pediatric Diabetes, 23(7), 835–856. https://doi.org/10.1111/pedi.13406
- Evans, L., Rhodes, A., Alhazzani, W., Antonelli, M., Coopersmith, C. M., French, C., et al. (2021). Surviving Sepsis Campaign: international guidelines for management of sepsis and septic shock 2021. Intensive Care Medicine, 47(11), 1181–1247. https://doi.org/10.1007/s00134-021-06506-y
- Global Initiative for Chronic Obstructive Lung Disease. (2026). Global strategy for prevention, diagnosis and management of COPD: 2026 report. https://goldcopd.org/wp-content/uploads/2026/01/GOLD-REPORT-2026-v1.3-8Dec2025_WMV2.pdf
- Acute Respiratory Distress Syndrome Network. (2008). Ventilator protocol: lung-protective ventilation card (July 2008; accessed 2026-10-14). https://www.ardsnet.org/files/ventilator_protocol_2008-07.pdf
- International Medication Systems, Limited. (current label, accessed 2026-10-14). Naloxone hydrochloride injection, solution: prescribing information. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=236349ef-2cb5-47ca-a3a5-99534c3a4996
- Hikma Pharmaceuticals USA Inc. (current label, accessed 2026-10-14). Acetazolamide for injection: prescribing information. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=85975cf0-1286-4af9-ac7f-94bb2483bf09
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.