

Bedside Snapshot
- Normal (Adult)
- 150–400 ×10³/µL (150–400 ×10⁹/L); some labs use 450 as the upper limit. Thrombocytopenia <150; thrombocytosis above the lab upper limit (>400, or >450 where that is the limit)
- Critical Values
- <30 or >1,000 ×10³/µL (<30 or >1,000 ×10⁹/L); typical, lab-specific
- High Suggests
- Infection, inflammation, trauma or bleeding (reactive)
- Iron deficiency
- Splenectomy or asplenia
- Myeloproliferative neoplasm (clot risk)
- Low Suggests
- Consumption: DIC, TTP/HUS, HELLP, bleeding
- HIT or another drug
- ITP, sepsis, viral infection
- Marrow failure, chemotherapy, cirrhosis, dilution
- Act Now If
- <30 or >1,000 ×10³/µL, bleeding with <50, or a fall with schistocytes, clots or neuro signs: smear, PT/INR, fibrinogen; stop heparin if HIT is likely; notify hematology or medical control
- Watch Out For
- EDTA clumping gives a falsely low count. Check the smear or redraw in citrate before transfusing a well, non-bleeding patient
Reference & Critical Ranges
Reference ranges
| Population | Conventional | SI | Notes |
|---|---|---|---|
| Adults (men and women) | 150–400 ×10³/µL | 150–400 ×10⁹/L | Rosen's Emergency Medicine and Lewis's Medical-Surgical Nursing reference; some labs set the upper limit at 450. Thrombocytopenia is <150 |
| Pregnancy | Falls slightly toward term | — | Gestational thrombocytopenia is usually 100–149 and rarely falls below 70; a count below 100 or a falling count needs a cause (preeclampsia, HELLP, ITP, TTP) |
| Older adults | Adult range | Adult range | A new low count is not part of aging; review drugs and look for marrow disease |
| Neonates (0–28 days) | Use the NICU's interval (many references print 150–450 ×10³/µL) | — | No E3 textbook neonatal interval. Below 150 is thrombocytopenia at any age; common in sick and preterm neonates, so use NICU ranges for preterm infants |
| Infants, children and adolescents | Same as adult | Same as adult | Children: same as adult |
Severity & critical values
| Level | Conventional | SI | What it means / typical findings |
|---|---|---|---|
| Mild thrombocytopenia | 100–149 ×10³/µL | 100–149 ×10⁹/L | Usually no bleeding; find the cause and trend it |
| Moderate thrombocytopenia | 50–99 ×10³/µL | 50–99 ×10⁹/L | Easy bruising; at 50 or more, the count alone rarely explains bleeding |
| Severe thrombocytopenia | <50 ×10³/µL | <50 ×10⁹/L | Bleeding with surgery or trauma; spontaneous mucosal or intracranial bleeding risk rises sharply below about 10 (approximate; thresholds vary by source) |
| Thrombocytosis | >400 ×10³/µL (>450 where that is the lab limit) | >400 ×10⁹/L | Above the lab upper limit (400 on the Rosen's and Lewis range used here, 450 at many labs; Rosen's reserves the clinical term for counts above 600). Usually reactive; persistent and unexplained needs hematology (≥450 is the essential thrombocythemia criterion) |
| Extreme thrombocytosis | >1,000 ×10³/µL | >1,000 ×10⁹/L | Clot risk plus paradoxical bleeding from acquired von Willebrand syndrome |
| Critical | <30 or >1,000 ×10³/µL | <30 or >1,000 ×10⁹/L | Typical; lab-specific (some labs call at 20 or 40). Assess for bleeding or clotting and notify |
Conversion: Read ×10³/µL and ×10⁹/L as the same number. 150,000/µL is 150 ×10³/µL.
Causes of Abnormal Results
Low (thrombocytopenia <150 ×10³/µL; mild 100–149, moderate 50–99, severe <50)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Thrombotic microangiopathy | Thrombotic thrombocytopenic purpura (TTP), hemolytic uremic syndrome (HUS: Shiga toxin or complement-mediated), HELLP syndrome | Schistocytes, high LDH, low haptoglobin; neuro signs in TTP, AKI in HUS, hypertension and RUQ pain in HELLP; PT and fibrinogen near normal |
| Heparin-induced | Heparin-induced thrombocytopenia (HIT), including from flushes, locks, coated catheters and Impella purge | Fall >50% on day 5–10 of heparin; new venous or arterial clot; nadir usually ≥20 |
| Consumption with coagulopathy | Disseminated intravascular coagulation (DIC): sepsis, trauma, abruption, amniotic fluid embolism, acute promyelocytic leukemia; massive bleeding | Oozing lines, long PT, low fibrinogen, very high D-dimer |
| Immune destruction | Immune thrombocytopenia (ITP), primary or with HIV, HCV or lupus; drug-induced (quinine, trimethoprim-sulfamethoxazole, vancomycin, piperacillin, valproic acid, GP IIb/IIIa inhibitors); post-transfusion purpura | Isolated low count in a well-looking patient; petechiae, wet purpura; new drug; transfusion 7–10 days ago |
| Infection | Sepsis, dengue, malaria, HIV, HCV, EBV, CMV | Fever, travel history, rising lactate |
| Underproduction | Chemotherapy, leukemia, myelodysplasia, aplastic anemia, marrow infiltration, B12 or folate deficiency, alcohol, prolonged linezolid | Other cell lines low; blasts or macrocytes on smear |
| Sequestration | Cirrhosis with portal hypertension and splenomegaly (with low thrombopoietin); sickle cell splenic sequestration crisis | Stable moderate count, splenomegaly, stigmata of liver disease; sickle crisis: acute drop with an enlarging spleen, pain and anemia |
| Hypothermia | Cold exposure or resuscitation with hypothermia | Platelet sequestration and dysfunction; count falls as core temperature drops. Rewarm and recheck |
| Dilution and devices | Massive transfusion without platelets, large crystalloid volumes, ECMO, cardiopulmonary bypass, IABP or Impella | Count falls with resuscitation or circuit time; recheck after each product round |
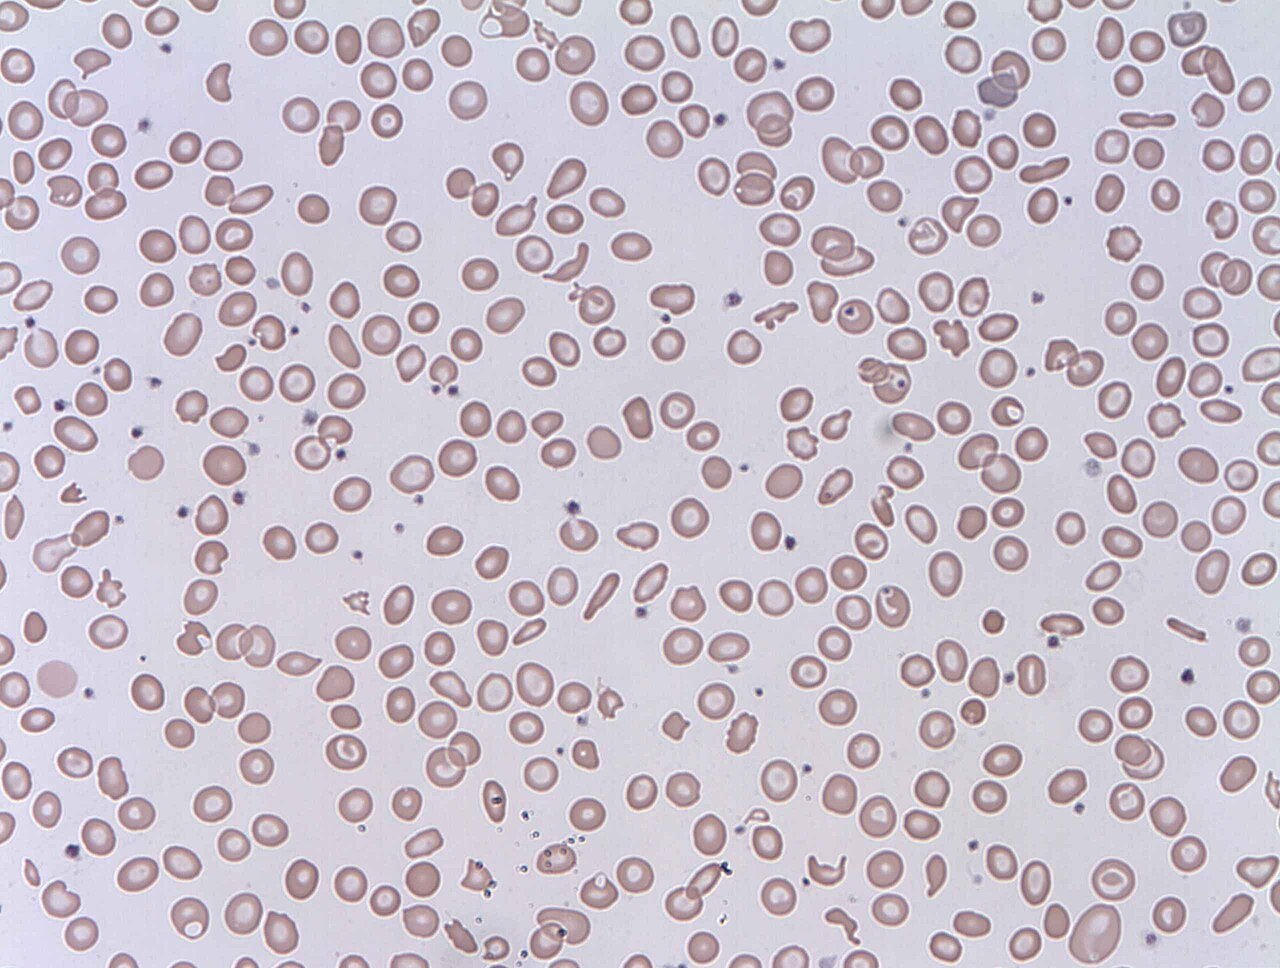
High (thrombocytosis >400 ×10³/µL, or above the lab upper limit; extreme >1,000)
| Mechanism | Common causes | Bedside clue |
|---|---|---|
| Reactive (most common) | Infection, inflammation, surgery, trauma, burns, acute bleeding, iron deficiency, cancer, transient exercise, drugs such as ATRA and G-CSF | Recent illness or injury, high CRP, low ferritin; falls as the cause resolves |
| Asplenia | Splenectomy or functional asplenia (sickle cell disease) | Surgical scar or history; Howell-Jolly bodies on smear; count peaks 7–21 days after splenectomy and is usually benign and self-limited |
| Rebound | Recovery after chemotherapy, marrow suppression or treated ITP | Count overshoots, then settles over weeks |
| Clonal (myeloproliferative neoplasm) | Essential thrombocythemia, polycythemia vera, chronic myeloid leukemia, myelodysplasia with thrombocytosis | Persistent with no cause, splenomegaly, arterial or venous clots, high Hb or WBC; JAK2, CALR or MPL mutation; hematology decides on aspirin or cytoreduction (hydroxyurea) |
Interpretation & Bedside Approach
Step-by-step approach
- Is it real? A low count in a well patient, with normal Hb and WBC, is EDTA clumping until the smear proves otherwise. Check the analyzer flags and the smear. Or redraw in a citrate (light-blue) tube.
- How sick is the patient? Bleeding and clots outrank the number. Look for wet purpura (mouth blisters), mucosal or urinary bleeding, retinal hemorrhage, neuro change, new clots, fever, pregnancy and antiplatelet or anticoagulant use.
- Acute or chronic, and what is the trend? Set it against the last count. A fall of more than 50% matters even when the count is still in range. HIT is defined by the fall, not the floor.
- Read the rest of the CBC and the smear. Low platelets alone point to immune, drug or HIT causes. Other low lines point to the marrow. Schistocytes point to microangiopathy. Blasts point to leukemia.
- Classify with named criteria. Use the 4Ts for HIT, per ASH 2018. Use the PLASMIC score with ADAMTS13 testing for TTP, per ISTH 2020. Use Mississippi classes for HELLP. For DIC, PT, fibrinogen and D-dimer.
- Escalate or dispose. Transfuse to the AABB 2025 threshold for this situation (see Management Priorities). Suspected TTP, HIT, new pancytopenia or extreme thrombocytosis all go to hematology the same day.
HIT: 4Ts score
| Category | 2 Points | 1 Point | 0 Points |
|---|---|---|---|
| Thrombocytopenia | Fall >50% and nadir ≥20 | Fall 30–50% or nadir 10–19 | Fall <30% or nadir <10 |
| Timing of fall | Day 5–10, or ≤1 day with heparin in past 30 days | Probably day 5–10, after day 10, or ≤1 day with heparin 30–100 days ago | Fall before day 4 with no recent heparin |
| Thrombosis | New proven clot, injection-site skin necrosis, or acute reaction after IV bolus | Progressive or recurrent clot, red skin lesions, or suspected clot | None |
| Other cause | None apparent | Possible | Definite |
Nadir in ×10³/µL. 0–3 low: HIT is very unlikely. Don't test. Keep the heparin and find the other cause. 4–5 intermediate or 6–8 high: Stop all heparin. Start a non-heparin anticoagulant and send a PF4/heparin immunoassay. If that is positive, send the functional assay.
TTP, HUS and other thrombotic microangiopathy red flags
| Pattern | Suggests | Next step |
|---|---|---|
| Low platelets + schistocytes, high LDH, low haptoglobin, normal PT and fibrinogen; confusion, headache or fever; creatinine <2 mg/dL | TTP | Draw ADAMTS13 before any plasma; hematology now for plasma exchange |
| Same hemolysis pattern with AKI, often a child after bloody diarrhea | Shiga toxin HUS (complement-mediated HUS if no diarrhea) | Stool Shiga toxin testing; nephrology; ADAMTS13 to exclude TTP |
| Low platelets with long PT, low fibrinogen, very high D-dimer, a trigger such as sepsis or trauma | DIC | Treat the trigger; see fibrinogen and D-dimer pages |
| Pregnancy ≥20 weeks or postpartum, hypertension, RUQ or epigastric pain, high AST and LDH | HELLP (or preeclampsia with severe features) | Obstetrics now; Mississippi class (below) |
Severe ADAMTS13 deficiency (<10%) is likely at these scores. 0–4 points: 0–4%. 5 points: 5–24%. 6–7 points: 62–82%. The score was validated in adults without pregnancy, cancer, sepsis or transplant.
HELLP: Mississippi classes (by platelet nadir)
| Class | Platelet nadir | Other criteria |
|---|---|---|
| Class 1 | ≤50 ×10³/µL | LDH ≥600 U/L and AST or ALT ≥70 U/L |
| Class 2 | >50–100 ×10³/µL | LDH ≥600 U/L and AST or ALT ≥70 U/L |
| Class 3 | >100–150 ×10³/µL | LDH ≥600 U/L and AST or ALT ≥40 U/L |
Management Priorities
Doses vary by protocol; follow local protocols and medical direction.
Emergency: Bleeding with thrombocytopenia
- Control bleeding: Apply pressure and go after the source. Stop antiplatelets and reverse anticoagulants. No IM injections.
- Transfuse to the target: In major bleeding, keep platelets ≥50 ×10³/µL. Multiple trauma, brain or eye injury, or spontaneous intracranial hemorrhage: aim for ≥100. Nonoperative intracranial hemorrhage with a count >100 (on or off antiplatelets): platelets are not recommended.
- Treat the cause: For ITP, give IVIG and IV corticosteroids alongside platelets. For DIC, treat the trigger and replace fibrinogen. In HIT or TTP, use platelets only for life-threatening bleeding. In trauma, give TXA per protocol.
- Monitor & repeat: Recheck the count 10–60 min after each dose, along with Hb, PT/INR and fibrinogen.
Emergency: Suspected TTP or HIT (low platelets with clots or schistocytes)
- TTP: draw first, then treat: Send ADAMTS13 activity before any plasma or blood product. Start therapeutic plasma exchange and corticosteroids now, without waiting for the result. Hematology may add caplacizumab and rituximab.
- HIT (4Ts ≥4): stop all heparin: That covers infusions, flushes, locks, heparin-coated catheters and heparinized Impella purge.
- Anticoagulate: Start a non-heparin anticoagulant (argatroban, bivalirudin, fondaparinux or a DOAC) at therapeutic intensity unless bleeding risk is high. Send the immunoassay and order a leg ultrasound. No warfarin until platelets recover to ≥150.
- Platelets: Avoid them in HIT and TTP unless bleeding is life-threatening or a high-risk procedure cannot wait.
Medications and blood products
| Drug | Adult dose | Pediatric dose (max) | Onset / key notes |
|---|---|---|---|
| Platelets (blood component) | 1 adult dose: 1 apheresis unit or a pool of about 6 whole-blood-derived units; expect a 1-hr rise of about 30–60 ×10³/µL | Under 50 kg: 5–10 mL/kg, or 1 whole-blood-derived unit per 10 kg if over 10 kg (rise about 50–100 ×10³/µL); max 1 adult dose | Immediate. Room temperature; finish within 4 hr; count 10–60 min after |
| IV immune globulin (IVIG) | ITP with serious bleeding or urgent rise: 1 g/kg IV once, may repeat next day (max 2 g/kg per course) | ITP with serious bleeding: 0.8–1 g/kg IV once (max 1 g/kg per dose) | Response in days (median about 2.5). Thrombosis, renal injury and hemolysis risks; give with corticosteroids |
| Dexamethasone or prednisone | ITP needing treatment: dexamethasone 40 mg PO/IV daily × 4 days, or prednisone 0.5–2 mg/kg/day PO (course ≤6 weeks including taper) | ITP needing treatment: prednisone 2–4 mg/kg/day PO for 5–7 days (max 120 mg/day) | Dexamethasone acts faster early. No IM corticosteroids in ITP |
| Argatroban | HIT: 2 mcg/kg/min IV continuous infusion, no bolus; moderate or severe hepatic impairment 0.5 mcg/kg/min; titrate to aPTT 1.5–3× baseline, not over 100 s (max 10 mcg/kg/min) | Not established in children; label modeling suggests starting 0.75 mcg/kg/min (0.2 with hepatic impairment); pediatric hematology only | High-alert Stop heparin and get a baseline aPTT first; check aPTT 2 hr after start and each change. Raises INR, so warfarin overlap needs adjusted targets |
Platelet transfusion thresholds (no active bleeding unless stated)
| Situation | Transfuse below (×10³/µL) | Basis |
|---|---|---|
| Chemotherapy or allogeneic stem cell transplant | 10 (autologous transplant or aplastic anemia: no routine prophylaxis) | AABB 2025 |
| Consumptive thrombocytopenia, adults | 10 | AABB 2025 |
| Consumptive thrombocytopenia, neonates | 25 | AABB 2025 |
| Central line at a compressible site (adults) | 10 | AABB 2025 |
| Lumbar puncture | 20 | AABB 2025 |
| Interventional radiology | 20 low-risk; 50 high-risk | AABB 2025 |
| Major non-neuraxial surgery | 50 | AABB 2025 |
| Neuraxial anesthesia in obstetrics | 70 (some policies 80) | Obstetric consensus; local policy |
| Neurosurgery or posterior-segment eye surgery | 100 | BSH 2016; older, low certainty; follow local protocol |
| Major bleeding; multiple trauma, brain or eye injury, intracranial hemorrhage | 50; 100 | BSH 2016; older, low certainty; follow local protocol |
| Nonoperative intracranial hemorrhage, count over 100 (on or off antiplatelets) | Do not transfuse (conditional recommendation, low certainty) | AABB 2025 |
| Dengue or cardiac surgery without thrombocytopenia, no major bleeding | Do not transfuse | AABB 2025 |
| HIT, TTP, ITP | Only for life-threatening bleeding (ITP also urgent procedures) | AABB Circular 2024; BSH 2016 |
Definitive care & disposition
- TTP: Get them to a center that can start plasma exchange today. Caplacizumab and rituximab are hematology's call.
- HIT: Anticoagulate at least until platelets recover, and for about 3 months if HIT caused a clot. Put the heparin allergy on the chart and the transfer paperwork.
- ITP: adults with a new diagnosis and a count <20 ×10³/µL are usually admitted. Children with no or mild bleeding take the outpatient route, with observation.
- HELLP: Send them to an obstetric unit to plan delivery, per obstetric protocol. Everything below depends on the protocol. Severe-range blood pressure (160 systolic or 110 diastolic or higher) needs urgent antihypertensive treatment per protocol. Magnesium sulfate for seizure prophylaxis goes per obstetric direction. Position them on the left side. Transport to a center with obstetric and NICU capability.
Doses are typical references. Follow local protocols, medical direction and institutional policy.
Field & Transport Considerations
Point-of-care testing
- Platelet count: Rarely available in the field. Some EDs and transport programs carry point-of-care CBC analyzers. Treat the bleeding on clinical grounds.
- Viscoelastic tests (TEG, ROTEM): Clot strength reflects platelets and fibrinogen together. The fibrinogen-specific channel pulls the two apart. Cut-offs depend on the device and the protocol.
Before and during interfacility transport
| Setting | Consideration |
|---|---|
| Handoff (Paramedic/RN/CCT) | Last count with time and trend, products given and times, heparin exposure and HIT status, antiplatelet or anticoagulant use, bleeding sites |
| Platelets en route | Room temperature: never in a cooler with red cells or plasma unless the blood bank issued cold-stored platelets; finish within 4 hr; standard blood set |
| Suspected or known HIT | No heparin flushes, locks or heparin-coated lines; tell the receiving team before a line or Impella purge is set up |
| Severe thrombocytopenia | Avoid IM injections and arterial sticks; longer pressure on punctures; pad rails and secure tubes |
| When to redirect | Suspected TTP: a center with plasma exchange; intracranial bleeding: neurosurgical center; HELLP: obstetric center |
Timing & Kinetics
| Parameter | Value | Clinical implication |
|---|---|---|
| Platelet lifespan | 7–10 days | Marrow failure lowers the count over days; consumption can drop it in hours |
| Transfused platelets | Survive 3–4 days; 1-hr count is the best check of the dose | Prophylactic doses may need repeating every 1–3 days |
| Post-transfusion count | 10–60 min after the dose, then 24 hr | Separates immune refractoriness (poor 1-hr rise) from consumption (poor 24-hr survival) |
| HIT | Fall starts day 5–10 of heparin; within 24 hr if heparin in the past 30 days; can begin after heparin stops | Time the fall against the first heparin dose, including flushes and bypass |
| Drug-induced immune thrombocytopenia | Usually 1–2 weeks after a new drug; within hours to a day on re-exposure | Ask about every new drug, quinine (including tonic water) and GP IIb/IIIa inhibitors |
| Post-transfusion purpura | 7–10 days after transfusion | Sudden severe drop in a previously pregnant or transfused patient; IVIG, not platelets |
| ITP treatment | IVIG: response in days (median about 2.5); dexamethasone: faster than prednisone in the first week | Platelet transfusion bridges life-threatening bleeding until these work |
| HELLP | About 70% before delivery, 30% after, usually within 48 hr of delivery | A normal antepartum count does not rule out postpartum HELLP |
Two checks, two answers. Over 7,500 at 10–60 min and over 4,500 at 24 hr is the target. A 1-hr CCI under 5,000 with antibody evidence suggests immune refractoriness. Good at 1 hr but poor at 24 hr? That points to fever, sepsis, DIC, splenomegaly or bleeding.
Special Populations
| Population | What changes | Clinical implication |
|---|---|---|
| Neonates & infants | Thrombocytopenia (<150) is common in sick and preterm neonates; consumption from sepsis or necrotizing enterocolitis | Transfuse a non-bleeding neonate with consumptive thrombocytopenia below 25 per AABB 2025; pediatric product volumes in mL/kg |
| Children & adolescents | ITP often follows a viral illness; Shiga toxin HUS follows bloody diarrhea | ITP with no or mild bleeding (skin only): observation, not drugs; HUS: watch urine output and creatinine |
| Pregnancy | Gestational thrombocytopenia: mild, late second or third trimester, resolves after delivery; HELLP, preeclampsia, TTP and ITP also occur | Count below 100, a falling count, hypertension or RUQ pain needs urgent evaluation; neuraxial anesthesia usually needs ≥70 |
| Older adults | More antiplatelet and anticoagulant use; myelodysplasia more common | A normal count does not mean normal function; a new low count needs drug review and a smear |
| CKD / dialysis | Uremic platelet dysfunction; heparin exposure with dialysis | Bleeding despite a normal count: dialysis, correct anemia, desmopressin per nephrology; consider HIT if counts fall on heparin |
| Liver disease | Splenic sequestration and low thrombopoietin | Chronic stable thrombocytopenia; follow the procedural threshold in your protocol |
| Other: dengue, ECMO and mechanical support | Dengue consumption; circuit consumption and frequent heparin exposure | Dengue without major bleeding: no platelets, a strong AABB 2025 recommendation; on ECMO or Impella, score the 4Ts for any unexplained fall |
Interfering Factors & Pitfalls
Collection & handling
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
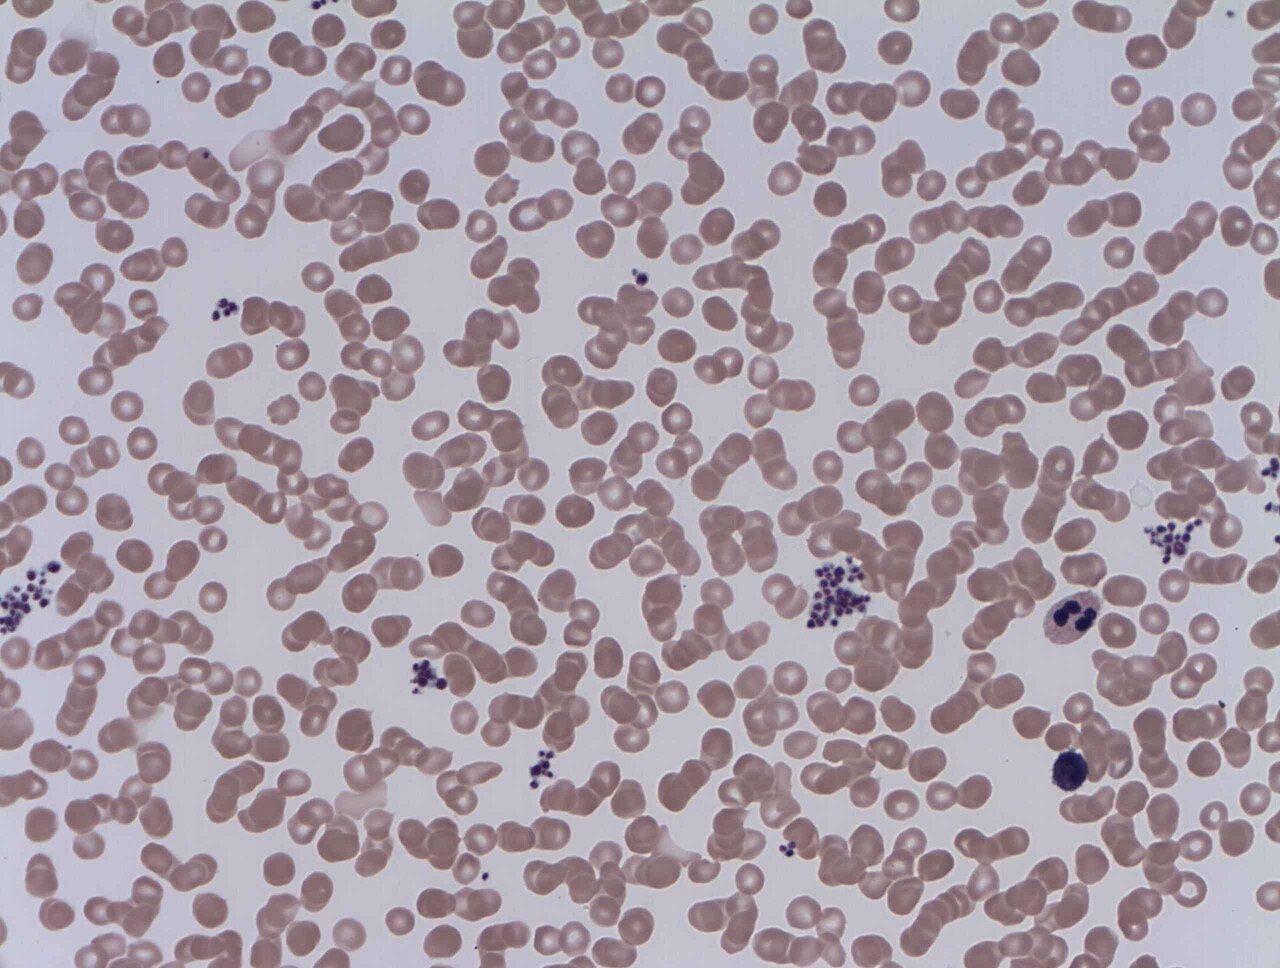
| EDTA-dependent clumping (pseudothrombocytopenia) | ↓ (False −) | Antibodies clump platelets in EDTA; clumps are not counted | Smear review; redraw in citrate (light-blue top) and let the lab correct for dilution |
| Platelet satellitism | ↓ (False −) | Platelets ring neutrophils in EDTA | Smear review; citrate redraw |
| Partially clotted sample | ↓ (False −) | Platelets trapped in the clot | Invert gently right after the draw; redraw |
| Delayed processing (over 4 hours at room temperature) | ↓ (False −) | Platelets degrade and clump over time | Analyze within 4 hours; redraw if the sample was delayed |
| Hemolysis | Variable | Interferes with optical platelet counting | Check analyzer flags and the smear |
Physiologic, assay & device-specific
| Factor | Effect | Why | Avoid / fix |
|---|---|---|---|
| Giant platelets (inherited macrothrombocytopenia, ITP) | ↓ (False −) | Impedance counters size them as red cells | Smear estimate or optical/immunologic count |
| Red cell fragments, microspherocytes, cryoglobulins, leukemic cell fragments | ↑ (False +) | Small particles counted as platelets | Smear review; can hide severe thrombocytopenia in TTP or burns |
| Antiplatelet drugs, uremia, cardiopulmonary bypass | Normal count, ↓ function | The count is not a function test | Treat bleeding by the clinical picture and viscoelastic testing |
| Thrombocytosis in a clotted (serum) sample | ↑ K⁺ (False +) | Platelets release potassium as the sample clots | Check plasma (heparin tube) potassium before treating |
Common misinterpretations
- “Low platelets, so bleeding risk”: In HIT, TTP and DIC the danger is clotting.
- “Normal count, so hemostasis is fine”: Aspirin, P2Y12 inhibitors, uremia and bypass all impair function, whatever the count.
- “Count still in range, so no HIT”: A 50% fall from 400 to 190 earns full points.
- “High platelets mean clot risk”: Reactive thrombocytosis rarely clots. Persistent clonal disease does.
Physiology & Test Basics
What it measures
The platelet count tells you how many platelets (thrombocytes) sit in each microliter of whole blood. Every CBC reports it. It measures quantity, not function. Normal numbers don't prove normal hemostasis. Analyzers also give mean platelet volume (MPV). Some add the immature platelet fraction, which reflects marrow output.
Physiology & regulation
- Production: Thrombopoietin drives it. The liver makes most of that hormone, and marrow megakaryocytes do the shedding.
- Lifespan: They last 7–10 days. Roughly a third are parked in the spleen at any moment, and that share climbs when the spleen is enlarged.
- Adhesion: Von Willebrand factor ties platelets to exposed collagen.
- Activation and aggregation: ADP and thromboxane A₂ recruit more platelets. Fibrinogen bridges GP IIb/IIIa receptors into a plug.
- Coagulation: The activated platelet surface is where thrombin gets made. Fibrin then locks the plug in place.
- Clearance: Aged platelets and antibody-coated platelets get pulled out by the spleen and liver. ITP works this way.
How it is measured
- Specimen: Lavender top (K₂EDTA) whole blood, mixed by gentle inversion. No fasting is needed. Use a light-blue top (3.2% sodium citrate) when you suspect EDTA clumping.
- Method: The analyzer counts by impedance or optics. Flagged results get checked on a stained peripheral smear.
- Turnaround: Minutes, along with the CBC. Some EDs and transport programs have point-of-care CBC analyzers.
Why it matters
The count drives transfusion and procedure decisions. A fall is often the first sign of HIT, TTP, DIC, HELLP or sepsis. Read it alongside its trend, the smear and the patient. That is how you split the bleeding problem from the clotting one.
Clinical Pearls
References
- Metcalf, R. A., Nahirniak, S., Guyatt, G., et al. (2025). Platelet transfusion: 2025 AABB and ICTMG international clinical practice guidelines. JAMA, 334(7), 606–617. https://doi.org/10.1001/jama.2025.7529
- Estcourt, L. J., Birchall, J., Allard, S., et al. (2017). Guidelines for the use of platelet transfusions (British Society for Haematology). British Journal of Haematology, 176(3), 365–394. https://doi.org/10.1111/bjh.14423
- AABB, American Red Cross, America’s Blood Centers, & Armed Services Blood Program. (2024). Circular of information for the use of human blood and blood components (June 2024). AABB. https://www.aabb.org/news-resources/resources/circular-of-information
- Cuker, A., Arepally, G. M., Chong, B. H., et al. (2018). American Society of Hematology 2018 guidelines for management of venous thromboembolism: Heparin-induced thrombocytopenia. Blood Advances, 2(22), 3360–3392. https://doi.org/10.1182/bloodadvances.2018024489
- Neunert, C., Terrell, D. R., Arnold, D. M., et al. (2019). American Society of Hematology 2019 guidelines for immune thrombocytopenia. Blood Advances, 3(23), 3829–3866. https://doi.org/10.1182/bloodadvances.2019000966
- Zheng, X. L., Vesely, S. K., Cataland, S. R., et al. (2020). ISTH guidelines for the diagnosis of thrombotic thrombocytopenic purpura. Journal of Thrombosis and Haemostasis, 18(10), 2486–2495. https://doi.org/10.1111/jth.15006
- Giannubilo, S. R., Marzioni, D., Tossetta, G., & Ciavattini, A. (2024). HELLP syndrome and differential diagnosis with other thrombotic microangiopathies in pregnancy. Diagnostics, 14(4), 352. https://doi.org/10.3390/diagnostics14040352
- Stavros, S., Kathopoulis, N., Gerede, A., et al. (2026). Thrombocytopenia in pregnancy: Clinical challenges, maternal-fetal risks, and management strategies. Life, 16(3), 462. https://doi.org/10.3390/life16030462
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.