

Bedside Snapshot
- Use It For
- Severe agitation (alone or with a benzodiazepine); hyperactive delirium with distress or danger; refractory nausea and vomiting, including cannabinoid hyperemesis (off-label)
- Adult Dose
- Agitation: 5–10 mg IM per NASEMSO 2022 guideline. Differs from FDA label: 2–5 mg IM, max 20 mg/day
- Delirium: 1–10 mg IM (UK label), max 10 mg/day; ICU ~2.5 mg IV off-label
- Nausea: 2–3 mg IV/IM; CHS: 0.05 mg/kg IV
- Pediatric Dose
- Age 6–12 yr: 1–3 mg IM, max 0.15 mg/kg per NASEMSO 2022 (limited data). Other ages: 2019 BETA consensus (off-label): 0.05–0.1 mg/kg PO or IM, max 5 mg/dose. Differs from FDA label: no pediatric injection dose
- Onset / Duration
- IM: 10–20 min per NASEMSO 2022; 30–60 min to calm per 2018 review / variable. IV (off-label): 5–10 min per NASEMSO 2022, or 10–15 min per IBCC. One or a few doses may wear off by redistribution; repeat doses accumulate
- Do Not Give / Hold If
- Coma or severe CNS depression; Parkinson's disease or Lewy body dementia; QTc >500 ms, long QT or prior torsades; uncorrected low K⁺ or Mg²⁺
- Watch For
- Torsades (QTc on ECG); acute dystonia incl. laryngeal (neck, eyes, jaw, stridor); akathisia mistaken for agitation; hypotension; NMS (fever, rigidity, CK)
- Reversal / Rescue
- Dystonia: diphenhydramine 25–50 mg or benztropine 1–2 mg IV/IM
- Torsades: IV magnesium; unsynchronized shock if pulseless or unstable
- Low BP: fluids, norepinephrine; epinephrine only for anaphylaxis or arrest
- Must Remember
- Lactate 5 mg/mL is the acute drug; decanoate is a 4-week depot: never give decanoate IV or for agitation. Any IV haloperidol needs continuous ECG monitoring
Indications
Emergency & Prehospital
- Severe agitation: use it when verbal de-escalation has failed and the patient, bystanders or staff are at risk. Effective alone or with lorazepam, but it is slower than droperidol or an atypical antipsychotic plus midazolam. IV use is off-label.
- Acute psychosis or mania with agitation: fast control when oral therapy is not appropriate. The US injection label covers schizophrenia.
ED / ICU / Transport
- Hyperactive delirium with distress or danger: short-term control of agitation, hallucinations or self-harm (pulling lines or tubes). Use it after the causes are treated and nonpharmacologic measures have failed (off-label in the US). Not for hypoactive delirium.
- Refractory nausea and vomiting: use it when first-line antiemetics have failed (off-label).
- Cannabinoid hyperemesis syndrome (CHS): it relieved nausea and abdominal pain better than ondansetron. Off-label.
- Postoperative nausea and vomiting (PONV): prophylaxis, or combination treatment, in moderate- to high-risk patients when other antiemetics fail. UK-labeled, off-label in the US.
Other Uses
- Schizophrenia and other psychotic disorders: oral and IM maintenance. Haloperidol decanoate is the 4-weekly depot.
- Tourette's disorder: oral haloperidol carries an FDA label for tics in children and adults.
- Huntington's disease chorea: IM, once other drugs have failed and oral therapy is not possible. UK-labeled.
Dosing & Administration
Doses vary by protocol; follow local protocols and medical direction. Unless a dose is marked (UK label or guideline), it follows the FDA label. Where a current guideline disagrees, its dose goes first, and the label value stays visible.
Available Forms
- Haloperidol lactate injection (immediate release): 5 mg/mL in a 1 mL (5 mg) single-dose vial or 10 mL (50 mg) multiple-dose vial. The label covers IM use only, so IV is off-label. This is the one EDs, ICUs and EMS agencies carry.
- Haloperidol decanoate (long-acting depot): 50 mg/mL and 100 mg/mL in sesame oil, deep IM every 4 weeks for schizophrenia maintenance. Never give it IV. Never use it for acute agitation.
- Oral: tablets 0.5, 1, 2, 5, 10 and 20 mg; oral concentrate 2 mg/mL (as lactate).
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| Severe agitation (adults under 65 yr) | 5–10 mg IM (NASEMSO 2022 guideline). Differs from FDA label: 2–5 mg IM. IBCC expert practice: 5–10 mg IV or IM for dangerous agitation in young, robust adults (IV is off-label) | US label: repeat as often as hourly (4–8 hr intervals often enough); UK label: most patients need up to 15 mg/day; max 20 mg/day (both labels). No response after about 10 mg cumulative: IBCC suggests changing agent rather than escalating (expert practice, not a label or guideline limit) | ACEP 2024: effective alone or with lorazepam, but droperidol or an atypical antipsychotic plus midazolam works faster; consider ketamine when safety is at immediate risk. IM onset 10–20 min per the NASEMSO 2022 guideline; 30–60 min to calm per a 2018 review. The same guideline also lists 5 mg IV (off-label; onset 5–10 min) |
| Hyperactive delirium with distress or danger | 1–10 mg IM (UK label): start at the lowest dose. ICU practice: about 2.5 mg IV (off-label) | Increase in steps at 2–4 hr intervals if agitation continues; max 10 mg/day (UK label) | Treat the cause first. Use for the shortest time and stop when distress resolves. Not for hypoactive delirium; SCCM 2025 makes no recommendation for or against antipsychotics to treat ICU delirium. |
| Older adults (65 yr and older) or frail | Start at half the lowest adult dose: 0.5 mg for delirium; about 1 mg IV for moderate agitation in an older ICU patient | Titrate slowly; max 5 mg/day (UK label); higher only after reassessment in patients who have tolerated it | FDA boxed warning: higher mortality in dementia-related psychosis. Contraindicated in Parkinson's disease and dementia with Lewy bodies |
| Refractory nausea and vomiting (off-label) | 2–3 mg IV or IM | One more dose after 20–30 min if needed. No labeled antiemetic maximum: reassess after 2 doses and change agent rather than escalate; count toward the 24-hr haloperidol total | Watch for akathisia and dystonia; check QTc when combining with ondansetron or droperidol |
| Cannabinoid hyperemesis syndrome (off-label) | 0.05 mg/kg IV | Single dose studied (0.05 or 0.1 mg/kg); both dystonia return visits occurred at 0.1 mg/kg | Superior to ondansetron 8 mg IV at 2 hr in the HaVOC trial (adults); also shortened ED stay |
| PONV prophylaxis or treatment | 1–2 mg IM at induction or 30 min before the end of anesthesia; 1–2 mg IM to treat | Max 2 mg/dose (UK label) | UK-labeled indication; off-label in the US. UK label advises ECG monitoring for up to 6 hr after a PONV dose |
Pediatric Dosing
Where does a pediatric dose come from? Three sources, in this order: AHA/AAP 2025 where it states a dose, then the NASEMSO National Model EMS Clinical Guidelines v3.0 (2022), then the US label. If none of them gives a dose, none is shown. A pediatric maximum never exceeds the adult maximum dose (NASEMSO Universal Care Guideline, p. 13). "Pediatric" here means up to 40 kg or 14 years, whichever comes first. Unless marked labeled, a pediatric dose is off-label.
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| Severe agitation, age 6–12 yr (off-label; NASEMSO 2022) | 1–3 mg IM (limited data; optimal dose not established). NASEMSO gives no dose for other ages | Max 0.15 mg/kg | Differs from FDA label: the label gives no pediatric injection dose. Other ages: see the BETA consensus row below. For severe agitation, pairing with lorazepam is preferred over a second antipsychotic dose in non-delirious youth. EPS risk rises above 3 mg/day, and IV dosing carries a very high EPS risk; diphenhydramine may be given with haloperidol when EPS is a concern (avoid diphenhydramine in delirium) |
| Severe agitation, all ages (off-label; 2019 BETA consensus) | 0.05–0.1 mg/kg PO or IM (usual 0.5–5 mg/dose); the consensus advises an IM dose about half the oral dose | Max 5 mg/dose; max 6 mg/day for 15–40 kg, 15 mg/day over 40 kg | 2019 pediatric BETA consensus (corrected dosing table). For severe agitation, pairing with lorazepam is preferred over a second antipsychotic dose in non-delirious youth. EPS risk rises above 3 mg/day, and IV dosing carries a very high EPS risk; diphenhydramine may be given with haloperidol when EPS is a concern (avoid diphenhydramine in delirium) |
| Psychosis, Tourette's, severe behavior disorders (oral, labeled, 3–12 yr, 15–40 kg) | Start 0.5 mg/day PO; increase by 0.5 mg every 5–7 days. Psychosis 0.05–0.15 mg/kg/day; Tourette's and non-psychotic behavior 0.05–0.075 mg/kg/day, divided 2–3 times daily | No established maximum; little added benefit for behavior above 6 mg/day | Chronic therapy, not acute care. Not intended for children under 3 yr (FDA tablet label) |
| Delirium, nausea, CHS | Not established in children | Not routinely used (consult pediatric critical care or toxicology) | Injection safety and effectiveness are not established in children (US label) or under 18 yr (UK label) |
Weight-based dose checks: pediatric weight-based dosing.
Preparation & Administration
- Check the product: confirm "haloperidol lactate 5 mg/mL" (immediate release) and not decanoate before drawing up. Inspect for particles and discoloration.
- IM: undiluted into a large muscle. That's the labeled route.
- IV (off-label): give only with continuous ECG monitoring for QTc prolongation and arrhythmias (US and UK labels). Torsades risk is highest at higher-than-recommended doses and with IV use.
- Before dosing when feasible: baseline ECG, and correct low K⁺ and Mg²⁺ (UK label). In dangerous agitation, the dose comes first. Get the ECG as soon as it is safe.
- Switch to oral: use the previous 24-hr parenteral total as the first estimate of the oral daily dose (US label; UK label: 1:1); first oral dose 12–24 hr after the last injection.
Contraindications & Precautions
Contraindications
- US label: severe toxic CNS depression or coma from any cause; hypersensitivity (anaphylaxis, angioedema reported); Parkinson's disease; dementia with Lewy bodies
- UK label adds (relative in US practice): known QTc prolongation or congenital long QT syndrome; history of ventricular arrhythmia or torsades de pointes; recent acute myocardial infarction; uncompensated heart failure; uncorrected hypokalemia; other QT-prolonging drugs; progressive supranuclear palsy
Precautions
- QTc risk factors: low K⁺, Mg²⁺ or Ca²⁺, bradycardia, structural heart disease, hypothyroidism, heavy alcohol use, CYP2D6 poor metabolizers taking a CYP3A4 inhibitor.
- Seizure risk: it lowers the seizure threshold. Use caution in epilepsy, brain injury and alcohol withdrawal.
- Prior neuroleptic malignant syndrome (NMS): recurrence has been reported on re-exposure.
- Cardiovascular disease and hypotension: transient hypotension or angina may occur.
- Thyrotoxicosis: severe neurotoxicity, with rigidity and inability to walk or talk, has been reported.
- Older adults, dementia, stroke risk: higher mortality, cerebrovascular events and falls.
Hold / Reassess If
- QTc >500 ms: stop haloperidol (UK label); any QTc prolongation: reduce the dose
- K⁺ or Mg²⁺ low: correct before the next dose
- Restlessness rising after a dose (akathisia): do not escalate the dose
- Fever, rigidity or autonomic instability: stop and evaluate for NMS
- Over-sedation or falling SpO₂ with benzodiazepines or opioids on board: support the airway, hold further doses
Adverse Effects & Toxicity
Common
- Extrapyramidal symptoms (EPS): about 51% vs 16% with placebo in oral trials (Fresenius label, Table 1: 284 haloperidol, 282 placebo); tremor 8%, hypertonia 7%, dystonia 7%
- Akathisia and hyperkinesia: hyperkinesia about 10%; akathisia is subjective. The patient feels a distressing restlessness.
- Somnolence: about 5%
- Constipation and dry mouth: about 4% and 2%
- Orthostatic hypotension and tachycardia
- Hyperprolactinemia: galactorrhea, amenorrhea, gynecomastia with ongoing use
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
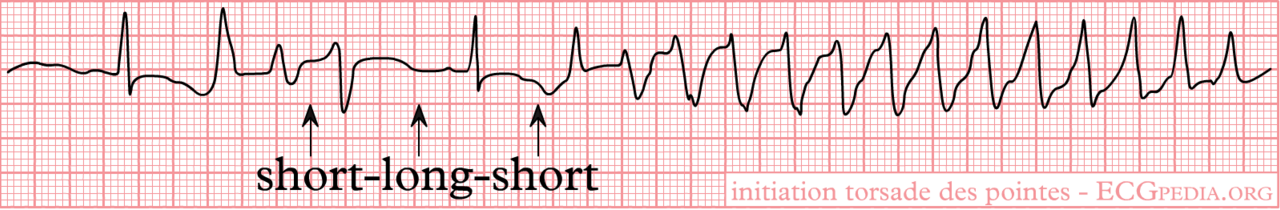
| QTc prolongation, torsades de pointes | QTc >500 ms, pauses, short-long-short onset of polymorphic VT, syncope, sudden death | Stop the drug; correct K⁺ and Mg²⁺; IV magnesium; defibrillate pulseless or unstable torsades |
| Acute dystonia | Torticollis, oculogyric crisis, trismus, tongue protrusion; laryngeal involvement causes stridor. Usually within the first few days; higher risk in young males | Diphenhydramine 25–50 mg IV/IM (child 1 mg/kg, max 50 mg) or benztropine 1–2 mg IV/IM (not under 3 yr); airway support if stridor |
| Akathisia | Inner restlessness, pacing, inability to sit still; easily mistaken for worsening agitation | Do not give more haloperidol; reassess and use an alternative agent |
| Neuroleptic malignant syndrome | Hyperthermia, lead-pipe rigidity, altered mental status, autonomic instability, high CK, myoglobinuria, renal failure. Hyperthermia and heat stroke without NMS are also reported | Stop all antipsychotics; active cooling, IV fluids, ICU care; no agreed drug regimen: discuss dantrolene or bromocriptine with toxicology |
| Tardive dyskinesia | Involuntary, repetitive movements of the tongue, lips, face, jaw or limbs; potentially irreversible | Risk rises with treatment duration and total cumulative dose but can follow brief, low-dose use: give the lowest effective dose for the shortest time and reassess if signs appear |
| Hypotension | Low or orthostatic BP, especially with volume depletion or other sedatives | IV fluids; if a vasopressor is needed use norepinephrine or phenylephrine; label says do not use epinephrine (paradoxical BP fall). This applies only to haloperidol-induced hypotension: never withhold epinephrine for anaphylaxis or cardiac arrest |
| Seizures, hypersensitivity, neutropenia | New seizure; urticaria, angioedema, laryngeal edema; fever with low white count | Treat seizures per protocol; anaphylaxis per protocol; stop if neutrophils <1,000/mm³ |
Overdose & Toxicity Management
- Signs: severe EPS (rigidity, tremor), hypotension, sedation progressing to coma with respiratory depression and shock; QTc prolongation and torsades. Hypertension has been reported in a 2-year-old.
- Immediate management: airway and ventilation; IV fluids, then norepinephrine or phenylephrine for hypotension (no epinephrine); anticholinergic for severe EPS; continuous ECG until it normalizes.
- Antidote: none specific. Treat torsades with magnesium and defibrillation; call Poison Control (1-800-222-1222).
- Extracorporeal removal: dialysis is not recommended. It removes very little haloperidol.
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: ECG and QTc | Baseline before dosing when feasible; continuous with IV dosing or repeated IM doses; up to 6 hr after a PONV dose | QTc prolonged: reduce the dose. QTc >500 ms: stop (UK label). Torsades: magnesium, defibrillate if pulseless. See QT interval |
| Clinical: sedation and airway | Continuously after parenteral doses, especially with benzodiazepines, opioids or alcohol | Falling SpO₂, slow RR or rising EtCO₂: stimulate, support the airway, hold further sedatives |
| Clinical: BP and HR | Frequently after each parenteral dose; check for orthostasis before mobilizing | Hypotension: IV fluids; vasopressor norepinephrine or phenylephrine, not epinephrine |
| Clinical: EPS | After every dose and for several days (dystonia usually in the first few days) | Dystonia: diphenhydramine or benztropine. Akathisia: stop escalating, change agent |
| Clinical: temperature and muscle tone | Every set of vitals; any patient on repeated doses or several antipsychotics | Fever with rigidity or altered mental status: stop and evaluate for NMS (CK, myoglobin, creatinine) |
| Clinical: delirium and agitation scores | Every shift (for example CAM-ICU and RASS in ICU) | Distress resolved: stop haloperidol; hypoactive delirium: do not give |
| Laboratory: K⁺ and Mg²⁺ | Baseline and periodically during repeated dosing | Low K⁺ or Mg²⁺: correct before further doses |
| Laboratory: CBC | History of low white count or drug-induced neutropenia | Neutrophils <1,000/mm³: stop haloperidol and follow until recovery |
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| QT-prolonging drugs (droperidol, ondansetron, amiodarone, procainamide, sotalol, methadone, citalopram, erythromycin, levofloxacin, ziprasidone) | Additive QTc prolongation and torsades | Avoid combinations in high-risk patients (UK label contraindicates); if needed, ECG and continuous monitoring |
| CNS depressants (benzodiazepines, opioids, alcohol, anesthetics) | Additive sedation and respiratory depression | Continuous SpO₂ and EtCO₂; lower doses of the second agent |
| CYP3A4 or CYP2D6 inhibitors (ketoconazole, itraconazole, ritonavir, fluoxetine, paroxetine, sertraline, quinidine, promethazine, chlorpromazine) | Higher haloperidol levels; QTc rise seen with ketoconazole plus paroxetine | Lower doses; monitor ECG and EPS |
| CYP3A4 inducers (carbamazepine, phenytoin, phenobarbital, rifampin, St John's wort) | Lower levels (rifampin: mean 70% drop); levels rise again after the inducer stops | Expect less effect; reduce dose after the inducer is stopped |
| Lithium | Rare encephalopathic syndrome (fever, confusion, EPS) with irreversible brain damage reported | Monitor for neurotoxicity; stop promptly if it appears; check a lithium level |
| Levodopa and dopamine agonists | Mutual antagonism; worse parkinsonism | Avoid haloperidol in Parkinson's disease (contraindicated) |
| Epinephrine | Vasopressor effect blocked; paradoxical further BP fall | For haloperidol-related hypotension use norepinephrine or phenylephrine |
| Diuretics and corticosteroids | Low K⁺, Mg²⁺ or Ca²⁺ raises torsades risk | Check and correct electrolytes |
IV Compatibility
- Labeling: US and UK haloperidol lactate products are labeled for IM use. Their labels give no IV diluent or Y-site data.
- Practice: flush the line before and after an IV push; do not mix in a syringe or line with other drugs unless your compatibility reference confirms it.
- Decanoate: it is an oil-based depot. Never IV.
- Verify with an institutional compatibility resource.
Special Populations
- Pediatrics: Injection safety and effectiveness in children are not established (US and UK labels). Oral haloperidol is labeled from age 3 yr. Younger patients get acute dystonia more often. EPS risk climbs above 3 mg/day, and IV dosing carries a very high EPS risk. Agitation dosing lives in the Pediatric Dosing table (NASEMSO 2022: 1–3 mg IM, age 6–12 yr; the 2019 BETA consensus differs). See also weight-based dosing.
- Neonates: Not used. Third-trimester exposure can cause neonatal EPS or withdrawal. Watch for agitation, abnormal tone, tremor, respiratory distress and feeding problems. Tell the neonatal team.
- Pregnancy: There are no well-controlled human studies. Still, more than 400 exposed pregnancies show no malformative or fetal/neonatal toxicity signal (UK label). Limb malformations were reported with first-trimester use, alongside other possibly teratogenic drugs, and no cause was proven. Animal studies: resorption and pup mortality, but no malformations in rats or rabbits. Cleft palate appeared in mice at about 0.1 times the maximum human dose (US label). The UK label advises avoiding use in pregnancy as a precaution. The US label advises use only when the benefit justifies the potential risk, such as dangerous agitation.
- Lactation: It passes into breast milk. The US label advises against breastfeeding during treatment. For a short exposure, talk it through with a pharmacist or lactation resource.
- Older Adults: The boxed warning for dementia-related psychosis applies here. Start at half the lowest adult dose. The UK label caps the dose at 5 mg/day. Tardive dyskinesia, falls and stroke all occur at higher rates. The AGS Beers Criteria list antipsychotics as potentially inappropriate in older adults.
- Renal Impairment: No dose adjustment is recommended, but use caution (UK label). Less than 3% is excreted unchanged. In severe impairment, consider a lower initial dose, then titrate to response, because haloperidol and its reduced metabolite have long half-lives and may accumulate (UK label). Dialysis does not remove it.
- Hepatic Impairment: The liver does most of the clearing, so halve the initial dose and titrate to response (UK label).
- Obesity / Dosing Weight: Adult doses don't scale with weight. The drug is lipophilic and spreads widely, with a volume of distribution of 8–21 L/kg. Pediatric per-kg doses stop at the adult-range caps.
- Parkinson's Disease, Lewy Body Dementia, Progressive Supranuclear Palsy: Expect severe EPS, confusion and falls. Contraindicated (PSP: UK label only). Pick a strategy that doesn't block dopamine.
- CYP2D6 Poor Metabolizers: Levels run higher. Use caution, especially with a CYP3A4 inhibitor.
Field & Transport Considerations
- Scope: Carried by paramedic, RN and critical-care transport teams where it is stocked, for behavioral emergencies (Paramedic/RN/CCT). It varies by state and agency protocol. ACEP 2024 makes no recommendation for or against specific agents out of hospital.
- Storage & Stability: 20–25°C (68–77°F); protect from light; do not freeze. Keep vials in the carton. Don't leave them where the vehicle heats up or chills down.
- Carried Concentration: haloperidol lactate 5 mg/mL (5 mg = 1 mL). Decanoate vials (50 or 100 mg/mL) look similar on a shelf, but they are a depot product. Read the label aloud before drawing up.
- Monitoring After Chemical Sedation: continuous SpO₂, cardiac monitor and EtCO₂ when combined with a benzodiazepine; reassess vital signs, airway and tone often. Check glucose and look for hypoxia, head injury, intoxication or withdrawal.
- Interfacility Transport: confirm the 24-hr total haloperidol dose, latest QTc and electrolytes, and any other QT-prolonging drugs before departure; bring diphenhydramine for dystonia.
- Handoff Essentials: time, dose and route of each dose (mg), total mg in 24 hr, other sedatives given, response, restraint use, ECG or QTc, EPS signs and temperature.
Clinical Pearls
- Dystonia: minutes to days after a dose, alert, afebrile, sustained spasm (neck, eyes, jaw). It resolves with an anticholinergic.
- NMS: develops over days, fever, lead-pipe rigidity, confusion, unstable vital signs, high CK. Stop the drug and cool.
Pharmacology
Mechanism of Action
- It blocks central dopamine D₂ receptors (mesolimbic). The result is less psychosis and agitation.
- Blocking D₂ in the nigrostriatal pathway causes EPS (dystonia, akathisia, parkinsonism). With long use, it leads to tardive dyskinesia.
- Blocking D₂ in the chemoreceptor trigger zone gives the antiemetic effect. Blocking it in the pituitary causes hyperprolactinemia.
- Weaker α₁-adrenergic binding causes orthostatic hypotension. Minimal muscarinic and H₁ binding means little anticholinergic effect.
- QTc prolongation rises with dose and concentration, and torsades risk is highest with IV and high doses.
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| IV (off-label) | 5–10 min per NASEMSO 2022; 10–15 min per IBCC (both off-label) | — | Variable: one or a few doses may wear off as drug redistributes into tissue |
| IM (lactate) | 10–20 min per NASEMSO 2022 guideline; 30–60 min to calm per a 2018 review | Plasma 20–40 min | Variable; repeated doses accumulate |
| PO | — | Peak effect about 2 hr | — |
| IM (decanoate depot) | Gradual (days) | Plasma about 6 days | Dosed every 4 weeks |
- Half-life: on average 21 hr (range 13–36 hr) after IM dosing. It runs longer in older adults. Decanoate: about 3 weeks.
- Metabolism: the liver breaks it down along several routes: glucuronidation, ketone reduction (to reduced haloperidol, which may convert back) and CYP3A4 and CYP2D6 oxidation. Haloperidol inhibits CYP2D6.
- Elimination: about 33% in urine and 21% in feces after IV dosing; less than 3% unchanged in urine.
- Absorption and distribution: IM absorption is complete. Oral bioavailability is 40–75% (first-pass). Protein binding is 88–92%, and volume of distribution is 8–21 L/kg. It crosses the blood-brain barrier and the placenta.
Names & Classification
- Generic Name
- Haloperidol (tablets); haloperidol lactate (immediate-release injection, oral concentrate); haloperidol decanoate (depot injection)
- Brand Names
- Haldol (historical brand; current US injectable and oral products, including the decanoate, are marketed generically)
- Pharmacologic Class
- Butyrophenone; dopamine D₂ receptor antagonist
- Therapeutic Class
- First-generation (typical) antipsychotic; antiemetic (off-label)
- Controlled Substance
- Not controlled
- ISMP High-Alert
- No
- Look-Alike / Sound-Alike
- None on the ISMP confused-names list. Product mix-up risk: haloperidol lactate (immediate release, 5 mg/mL) vs haloperidol decanoate (depot, 50 or 100 mg/mL)
References
- Fresenius Kabi USA. (2026). Haloperidol injection, USP (haloperidol lactate) 5 mg/mL [prescribing information] (revised June 2026). DailyMed, National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=b1ad2abd-a9d6-44e3-957b-36a73260f4f5
- Mercury Pharmaceuticals Ltd (ADVANZ Pharma). (2024). Haloperidol 5 mg/ml solution for injection: summary of product characteristics (text revised 16 April 2024). Electronic Medicines Compendium. https://www.medicines.org.uk/emc/product/514/smpc
- Thiessen, M. E. W., Godwin, S. A., Hatten, B. W., Whittle, J. A., Haukoos, J. S., Diercks, D. B., et al. (2024). Clinical policy: critical issues in the evaluation and management of adult out-of-hospital or emergency department patients presenting with severe agitation. Annals of Emergency Medicine, 83(1), e1–e30. https://doi.org/10.1016/j.annemergmed.2023.09.010
- Lewis, K., Balas, M. C., Stollings, J. L., McNett, M., Girard, T. D., Chanques, G., et al. (2025). A focused update to the clinical practice guidelines for the prevention and management of pain, anxiety, agitation/sedation, delirium, immobility, and sleep disruption in adult patients in the ICU. Critical Care Medicine, 53(3), e711–e727. https://doi.org/10.1097/CCM.0000000000006574
- Gerson, R., Malas, N., Feuer, V., Silver, G. H., Prasad, R., & Mroczkowski, M. M. (2019). Best practices for evaluation and treatment of agitated children and adolescents (BETA) in the emergency department: consensus statement of the American Association for Emergency Psychiatry. Western Journal of Emergency Medicine, 20(2), 409–418 (haloperidol dose corrected in erratum, 20(4), 688–689). https://doi.org/10.5811/westjem.2019.1.41344
- Ruberto, A. J., Sivilotti, M. L. A., Forrester, S., Hall, A. K., Crawford, F. M., & Day, A. G. (2021). Intravenous haloperidol versus ondansetron for cannabis hyperemesis syndrome (HaVOC): a randomized, controlled trial. Annals of Emergency Medicine, 77(6), 613–619. https://doi.org/10.1016/j.annemergmed.2020.08.021
- Zun, L. S. (2018). Evidence-based review of pharmacotherapy for acute agitation. Part 1: onset of efficacy. Journal of Emergency Medicine, 54(3), 364–374. https://doi.org/10.1016/j.jemermed.2017.10.011
- Farkas, J. (2022, July 18). Antipsychotic pharmacology. Internet Book of Critical Care (IBCC), EMCrit Project. https://emcrit.org/ibcc/delirium/
- Mylan Pharmaceuticals Inc. (2025). Haloperidol tablets, USP 0.5, 1, 2, 5, 10 and 20 mg [prescribing information] (revised January 2025). DailyMed, National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=c559b0b0-4087-d12a-e718-c18ccb6811e6
- National Association of State EMS Officials. (2022). National Model EMS Clinical Guidelines, Version 3.0 (rev. March 2022). Agitated or Violent Patient/Behavioral Emergency guideline, p. 61 (adult and pediatric haloperidol dosing and onset); Universal Care Guideline, p. 13 (pediatric dose caps). https://nasemso.org/docs.ashx?id=1444322
- American Geriatrics Society. (2023). American Geriatrics Society 2023 updated AGS Beers Criteria® for potentially inappropriate medication use in older adults. Journal of the American Geriatrics Society, 71(7), 2052–2081. https://doi.org/10.1111/jgs.18372
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.