

Bedside Snapshot
- Use It For
- Symptomatic bradycardia or AV block refractory to atropine (bridge to pacing); recurrent pause-dependent torsades despite magnesium; Brugada or idiopathic VF storm (specialist)
- Adult Dose
- Bradycardia: 1–20 mcg/min IV infusion, titrated to heart rate
- Bolus option: 20–60 mcg IV, then 10–20 mcg
- Torsades or VF storm: 0.5–10 mcg/min IV
- Pediatric Dose
- Not established in children: specialist use only. Start 0.1 mcg/kg/min IV infusion, usual 0.1–1 mcg/kg/min. PALS bradycardia uses CPR, epinephrine, atropine and pacing; no isoproterenol
- Onset / Duration
- IV infusion or bolus: immediate / brief; effect fades within minutes of stopping
- Do Not Give / Hold If
- Tachyarrhythmia or ventricular arrhythmia (except specialist torsades or VF-storm use); angina or ACS; congenital long QT; digoxin-toxic rhythm. Heart rate above goal or >130/min, new VT or chest pain: reduce or stop
- Watch For
- Ventricular arrhythmias (monitor, PVCs); ischemia (chest pain, ST change); hypotension from vasodilation (falling diastolic and MAP); pulmonary edema (SpO₂, crackles)
- Reversal / Rescue
- No antidote: half-life about 2 min, so reduce or stop. Arrhythmia: ACLS. No rate response: transcutaneous or transvenous pacing
- Must Remember
- Adults: mcg/min, not mcg/kg/min. A unit mix-up is a 70-fold error in a 70 kg adult. It is a bridge: pads on and pacing arranged before you start
Indications
ED / ICU / Transport
- Symptomatic bradycardia or AV block refractory to atropine: sinus node dysfunction or second- or third-degree AV block with hypotension or poor perfusion. Use it in patients at low likelihood of coronary ischemia. It is a bridge to transcutaneous or transvenous pacing. That use is off-label under current PLR-format labels. Some older-format labels, including Hospira's Isuprel, still list heart block and Adams-Stokes attacks.
- Recurrent pause-dependent torsades de pointes: acquired long QT with bradycardia or pauses, recurring despite IV magnesium. The drug raises the rate and shortens the QT. Use it with expert input, as an alternative or bridge to overdrive pacing (off-label).
- Electrical storm in Brugada syndrome, idiopathic VF or early repolarization syndrome: Specialists direct this. The goal is suppressing recurrent VF (off-label).
- Shock with low cardiac output or distributive shock: The FDA label covers improving hemodynamics. Few clinicians reach for it now, because it lowers diastolic and mean pressure.
- Bronchospasm during anesthesia: The FDA label covers an IV bolus.
Other Uses
- Beta-blocker overdose with refractory bradycardia: Adjunct only, with toxicology input. The 2025 AHA Guidelines for CPR and ECC, Part 10, lists vasopressors (COR 1) and high-dose insulin for hypotension refractory to vasopressors (COR 1). Glucagon is COR 2a. VA-ECMO for cardiogenic shock refractory to drugs is COR 2a. Calcium is COR 2b. Lipid emulsion has uncertain usefulness (COR 2b) (off-label).
- Electrophysiology (EP) lab and diagnostic testing: Used for provoking arrhythmias during an EP study and for testing the level of AV block. Follow the lab's own protocol (off-label).
Not a vasopressor: Isoproterenol has almost no α activity. Rate and output go up. Vessels dilate, though, so diastolic and mean pressure usually drop. It won't treat vasodilatory hypotension, and it has no role during CPR.
Dosing & Administration
Doses vary by protocol; follow local protocols and medical direction.
Available Forms
- Injection: 0.2 mg/mL (200 mcg/mL) in 1 mL (0.2 mg) and 5 mL (1 mg) single-dose vials or ampuls (Isuprel and generics). Must be diluted before use. Some products contain sodium metabisulfite
High-Alert Medication: Adult doses run in mcg/min and pediatric doses in mcg/kg/min. Mix those up and a 70 kg adult gets a 70-fold error. Concentrations vary too. The label notes that mixes up to 10 times the standard strength have been used when volume must be limited. Check the dose units, concentration and pump rate independently at start, at every bag change and at handoff.
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| Symptomatic bradycardia or AV block (atropine-refractory) | Infusion 1–20 mcg/min IV, titrated to heart rate response | Max 20 mcg/min (guideline range) | High-alert Caution if coronary ischemia is possible (see Clinical Pearls). Pads on; arrange pacing |
| Bradycardia: bolus option | 20–60 mcg IV bolus (1–3 mL of a 20 mcg/mL dilution), then 10–20 mcg IV boluses | No fixed max: titrate to heart rate, or start an infusion | High-alert Guideline alternative to starting an infusion |
| Recurrent pause-dependent torsades; Brugada or idiopathic VF storm | Infusion 0.5–10 mcg/min IV, titrated to the heart rate that suppresses recurrences | Usual max 10 mcg/min per the 2022 ESC guideline | High-alert After magnesium (2025 AHA Part 9, COR 2b) and defibrillation as needed; expert consultation. Not for congenital long QT |
| Shock (low output or distributive; labeled) | Infusion 0.5–5 mcg/min IV; start at the lowest dose | Rates above 30 mcg/min have been used in advanced shock (label) | High-alert Correct volume first. Label: consider reducing or stopping if heart rate exceeds 110/min |
| Bronchospasm during anesthesia (labeled) | 10–20 mcg IV bolus (0.5–1 mL of a 20 mcg/mL dilution) | Repeat as needed; no fixed max | High-alert Anesthesia setting; titrate to bronchospasm and heart rate |
| Beta-blocker overdose (adjunct) | Infusion IV, titrated to heart rate and blood pressure | No fixed max: toxicology-directed | High-alert Response is blunted. Per the 2025 AHA Part 10: vasopressors (COR 1) and high-dose insulin for vasopressor-refractory hypotension (COR 1); glucagon (COR 2a); VA-ECMO for refractory cardiogenic shock (COR 2a); calcium (COR 2b); lipid emulsion, usefulness uncertain (COR 2b) |
Dosing weight: Adult doses don't use weight. They're written in mcg/min.
Pediatric Dosing
Not established in children: The label has no pediatric studies. It cites an AHA-suggested infusion for specialists only. The 2025 AHA Guidelines for CPR and ECC, Part 8 (the PALS bradycardia pathway), runs on oxygenation and ventilation. CPR is for a heart rate under 60/min with cardiopulmonary compromise despite effective ventilation (COR 1, LOE C-EO). Bradycardia that persists after other causes, such as hypoxia, are corrected gets epinephrine IV/IO (COR 1, C-EO). Increased vagal tone or AV block, not hypoxia, gets atropine (COR 1, C-LD). Transcutaneous pacing is for complete heart block or sinus node dysfunction that doesn't respond to CPR (COR 2b, C-EO). No isoproterenol recommendation appears in the 2025 PALS text or algorithms.
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| Refractory bradycardia or heart block (specialist use) | Start 0.1 mcg/kg/min IV infusion; usual 0.1–1 mcg/kg/min | Usual max 1 mcg/kg/min (label-cited AHA range) | High-alert Pediatric cardiology or PICU direction. See weight-based dosing |
| Status asthmaticus | Not routinely used (consult) | — | Label: infusions of 0.05–2.7 mcg/kg/min in refractory asthma caused myocardial necrosis, heart failure and death |
Continuous Infusion
| Setting | Example Concentration | Start | Titrate | Usual Range / Max |
|---|---|---|---|---|
| Adult bradycardia or AV block | Example (institution-specific): 2 mcg/mL (label mix) | 1 mcg/min | By heart rate and perfusion | 1–20 mcg/min |
| Adult torsades or VF storm | Example (institution-specific): 2 mcg/mL | 0.5 mcg/min | To the rate that suppresses recurrences | 0.5–10 mcg/min |
| Pediatric (specialist use) | Example (institution-specific) | 0.1 mcg/kg/min | By heart rate and perfusion | 0.1–1 mcg/kg/min |
Preparation & Administration
- Infusion dilution (label): 5 mL (1 mg) in 500 mL D5W = 2 mcg/mL. At that strength, 10 mcg/min runs at 300 mL/hr and 20 mcg/min at 600 mL/hr. The label also notes that concentrations up to 10 times stronger have been used when volume must be limited.
- Bolus dilution (label): 1 mL (0.2 mg) diluted to 10 mL with 0.9% NaCl or D5W = 20 mcg/mL.
- Use and inspection: use diluted solution immediately. Do not use if pinkish, darker than slightly yellow, or with a precipitate.
- Pump: infusion pump only, with the drug library set to the actual concentration; no free flow.
- Line: dedicated line or lumen so flushes do not bolus the drug.
Dosing Notes:
- The bradycardia doses come from the 2018 ACC/AHA/HRS guideline. Current PLR-format labels give no bradycardia dosing. The heart-block dosing in older-format labels (initial bolus 20–60 mcg IV) matches it.
- The torsades and VF-storm range (0.5–10 mcg/min) comes from the 2022 ESC guideline. The 2025 AHA Guidelines for CPR and ECC, Part 9 (polymorphic VT), name no isoproterenol dose. For sustained polymorphic VT, the call is an immediate unsynchronized shock (COR 1, LOE B-NR). For recurrences with a long QT, magnesium (COR 2b, LOE C-LD). When pauses trigger torsades, expert consultation is the route to overdrive pacing or isoproterenol.
- Current prescribing information is IV only. Some vial and carton labels still print IM, subcutaneous and intracardiac routes from older labeling. Give IV.
Contraindications & Precautions
Contraindications
- Tachycardia or tachyarrhythmias (label).
- Ventricular arrhythmias (label), except as specialist therapy for recurrent pause-dependent torsades (acquired long QT) or for electrical storm in Brugada syndrome, early repolarization syndrome or idiopathic VF.
- Angina pectoris (label) and acute coronary syndrome, per the 2022 ESC guideline.
- Congenital long QT syndrome, per the 2022 ESC guideline. Adrenergic stimulation can trigger torsades.
- Tachycardia or heart block from digitalis toxicity (older labels): treat with digoxin immune fab instead.
Precautions
- Coronary artery disease or cardiomyopathy: Arrhythmias and ischemia become more likely.
- Hypovolemia: Replace volume first. Vasodilation can drop the pressure.
- Organic AV node disease: Older labels report that heart block or Adams-Stokes attacks can paradoxically worsen. Have pacing ready.
- Sulfite sensitivity: Some products contain sodium metabisulfite. That doesn't rule out emergency use.
- Potent inhaled anesthetics such as halothane: avoid the combination (arrhythmias).
Hold / Reassess If
- Heart rate above the goal set by the prescriber (shock dosing per label: consider reducing or pausing above 110/min): reduce the rate.
- Heart rate above 130/min, new or increasing PVCs, or VT: reduce or stop; ventricular arrhythmia risk rises at these rates.
- Chest pain or new ST changes: reduce or stop; 12-lead ECG.
- MAP or diastolic pressure below goal: reduce, give volume, or switch to epinephrine (stop isoproterenol first; do not run both together).
- No rate response at the top of the range: pace rather than escalate.
Adverse Effects & Toxicity
Common
Nobody has established how often these happen. The labels only list voluntary reports.
- Tachycardia and palpitations
- Nervousness, mild tremor, weakness, headache, dizziness, blurred vision
- Flushing, sweating, pallor
- Nausea
- Blood pressure changes: vasodilation usually drops the diastolic and mean pressure. The systolic may rise or stay the same. Both hypotension and hypertension have been reported.
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
| Ventricular arrhythmias | PVCs, VT or VF on the monitor; Adams-Stokes attacks | Reduce or stop; correct K⁺ and Mg²⁺; ACLS and defibrillation as needed |
| Myocardial ischemia | Angina, ST depression or elevation, troponin rise | Reduce or stop; 12-lead ECG, troponin; pace instead |
| Hypotension | Falling diastolic and mean pressure as the rate rises | Reduce; give volume if underfilled; switch to epinephrine (stop isoproterenol first; do not run both together) or add norepinephrine per prescriber |
| Pulmonary edema | Dyspnea, crackles, falling SpO₂ | Reduce or stop; oxygen and ventilatory support |
Overdose & Toxicity Management
- Signs: tachycardia or other arrhythmias, palpitations, angina, hypotension or hypertension.
- Immediate: Reduce the rate or stop until the patient is stable. The effect fades within minutes. Monitor blood pressure, pulse, respirations and ECG.
- Antidote: There isn't one. Treat arrhythmias per ACLS/PALS. Dialyzability is unknown.
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: ECG rate and rhythm | Continuous | Rate above goal: reduce. Above 130/min, new PVCs or VT: reduce or stop |
| Clinical: QTc and pauses (torsades) | Continuous rhythm; 12-lead before and after titration | Recurrent torsades: increase toward the rate that suppresses it, or pace; sustained polymorphic VT: unsynchronized shock |
| Clinical: blood pressure | Continuous arterial line in shock; otherwise frequent cuff readings while titrating | MAP or diastolic falling below goal: reduce, give volume, add norepinephrine per prescriber, or switch to epinephrine (never both with isoproterenol) |
| Clinical: ischemia | Symptoms and ST segments continuously | Chest pain or ST change: reduce or stop; 12-lead ECG and troponin |
| Clinical: perfusion | Mentation, skin, urine output, CVP if available | No improvement at the top of the range: pace |
| Laboratory: potassium and magnesium | Baseline and repeat during torsades or ventricular ectopy | Low K⁺ or Mg²⁺: replace (lowers arrhythmia risk) |
| Infusion safety: pump and concentration | At start, every bag change and handoff | Units must read mcg/min (adult) or mcg/kg/min (pediatric) and match the bag |
| Pacing readiness | Before starting | Pads on and capture tested if feasible; see transcutaneous pacing |
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| Epinephrine | Combined β stimulation can cause serious arrhythmias | Do not give at the same time (label); older labels allow alternating with an interval |
| β-blockers (propranolol, metoprolol, esmolol) | Antagonize the cardiac and bronchodilator effects | Expect a blunted response; in overdose use vasopressors and high-dose insulin (2025 AHA Part 10, COR 1), glucagon (COR 2a), and refer for VA-ECMO if shock is refractory (COR 2a) |
| Tricyclic antidepressants, MAO inhibitors, levothyroxine | Potentiate isoproterenol effects | Start low; monitor heart rate, rhythm and blood pressure |
| Antihistamines (diphenhydramine, chlorpheniramine) | May potentiate effects (label) | Monitor and adjust the dose |
| Halothane and other potent inhaled anesthetics | Higher arrhythmia risk | Avoid the combination (older labels) |
| Other catecholamines and inotropes (dopamine, dobutamine) | Additive tachycardia, ectopy and oxygen demand | Titrate one agent at a time; reassess each |
IV Compatibility
- Diluents (label): D5W for infusion; 0.9% NaCl or D5W for bolus dilution.
- Dedicated line or lumen: no boluses or flushes through the isoproterenol line.
- Discard any solution that is pink, darker than slightly yellow or has a precipitate.
- Verify with an institutional compatibility resource.
Special Populations
- Pediatrics: Not established. Specialists only (see the Pediatric Dosing table). IV use in refractory asthma has caused deaths, and the risk climbs with acidosis, hypoxemia, corticosteroids or methylxanthines. If it's used, the label calls for continuous vital signs, frequent ECGs and daily CK-MB.
- Pregnancy: Decades of published use show no drug-associated risk of major birth defects or miscarriage. Untreated shock or bradycardia endangers mother and fetus, so don't withhold indicated therapy. Avoid it during the second stage of labor, since it may inhibit contractions and delay delivery. The label also says to avoid it in obstetrics when maternal blood pressure is above 130/80 mmHg. It warns of uterine vasoconstriction, reduced uterine blood flow, uterine atony with hemorrhage and fetal anoxia.
- Lactation: There are no data on transfer into human milk. The short half-life makes infant exposure likely very low.
- Older Adults: They may respond less to β stimulation (label). Start at the low end of the range and watch for ischemia. It isn't on the AGS Beers Criteria.
- Renal Impairment: No specific adjustment has been established. Titrate to effect.
- Hepatic Impairment: No specific adjustment has been established. Titrate to effect.
- Obesity / Dosing Weight: Adult doses are in mcg/min, not weight-based. Pediatric mcg/kg/min dosing has no labeled guidance. Pick one institutional dosing weight and document it.
- Heart Transplant Recipients: Atropine should not be used for sinus bradycardia without reinnervation (2018 ACC/AHA/HRS: harm). The transplant team uses aminophylline or theophylline, a direct β-agonist or pacing.
Field & Transport Considerations
- Scope: Critical-care transport (CCT), RN and Paramedic crews usually keep running an infusion the sending facility started. That varies by state and agency protocol.
- Storage & Stability: Current US labels for Isuprel and generics say 20–25°C (68–77°F), protected from light in the carton. Check yours. The label says to use diluted solution immediately, so follow the sending pharmacy's beyond-use date on any bag that travels.
- Carried Concentration: Mixes run from the label's 2 mcg/mL up to 10 times stronger, which is used when volume must be limited. Confirm the mcg/mL on the bag and in the pump library before you leave.
- Infusions in Transport: Give it a dedicated pump channel and line. Carry enough volume for the trip, since dilute mixes run at high mL/hr. Pads go on the patient and the pacer stays ready, because this is a bridge.
- Handoff Essentials: indication, current rate in mcg/min, concentration, last titration and heart-rate goal, rhythm and blood pressure response, pacing status, latest K⁺ and Mg²⁺, and magnesium given for torsades.
Clinical Pearls
Acquired vs congenital long QT: Pause-dependent torsades from drugs, bradycardia or low K⁺/Mg²⁺ responds to a faster rate. Congenital long QT works differently. Adrenergic surges trigger torsades there, so isoproterenol is contraindicated. Reach for magnesium, pacing and β-blockade per cardiology.
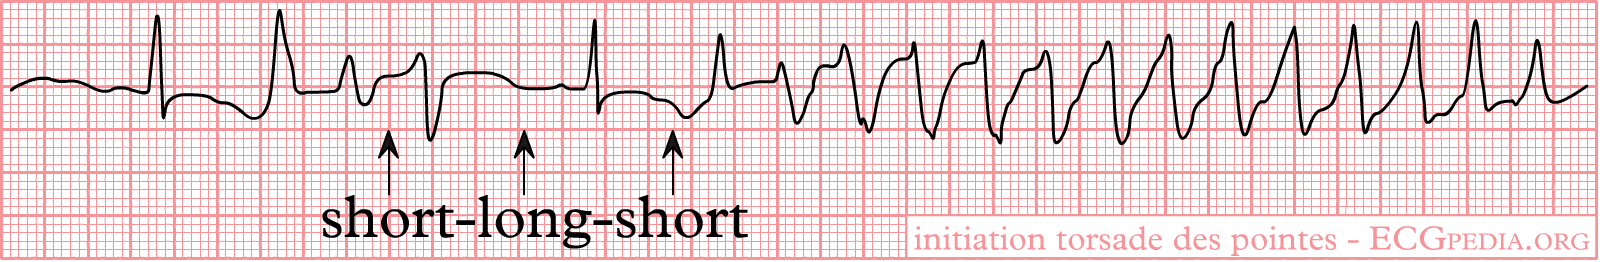
Why speed fixes torsades: A faster rate shortens the QT. It also removes the short-long-short pause that starts each run (Figure 1). Isoproterenol gets you that rate within minutes, while transvenous overdrive pacing is set up.
Isoproterenol vs epinephrine vs dopamine for bradycardia:
- Epinephrine and dopamine: The 2025 AHA adult bradycardia algorithm names both. Part 9 lists them as options when atropine fails (COR 2b, LOE C-LD). Their α effects help support blood pressure.
- Isoproterenol: Pure β. The rate and conduction effect is strong, but blood pressure often falls.
- All three: A bridge to pacing. Not a fix.
Ischemia is the trap: β-agonists raise heart rate and myocardial oxygen demand. That can worsen ischemia. When ischemia is likely, as in AV block with acute MI, favor atropine for nodal block and pacing over a pure β-agonist. This is clinical caution, not a guideline rule. AHA 2025 Part 9 lists IV adrenergic agonists only as a 2b option when atropine fails. It also names myocardial ischemia among the reversible causes to evaluate and treat.
Exam discriminator: Symptomatic bradycardia in a heart transplant recipient is the trap. The denervated heart doesn't respond to atropine, and atropine can cause harm. Isoproterenol still acts at the receptor, since it's a direct-acting β-agonist. Aminophylline and pacing are the other options.
Pharmacology
Mechanism of Action
- Synthetic catecholamine, nonselective β₁ and β₂ agonist. Its α affinity is very low.
- β₁ (heart): The sinus rate speeds up, AV conduction speeds up and contractility rises. Cardiac output goes up. The QT shortens.
- β₂ (vessels, airways): Skeletal muscle, renal and mesenteric beds dilate, and bronchial smooth muscle relaxes. SVR drops. Diastolic pressure falls, and mean pressure usually does too.
- Net effect: Rate and output rise. So does myocardial oxygen demand, while coronary perfusion pressure falls.
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| IV infusion or bolus | Immediate | Within minutes | Brief: fades within minutes of stopping |
- Half-life: about 2 min (plasma).
- Metabolism: Catechol-O-methyltransferase (COMT) breaks it down in the liver and other tissues. It's a poor monoamine oxidase (MAO) substrate, with less neuronal uptake than epinephrine. The action runs slightly longer but stays brief.
- Elimination: dialyzability unknown.
- Tolerance: Continued use can build tolerance to the smooth-muscle effects.
Names & Classification
- Generic Name
- Isoproterenol hydrochloride (international name: isoprenaline)
- Brand Names
- Isuprel; multiple generic vials
- Pharmacologic Class
- Synthetic catecholamine; nonselective β-adrenergic agonist
- Therapeutic Class
- Chronotrope and inotrope; bronchodilator (anesthesia)
- Controlled Substance
- Not controlled
- ISMP High-Alert
- Yes: ISMP high-alert medication (adrenergic agonists, IV; inotropic medications, IV)
- Look-Alike / Sound-Alike
- None on the ISMP confused drug names list
References
- Nexus Pharmaceuticals. (2023). Isoproterenol hydrochloride injection, USP: prescribing information (revised 03/2023). DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=dfb97590-dcbf-47e7-bbfe-f01580eb6ed0
- Hospira, Inc. (2018). Isuprel (isoproterenol hydrochloride injection, USP): prescribing information (revised 02/2018; older-format label with heart block, Adams-Stokes and cardiac arrest indications). Pfizer Labeling. https://labeling.pfizer.com/ShowLabeling.aspx?id=10254
- Wigginton, J. G., Agarwal, S., Bartos, J. A., Coute, R. A., Drennan, I. R., Haamid, A., Kudenchuk, P. J., Link, M. S., et al. (2025). Part 9: Adult advanced life support: 2025 American Heart Association guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation, 152(Suppl 2), S538–S577. https://doi.org/10.1161/CIR.0000000000001376
- Lasa, J. J., Dhillon, G. S., Duff, J. P., Hayes, J., Kamath-Rayne, B. D., Levy, A., et al. (2025). Part 8: Pediatric advanced life support: 2025 American Heart Association and American Academy of Pediatrics guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation, 152(Suppl 2), S479–S537. https://doi.org/10.1161/CIR.0000000000001368
- Kusumoto, F. M., Schoenfeld, M. H., Barrett, C., Edgerton, J. R., Ellenbogen, K. A., Gold, M. R., et al. (2019). 2018 ACC/AHA/HRS guideline on the evaluation and management of patients with bradycardia and cardiac conduction delay: Executive summary. Circulation, 140(8), e333–e381. https://doi.org/10.1161/CIR.0000000000000627
- Zeppenfeld, K., Tfelt-Hansen, J., de Riva, M., Winkel, B. G., Behr, E. R., Blom, N. A., et al. (2022). 2022 ESC guidelines for the management of patients with ventricular arrhythmias and the prevention of sudden cardiac death. European Heart Journal, 43(40), 3997–4126. https://doi.org/10.1093/eurheartj/ehac262
- American Heart Association. (2025). Part 10: Adult and pediatric special circumstances of resuscitation: 2025 American Heart Association guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation, 152(Suppl 2), S578–S672. https://doi.org/10.1161/CIR.0000000000001380
- Szymanski, M. W., Patel, P., & Singh, D. P. (2026). Isoproterenol. In StatPearls (updated February 26, 2026). StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK526042/
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.