

Bedside Snapshot
- Use It For
- Potassium deficiency when oral replacement is not feasible (IV); oral prevention and treatment of hypokalemia; potassium replacement in DKA when serum K⁺ is low
- Adult Dose
- IV: up to 10 mEq/h, ≤40 mEq/L; K⁺ below 2 with ECG change: up to 40 mEq/h, monitored
- DKA, K⁺ below 3.5: 10 mEq/h; hold insulin
- Oral: 20 mEq/day (prevention); 40–100 mEq/day (treatment)
- Pediatric Dose
- IV ward: 0.2 mEq/kg/h over 3 h (max 10 mEq/h); critical care: 0.4 mEq/kg/h over 1–2 h (max 20 mEq/h); oral: max 20 mEq per dose
- Onset / Duration
- IV: effect during infusion; serum K⁺ does not necessarily reflect tissue stores. Oral extended-release: onset not defined
- Do Not Give / Hold If
- Undiluted or IV push (fatal); hyperkalemia; serum K⁺ above 5 mEq/L (practice point); falling urine output or rising creatinine; delayed GI transit (oral)
- Watch For
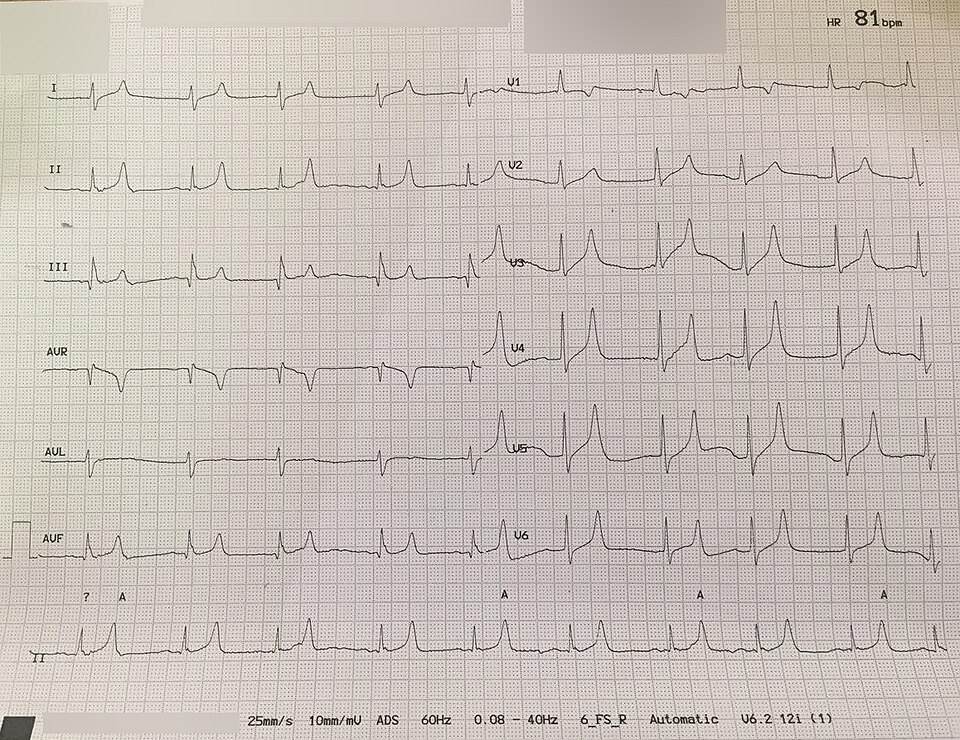
- Hyperkalemia (peaked T waves, QRS widening, bradycardia, weakness); extravasation (pain, swelling, necrosis); GI ulceration with extended-release tablets
- Reversal / Rescue
- No specific antidote: stop the infusion, monitor on ECG, and treat hyperkalemia per protocol (calcium chloride for membrane protection, insulin with dextrose, sodium bicarbonate); cardiac arrest per ACLS
- Must Remember
- Never push it: concentrate (2 mEq/mL) must be diluted before use. Check mEq (not mL), the dilution and the pump rate with an independent double-check
Indications
Emergency & Prehospital
- Symptomatic or ECG-significant hypokalemia where oral replacement is not feasible: IV replacement under monitoring
- Prehospital use: uncommon. IV potassium is carried only where a protocol allows it. Follow local protocols and medical direction.
ED / ICU / Transport
- Hypokalemia with IV access: replace it IV in a monitored setting. Serum K⁺ and the ECG guide the rate.
- Diabetic ketoacidosis (DKA): replace K⁺ before insulin or alongside it. Hold insulin while K⁺ sits below 3.5 mEq/L.
- Refractory hypokalemia: check and correct magnesium. Low magnesium promotes potassium wasting.
Other Uses
- Prevention of hypokalemia: oral extended-release tablets are for patients at risk of potassium loss, such as those on potassium-losing diuretics. Typical prevention is about 20 mEq/day.
Dosing & Administration
Doses vary by protocol; follow local protocols and medical direction.
Available Forms
- Injection concentrate: 2 mEq/mL. Pharmacy makes it up, not floor stock. Vial sizes depend on the product. One labeled presentation is a 500 mEq/250 mL pharmacy bulk package. It must be diluted first.
- Premixed IV solutions: potassium chloride rides in dextrose, sodium chloride or both. Strength varies by product.
- Oral extended-release tablets: 10, 15 and 20 mEq. On EMS and transport, the form is the IV concentrate or the premixed bag. Never oral.
- Oral liquid and effervescent forms: preferred over extended-release tablets where available. Extended-release tablets are for patients who cannot tolerate or refuse liquid or effervescent preparations.
High-Alert Medication: Undiluted, it can cause fatal arrhythmia and cardiac arrest. A direct injection can be instantly fatal. Before any run, independently double-check the mEq dose, the mL volume, the dilution, the final concentration and the pump rate.
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| Hypokalemia, IV (peripheral) | Dilute; infuse at up to 10 mEq/h; dose by deficit per protocol | Max 10 mEq/h; max 200 mEq per 24 h (when serum K⁺ is above 2.5 mEq/L) | High-alert Concentration up to 40 mEq/L. Recheck K⁺ and ECG before further doses |
| Severe hypokalemia (K⁺ below 2 mEq/L) with ECG change or muscle paralysis | Up to 40 mEq/h, very cautiously | Max 400 mEq per 24 h | High-alert Continuous cardiac monitoring required; ICU or equivalent setting; medical direction |
| DKA with K⁺ below 3.5 mEq/L | Start 10 mEq/h IV; hold insulin until K⁺ is above 3.5 mEq/L | No fixed max: titrate to K⁺ per protocol | High-alert Check K⁺ 2 h after insulin starts, then every 4 h |
| DKA with K⁺ 3.5–5 mEq/L | 20–30 mEq per litre of IV fluid to hold K⁺ at 4–5 mEq/L (fluid concentration, not an hourly rate) | No fixed max: titrate to K⁺ per protocol | High-alert Start replacement once K⁺ falls below 5 mEq/L |
| Central venous line (ICU) | Per ICU protocol; no fixed maximum. The adult central-line rate is intentionally not stated here | Protocol-dependent: confirm the local maximum | High-alert Concentrations above 40 mEq/L need central access per local policy |
| Oral prevention of hypokalemia | About 20 mEq PO once daily (typical) | Max 20 mEq per single dose | Take with meals and a full glass of water; not on an empty stomach |
| Oral treatment of potassium depletion | 40–100 mEq/day in divided doses | No single dose above 20 mEq | Monitor serum K⁺; GI ulceration warning (see Contraindications) |
Pediatric Dosing
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| Hypokalemia, IV ward infusion | 0.2 mEq/kg/h IV over 3 h | Max 10 mEq/h; no IV single-dose cap stated | High-alert Some guidance writes doses in mmol; for potassium chloride mmol equals mEq. Check the child is passing urine before starting. Peripheral usual maximum 40 mEq/L; discuss with a senior clinician for 40–60 mEq/L; above 60 mEq/L central line only. Recheck K⁺ 1 h after completion; ECG only if K⁺ is below 3 mEq/L or there is arrhythmia risk. Use measured or length-based weight (Broselow) |
| Hypokalemia, IV critical care area | 0.4 mEq/kg/h IV over 1–2 h | Max 20 mEq/h | High-alert Continuous ECG monitoring. Recheck K⁺ 1 h after starting and 1 h after completion. Concentrations above 60 mEq/L need a central line and senior-clinician approval. Specialist advice for critical hypokalemia |
| IV maintenance (if required) | 1–4 mEq/kg/day | Max 10 mEq/h | High-alert Give only where IV replacement is still needed; prefer oral when feasible |
| Oral (preferred route) | Per the pediatric oral regimen and pharmacy weight-based order (regimen not transcribed here) | Max 20 mEq per dose | Oral is the preferred route; IV potassium is high-risk |
| Neonates and infants under 1 month | Specialist (NICU) use only | — | No neonatal dose verified in this reference; use the neonatal protocol and medical direction |
Continuous Infusion
| Setting | Example Concentration | Start | Titrate | Usual Range / Max |
|---|---|---|---|---|
| Adult peripheral IV | Up to 40 mEq/L (example, institution-specific) | Dose by deficit per protocol | Per serum K⁺ and ECG | Up to 10 mEq/h; 200 mEq per 24 h |
| Adult central venous line | Institution-specific | Per ICU protocol | Per protocol | Protocol-dependent (no fixed maximum) |
| Pediatric peripheral IV | Usual maximum 40 mEq/L; senior clinician for 40–60 mEq/L | 0.2 mEq/kg/h (ward) | Per K⁺ and ECG; reassess after each change | Max 10 mEq/h |
Preparation & Administration
- Dilution: It must be diluted before IV use. Peripheral solutions go up to 40 mEq/L.
- Push rate: never IV push or bolus; infuse by pump only
- Flush: Do not flush the line after a potassium chloride infusion. The drug left in the tubing would reach the patient as a bolus. Flush or prime before connecting only, per protocol. Do not mix it in a syringe with other drugs. Label every bag, syringe, pump and line that holds potassium, so nobody flushes it by accident.
- Line: peripheral: infuse slowly through a small-bore needle placed well within a large vein. The solution is irritating in itself, so watch for infiltration. Central line per protocol.
- Pump: infusion pump with a drug library; confirm mEq/h versus mL/h on the pump
- Oral extended-release: take with meals and a full glass of water, not on an empty stomach
Contraindications & Precautions
Contraindications
- Hyperkalemia
- Renal failure or conditions in which potassium is retained
- Delayed GI transit of oral tablets, for example diabetic gastroparesis or anticholinergic drugs
- Potassium-sparing diuretic co-use (triamterene, amiloride, spironolactone). They sit inside the hyperkalemia contraindication. Combining them to treat hypokalemia is advised against.
- Conditions in which potassium and chloride additives could be clinically detrimental
- Undiluted administration: never (warning on fatal arrhythmia)
No emergency exception to the hyperkalemia contraindication is stated. When hypokalemia threatens life, lean on specialist and medical direction.
Precautions
- Hyperkalemia risk factors: chronic renal failure, systemic acidosis (for example diabetic acidosis), acute dehydration, extensive tissue breakdown (for example severe burns), adrenal insufficiency, and potassium-sparing diuretics
- Renal impairment: may cause life-threatening hyperkalemia, because potassium is retained.
- Digitalis: serial ECG mainly guides potassium therapy.
- Serum level vs tissue: Serum K⁺ does not necessarily mirror tissue potassium.
- Enlarged left atrium: esophageal ulceration can occur with extended-release tablets, through esophageal compression. Use a liquid or aqueous form.
- Pregnancy: only if clearly needed. Animal reproduction studies have not been conducted.
Hold / Reassess If
- Serum K⁺ above 5 mEq/L: hold replacement and recheck. Follow protocol. Think of this as a conservative practice point, not a formal guideline stop rule. In DKA, replacement waits until K⁺ falls below 5 mEq/L (see the DKA rows in the Adult Dosing table).
- New peaked T waves, QRS widening, bradycardia or new arrhythmia: stop the infusion, check K⁺ and treat per protocol
- Falling urine output or rising creatinine: hold and reassess before any further dose
- Serum Mg²⁺ low: check and correct magnesium with refractory hypokalemia
Adverse Effects & Toxicity
Common
- Pain, burning or redness along an infused vein (intrinsically irritating)
- Nausea, abdominal discomfort and gastric irritation with oral doses
- Local tissue injury from infiltration: swelling, necrosis and sloughing
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
| Hyperkalemia | Peaked T waves, PR prolongation, QRS widening, bradycardia, flaccid weakness or paralysis, asystole | Stop the infusion; continuous ECG; check K⁺ and glucose; treat per protocol (see Toxicity) |
| Fatal arrhythmia or cardiac arrest | Sudden collapse after undiluted or rapid IV administration | ACLS per protocol; the cause is the undiluted drug, so review the infusion first |
| Extravasation | Pain, swelling, blanching, cool skin at the site | Stop and remove the line; treat per local extravasation protocol; monitor the limb |
| GI ulceration or bleeding (extended-release) | Severe vomiting, abdominal pain, distention or GI bleeding | Discontinue immediately; consider ulceration, obstruction or perforation |
Overdose & Toxicity Management
- Toxidrome: hyperkalemia: weakness, paralysis, peaked T waves, QRS widening, bradycardia, arrest
- Immediate: stop the infusion; continuous ECG and a 12-lead; check K⁺, glucose and ionized calcium
- Membrane stabilization: Give IV calcium for ECG changes (see calcium chloride). It protects the heart. It does not lower K⁺.
- Shift: insulin with dextrose (see insulin and dextrose); sodium bicarbonate per protocol (see sodium bicarbonate)
- Removal: potassium removal per protocol; for refractory cases see hemodialysis
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: ECG | Ward IV replacement: ECG only if K⁺ is below 3 mEq/L or there is arrhythmia risk. Critical-care rate: continuous ECG. Serial 12-lead ECG with digitalis | Peaked T waves, QRS widening, new arrhythmia or bradycardia: stop the infusion, check K⁺, treat |
| Clinical: IV site | Every check during the infusion | Pain, swelling or blanching: stop and restart the line; treat extravasation |
| Clinical: urine output | Before each dose | Falling output or rising creatinine: hold and reassess |
| Laboratory: serum K⁺ | DKA: 2 h after insulin starts, then every 4 h; otherwise per protocol and after each change. Potassium lab page | Below 3.5 mEq/L: start replacement (DKA: hold insulin). Above 5 mEq/L: do not start or continue; recheck |
| Laboratory: magnesium | When hypokalemia is refractory or does not respond | Low Mg²⁺: correct it; hypomagnesemia promotes potassium wasting |
| Infusion safety | Every titration and every handoff | Confirm mEq total (not mL), concentration up to 40 mEq/L, rate up to 10 mEq/h peripheral, 24-h total up to 200 mEq |
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| Potassium-sparing diuretics (triamterene, amiloride, spironolactone) | Severe hyperkalemia when combined with potassium salts | Do not combine for hypokalemia; choose another strategy and reassess with medical direction |
| ACE inhibitors, ARBs, aliskiren, eplerenone, NSAIDs | Potassium retention and hyperkalemia | Monitor K⁺ closely; reassess the need for potassium |
| Digitalis (digoxin) | Potassium changes affect digitalis risk; therapy is guided by serial ECG | Serial ECG during replacement |
| Insulin | Insulin moves K⁺ into cells; in DKA with K⁺ below 3.5 mEq/L, replace K⁺ first | Check K⁺ before insulin; hold insulin while K⁺ is below 3.5 mEq/L |
| Anticholinergic drugs or delayed GI transit | Tablets can lodge and injure the GI tract (contraindicated) | Do not use oral extended-release tablets with delayed transit; use liquid |
IV Compatibility
- Diluent: dilute in a compatible IV solution per pharmacy and product instructions
- Admixture: Additives may clash with the fluid withdrawn from the container. Consult a pharmacist.
- Verify with an institutional compatibility resource.
Special Populations
- Pediatrics: IV potassium is high-risk in children. The doses are in the Pediatric Dosing table. Use measured or length-based weight.
- Neonates: Premature neonates are at particular risk of aluminum accumulation, because their kidneys are immature. No neonatal dose is given here. Specialist use only.
- Pregnancy: Give only if clearly needed. Animal reproduction studies have not been conducted. Correct hypokalemia through the usual monitored route, and follow obstetric direction.
- Lactation: No lactation-specific data are stated. No specific adjustment has been established.
- Older Adults: Older adults carry a higher risk of hyperkalemia as kidney function declines and when they take RAAS inhibitors. No specific age-based dose has been established.
- Renal Impairment: Life-threatening hyperkalemia can occur with renal insufficiency and potassium retention. No numeric renal dose adjustment is stated. Check creatinine, urine output and K⁺ before each dose.
- Hepatic Impairment: No specific adjustment has been established.
- Obesity / Dosing Weight: Adult doses are fixed mEq amounts. Pediatric doses are weight-based, using ideal or measured weight per protocol.
- Diabetic Ketoacidosis: Total-body potassium is low even when serum K⁺ reads normal or high. The K⁺-based rules are in Dosing.
Field & Transport Considerations
- Scope: IV potassium is usually given by RNs, critical-care nurses and CCT teams. Paramedic scope varies by state and agency protocol.
- Storage & Stability: Store as directed on the product. The concentrate is kept segregated and locked away from routine stock, depending on protocol.
- Carried Concentration: Never carry or draw up the 2 mEq/mL concentrate undiluted in the field. Prefer premixed bags where they are stocked. Write doses as mEq and volume as mL.
- Infusions in Transport: pump with drug library; dilution done per pharmacy; cardiac monitoring; confirm mEq total, rate and last K⁺ at handoff; carry bag volume for the trip plus delays.
- Handoff Essentials: total mEq given, concentration and dilution, current rate, last serum K⁺ and time, rhythm and ECG changes, site condition, and insulin or magnesium given.
Clinical Pearls
Never push or bolus: Concentrate must be diluted. Undiluted or rapid IV doses have caused fatal arrhythmia and arrest. It is a high-alert medication, and a dosing mistake does its worst damage here.
DKA sequence (CCRN, FP-C): Low K⁺ in DKA? Potassium first. If K⁺ is below 3.5 mEq/L, start at 10 mEq/h and hold insulin until K⁺ climbs above 3.5 mEq/L.
Check magnesium: If the potassium will not come up, look at magnesium. Low magnesium promotes potassium wasting.
Peripheral vs central (CCRN, CCP-C):
- Peripheral: up to 10 mEq/h, up to 40 mEq/L, 200 mEq per 24 h
- Urgent (K⁺ below 2 mEq/L with ECG change or paralysis): up to 40 mEq/h with monitoring
- Adult central-line rates: this reference states no maximum. Follow the ICU protocol. The omission is intentional.
- Pediatric central line: concentrations above 60 mEq/L only via a central line, at no more than 0.4 mEq/kg/h, with senior approval and ECG monitoring
Serum is not tissue: The lab can read normal while the stores are not replete. Serum K⁺ does not necessarily reflect tissue potassium.
Pharmacology
Mechanism of Action
- Potassium ion → restores the main intracellular cation → resting membrane potential for nerve and muscle function
- Excess extracellular K⁺ → reduced membrane gradient → conduction slowing, peaked T waves and QRS widening
- Renal excretion → the kidney is the main exit for potassium, so kidney function sets the safe rate
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| IV | During infusion | Not defined | Depends on renal excretion and cellular shifts |
| PO (extended-release) | Not defined | Not defined | Depends on renal excretion |
- Half-life: not applicable. The kidney and cellular shifts regulate body potassium.
- Metabolism: none (electrolyte)
- Elimination: renal (main route)
Names & Classification
- Generic Name
- Potassium chloride
- Brand Names
- Injection: generic (concentrate and premixed). Oral extended-release: Klor-Con M and generics
- Pharmacologic Class
- Electrolyte; potassium salt
- Therapeutic Class
- Potassium replacement
- Controlled Substance
- Not controlled
- ISMP High-Alert
- Yes: ISMP high-alert medication (concentrated injectable electrolytes)
- Look-Alike / Sound-Alike
- None commonly reported in this reference
- Error-Prone Abbreviations to Avoid
- None specific; write doses in mEq and volume in mL
References
- B. Braun Medical Inc. (2022). Potassium chloride for injection concentrate, USP: Prescribing information (revised November 2022). DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/lookup.cfm?setid=ab67b151-8368-4321-b562-bad5eff7b740
- Advagen Pharma Ltd. (2026). Potassium chloride extended-release tablets, USP: Prescribing information (revised January 2026). DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/fda/fdaDrugXsl.cfm?setid=f4497c26-da16-45b0-975d-81f2c2132704
- Umpierrez, G. E., et al. (2024). Hyperglycemic crises in adults with diabetes: A consensus report. Diabetes Care, 47(8), 1257–1275. https://doi.org/10.2337/dci24-0032
- The Royal Children's Hospital Melbourne. (2024). Clinical Practice Guidelines: Hypokalaemia (last updated October 2024). https://www.rch.org.au/clinicalguide/guideline_index/Hypokalaemia/
- Institute for Safe Medication Practices (ISMP). (2021). Administration of concentrated potassium chloride for injection during a code: Still deadly! ISMP Medication Safety Alert! Acute Care Edition, 26(11), 1–5 (June 3, 2021). Hosted by AHRQ Patient Safety Network. https://psnet.ahrq.gov/issue/administration-concentrated-potassium-chloride-injection-during-code-still-deadly
- Institute for Safe Medication Practices (ISMP). (2024). ISMP List of High-Alert Medications in Acute Care Settings. https://home.ecri.org/blogs/ismp-resources/high-alert-medications-in-acute-care-settings
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.