

Bedside Snapshot
- Indications
- Hgb <7 g/dL in stable hospitalized adults per the AABB 2023 guideline
- Hemorrhage with shock: massive transfusion protocol, not a Hgb trigger
- Children: weight-based volume per blood bank protocol
- Contraindications / Abort
- Unit label does not match order or patient: do not start
- Fever, chills, flank pain, dyspnea or hypotension: stop
- Dextrose or Lactated Ringer's in the line: do not use
- Critical Steps
- Two identifiers and a second-person or bar-code check
- 0.9% saline only; 170–200 µm filter
- Start promptly after leaving storage (often 30 min); finish within 4 h
- Confirm & Monitor
- Vital signs at baseline, at start, about 15 min and at completion
- Watch for reaction signs for hours after the last unit
- Stop, keep the IV open with fresh saline, notify the blood bank
Key Numbers
Use these numbers at the bedside. Volumes are weight-based where the blood bank or protocol says so. Follow local protocols and medical direction.
| Parameter | Value |
|---|---|
| Hemoglobin trigger (stable hospitalized adults) | Transfuse when Hgb <7 g/dL in stable hospitalized adults per the AABB 2023 guideline (strong recommendation); 8 g/dL for orthopedic surgery or preexisting cardiovascular disease. Does not apply to active bleeding |
| Start after leaving storage | Start promptly; many policies require the start within 30 min. If it cannot start, return the unit per blood bank policy |
| Finish time | Complete within 4 h of leaving controlled storage (the hard limit); follow blood bank policy |
| Line and filter | Standard blood set with a 170–200 µm filter; 0.9% saline only |
| Reaction first action | Stop the transfusion; replace the set and keep the IV open with fresh 0.9% saline (not the blood line); notify the blood bank |
| Anaphylaxis | Adult: epinephrine 0.3–0.5 mg IM Peds: 0.01 mg/kg IM (max 0.3 mg) |
| Hypocalcemia (massive transfusion) | Calcium replacement guided by ionized calcium per protocol; adult calcium chloride 1 g IV through a separate IV (see Medications) |
| Pediatric volume | Weight-based (mL/kg) per blood bank protocol; never a fixed adult unit |
Overview & Principles
Blood components (red cells, plasma, platelets, and whole blood where a program uses it) replace one of two things: oxygen-carrying capacity or clotting factors. Transfusion acts like a drug, and it carries real risk. Get the indication right, check the unit, and know your reaction response. Those matter as much as the connection itself.
How It Works
- Red cells: the cells restore oxygen-carrying capacity. Low hemoglobin and a patient who shows need are the reasons to give them.
- Plasma and platelets: they replace clotting factors or platelets in a bleeding patient. In hemorrhage, the massive transfusion protocol is the tool.
- Unit handling: keep it cold until it is spiked. Don't leave it at room temperature.
- Line: one fluid, the right set. Use a compatible set and 0.9% saline only. Dextrose and calcium-containing solutions are not used with red cells.
- Reactions: most show up within the first minutes to hours. Watch the patient from start to finish.
Where It Fits
- Stable anemia: the AABB 2023 restrictive strategy runs on a hemoglobin trigger.
- Active hemorrhage: the hemoglobin number does not guide transfusion. Run the massive transfusion protocol and follow the clinical response.
- Prehospital or in-flight: transport teams may carry blood under local protocol. The JTS 2020 guideline names cold-stored low-titer O whole blood, calcium replacement and minimal crystalloid as key points (see Indications).
Indications & Contraindications
Indications
- Stable hospitalized adults: transfuse red cells when Hgb is below 7 g/dL per the AABB 2023 guideline.
- Orthopedic surgery or preexisting cardiovascular disease: a threshold of 8 g/dL is an accepted choice per the AABB 2023 guideline.
- Hematologic or oncologic disorders: a restrictive 7 g/dL threshold per the AABB 2023 guideline (conditional, low certainty evidence).
- Cardiac surgery: a threshold of 7.5 g/dL is an accepted choice per the AABB 2023 guideline.
- Hemorrhage with shock: transfuse under the massive transfusion protocol, guided by response, not a single hemoglobin value.
- Children: critically ill, hemodynamically stable children without hemoglobinopathy, cyanotic cardiac condition or severe hypoxemia use a restrictive 7 g/dL threshold per the AABB 2023 guideline (strong recommendation). Congenital heart disease thresholds: see Special Populations.
Prehospital and In-Flight Hemorrhage
- No hemoglobin trigger: the 7 g/dL number does not apply to hemorrhage. Judge by blood loss, shock and response.
- Product: if the program carries cold-stored low-titer O whole blood, the JTS 2020 guideline names it as a key option. Otherwise, follow the program’s component plan. Ratios are set by protocol, and this page does not state them.
- Calcium: calcium replacement goes with blood products, per protocol (see Medications).
- Crystalloid: keep it to a minimum. Crystalloid dilutes clotting factors and red cells.
- Warming: rapid infusion calls for a warmer. Hypothermia worsens coagulopathy.
- Evidence: a randomized trial of air-transported trauma patients at risk of hemorrhagic shock found that prehospital plasma lowered 30-day mortality (PAMPer). Hemorrhage control and tranexamic acid follow the program protocol. Their doses are not on this page.
Absolute Contraindications
- Wrong unit or wrong patient: the unit label does not match the order or the patient.
- Incompatible unit: a crossmatch or ABO mismatch is found.
Relative Contraindications & Cautions
- Volume overload: heart failure or renal failure raises the TACO risk. Give slowly. Reassess the lung exam and oxygenation.
- Unexplained fever or hypotension: assume a possible reaction until the blood bank says otherwise.
- Known antibodies: units need extended matching. The blood bank decides.
Consider an Alternative
- Volume loss without anemia: crystalloid or albumin per protocol; see Albumin.
- Vascular access problems: see IO Access when IV access fails.
Scope & Team Roles
| Provider Level | Typical Role | Notes |
|---|---|---|
| EMT | Not in scope | Recognize and report reaction signs; do not start or manage a unit. |
| AEMT | Not in scope | Monitor and report; state and agency rules decide. |
| Paramedic | Performs (protocol/credentialing required) | Blood carriage and administration only under agency credentialing. Not in national model; state/agency credentialing. |
| RN (ED/ICU) | Performs (protocol/credentialing required) | Hang and monitor under facility policy and blood bank procedure. |
| Critical Care Transport (CFRN / CTRN / FP-C / CCP-C) | Performs (protocol/credentialing required) | In-flight administration under medical direction and agency policy. |
| Physician / APP | Performs | Orders the product, sets the indication and decides on the reaction plan. |
Team Roles During the Transfusion
- Verifier: checks the unit, order and patient with a second clinician or a bar-code check.
- Operator: starts the unit, sets the rate and watches the line.
- Monitor: records vital signs and calls for reaction signs.
- Blood bank contact: receives the call for any reaction and returns the unit if needed.
Pre-Procedure Assessment
Patient Check
- Identifiers: two patient identifiers (name plus date of birth or ID number) per facility policy. A room number is not one.
- Baseline: temperature, heart rate, blood pressure, respiratory rate and SpO₂ before the first mL.
- Indication: the Hgb or bleeding status that led to the order.
- Allergy and prior reactions: note any past reaction and the blood bank history.
Unit Check
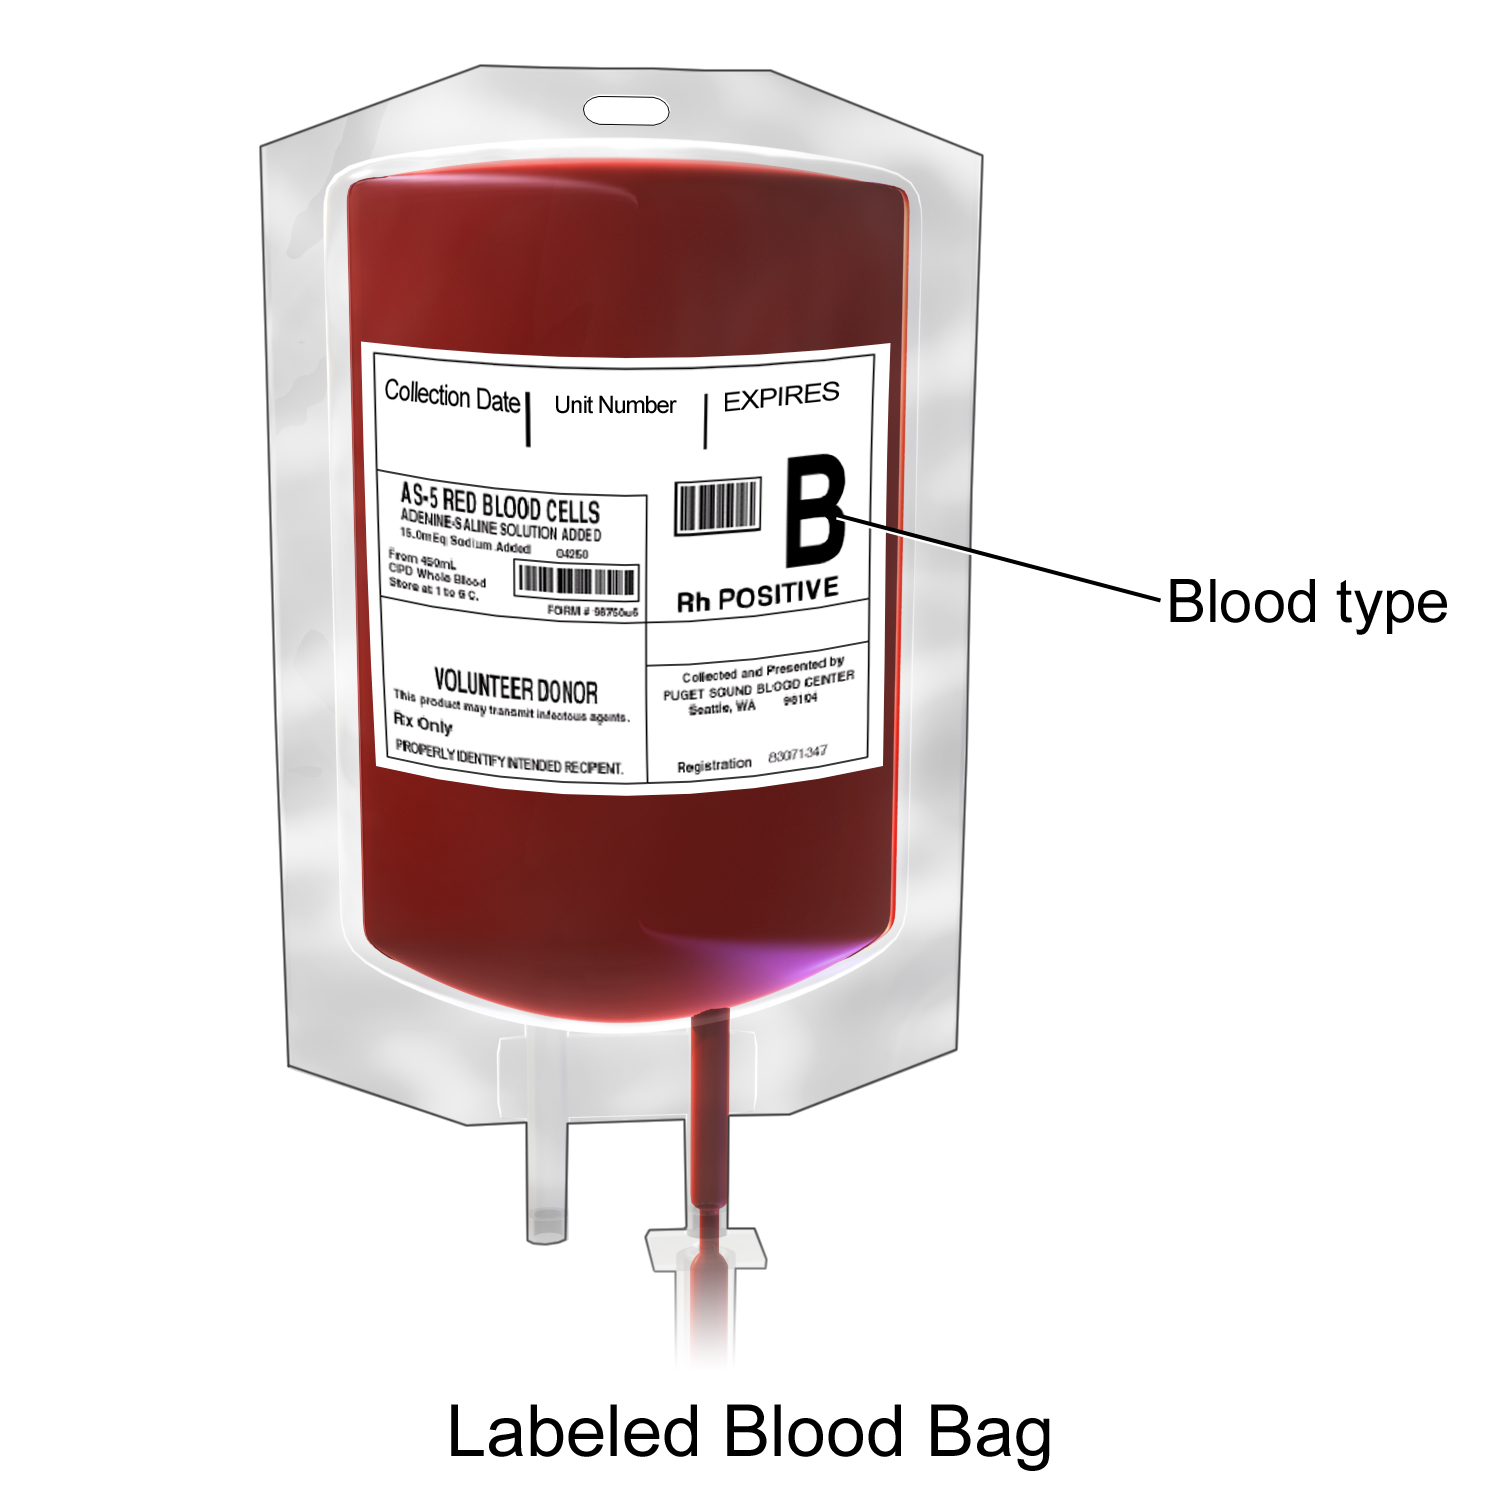
- Label: component type, ABO/Rh, donor number and unit number match the order and the patient.
- Storage: track the time out of refrigeration. If the 4-hour limit cannot be met, return the unit.
Equipment & Preparation
Equipment
- Blood administration set: standard set with a 170–200 µm filter (not a dextrose-compatible set).
- 0.9% sodium chloride: the only line fluid; no dextrose and no Lactated Ringer's with the unit.
- Warmer: use a blood warmer per device labeling for rapid or large-volume transfusion.
- Pump or rapid infuser: set the rate per protocol; use a pressure device only where the device is labeled for blood.
- Monitoring: cardiac monitor, pulse oximetry, blood pressure and temperature.
- Emergency drugs: epinephrine (IM and IV), diphenhydramine, calcium chloride and hydrocortisone available.
Patient Positioning & Preparation
- Place the patient in a stable position with the IV site visible and checked.
- Give the team a clear plan for reactions and the blood bank phone number.
Pre-Transfusion Checklist
- Two patient identifiers checked against the order
- Unit label matches the order (component, ABO/Rh, unit number)
- Second person or bar-code verification done
- Baseline vital signs recorded
- 0.9% saline line and 170–200 µm filter set
- Time left refrigeration noted; 4-hour limit in view
- Reaction plan and blood bank contact ready
Medications & Settings
Read these as typical adult and pediatric references for reaction response. Before use, check them against local protocol and current drug labeling. Doses vary by protocol; follow local protocols and medical direction.
| Drug | Adult Dose | Pediatric Dose | Onset / Duration | Notes |
|---|---|---|---|---|
| Epinephrine IM 1 mg/mL | 0.3–0.5 mg IM (anaphylaxis) | 0.01 mg/kg IM (max 0.3 mg) | IM peak 5–10 min / short | Anaphylaxis with wheeze, stridor or hypotension. Repeat per protocol. |
| Diphenhydramine | 25–50 mg IV/IM | 1 mg/kg (max 50 mg) | IV rapid / 4–6 hr | Mild allergic reaction (hives, itch). Sedating; not a substitute for epinephrine in anaphylaxis. |
| Hydrocortisone | 100 mg IV/IM | 2 mg/kg (max 100 mg) | IV/IM ≤1 hr / 4–6 hr | Per protocol for allergic reactions; does not treat acute anaphylaxis by itself. |
| Calcium chloride | 1 g (10 mL of 10%) IV | 20 mg/kg (max 1 g per dose) per local protocol | IV ≤3 min / 30–60 min | Hypocalcemia from citrate. Give slowly through a large vein or a separate IV, never through the blood line. Guide dosing by ionized calcium. Monitor rhythm. |
| Furosemide | 20–40 mg IV/IM | 1 mg/kg IV | IV ≤5 min / about 2 hr | For suspected TACO with volume overload and no shock. Per protocol. |
Settings
- Completion time: finish within 4 h of leaving refrigerated storage.
- Rate: set per protocol and per patient response; slow rate for TACO risk.
- Pediatric rate and volume: set by weight per blood bank protocol.
Step-by-Step Procedure
Phase 1: Prepare
- Confirm the order: product, indication and the patient. Check two patient identifiers.
- Check the unit: label matches the order and the patient. A second person or bar-code check confirms the match.
- Check the time: note the time the unit left controlled storage. Start promptly; many policies require the start within 30 minutes. If it cannot start, return it to the blood bank per policy.
- Set the line: use a standard blood set with a 170–200 µm filter, primed with 0.9% saline.
Phase 2: Perform
- Start slowly: begin at the slow rate set by protocol and check vital signs at about 15 minutes; a reaction most often shows early.
- Keep the line saline-only: no dextrose, no Lactated Ringer's and no drug through the unit line.
- Increase the rate: per protocol and per patient response, watching for volume overload.
Phase 3: Confirm & Finish
- Finish within 4 hours: complete the unit within 4 h of leaving controlled storage; this is the hard limit.
- Record: unit number, start and stop times, rate, vital signs and any reaction.
- Return the bag: per blood bank policy when the unit is not used.
Confirmation & Monitoring
Primary Confirmation
The primary check happens at the bedside. Match the unit label against the order and the patient, by two people or by bar code. No lab or waveform confirms a transfusion. Vital signs and the patient's clinical course do.
Secondary Confirmation
- Flow is steady through the filter, with no clotting or swelling at the site.
- Vital signs are stable before, during and after the first 15 minutes.
- The patient has no new rash, dyspnea or fever.
| Finding | Success | Failure / Reaction |
|---|---|---|
| Unit label | Matches order and patient | Any mismatch: stop, do not start |
| Vital signs | Stable from baseline | Fall in BP, rise in HR, fever: stop and assess |
| Breathing | No new dyspnea | Dyspnea, hypoxemia, new crackles: stop; oxygen; reaction workup |
| Urine | Normal color | Dark or red urine: stop; hemolysis workup |
Ongoing Monitoring
- Baseline: vital signs before the first mL.
- At start: vital signs when the unit starts.
- About 15 minutes after start: vital signs and a symptom check.
- During: vital signs and symptoms at the frequency set by facility policy.
- After completion: vital signs at completion and with any new symptom.
Troubleshooting
| Problem | Likely Cause | Fix |
|---|---|---|
| Fever, chills, rigors | Febrile non-hemolytic, hemolytic or sepsis | Stop; check the unit and patient; notify the blood bank; blood cultures of patient and bag if sepsis is possible, per policy |
| Hypotension, flank pain, dark urine | Acute hemolytic reaction | Stop; keep the IV open with saline; notify the blood bank; ICU-level care |
| Dyspnea, hypoxemia, new infiltrates | TRALI or TACO | Stop; oxygen; TACO: diuretic per protocol; TRALI: supportive ventilation; blood bank review |
| Hives or itch only | Mild allergic reaction | Pause; antihistamine per protocol; resume only per blood bank |
| Wheeze, stridor, hypotension | Anaphylaxis | Stop; epinephrine IM; airway and fluids per protocol |
| Slow or stopped flow | Clot, kink, filter or small-gauge IV | Check the line and site; replace the set per policy; do not force flow |
| Tingling, tremor, low calcium signs | Citrate effect during rapid transfusion | Calcium replacement per protocol; slow the rate |
Suspected Acute Hemolytic Reaction
- Stop the transfusion: close the unit, replace the set and keep the IV line open with fresh 0.9% saline.
- Notify the blood bank: send the unit, bag and paperwork as the blood bank directs, and recheck the label and patient identity at the bedside.
- Support the patient: treat hypotension and fluid needs per protocol; watch urine output and for bleeding (DIC).
Blood Bank Workup
- Direct antiglobulin test (DAT), repeat ABO/Rh typing and crossmatch on a new sample.
- Hemolysis tests: plasma free hemoglobin, LDH, bilirubin, haptoglobin and urine for hemoglobin.
- Blood cultures from the patient and the bag when sepsis is possible.
- Return the bag and paperwork to the blood bank.
Complications
| Complication | Recognition | Prevention | Management |
|---|---|---|---|
| Immediate: acute hemolytic reaction | Fever, hypotension, flank pain, dark urine, bleeding | Two-person check; right patient; right unit | Stop; replace set; saline; notify blood bank; ICU care |
| Immediate: allergic or anaphylactic | Hives, wheeze, stridor, hypotension | History of prior reactions; blood bank review | Mild: antihistamine per protocol. Anaphylaxis: epinephrine IM |
| Immediate: TRALI | Hypoxemia and new bilateral infiltrates within 6 h; often hypotension; no fluid-overload pattern | Male or never-pregnant donors per blood bank; slow rate in at-risk patients | Stop; oxygen; supportive ventilation; blood bank review (donor and product) |
| Immediate: TACO | Dyspnea, crackles, hypertension, tachycardia, distended neck veins; often improves with a diuretic | Slow rate in at-risk patients; reassess lungs and oxygenation at each step | Stop; oxygen; sit up; diuretic per protocol |
| Immediate: febrile non-hemolytic | Fever and chills during or within 4 h of transfusion, without hemolysis | Leukoreduced product per blood bank | Stop and check; acetaminophen per protocol after the blood bank review |
| Metabolic (rapid or massive transfusion): hypocalcemia | Tingling, tremor, hypotension, QT prolongation | Calcium replacement per protocol; slow the rate | Calcium chloride 1 g IV adult through a separate IV, guided by ionized calcium; weight-based pediatric dose per protocol |
| Metabolic (rapid or massive transfusion): hyperkalemia | Arrhythmia or weakness during large-volume transfusion | Check potassium during massive transfusion | Treat per the electrolyte protocol |
| Delayed: delayed hemolytic reaction | Fever, jaundice, falling hemoglobin or dark urine, days to weeks after transfusion | Antibody screen before transfusion (blood bank) | Blood bank workup; notify blood bank; ICU care as needed |
| Rapid or large-volume: hypothermia | Low core temperature, shivering, arrhythmia, worsening coagulopathy | Warmer per device labeling for rapid or large-volume transfusion | Warm the patient; warm the product; reassess the rate |
| Rare: bacterial sepsis | Rigors, fever and hypotension within hours | Storage and handling rules | Stop; blood cultures; antibiotics per protocol |
Life-Threatening: Anaphylaxis
- Stop the unit.
- Epinephrine: 0.3–0.5 mg IM (adult), repeat per protocol.
- Airway and fluids: per protocol; notify the blood bank.
Special Populations
Pediatrics
- Volume: weight sets it, in mL/kg, per blood bank and hospital protocol. Never give a fixed adult unit.
- Rate: go slow and reassess. Children have less reserve for volume overload.
- Thresholds: critically ill, hemodynamically stable children without hemoglobinopathy, cyanotic cardiac condition or severe hypoxemia use 7 g/dL (AABB 2023, strong recommendation). Stable children with congenital heart disease (AABB 2023, conditional, low certainty): 7 g/dL after biventricular repair, 9 g/dL after single-ventricle palliation, and 7 to 9 g/dL when uncorrected.
- Drugs: epinephrine IM 0.01 mg/kg (max 0.3 mg) and diphenhydramine 1 mg/kg (max 50 mg) per the medication pages.
- See Weight-Based Dosing and Pediatric Vascular Access.
Pregnancy
- The blood bank selects the product. Rh-negative patients who may bear children get Rh-negative red cells per blood bank policy.
- Emergency release for females of childbearing potential: until the patient’s type is known, the blood bank may issue group O red cells, Rh-negative when available (blood bank policy).
Older Adults and Heart Failure
- TACO risk runs higher here. Slow the rate and reassess lungs and oxygenation at each step.
Post-Procedure Care & Transport
Immediate Aftercare
- Recheck vital signs at completion and at the interval set by policy.
- Watch for delayed reactions for hours after the last unit.
Ongoing Maintenance
- Keep the IV patent with saline and check the site.
- Repeat labs per protocol after large-volume transfusion (hemoglobin, potassium, calcium).
Transport Considerations
- Secure the line and the unit; check the rate after every move.
- Keep the unit cold until spiked; do not let it sit at room temperature in the transport vehicle.
- Rely on monitors and vital signs in noise and vibration; a reaction can start after departure.
Document & Hand Off
- Unit number, component and start and stop times
- Rate changes and total volume given
- Pre-transfusion check and who verified
- Vital signs before, during and after
- Any reaction, treatment given and blood bank notified
Clinical Pearls & Pitfalls
Pearls
- Stable threshold: Hgb <7 g/dL in stable hospitalized adults per the AABB 2023 guideline.
- Saline only: one line, one fluid, no dextrose.
- Reaction response: stop, keep the line, notify the blood bank.
- Time limit: 4 h from leaving storage.
Common Pitfalls
- Skipped check → wrong unit: confirm two identifiers and the unit label at the bedside.
- Slow reaction call → delayed response: stop the unit at the first sign and call the blood bank.
- Drugs in the unit line → clotting or hemolysis risk: use a separate line for drugs.
- Threshold used in hemorrhage → delayed blood: judge by blood loss and shock.
Education & Skill Maintenance
Skill Maintenance
- Run a simulated reaction drill with the blood bank call included.
- Practice the two-person bedside check on every unit.
- Review the facility transfusion policy each year.
References
- Carson JL, et al. Red Blood Cell Transfusion: 2023 AABB International Guidelines. JAMA. 2023;330(19):1892-1902. doi:10.1001/jama.2023.12914. https://doi.org/10.1001/jama.2023.12914
- Vlaar APJ, et al. A consensus redefinition of transfusion-related acute lung injury. Transfusion. 2019;59:2465-2476. doi:10.1111/trf.15311. https://doi.org/10.1111/trf.15311
- Soutar R, et al. Guideline on the investigation and management of acute transfusion reactions. Br J Haematol. 2023;201(5):832-844. doi:10.1111/bjh.18789. https://doi.org/10.1111/bjh.18789
- Voller J, et al. Joint Trauma System Clinical Practice Guideline (JTS CPG): Prehospital Blood Transfusion. J Spec Oper Med. 2021;21(4):11-21 (guideline dated 30 October 2020). https://jsomonline.org/product/joint-trauma-system-clinical-practice-guideline-jts-cpg-prehospital-blood-transfusion-30-october-2020/
- Robinson S, et al. The administration of blood components: a British Society for Haematology Guideline. Transfus Med. 2018;28(1):3-21. doi:10.1111/tme.12481. https://doi.org/10.1111/tme.12481
- Sperry JL, et al. Prehospital Plasma during Air Medical Transport in Trauma Patients at Risk for Hemorrhagic Shock. N Engl J Med. 2018;379(4):315-326. doi:10.1056/NEJMoa1802345. https://doi.org/10.1056/NEJMoa1802345
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.