

Bedside Snapshot
- Indications
- Incident declared: patients exceed immediate resources
- Many casualties at one scene, sorted before transport
- Tags carry the category to each receiving facility
- Contraindications / Abort
- Unsafe scene: do not enter until hazards are controlled
- Immediate patient: bleeding and airway first, not the full sort
- Resources exceeded: escalate to incident command
- Critical Steps
- Global sort: walking last, obvious bleeding first
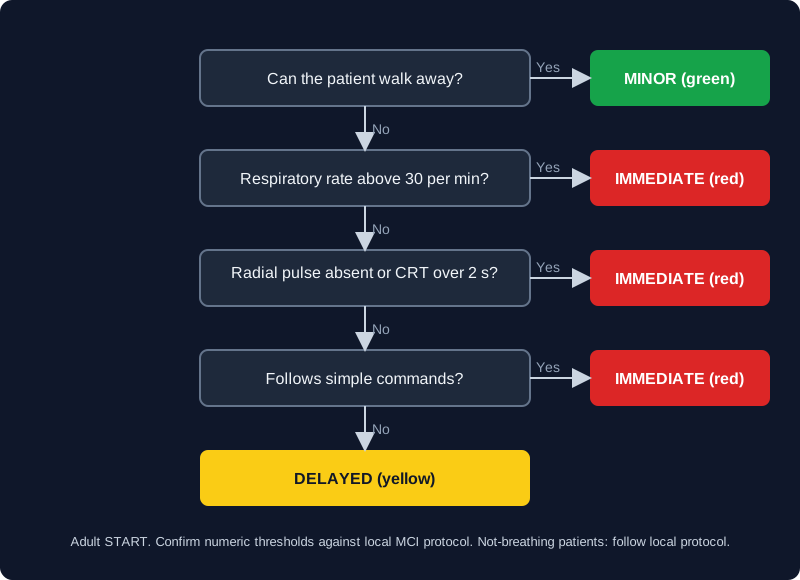
- Adult START: RR >30/min, no radial pulse or CRT >2 s, or no simple commands = Immediate
- JumpSTART (under 8 y): RR outside 15–45/min = Immediate
- Confirm & Monitor
- One tag per patient; colour counts match the headcount
- Re-triage at every move and at the receiving site
- Injured patients: destination per 2021 field triage
Key Numbers
Triage sorts many patients quickly so that the most treatable life threats are treated and moved first. Use these thresholds to decide the category, then follow your local protocol for every decision that changes care or destination.
| Parameter | Value |
|---|---|
| START: breathing | Respiratory rate above 30/min: Immediate (red) |
| START: not breathing | Reposition the airway once. Still not breathing: Deceased/Expectant (black). Breathing after repositioning: Immediate (red). Local protocols differ on how deceased and expectant are assigned |
| START: perfusion | No radial pulse, or capillary refill time over 2 s: Immediate (red) |
| START: mental status | Cannot follow simple commands: Immediate (red). Otherwise Delayed (yellow) |
| START: walking | Can walk away from the scene: Minor (green) |
| JumpSTART: age | Children younger than 8 years (pediatric algorithm) |
| JumpSTART: breathing | Respiratory rate below 15/min or above 45/min: Immediate (red) |
| JumpSTART: mental status | Alertness, or appropriate response to verbal or painful stimuli (not the adult simple-commands test) |
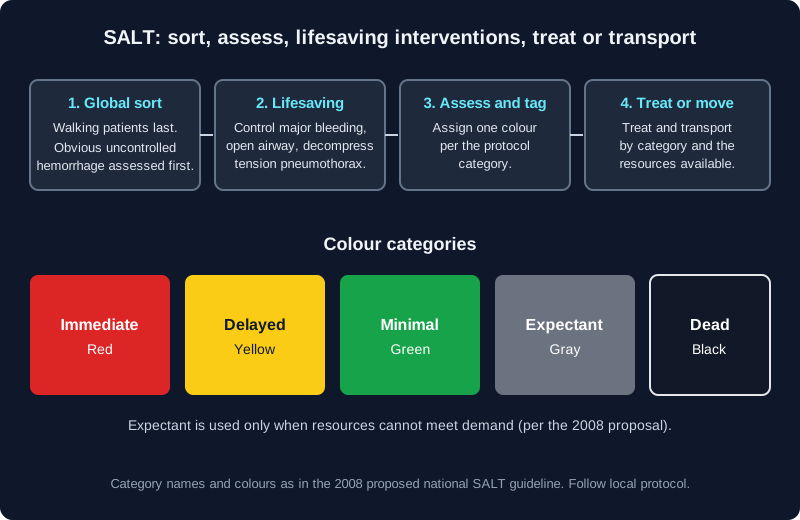
| SALT: categories | Immediate (red), Delayed (yellow), Minimal (green), Expectant (gray), Dead (black) |
| Injured patient: destination | Physiologic criteria include: motor GCS below 6 (unable to follow commands), respiratory rate <10 or >29/min, respiratory distress or need for respiratory support, room-air SpO2 below 90%; systolic BP <90 mm Hg (age 10–64 y), <110 mm Hg (65 y and older), <70 + 2 × age mm Hg (0–9 y); at age 10 y and older, heart rate above systolic BP (2021 field triage, for trauma center destination) |
| Re-triage interval | Per local protocol. No fixed interval in the sources reviewed |
Overview & Principles
When resources cannot treat everyone at once, triage gives each patient a priority category. That category sets the order of treatment and transport. It is a scene-level call. It is not a diagnosis, and it is not a plan for one patient.
How It Works
- Global sort: Split walkers from non-walkers. Under SALT, walkers are assessed last. Obvious uncontrolled bleeding is assessed first.
- Individual assessment: Check breathing, perfusion and mental status, always in the same short order. Simple Triage and Rapid Treatment (START) is the adult algorithm.
- Lifesaving care: Control major bleeding and open the airway. Other lifesaving steps, such as decompressing a tension pneumothorax, happen as the protocol allows. SALT builds this step into the sequence.
- Tag and move: attach a tag with the category, time and an identifier, then send the highest category first.
- Re-triage: reassess at each move, at the transport point and at the receiving facility.
Where It Fits
START is the adult tool. JumpSTART is its pediatric version, for children younger than 8 years. SALT (Sort, Assess, Lifesaving Interventions, Treatment and/or Transport) is the 2008 proposed national guideline (Lerner et al.). It folds the older systems into one set of colour categories. This page covers SALT's categories and sequence only. The individual assessment questions sit in the 2008 flowchart, and this page does not reproduce them. Local systems differ, so your tag labels have to match your agency's protocol. Figure 1 shows the adult START sequence.
Indications & Contraindications
Indications
- An incident declared under your local system, where the number of patients exceeds the immediate resources available
- Multiple casualties at one scene, where a fast category decides which patients are moved and treated first
- Hand-off of many patients to several receiving facilities, where the tag carries the category forward
Absolute Contraindications
None once an incident is declared. A single patient with a clear, time-critical problem goes through the individual protocol, not a tag.
Relative Contraindications & Cautions
- Unsafe scene: do not enter until hazards such as traffic, fire, violence or hazardous materials are controlled, per agency policy.
- Hazardous material or infectious exposure: Decontamination and PPE come first, per protocol. The sort happens afterward, inside the decontaminated zone.
- Resources already exceeded: The sort is no substitute for escalation. Request more resources early.
Abort / Stop Criteria
- Scene hazards persist: stop entry, request resources and wait for safe access.
- Patient in extremis at the scene: control bleeding and open the airway first, then continue the sort.
Scope & Team Roles
| Provider Level | Typical Role | Notes |
|---|---|---|
| EMT | Performs | Sort and tag with START or SALT; scope varies by state and agency |
| AEMT | Performs | Sort, tag and monitor Immediate patients per protocol |
| Paramedic | Performs | Lead triage and lifesaving care per protocol; often the triage officer |
| RN (ED/ICU) | Performs | Triage or re-triage at the facility, per the hospital disaster plan |
| Critical Care Transport (CFRN / CTRN / FP-C / CCP-C) | Monitors & maintains | Monitors Immediate patients in transport; re-triages per protocol |
| Physician / APP | Assists | Medical command: decides expectant categories and resource allocation |
Team Roles During the Procedure
- Triage officer: runs the sort, assigns categories and calls the next patient.
- Treatment lead: directs lifesaving care for the Immediate group.
- Recorder: keeps the count by colour, the times and the tag numbers.
- Transport officer: matches categories to destinations and vehicles.
Equipment & Preparation
Equipment
- Triage tags: colour-coded, numbered and tear-off, with fields for category, time and identifier
- Marking pen and clipboard: to write on tags and the recorder's sheet
- Watch or timer: to time each assessment and each re-triage
- Bleeding control: tourniquets and hemostatic dressings, per protocol
- Airway and decompression: suction, an airway adjunct and a tension pneumothorax kit, per protocol
- Pediatric sizing: a length-based tape or sizing system for children, per protocol (see Broselow)
Sizing
Triage uses vital signs and observation, not sizing. Use the pediatric vital signs reference to judge what is normal for a child's age. Adult START and pediatric JumpSTART use different breathing ranges. See Key Numbers.

Pre-Procedure Checklist
- Incident declared and command post identified
- Scene safety confirmed; entry point and exit route chosen
- Triage officer, recorder, treatment lead and transport officer assigned
- Tags in all four categories, plus extras, staged and visible
- Count sheet ready for colours and times
- Lifesaving equipment within reach of the treatment lead
- Communication with receiving facilities and transport confirmed
- Pediatric triage reference and sizing available
Step-by-Step Procedure
Phase 1: Prepare
- Confirm the incident and scene safety: declare the incident per the local system. Do not enter an unsafe scene.
- Assign roles: one triage officer, one recorder, one treatment lead and one transport officer.
- Stage the tags: set out the colour-coded tags and a pen where the triage officer can reach them.
Phase 2: Sort and Assess
- Global sort: direct walking patients to a Minor area and assess them last. Assess patients with obvious uncontrolled bleeding first.
- Check breathing: count the respiratory rate of each patient who cannot walk. In adult START, a rate above 30/min is Immediate. A patient who is not breathing has the airway repositioned once: still not breathing is Deceased/Expectant (black); breathing after repositioning is Immediate (red). Local plans differ on how deceased and expectant are assigned.
- Check perfusion: feel for a radial pulse and check capillary refill time (CRT). No pulse or CRT over 2 s is Immediate.
- Check mental status: ask the patient to follow a simple command (adult START; JumpSTART uses alertness or appropriate response to verbal or painful stimuli). Failure is Immediate. A patient who passes all checks is Delayed.
- Apply lifesaving care: control major bleeding and open the airway as your protocol allows. Decompression and other interventions are protocol-dependent; then move on.
Phase 3: Tag and Move
- Tag each patient: record the category, time and identifier, and attach the tag to the patient.
- Move the Immediate group first: send Immediate patients to the treatment lead, then to transport in category order.
- Keep a count: record the total for each colour and report it to incident command.
- Re-triage: reassess tagged patients as they move and at intervals set by protocol.
Confirmation & Monitoring
Primary Confirmation
Each patient has one tag with a category, time and identifier. The colour counts add up to the headcount.
Secondary Confirmation
- The Immediate group is being treated and moved first.
- Walking patients are separated from patients who cannot walk.
- The receiving facility has the count and the tag details.
| Finding | Success | Failure / Re-tag |
|---|---|---|
| Tag on each patient | One tag per patient, matched identifier | Missing or duplicate tag: tag now and log it |
| Immediate group | Treated and moved first | Immediate patient still waiting: escalate to the treatment lead |
| Walking patients | Minor, separated from the rest | Walking patient now cannot walk: re-triage as Immediate |
| Count | Colour totals match the headcount | Mismatch: recount and report to incident command |
Ongoing Monitoring
- Re-triage at every move, at the transport point and at the receiving facility
- Reassess the Immediate group's airway, breathing, bleeding and mental status at the protocol interval
- Update the count after every transport and every change in category
Troubleshooting
| Problem | Likely Cause | Fix |
|---|---|---|
| Too many Immediate tags | Single criterion used as the whole decision, or overtriage | Recheck each criterion; follow the protocol and escalate to medical command |
| Patient cannot follow a command | Language or hearing barrier, intoxication, head injury, confusion or distress | Use a nonverbal command per protocol; treat as Immediate until reassessed |
| No radial pulse | Shock, cold extremity or the wrong arm | Check the other arm and capillary refill; treat as Immediate per the criterion |
| Walking patient collapses | Initial Minor tag was wrong, or the injury is delayed | Re-triage at once and move the patient to the Immediate group |
| Not breathing after airway opening | Airway obstruction or a fatal injury | Reposition the airway once: still not breathing = Deceased/Expectant (black); breathing after repositioning = Immediate (red). Follow local protocol and medical command |
| Tag separated from patient | Tag not attached, or torn off in transport | Retag from the recorder's sheet, match the identifier and log it |
If the Sort Cannot Keep Up
- Call for resources: ask incident command for more units, staff and receiving capacity.
- Move the Immediate group: send transports in category order and report the count.
- Escalate expectant decisions: these belong to medical command under the local plan, not to the first responder.
Complications
| Complication | Recognition | Prevention | Management |
|---|---|---|---|
| Immediate: undertriage | Patient tagged Delayed or Minor deteriorates on transport or at the hospital | Use all checks; re-triage at each move | Retag now, move the patient, and notify the receiving team |
| Immediate: overtriage | Many Immediate tags with few life threats found on reassessment | Follow the criteria in order; avoid tagging on a single finding | Retag downward only after reassessment; report the count |
| Delayed: resources exhausted | Delayed patients wait too long and deteriorate | Reassess the Delayed group at set intervals | Escalate to incident command for more resources |
| Rescuer injury | Hazard not recognized on entry | Scene safety first; use PPE per protocol | Withdraw from the hazard and request support |
| Wrong patient or tag | Identifier does not match the patient | Attach the tag at the point of assessment; match the identifier | Reidentify the patient and log the correction |
One 2003 train-crash evaluation found that START overtriaged 79 of 148 patients and undertriaged 3. Overtriage drains resources. Undertriage delays life-saving care.
Special Populations
Pediatrics
- Use the pediatric algorithm: JumpSTART is for children younger than 8 years. Adult START thresholds don't fit young children.
- Breathing: In JumpSTART, a respiratory rate outside 15 to 45/min is Immediate. The adult cutoff of 30/min does not apply here.
- Perfusion: JumpSTART's perfusion check is simple. Is there a palpable pulse, yes or no?
- Mental status: JumpSTART asks about alertness, or whether the child responds to voice or pain. It skips the adult simple-commands test.
- Not breathing: reposition the airway. If the child is still apneic, check for a palpable pulse. No pulse: Expectant (black). Pulse present: give 5 rescue breaths. Breathing resumes: go to the respiratory-rate check. Still apneic: Expectant (black).
- Late hypotension: Children compensate with tachycardia and vasoconstriction. Their blood pressure drops late, so watch perfusion, capillary refill and mental status. Use the Pediatric Assessment Triangle to organize the look.
- Age cutoff: Your local protocol sets the line between JumpSTART and adult START. The CHEMM description used here gives only the under-8 limit.
Older Adults
- In the 2021 field triage guideline, a systolic BP below 110 mm Hg at age 65 y or older is high-risk. It may already mean shock.
- A low-level fall with significant head impact, in an adult 65 y or older, is an EMS judgment factor.
Pregnancy
- In the 2021 field triage guideline, pregnancy over 20 weeks is an EMS judgment factor for trauma-center destination.
- Tag by the same physiologic criteria. Notify the receiving obstetric service per local protocol.
Language and Communication Barriers
- Language, hearing or a cognitive barrier can stop a patient from following a verbal command. The perfusion and breathing checks still apply.
- Use a nonverbal command or a gesture per protocol, and record that method on the tag.
Post-Procedure Care & Transport
Immediate Aftercare
- Move the Immediate group first and keep the tag with the patient through every move.
- Treat and transport by category; do not hold an Immediate patient to finish the count.
Ongoing Maintenance
- Reassess tagged patients at each move and at protocol intervals.
- Keep the count by colour current for incident command.
Transport Considerations
- Vehicle load: load by category and destination, and record the tag numbers on each vehicle.
- Reassessment en route: monitor Immediate patients and re-triage on any change in breathing, perfusion or mental status.
- Destination: injured patients meeting field-triage criteria go to the destination named in the 2021 guideline (see Key Numbers); the MCI tag does not replace that decision.
Document & Hand Off
- Tag number, category, time and identifier for each patient
- Category count by colour and the vehicle or destination for each group
- Any change in category since triage, with time and reason
- Interventions done (bleeding control, airway, decompression) and response
- Hand-off to the receiving team by category, not by the first tag alone
Clinical Pearls & Pitfalls
Pearls
- Sort first, treat second: The sequence is what puts each patient in a category. Treatment comes after, and it follows that category.
- Walking patients are reassessed: START tags them Minor, and SALT assesses them last. Either way, a walker who deteriorates gets reassessed.
- Colours differ by system: A Japanese tag runs 0 to III, with colours. SALT uses named categories. Confirm which system is in use on the scene.
- Start with bleeding: SALT assesses obvious uncontrolled bleeding first. A bleeding patient is not sorted last.
Common Pitfalls
- Pitfall: one tag treated as final. Fix: re-triage at each move and at receiving facilities.
- Pitfall: mixing adult and pediatric thresholds. Fix: use JumpSTART for children younger than 8 years and adult START for older patients.
- Pitfall: using the trauma destination thresholds as the MCI tag. Fix: the 2021 field triage thresholds (respiratory rate below 10 or above 29/min; age-specific systolic BP) decide destination for injured patients; the MCI sequence decides order.
- Pitfall: finishing every assessment before treatment. Fix: stop the sort for the Immediate patient who needs bleeding control or an airway.
- Pitfall: treating every not-breathing patient the same. Fix: reposition the airway once; the result sets the tag, and local protocol and medical command govern expectant decisions.
Education & Skill Maintenance
Skill Maintenance
- Run a timed sort drill at least once per shift or per quarter, with a debrief of each miscategory.
- Practice the three checks (breathing, perfusion, mental status) on partners before a drill.
- Rehearse the count and hand-off with the receiving facility.
- Use virtual reality or low-fidelity simulation to rehearse the scene where live drills are limited.

References
- Lerner EB, Schwartz RB, Coule PL, Weinstein ES, Cone DC, Hunt RC, et al. Mass casualty triage: an evaluation of the data and development of a proposed national guideline. Disaster Med Public Health Prep. 2008;2(Suppl 1):S25-S34. https://doi.org/10.1097/DMP.0b013e318182194e
- Kahn CA, Schultz CH, Miller KT, Anderson CL. Does START triage work? An outcomes assessment after a disaster. Ann Emerg Med. 2009;54(3):424-430. https://doi.org/10.1016/j.annemergmed.2008.12.035
- Jenkins JL, McCarthy ML, Sauer LM, Green GB, Stuart S, Thomas TL, Hsu EB. Mass-casualty triage: time for an evidence-based approach. Prehosp Disaster Med. 2008;23(1):3-8. https://doi.org/10.1017/s1049023x00005471
- Stéfani GM, de Melo ME, Zardeto HN, Costa VSLP, Lima FS, Cola M. JumpSTART triage protocol in disaster pediatric patients: a systematic literature review. Prehosp Disaster Med. 2022;37(2):240-246. https://doi.org/10.1017/S1049023X22000127
- Kman N, Way D, Panchal AR, Patterson J, McGrath J, Danforth D, Mani A, Babbitt D, Hyde J, Pippin B, de Visser E, McVay J. Virtual reality simulation for assessment of hemorrhage control and SALT triage performance: a comparison of prehospital to in-hospital emergency responders. Prehosp Disaster Med. 2025;40(4):191-198. https://doi.org/10.1017/S1049023X25101349
- de Visser E, Way DP, Danforth D, McGrath J, Hyde J, Choy K, Audick J, Pippin B, Panchal AR, McVay J, Kman N. Field triage errors: a cross-sectional study of emergency responders in a virtual reality mass casualty simulation. Disaster Med Public Health Prep. 2025;20:e4. https://doi.org/10.1017/dmp.2025.10288
- Newgard CD, Fischer PE, Gestring M, et al. National guideline for the field triage of injured patients: recommendations of the National Expert Panel on Field Triage, 2021. J Trauma Acute Care Surg. 2022;93(2):e49-e60. https://doi.org/10.1097/TA.0000000000003627
- Office of the Assistant Secretary for Preparedness and Response (ASPR), Chemical Hazards Emergency Medical Management (CHEMM). JumpSTART Triage (incident primer, triage section). 2026; accessed October 2026. https://chemm.hhs.gov/incident-primer/triage/jumpstart-triage
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.