

At a Glance
- Represents
- The net direction of ventricular depolarization in the frontal plane, read from the limb-lead QRS.
- Normal (Adult)
- −30° to +90°; leads I and aVF both positive.
- Measure It
- Net QRS in lead I and aVF first, then lead II. If one lead is isoelectric, use the perpendicular lead.
- Abnormal → Think
- LAD (−30° to −90°): LAFB, LVH, inferior MI
- RAD (+90° to +180°): RVH, PE, LPFB
- Red Flags
- New extreme axis in a sick patient: VT or severe hyperkalemia until proven otherwise. Check lead placement first.
- Bedside Action
- Check the leads, compare with a prior ECG, repeat the 12-lead, and notify for a new extreme axis or ischemic symptoms.
Physiology & What It Represents
The cardiac (QRS) axis is the net direction the ventricles depolarize in the frontal plane. Follow the signal. It leaves the sinoatrial node, crosses the atria, and passes the atrioventricular node. Then it drops down the His bundle. The His bundle splits into the right bundle branch and the left bundle. The left bundle splits again, into anterior and posterior fascicles. Only then does the Purkinje network light up the ventricular myocardium.
The QRS vector points at the ventricular mass that depolarizes most. Aim toward a lead's positive pole and the QRS reads positive. Aim away and it reads negative. A lead at right angles to the vector sees an equiphasic, isoelectric complex. Limb leads sit at fixed angles on the hexaxial circle. Their polarities place the axis (Figure 1).

Three things move the axis: which ventricle is larger, which fascicle conducts first, and how many forces get lost. Ventricular hypertrophy changes ventricular mass. Infarction removes forces. Fascicular block or ventricular pacing reroutes activation.
Normal Values & How to Measure
| Parameter | Adult Normal | Pediatric Note | Where / How to Measure |
|---|---|---|---|
| Frontal QRS axis | −30° to +90° | Age-specific; rightward in the newborn period | Net QRS in leads I and aVF, then lead II |
| Lead I polarity | Positive | Positive in most ages | Net QRS (R plus S) in lead I |
| Lead aVF polarity | Positive; negative or isoelectric when the axis is 0° to −30° (upper-normal) | Age-specific | Net QRS in aVF |
- Confirm lead placement. P waves should be upright in I and II and negative in aVR. If they are not, check electrodes before reading the axis.
- Measure the net QRS (R plus S) in lead I, then in aVF. Do not use the tallest R alone.
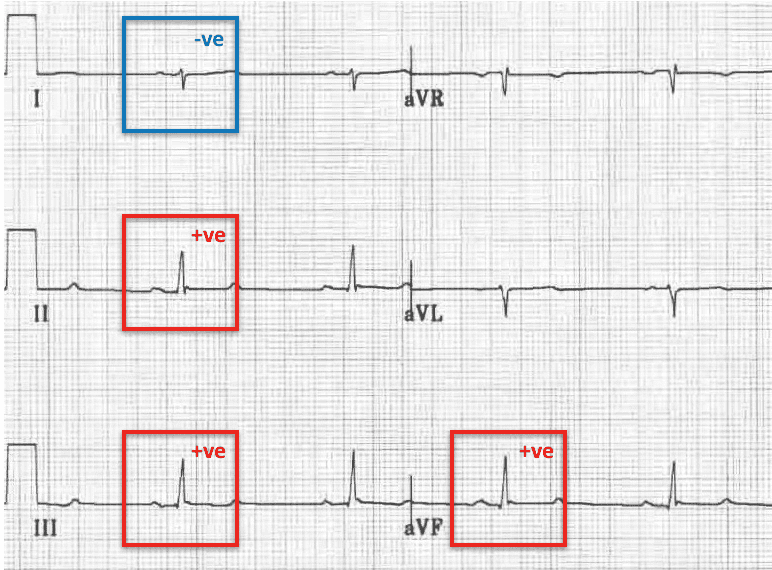
- Both I and aVF positive means a normal axis.
- I positive, aVF negative: check lead II. Positive II means upper-normal (0° to −30°). Negative II means LAD.
- I negative: aVF positive means RAD; aVF negative means an extreme axis.
- One isoelectric limb lead: the axis lies at right angles to it. Pick the direction with the neighboring lead.
- Use a typical beat or several beats in an irregular rhythm, and compare with a prior ECG.
| Zone | Degrees | Lead I | Lead II | aVF | Common Causes |
|---|---|---|---|---|---|
| Normal | −30° to +90° | Positive | Positive | Positive | Physiologic |
| Upper-normal (physiologic LAD) | 0° to −30° | Positive | Positive to equiphasic | Isoelectric to negative | Normal variant; body habitus, diaphragm elevation |
| Left axis deviation (LAD) | −30° to −90° | Positive | Negative | Negative | LAFB, LVH, inferior MI, LBBB, RV apical pacing |
| Right axis deviation (RAD) | +90° to +180° | Negative | Positive to equiphasic (negative beyond +150°) | Positive | RVH, acute right heart strain, LPFB, normal in children |
| Extreme (northwest) axis | −90° to ±180° | Negative | Negative | Negative | VT, severe hyperkalemia, lead reversal, unusual pacing sites |

Left Axis Deviation (LAD)
Left axis deviation puts the frontal axis between −30° and −90°. Lead I stays positive. aVF turns negative.
ECG Criteria
- Lead I: positive QRS.
- Lead aVF: negative QRS.
- Lead II: negative QRS. A positive lead II with a negative aVF is upper-normal, not LAD.
Causes
- Left anterior fascicular block (LAFB): the classic cause of marked LAD. The fascicular section covers it.
- Left ventricular hypertrophy (LVH): more left ventricular mass pulls the vector leftward.
- Inferior MI: lose the inferior forces and the axis drifts left.
- Left bundle branch block (LBBB): LAD often shows up with it.
- Right ventricular apical pacing: paced beats commonly point left.
Clinical Significance
- New LAD with inferior Q waves or ST changes? Work up ischemia (see the st-t-wave page).
- New LAD with RBBB suggests bifascicular block. Check the PR interval for AV block.
Look-Alikes
- Limb-lead reversal (LA/RA) can pass for LAD. See the Differential section.
Right Axis Deviation (RAD)
Right axis deviation puts the frontal axis between +90° and +180°. Lead I goes negative. aVF goes positive.
ECG Criteria
- Lead I: negative QRS.
- Lead aVF: positive QRS.
- Lead II: positive to equiphasic.
Causes
- Right ventricular hypertrophy (RVH): chronic lung disease, pulmonary hypertension and congenital right heart lesions all cause it. The voltage criteria live in the AHA/ACCF/HRS 2009 chamber-hypertrophy statement (Part V).
- Hyperinflated lungs (COPD): the lowered diaphragm can make the heart hang vertically and the axis swing right.
- Acute right heart strain: a large pulmonary embolism can drive RAD with sinus tachycardia.
- Left posterior fascicular block (LPFB): the fascicular section describes it. Make the call only after you exclude RVH, PE and lateral MI.
- Normal variant: children and thin young adults often carry a more vertical heart, and with it a rightward axis.
Clinical Significance
- New RAD with tachycardia, hypoxia or syncope? Think pulmonary embolism. S1Q3T3 and RAD support the diagnosis. They don't establish it (see Clinical Pearls). The 2019 ESC guideline grades PE risk on hemodynamics, right ventricular assessment and troponin, not on the ECG.
- RAD that matches a prior ECG is usually chronic. Compare before you act.
Extreme (Northwest) Axis
Any frontal axis from −90° to ±180° is the northwest, or extreme, axis. Lead I and aVF are both negative. It is almost never a normal finding.
Causes
- Ventricular tachycardia: an ectopic ventricular focus gives a wide QRS with an extreme axis. In a wide-complex tachycardia, a northwest axis points toward VT. It doesn't prove it. Run a wide-QRS algorithm.
- Severe hyperkalemia: a widened, bizarre QRS can drag the axis around. The progression is on the t-wave page.
- Sodium-channel blockade: drugs such as tricyclic antidepressants widen the QRS. In some cases the terminal QRS shifts right. That is a change in the terminal vector, not a northwest mean axis. A prospective study of 49 patients with tricyclic overdose found seizures with a QRS of 100 ms or more and ventricular arrhythmias with a QRS of 160 ms or more.
- Paced rhythms from unusual sites: pacing from non-standard sites can move the axis.
- Limb-lead reversal: a reversal can fake an extreme axis. Check the basics first.
Fascicular Blocks and the Axis
Fascicular blocks move the axis and barely widen the QRS. You diagnose LAFB from the QRS pattern, once other causes of left axis deviation, such as inferior MI, are excluded. LPFB is a diagnosis of exclusion. The criteria below come from the AHA/ACCF/HRS 2009 intraventricular conduction statement (Part III) and a 2007 review of hemiblocks.
Left anterior fascicular block (LAFB)
- Criteria: axis −45° to −90°; qR in aVL (R-wave peak time in aVL of 45 ms or more); rS in II, III and aVF; QRS <120 ms. Common finding: a small q in I.
- Causes: coronary disease (particularly anteroseptal MI), hypertension, cardiomyopathy and aortic disease.
- Clinical significance: LAFB gets more common with age. It can hide an infarct or fake one, so compare with a prior ECG before you call it new.
Left posterior fascicular block (LPFB)
- Criteria: axis above +90°; rS in I and aVL; qR in III and aVF; QRS <120 ms.
- Clinical significance: LPFB is a diagnosis of exclusion. Before anything else, rule out RVH, pulmonary embolism and lateral MI.
Bifascicular block
- RBBB with LAFB gives LAD with a wide QRS. The conduction-blocks page covers its AV-block risk.
Differential Diagnosis & Mimics
| Feature | Limb-lead reversal (LA/RA) | True RAD | VT (extreme axis) |
|---|---|---|---|
| Lead I | Inverted QRS and P wave | Negative QRS; upright P wave | Negative QRS; wide |
| P waves | Negative in I | Upright in I and II | May be dissociated from the QRS |
| QRS width | Normal | Normal | 120 ms or more |
| Next step | Correct the electrodes and repeat the 12-lead | Clinical context; compare with prior ECG | Treat as VT per protocol |
Artifact & Lead Misplacement
- LA/RA reversal: it inverts lead I, swaps aVR and aVL, and swaps II and III. Lead I can look like RAD. See the reversal figures below.
- Other reversal patterns: LA/LL, RA/LL and clockwise or anticlockwise rotation each move specific leads. Before you read the axis, find the lead that looks inverted or swapped.
- Motion, shivering or cable movement: these can build wide, bizarre complexes that pass for VT or an extreme axis.
- Precordial misplacement: it changes R-wave progression and leaves the frontal-plane axis alone.


Normal Variants
- A rightward axis can be normal in children and thin young adults.
- Expect an upper-normal leftward shift (0° to −30°) with obesity, pregnancy and diaphragm elevation. It is common.
Bedside Management & Escalation
A new axis rarely changes treatment on its own. It changes the next step.
- Extreme axis with a wide QRS: treat as VT until proven otherwise. Assess stability and follow the 2025 AHA adult ALS tachycardia algorithm for VT (Part 9) and local protocol (see the ventricular-rhythms page).
- Axis change with ischemic symptoms: repeat the 12-lead, add right-sided or posterior leads as indicated, and notify the receiving team (see the st-t-wave page).
- RAD with tachycardia, hypoxia or syncope: consider pulmonary embolism per local protocol and notify the ED or receiving team.
- Suspected hyperkalemia (wide QRS, bizarre axis): time-critical. Follow local protocol for IV calcium and other potassium-lowering therapy rather than waiting for a potassium level (see the 2025 AHA special circumstances guidance). Obtain a potassium level and notify. See the potassium lab value page.
- Wide QRS in suspected tricyclic overdose: follow local protocol (sodium bicarbonate) and notify poison control or medical direction.
Check lead placement and compare with a prior ECG. Do both before any of these steps.
Pediatric & Special Populations
Pediatrics
- The normal axis shifts with age. Use age-specific limits. The 2001 paediatric normal-limits study gives a limit for each age group.
- A rightward axis is normal in the newborn period and in young children. Check the age norm before you call RAD.
- Congenital heart disease commonly moves the axis. When RAD is new, compare with a prior ECG and refer for pediatric cardiology evaluation.
- In a child, left axis deviation or an extreme axis is usually abnormal, as with an AV canal defect or tricuspid atresia. Refer for pediatric cardiology evaluation.
Other Populations
- Older adults: LAFB gets more common with age. A new finding still needs a comparison with a prior ECG.
- Pregnancy: a raised diaphragm can move the axis toward upper-normal LAD.
- Pacemaker or ICD: the paced axis hangs on the lead site. Check it against the paced baseline. See the ventricular rhythms page.
Monitoring & Transport Considerations
| Issue | What to Do |
|---|---|
| Rhythm monitoring | Lead II shows P waves well. The axis itself needs a 12-lead. |
| Serial 12-leads | Repeat per local protocol (commonly every 15–30 minutes) in ongoing chest pain, or when the axis or QRS width changes. |
| Lead placement | Check electrodes after moving the patient. Confirm P waves are upright in I and II. |
| Artifact | Shivering, vibration and cable movement mimic axis change and wide QRS. Re-acquire the tracing. |
| Transmission | Transmit the 12-lead where allowed, and label the lead set. |
| Unstable brady or tachy patient | If transcutaneous pacing or defibrillation is likely, place anterior–posterior pads before moving the patient, per protocol (see the transcutaneous pacing page). |
| Paced patients | Note the pacing mode and compare with the paced baseline. |
Step-by-Step Approach & Pitfalls
- Confirm the lead set and electrodes. P waves should be upright in I and II and negative in aVR.
- Measure the net QRS in lead I, then in aVF.
- Both positive: the axis is normal.
- I positive, aVF negative: read lead II. Positive means upper-normal; negative means LAD.
- I negative: aVF positive means RAD; aVF negative means an extreme axis.
- Use the isoelectric lead to check borderline axes and to choose between two perpendicular options.
- Compare with a prior ECG. A new change matters more than a stable deviation.
Common Pitfalls
- Don't read the tallest R wave. Measure the net QRS.
- Don't call LAD off a reversed lead I. Check the P wave in I.
- Don't call pathologic LAD on an upper-normal axis.
- Don't miss VT in a wide-complex tachycardia with an extreme axis.
- Don't use RAD or S1Q3T3 alone to diagnose pulmonary embolism.
- Don't read an axis off a single irregular beat.
ECG Examples



Clinical Pearls
References
- Surawicz B, Childers R, Deal BJ, et al. AHA/ACCF/HRS recommendations for the standardization and interpretation of the electrocardiogram: part III: intraventricular conduction disturbances. Circulation. 2009;119(10):e235-e240. https://doi.org/10.1161/CIRCULATIONAHA.108.191095
- Kligfield P, et al. Recommendations for the standardization and interpretation of the electrocardiogram: part I: the electrocardiogram and its technology. Circulation. 2007;115:1306-1324. https://doi.org/10.1161/CIRCULATIONAHA.106.180200
- Hancock EW, et al. AHA/ACCF/HRS recommendations for the standardization and interpretation of the electrocardiogram: part V: electrocardiogram changes associated with cardiac chamber hypertrophy. J Am Coll Cardiol. 2009;53(11):992-1002. https://doi.org/10.1016/j.jacc.2008.12.015
- Elizari MV, Acunzo RS, Ferreiro M. Hemiblocks revisited. Circulation. 2007;115(9):1154-1163. https://doi.org/10.1161/CIRCULATIONAHA.106.637389
- Rijnbeek PR, Witsenburg M, Schrama E, Hess J, Kors JA. New normal limits for the paediatric electrocardiogram. Eur Heart J. 2001;22(8):702-711. https://doi.org/10.1053/euhj.2000.2399
- Konstantinides SV, Meyer G, Becattini C, et al. 2019 ESC Guidelines for the diagnosis and management of acute pulmonary embolism. Eur Heart J. 2020;41(4):543-603. https://doi.org/10.1093/eurheartj/ehz405
- Boehnert MT, Lovejoy FH Jr. Value of the QRS duration versus the serum drug level in predicting seizures and ventricular arrhythmias after an acute overdose of tricyclic antidepressants. N Engl J Med. 1985;313(8):474-479. https://doi.org/10.1056/NEJM198508223130804
- Brugada P, et al. A new approach to the differential diagnosis of a regular tachycardia with a wide QRS complex. Circulation. 1991;83(5):1649-1659. https://doi.org/10.1161/01.CIR.83.5.1649
- American Heart Association. Part 9: Adult Advanced Life Support: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16 suppl 2). https://doi.org/10.1161/cir.0000000000001376
- American Heart Association. Part 10: Adult and Pediatric Special Circumstances of Resuscitation: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16 suppl 2). https://doi.org/10.1161/cir.0000000000001380
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.