

At a Glance
- Pattern
- A wide-QRS tachycardia (QRS 120 ms or more, above 100/min): ventricular origin, aberrant SVT or pre-excited AF.
- Normal (Adult)
- QRS 110 ms or less; sinus rate 60–100 bpm; no tachycardia.
- Confirm It
- QRS in the widest lead; R-R regularity; AV relationship; the PR before each conducted beat.
- Abnormal → Think
- QRS 120 ms or more with tachycardia: VT until proven otherwise. Irregular and wide: pre-excited AF.
- Red Flags
- Hypotension, shock, ischemic chest pain or heart failure with a wide rhythm; torsades; pre-excited AF.
- Bedside Action
- Unstable: synchronized cardioversion (unsynchronized defibrillation for polymorphic VT or torsades). Stable regular: amiodarone 150 mg IV over 10 min or procainamide 20–50 mg/min to 17 mg/kg. Irregular: no AV nodal blockers.
Physiology & What It Represents
Wide-complex tachycardia means a QRS of 120 ms or more at a rate above 100/min. This page uses 100/min as its working line. The 2025 AHA Part 9 definition is generally a rate above 150/min with a QRS of 0.12 s or more. Its ACLS algorithm applies at 150/min or more. There are two ways the QRS ends up wide. In ventricular tachycardia (VT), the impulse starts in the ventricle and crawls from muscle cell to muscle cell. That is slower than conduction through the His–Purkinje system. In supraventricular tachycardia (SVT) with aberrancy, the impulse starts above the ventricles. It gets there by an abnormal route, such as through an existing bundle branch block or a rate-related one. A third mechanism is pre-excitation. An accessory pathway lets atrial impulses reach the ventricle without the AV node's delay. So the QRS width changes from beat to beat.
VT usually comes from scarred or ischemic muscle. That is why it is common after a myocardial infarction and in cardiomyopathy. The ventricles can beat without waiting for the atria. So atrioventricular (AV) dissociation is the most specific clue that the QRS starts in the ventricle.
Normal Values & How to Measure
Start with the widest lead, because its QRS width is the first thing that sorts these rhythms. Then check regularity and the AV relationship. Decide stability before any drug goes in.
| Parameter | Adult Normal | Pediatric Note | Where / How to Measure |
|---|---|---|---|
| QRS duration | 110 ms or less (0.11 s; under 3 small boxes) | Compare with age-based norms; PALS calls a QRS over 0.09 s wide | Widest lead; from QRS onset to return to baseline |
| Sinus rate | 60–100 bpm | Higher in infants and young children; see Vital Signs | Count R waves over 6 s and multiply by 10 |
| PR interval (sinus) | 120–200 ms (0.12–0.20 s; 3–5 small boxes) | Shorter in infants | P-wave onset to QRS onset; a short PR with a delta wave suggests WPW |
| Ventricular tachycardia | Three or more consecutive ventricular beats above 100/min | Same definition | Sustained if 30 s or longer, or needs intervention |
- Select the widest lead, usually II, V1 or V5. Use V1 and aVR for the morphology steps.
- Measure the QRS from onset to end in ms (one small box is 40 ms); 110–119 ms is borderline.
- Check the R-R intervals across at least three beats to decide whether the rhythm is regular.
- Look for P waves before each QRS, and for capture and fusion beats that show AV dissociation.
- Assess stability before choosing an algorithm; an unstable patient is treated first.
Ventricular Tachycardia (VT)
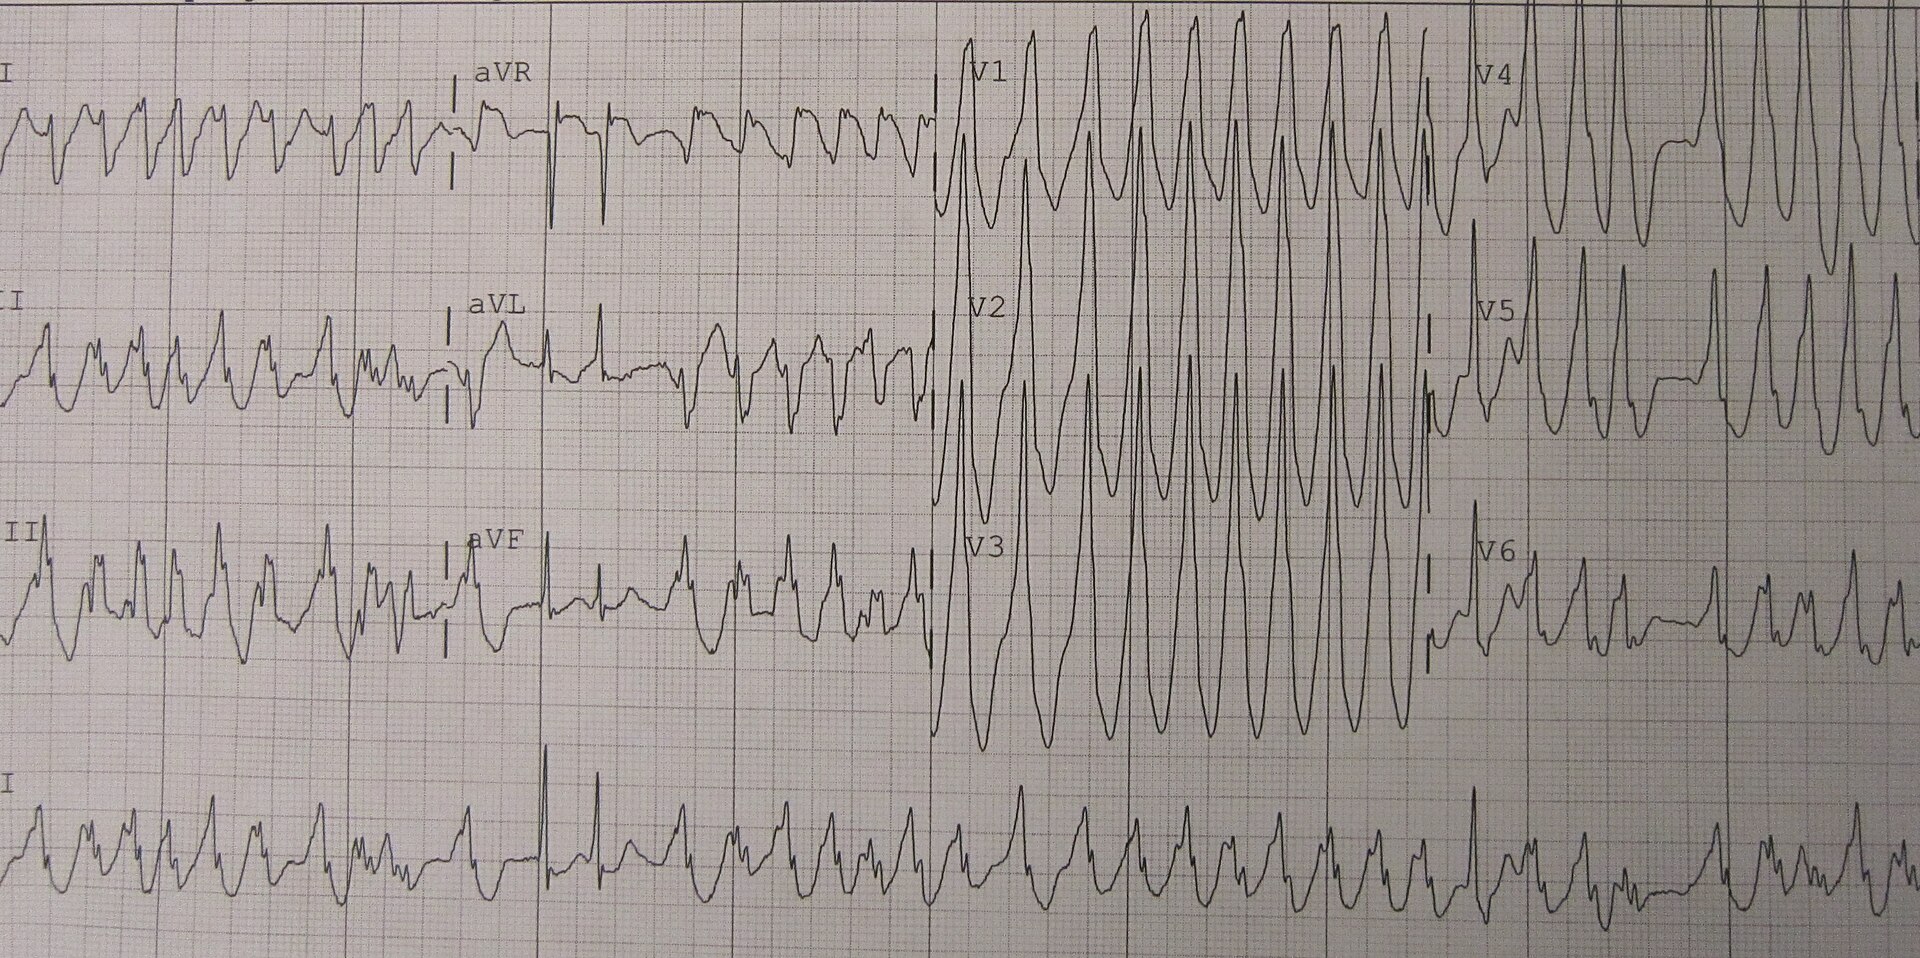
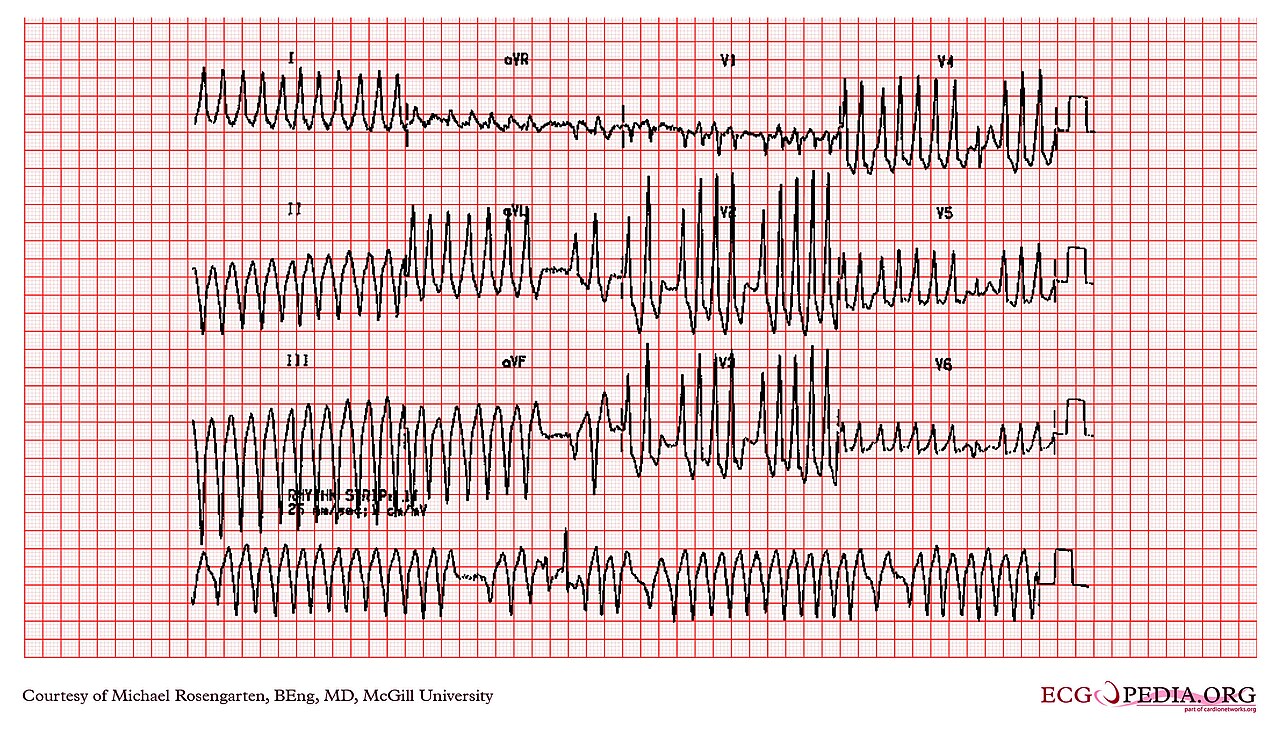
Three or more consecutive ventricular beats above 100/min is VT. It counts as sustained if it lasts 30 seconds or longer, or if it needs intervention. Monomorphic VT has one QRS shape. Polymorphic VT and torsades de pointes change shape and axis. They get their own lesson on the Ventricular Rhythms page.
ECG Criteria
- QRS: 120 ms or more, usually bizarre compared with the patient's sinus beats
- AV dissociation: P waves march through at their own rate and do not match the QRS
- Capture and fusion beats: A narrow QRS inside the wide run (capture) or a QRS that merges two shapes (fusion) favors VT
- Precordial pattern: No RS complex in any precordial lead (V1–V6) is highly specific for VT in the Brugada algorithm
- Concordance: All precordial QRS complexes (V1–V6) are positive, or all are negative; this favors VT
- Extreme axis: A northwest axis (between −90° and ±180°) favors VT
- Very wide QRS: Over 160 ms favors VT, especially with a bundle branch pattern
Causes
- Ischemia or prior myocardial infarction (scar-related re-entry), including acute ischemia
- Cardiomyopathy, structural heart disease and heart failure
- Electrolyte disturbance: hypokalemia, hypomagnesemia and hyperkalemia
- Drugs and toxins: class I antiarrhythmics, tricyclic antidepressants and other sodium-channel blockers, and digoxin toxicity
Clinical Significance
- Sustained VT with a pulse can deteriorate to ventricular fibrillation. It can also cause hypotension, heart failure or shock
- Heart disease changes the picture. Non-sustained VT in that patient needs evaluation for ischemia, scar and cardiomyopathy
- When the rhythm is uncertain, treat it as VT. Treating SVT as VT usually costs less than missing VT
SVT With Aberrancy
In SVT with aberrancy, a supraventricular impulse takes an abnormal path to the ventricles. The QRS widens only for as long as the aberration lasts. Rate-related aberrancy (Ashman phenomenon) shows up at fast rates or after a long pause. It is a bundle branch pattern that disappears at slower rates. How SVT itself works is taught on the Atrial Rhythms page.
ECG Criteria
- P waves: An atrial activity pattern that is related to each QRS, or a regular 1:1 atrial rhythm you can follow through the wide complexes
- QRS morphology: Usually resembles a bundle branch block, often without the bizarre shape of VT
- Comparison: An old ECG, or a slower strip with the same QRS, shows whether the width is rate-related
Causes
- AV nodal re-entrant tachycardia (AVNRT) or AV re-entrant tachycardia (AVRT) with a pre-existing bundle branch block
- Atrial fibrillation or flutter with a rapid ventricular response and a pre-existing bundle branch block
- Rate-related aberrancy after a long pause, or a pre-existing bundle branch block that becomes wider at fast rates
Clinical Significance
- A known bundle branch block is the classic trap. That wide QRS can be aberrant SVT. It can also be VT. Compare with an old ECG
- Adenosine can slow or stop the rhythm and show the atrial activity. If the rhythm does not change, manage it as VT. Stopping the rhythm does not rule out adenosine-sensitive VT. Review the 12-lead after any change
Pre-Excited Atrial Fibrillation (AF)
Pre-excited atrial fibrillation means atrial impulses reach the ventricles two ways: over an accessory pathway and through the AV node. The pathway does not slow conduction the way the node does. So many impulses can arrive at the ventricle very quickly. Each impulse fuses differently with the node pathway, so the QRS width and shape change from beat to beat. AF itself is taught on the Atrial Rhythms page. The delta wave lives on the PR Interval page.
ECG Criteria
- Rhythm: Irregular, with R-R intervals that vary
- QRS: Wide, with a width and shape that vary from beat to beat; the rate is often very fast
- Baseline clue: A short PR interval with a delta wave on a sinus ECG suggests an accessory pathway (see PR Interval)
Causes
- Wolff-Parkinson-White syndrome or another accessory pathway
- Any AF trigger in a patient with a known accessory pathway
Clinical Significance
- Very fast conduction over an accessory pathway can degenerate into ventricular fibrillation. That is why AV nodal blockers are dangerous
- Catheter ablation of the accessory pathway is the definitive treatment (2023 ACC/AHA/ACCP/HRS AF guideline, Class 1)
Differential Diagnosis & Mimics
Rhythm by Type
| Rhythm | Rate (bpm) | Regularity | P Waves | PR | QRS | First-Line Action |
|---|---|---|---|---|---|---|
| Monomorphic VT | Above 100 | Regular | Dissociated from QRS; capture or fusion beats | None; no fixed relation | 120 ms or more; bizarre | Stable: amiodarone or procainamide. Unstable: synchronized cardioversion |
| SVT with aberrancy | Above 100 | Regular | Fixed PR to each QRS, or a clear 1:1 atrial rhythm | Fixed when P waves are seen | 120 ms or more; bundle branch pattern | Stable: vagal maneuvers. Adenosine only if SVT with aberrancy is likely and a defibrillator is ready. If no change, treat as VT |
| Pre-excited AF | Often very fast | Irregular | No organized P waves | None | Wide; width and shape vary beat to beat | Unstable: synchronized cardioversion. Stable: procainamide or ibutilide. Never AV nodal blockers |
| Polymorphic VT or torsades | Fast | Irregular or variable | Usually dissociated | None | Wide; amplitude and axis twist | Pulseless: defibrillate. Unstable with a pulse: unsynchronized defibrillation, never synchronized cardioversion. Stable torsades: magnesium sulfate and QT review. Stable polymorphic VT with a normal QT: look for ischemia and electrolyte problems, correct them, and involve cardiology |
| Hyperkalemia or sodium-channel toxicity | Variable; sinus tachycardia is common in TCA toxicity; sine-wave in severe hyperkalemia | Regular | Flattened or absent P waves | Prolonged (hyperkalemia) | Wide and slurred | Treat the cause: sodium bicarbonate for sodium-channel toxicity, calcium for hyperkalemia (dosing in the linked pages). Do not give procainamide or other class I agents |
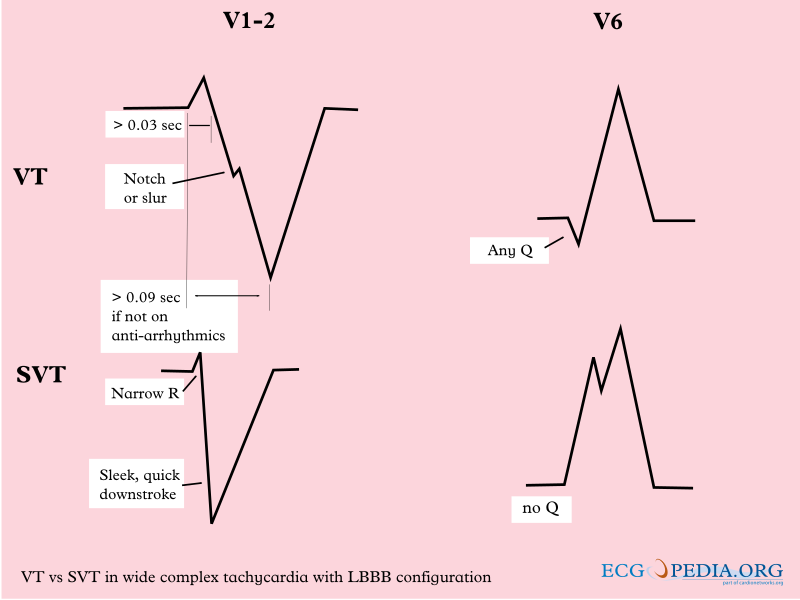
Two published algorithms split VT from SVT with aberrancy by QRS shape. Both are sensitive. Neither is specific. When the diagnosis is uncertain, a VT call is the safer default.
Brugada Algorithm (1991)
- Step 1: No RS complex in any precordial lead (V1–V6): VT
- Step 2: RS interval longer than 100 ms in any precordial lead: VT
- Step 3: AV dissociation: VT
- Step 4: Morphology criteria in V1 and V6: VT if met; if none apply, SVT with aberrancy. Use the exact criteria in the 1991 paper
Vereckei aVR Algorithm (2008)
- Step 1: Initial R wave in lead aVR: VT
- Step 2: Initial r or q wave wider than 40 ms: VT
- Step 3: Notch on the initial downstroke of a predominantly negative QRS in aVR: VT
- Step 4: Ventricular activation-velocity ratio (initial versus terminal 40 ms) above 1 suggests SVT; 1 or less suggests VT
Accuracy
| Algorithm | Pooled Sensitivity | Pooled Specificity |
|---|---|---|
| Brugada (1991) | 90.25% | 64.02% |
| Vereckei aVR (2008) | 90.35% | 60.88% |
| Vereckei-pre (earlier Vereckei algorithm) | 94.80% | 75.40% |
| R-wave peak time, lead II (RWPT-II) | 78.15% | 88.30% |
A 2023 meta-analysis of 14 studies (3,966 patients) found high sensitivity at 88.89% overall. Specificity was moderate, at 70.55%. RWPT-II had the highest pooled specificity (88.30%) and the lowest sensitivity (78.15%). The authors suggest the Brugada or Vereckei aVR algorithm, combined with RWPT-II, could be considered. These are pooled secondary-analysis figures. They are not guidance for a single patient.
VT Versus SVT With Aberrancy Versus Pre-Excited AF
| Feature | VT | SVT With Aberrancy | Pre-Excited AF |
|---|---|---|---|
| Rhythm | Regular (monomorphic) | Regular | Irregular |
| AV relationship | Dissociated; capture or fusion beats | Fixed P-QRS relation | No organized P waves |
| Precordial pattern | No RS in V1–V6; concordant pattern | Typical bundle branch pattern | Width varies; short PR baseline on sinus ECG |
| Response to adenosine | Usually no change in the ventricular rhythm | May terminate or reveal the atrial rhythm | Harmful: can accelerate conduction over the pathway |
Mimics
- Hyperkalemia and sodium-channel blockade: They produce a wide QRS from a different cause. Treat the cause (see QRS Complex and T Wave). An antiarrhythmic is not the answer
- Torsades de pointes: polymorphic VT with a long QT interval; see QT Interval
- Paced rhythm: a wide QRS with a left bundle pattern is what pacing produces. Look for pacing spikes and the device history
Artifact & Lead Misplacement
- Tremor, shivering or transport vibration: It can mimic VT or ventricular fibrillation. Confirm with a second lead or a pulse check
- Limb lead reversal: It changes lead I and aVR. That matters for the Vereckei steps
- Precordial misplacement: Electrodes placed high on V1 or V2 change the precordial pattern. The Brugada steps read that pattern
Bedside Management & Escalation
The doses below come from the 2025 AHA ACLS tachyarrhythmia algorithm. They line up with the linked medication and intervention pages.
| Situation | BLS (EMT) | ALS (AEMT / Paramedic / RN) | Critical Care / Transport |
|---|---|---|---|
| Unstable (hypotension, altered mental status, ischemic chest pain, shock, heart failure) | Oxygen if SpO₂ under 94%; monitor; 12-lead if available; call ALS early | Synchronized cardioversion per the dosing table; unsynchronized defibrillation for polymorphic VT or torsades; pads on before the shock | Continuous monitoring with pads on; cardioversion per the dosing table; expect deterioration to ventricular fibrillation |
| Stable regular, monomorphic (presumed VT) | Monitor; 12-lead; transport | IV amiodarone, procainamide or sotalol may be considered (2025 AHA Part 9, WCT rec 3, COR 2b, B-R); amiodarone or procainamide per the dosing table (guidelines differ on the first drug; sotalol dosing is not in this table, so use protocol or expert input); adenosine only if SVT with aberrancy is likely and a defibrillator is ready | Amiodarone 1 mg/min for 6 h after the bolus, or procainamide infusion (dosing table); cardiology or electrophysiology input |
| Stable irregular (possible pre-excited AF) | Monitor; 12-lead; transport | No AV nodal blockers. Procainamide infusion (dosing table) or ibutilide; cardioversion if drugs fail | Electrophysiology review; plan for catheter ablation |
| Pulseless (VT or ventricular fibrillation) | CPR and AED per the BLS sequence | Defibrillate and run the cardiac arrest algorithm | Arrest algorithm; treat reversible causes |
| Therapy | Adult | Pediatric | Key Notes |
|---|---|---|---|
| Amiodarone | 150 mg IV over 10 min, repeat if VT recurs; then 1 mg/min infusion for the first 6 hours (2025 AHA Part 9, ACLS algorithm); max initial rate 30 mg/min | Stable regular wide-complex tachycardia: 5 mg/kg IV/IO over 10 min, max 150 mg (NASEMSO v3.0, Tachycardia with a Pulse, p. 44; adenosine first if SVT with aberrancy is likely). Pulseless VF or pVT only: 5 mg/kg IV/IO bolus, max 300 mg (2025 PALS cardiac arrest algorithm) | High-alert Stable VT only. Not for torsades; not for pre-excited AF (AV nodal blocker harm). Do not add procainamide without expert input |
| Procainamide | Stable monomorphic VT or wide-complex tachycardia: infuse at 20 mg/min (urgent use up to 50 mg/min per AHA), stop when suppressed, hypotensive, QRS widens over 50%, or at 17 mg/kg (AHA VT maximum). Pre-excited AF (off-label; protocol-dependent): label loading infusion of 500–600 mg at 20 mg/min over 25–30 min, label maximum 1 g | 15 mg/kg IV/IO over 30–60 min (2020 AHA PALS tachyarrhythmia algorithm dose, Topjian 2020 Part 4; the 2025 PALS algorithm lists no procainamide dose and the label does not establish pediatric use); specialist or expert-consult use only. NASEMSO v3.0 gives no pediatric dose, and 2025 AHA Part 8 (WCT) gives no support for or against specific antiarrhythmic drugs | High-alert Avoid if prolonged QT or heart failure. Avoid combining with amiodarone, ibutilide or other QT-prolonging drugs unless expert input is available. Pediatric safety is not established in labeling. Pre-excited AF dosing is off-label; follow protocol. Differs from FDA label: the label loading infusion is 20 mg/min to a 1 g maximum; AHA 2025 allows 20–50 mg/min to 17 mg/kg (about 1.2 g at 70 kg). |
| Adenosine | 6 mg rapid IV push, then 12 mg if needed, max 12 mg/dose | 0.1 mg/kg rapid IV/IO push (max 6 mg), then 0.2 mg/kg (max 12 mg), SVT dosing | Stable, regular, monomorphic wide-complex tachycardia only, when SVT with aberrancy is likely or the cause is unclear (2025 AHA Part 9, WCT rec 4, COR 2b); defibrillator ready. Harm (COR 3) when unstable, irregularly irregular or polymorphic (rec 6). Never for an irregular wide-complex tachycardia or suspected pre-excited AF. Avoid after MI, with scar or cardiomyopathy, or when VT is likely: it can cause hypotension or deterioration. Contraindicated with 2nd- or 3rd-degree AV block and sick sinus syndrome unless paced; avoid in asthma (2025 AHA Part 9 lists asthma as a contraindication because of bronchospasm; the label says use caution). Dipyridamole potentiates it (label: smaller doses may be effective); caffeine and theophylline antagonize it; carbamazepine can deepen heart block; ventricular fibrillation has been reported when given with digoxin |
| Synchronized cardioversion | Unstable wide-complex tachycardia with a pulse: synchronized cardioversion (2025 AHA Part 9, WCT rec 1, COR 1), at the device-recommended energy or the maximum setting if unknown. Unstable pre-excited AF: use the AF cardioversion energy, an initial biphasic setting of at least 200 J synchronized (2025 AHA Part 9, AF rec 3, COR 2a, general AF recommendation), increased if the first shock fails | 0.5–1 J/kg, then 2 J/kg if the first shock fails | Confirm the sync marker on every R wave before the shock. Sedate an awake patient before the shock where time allows. Pulseless rhythm needs defibrillation, not cardioversion |
| Magnesium sulfate | Torsades de pointes: 2 g IV, diluted, over about 15 min, repeat if episodes persist | 25–50 mg/kg IV/IO, max 2 g per dose | High-alert Give for torsades whatever the serum level. Does not help polymorphic VT with a normal QT. Monitor BP, reflexes and respiration; reduce the dose in renal failure; calcium is the antidote for toxicity |
Hyperkalemia and sodium-channel toxicity: Go after the cause. For tricyclic-type toxicity with QRS widening, the first-line antidote is sodium bicarbonate: 50–150 mEq IV bolus for adult TCA or tetracyclic cardiotoxicity (2025 AHA Part 10, COR 1, B-NR). For children, 1–3 mEq/kg, and never above the adult dose (see Sodium Bicarbonate). In hyperkalemia, calcium steadies the myocardium while potassium is shifted (see Calcium Chloride and Insulin).
The dosing here comes from the 2025 AHA ACLS tachyarrhythmia algorithm and the linked pages.
Pediatric & Special Populations
Pediatrics
- Infant and child SVT: Infant SVT is usually above 220 bpm. Child SVT is usually above 180 bpm. A wide complex in a child can be SVT with aberrancy. If perfusion is poor or the rhythm is uncertain, treat it as VT with synchronized cardioversion. PALS calls a QRS over 0.09 s wide
- Pediatric VT: Uncommon. It is usually linked to congenital heart disease, cardiomyopathy or a channelopathy. An expert should review the rhythm
- Cardiopulmonary compromise: Unstable: synchronized cardioversion (0.5–1 J/kg, then 2 J/kg if the first shock fails). Stable with a regular, monomorphic QRS: adenosine can be useful with expert consultation (2025 AHA Part 8, WCT rec 2, COR 2a). Watch a running rhythm strip, with cardioversion kept ready. Never for an irregular QRS
- Congenital heart disease: After surgical repair, wide-complex rhythms are common. Pull the surgical history. Check for epicardial pacing wires and look at the atrial rhythm
- Dosing: Weight-based doses follow the Weight-Based Dosing
Other Populations
- Pregnancy: Unstable: shock promptly. In cardiac arrest, fetal monitoring should not delay defibrillation (2025 AHA Part 10, pregnant patients, supportive text). Stable: correct magnesium and potassium. If the patient progresses to cardiac arrest with the fundal height at or above the umbilicus, give manual left lateral uterine displacement with compressions (2025 AHA Part 10, pregnant patients rec 4, COR 1, LOE C-LD). Remove the fetal monitors. They should not be used during arrest (rec 9, No Benefit). Amiodarone can cause fetal thyroid and neurodevelopmental effects (label). Weigh that against VT treatment with expert input
- Heart transplant recipients: The denervated heart responds unusually to adenosine, and the effects may be profound. The 2025 AHA Part 9 (NCT section) notes that 1 mg IV may be enough to terminate the rhythm. Start low and titrate per the Adenosine page
- Older adults and structural heart disease: Ischemia and scar are common causes. A new wide QRS needs a 12-lead and serial ECGs
- Pacemaker or ICD: Paced beats and device therapy can produce wide complexes. Ask for device interrogation. Review the shock history before you give an antiarrhythmic
Monitoring & Transport Considerations
| Issue | What to Do |
|---|---|
| Monitoring lead | Lead II for atrial activity; V1 or MCL1 for QRS shape and the Brugada steps |
| Serial 12-leads | Repeat after cardioversion, after each antiarrhythmic and after any change in rhythm |
| Artifact | Confirm with a second lead and a pulse check before you treat a wide complex as VT |
| Pacing and defibrillation pads | Apply anterior–posterior pads before moving an unstable patient |
| Cardioversion | Confirm the synchronization marker on every R wave before each shock |
| Reassessment | Recheck the pulse and rhythm after every drug, shock or transfer |
| Transport | Hand off the rhythm strips, drug times and any cardioversion history |
Step-by-Step Approach & Pitfalls
- Decide whether the patient is stable or unstable before reading the strip in detail.
- Measure the QRS in the widest lead and confirm it is 120 ms or more.
- Check regularity. A wide and irregular rhythm is pre-excited AF until proven otherwise.
- Look for AV dissociation, capture beats and fusion beats.
- For a regular rhythm, apply the Brugada precordial steps and the Vereckei aVR steps.
- Treat by the stability row in the bedside table. Never give an AV nodal blocker to an irregular rhythm.
- Reassess after each drug and cardioversion: recheck the 12-lead, the pulse and the rhythm.
Common Pitfalls
- Calling a wide complex SVT because the patient has a known bundle branch block, without an old ECG for comparison
- Giving adenosine to an irregular wide-complex rhythm
- Calling a paced rhythm VT or SVT without checking the pacing history
- Treating electrical activity on the monitor as a perfusing rhythm when there is no pulse
- Using QRS width alone; the algorithms need the AV relationship and the precordial pattern
- Stacking antiarrhythmics such as amiodarone and procainamide without expert input
ECG Examples
Clinical Pearls
References
- Brugada P, Brugada J, Mont L, Smeets J, Andries EW. A new approach to the differential diagnosis of a regular tachycardia with a wide QRS complex. Circulation. 1991;83(5):1649-1659. (landmark derivation study) https://doi.org/10.1161/01.cir.83.5.1649
- Vereckei A, Duray G, Szénási G, Altemose GT, Miller JM. New algorithm using only lead aVR for differential diagnosis of wide QRS complex tachycardia. Heart Rhythm. 2008;5(1):89-98. https://doi.org/10.1016/j.hrthm.2007.09.020
- Sun X, Teng Y, Mu S, Wang Y, Chen H. Diagnostic accuracy of different ECG-based algorithms in wide QRS complex tachycardia: a systematic review and meta-analysis. BMJ Open. 2023;13(7):e069273. https://doi.org/10.1136/bmjopen-2022-069273
- Joglar JA, Chung MK, Armbruster AL, et al. 2023 ACC/AHA/ACCP/HRS Guideline for the Diagnosis and Management of Atrial Fibrillation. Circulation. 2024;149(1):e1-e156. https://doi.org/10.1161/CIR.0000000000001193
- Wigginton JG, Agarwal S, Bartos JA, Coute RA, et al. Part 9: Adult Advanced Life Support: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16 suppl 2):S538-S577. https://doi.org/10.1161/CIR.0000000000001376
- Lasa JJ, Dhillon GS, Duff JP, et al. Part 8: Pediatric Advanced Life Support: 2025 American Heart Association and American Academy of Pediatrics Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025. https://doi.org/10.1161/CIR.0000000000001368
- Zeppenfeld K, Tfelt-Hansen J, de Riva M, et al. 2022 ESC Guidelines for the management of patients with ventricular arrhythmias and the prevention of sudden cardiac death. Eur Heart J. 2022;43(40):3997-4126. https://doi.org/10.1093/eurheartj/ehac262
- Adenosine injection, US prescribing information (Sagent Pharmaceuticals). DailyMed. Accessed October 14, 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=546642f2-662f-46cf-9d82-5bb3bdcc7677
- Procainamide hydrochloride injection, US prescribing information (Hospira). DailyMed. Accessed October 14, 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=17e47845-daad-434c-a784-6d3875b0d704
- Cao D, Arens AM, Chow SL, Easter SR, Hoffman RS, Lagina AT III, Lavonas EJ, Patil KD, Sutherland LD, Tijssen JA, Wang GS, Zelop CM, Rodriguez AJ, Drennan IR, McBride ME. Part 10: Adult and Pediatric Special Circumstances of Resuscitation: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(suppl 2):S578–S672. https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/adult-and-pediatric-special-circumstances-of-resuscitation
- National Association of State EMS Officials. NASEMSO National Model EMS Clinical Guidelines, Version 3.0. March 2022. Cardiovascular: Tachycardia with a Pulse, pp. 43–45. Accessed October 15, 2026. https://nasemso.org/docs.ashx?id=1444322
- Topjian AA, Raymond TT, Atkins D, Chan M, Duff JP, Joyner BL Jr, Lasa JJ, Lavonas EJ, Levy A, Mahgoub M, Meckler GD, Roberts KE, Sutton RM, Schexnayder SM; Pediatric Basic and Advanced Life Support Collaborators. Part 4: Pediatric Basic and Advanced Life Support: 2020 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2020;142(16 suppl 2):S469–S523. https://doi.org/10.1161/CIR.0000000000000901
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.