

Bedside Snapshot
- Use It For
- Mild to moderate heart failure (adults, with a diuretic and ACE inhibitor); chronic AF rate control; pediatric heart failure. Acute AF rate control is off-label
- Adult Dose
- Load: 8–12 mcg/kg IV total, in stages (half, then ¼ every 6–8 h ×2)
- Maintenance: 2.4–3.6 mcg/kg/day IV; tablets 62.5–500 mcg daily (lean weight, CrCl)
- AF with RVR: protocol-specific; label has no acute schedule
- Pediatric Dose
- IV load 15–50 mcg/kg by age (highest 1–24 months); maintenance twice daily by age. AF rate control not established in children
- Onset / Duration
- IV: onset 5–30 min, peak 1–4 h; PO: onset 0.5–2 h, peak 2–6 h; effects last days
- Do Not Give / Hold If
- Ventricular fibrillation; digoxin hypersensitivity; pre-excited AF. Hold for toxicity signs, level above 2.0 ng/mL, potassium above 5.5 mEq/L with toxicity, or new high-grade AV block
- Watch For
- Bradycardia and AV block; bidirectional VT and VF; hyperkalemia after large ingestion; anorexia, nausea, yellow-green vision
- Reversal / Rescue
- Digoxin immune Fab (DigiFab) IV: 20 vials for unknown acute amount (10, then 10); 6 vials chronic (1 vial under 20 kg). Atropine, pacing and lidocaine bridge (phenytoin a further option); dialysis does not help
- Must Remember
- Toxicity occurs at 'therapeutic' levels with low K⁺ or Mg²⁺, high Ca²⁺ or renal failure. Treat the rhythm and K⁺ first; do not delay Fab for the level
Indications
Emergency & Prehospital
- AF with rapid ventricular response: The 2023 ACC/AHA AF guideline gives it a 2a recommendation when beta blockers and nondihydropyridine calcium channel blockers fail or are contraindicated. Never use it in pre-excited AF (see Contraindications).
ED / ICU / Transport
- Heart failure, mild to moderate (adults): It raises ejection fraction and improves symptoms and heart failure hospitalizations. It does not change mortality. Pair it with a diuretic and an ACE inhibitor where possible.
- Chronic AF rate control: the labelled AF indication. The 2023 AF guideline also calls digoxin reasonable for long-term rate control, alongside other agents or alone when others are not preferred, not tolerated or contraindicated. The setting is AF with HF symptoms.
- Pediatric heart failure: It raises myocardial contractility. Efficacy in controlled pediatric trials is not established.
Other Uses
- Pediatric AF rate control: Safety and effectiveness are not established. Specialist use only.
- Pregnancy with persistent AF: The 2023 AF guideline lists it as a rate-control option. Digoxin-like immunoreactive substances can make serum levels unreliable in pregnancy.
Dosing & Administration
Doses vary by protocol; follow local protocols and medical direction.
Available Forms
- Injection, adult: 250 mcg/mL; 500 mcg per 2 mL single-dose ampule or vial
- Injection, pediatric: 100 mcg/mL single-dose ampule or vial
- Tablets: 62.5, 125 and 250 mcg (oral)
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| Heart failure or AF: IV load | 8–12 mcg/kg IV, total load: half first, then ¼ every 6–8 h, two more doses | No fixed max: reassess before each dose | Give over 5 min or longer; no bolus. Label does not state the weight basis for the load |
| Heart failure or AF: IV maintenance | 2.4–3.6 mcg/kg/day IV, once daily (starting dose, normal renal function) | Table 3 maximum by lean weight and CrCl; adjust every 2 weeks | Lean body weight governs maintenance; reduce if lean weight is a small fraction of total mass (obesity or edema) |
| Heart failure or AF: oral load | 10–15 mcg/kg PO, total load: half first, then ¼ every 6–8 h, two more doses | No fixed max: reassess before each dose | Oral bioavailability 60–80%; IV 100% |
| Heart failure or AF: oral maintenance | 62.5–500 mcg PO once daily | Table 3 maximum 500 mcg/day; adjust every 2 weeks | Tablets 62.5, 125 and 250 mcg. Table 3 is the basis; start at the lower end when CrCl is reduced |
| AF with RVR, acute | Protocol-specific; the label gives no acute bolus schedule | No fixed max stated: titrate to effect and watch for toxicity | Only when beta blockers and nondihydropyridine calcium channel blockers are ineffective or contraindicated; contraindicated in pre-excited AF |
Pediatric Dosing
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| Heart failure: IV load, premature | 15–25 mcg/kg IV total (half first, then ¼ every 6–8 h ×2) | No fixed max: titrate to effect | Most sensitive group; individualize by maturity |
| Heart failure: IV load, full-term newborn | 20–30 mcg/kg IV total (same schedule) | No fixed max: titrate to effect | Neonates vary widely in tolerance |
| Heart failure: IV load, 1–24 months | 30–50 mcg/kg IV total (same schedule) | No fixed max: titrate to effect | Measure carefully; the adult vial is 250 mcg/mL, the pediatric vial 100 mcg/mL |
| Heart failure: IV load, 2–5 years | 25–35 mcg/kg IV total (same schedule) | No fixed max: titrate to effect | IM route, if used: no more than 200 mcg per site |
| Heart failure: IV load, 5–10 years | 15–30 mcg/kg IV total (same schedule) | No fixed max: titrate to effect | Oral load 20–45 mcg/kg PO total for 5–10 years |
| Heart failure: IV load, above 10 years | 8–12 mcg/kg IV total; use the adult table | As adult | Adult rules apply above age 10 years; ages 5–10 use the pediatric rows |
| Heart failure: IV maintenance under 10 years | Twice daily, mcg/kg per dose: premature 1.9–3.1; full-term 3–4.5; 1–24 mo 4.5–7.5; 2–5 y 3.8–5.3; 5–10 y 2.3–4.5 | Table 5 by age, lean weight and CrCl; no fixed max | Assumes normal renal function; adjust for CrCl |
| Heart failure: oral maintenance, 5–10 years | 3.2–6.4 mcg/kg per dose PO, twice daily | Table 5 by lean weight and CrCl | Oral dosing is labelled for ages 5–10 years in this range |
| AF rate control in children | Not established in children | Not established | Specialist use only |
Preparation & Administration
- Dilution: give it undiluted, or dilute it with at least 4 times the volume of sterile water, 0.9% sodium chloride or 5% dextrose. Less dilution can precipitate digoxin. Use it immediately.
- Push rate: give IV over 5 minutes or longer; avoid bolus
- Line: do not mix with other drugs or give in the same line at the same time; use a dedicated line where possible
- IM: inject deep and massage; no more than 500 mcg per site (adult) or 200 mcg per site (pediatric). Prefer IV, since IM hurts
- Oral conversion: IV 50, 100, 200 and 400 mcg equal oral 62.5, 125, 250 and 500 mcg. Adjust for bioavailability when switching
- Discard: discard any unused portion of the vial or ampule
Dosing Notes:
- Give loads in stages, and check the patient and look for toxicity before each dose.
- Doses are weight-based. Maintenance runs on lean weight. The label does not state the weight basis for the load.
- Stop digoxin and give digoxin immune Fab for toxicity. More digoxin is not the treatment. Antidote doses are on the DigiFab page.
- No continuous infusion is labelled. Dosing is intermittent: IV, IM or oral.
Contraindications & Precautions
Contraindications
- Ventricular fibrillation
- Known hypersensitivity to digoxin, or to other digitalis preparations
- Pre-excited AF (accessory pathway conduction): AV-nodal blockers, digoxin included, are contraindicated
- Acute myocardial infarction (relative): not recommended; digoxin may increase myocardial oxygen demand
- Myocarditis (relative): avoid; digoxin can cause vasoconstriction
Precautions
- Sinus node and AV disease: Digoxin can cause severe sinus bradycardia, sinoatrial block and complete heart block. Consider a pacemaker before treatment.
- Renal impairment: the kidneys clear most of it. As CrCl falls, the maintenance dose falls, and toxicity lasts longer.
- Electrolytes: Hypokalemia, hypomagnesemia, hypercalcemia and low body weight all raise toxicity risk. Hypocalcemia can make digoxin ineffective.
- Obstruction and restrictive physiology: digoxin may worsen hypertrophic obstructive cardiomyopathy. Amyloid raises toxicity risk.
- Cardioversion: consider holding digoxin 1–2 days before an elective cardioversion. If toxicity is suspected, delay the cardioversion.
- Thyroid: hypothyroidism means less digoxin is needed
Hold / Reassess If
- Serum digoxin above 2.0 ng/mL, or any sign of toxicity at any level
- Potassium above 5.5 mEq/L with toxicity; keep potassium between 4.0 and 5.5 mEq/L
- New second- or third-degree AV block, sinus pause or symptomatic bradycardia
- Ventricular tachycardia, bidirectional VT or frequent multiform PVCs (bigeminy or trigeminy)
- Fall in creatinine clearance: recalculate maintenance from Table 3
Pre-excited AF: Digoxin slows the AV node more than it slows the accessory pathway. Conduction can shift to the pathway and drive ventricular fibrillation. Unstable? Electrical cardioversion.
Adverse Effects & Toxicity
Common
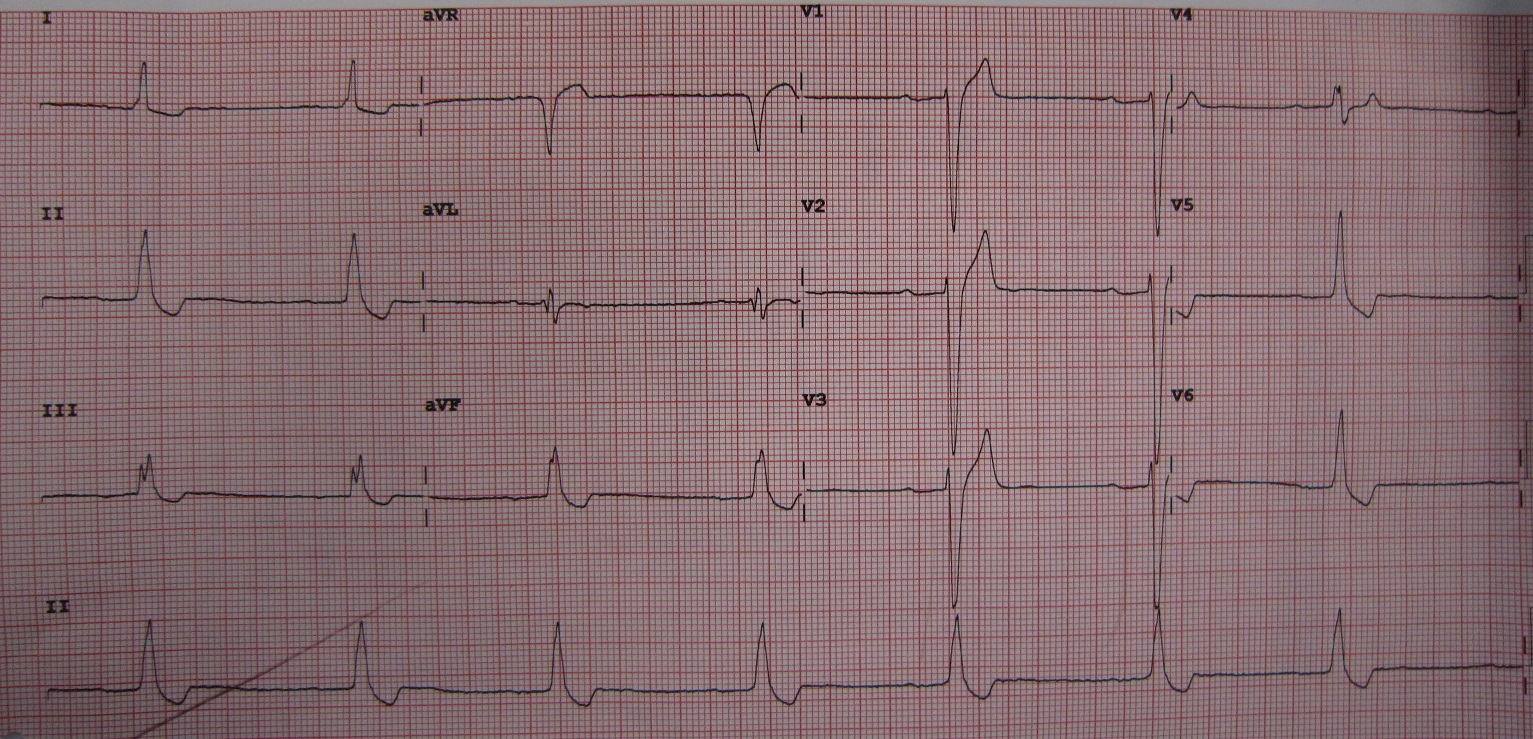
- GI symptoms: anorexia, nausea and vomiting. In overdosed patients, nausea, vomiting, anorexia and fatigue occur in 30–70%, and GI symptoms in up to 80%.
- Fatigue, malaise, dizziness and confusion: very common. They may linger after the rest of the toxicity has resolved.
- Yellow-green color vision: the visual change you are most likely to see
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
| Bradycardia and AV block | Sinus bradycardia, new Mobitz I, second- or third-degree AV block, junctional rhythm, atrial tachycardia with block | Stop digoxin; atropine often works (parasympathetic); transcutaneous pacing; digoxin immune Fab if unresponsive or life-threatening |
| Ventricular arrhythmias | Bidirectional VT, VT, VF, bigeminy or trigeminy | Digoxin immune Fab for life-threatening arrhythmia; the label lists lidocaine or phenytoin as options (order per local protocol); follow local protocol or Poison Control |
| Hyperkalemia | Potassium above 5.5 mEq/L (adult) with progressing toxicity, usually after a large ingestion | Digoxin immune Fab; calcium is not shown to help and rapid IV calcium is cautioned against, so do not delay Fab; glucose with insulin may be needed while Fab is pending if hyperkalemia is life-threatening |
Overdose & Toxicity Management
- Assess: the amount, the time, the co-ingestants and the renal function. In adults with heart disease, 10–15 mg kills about half. In a non-cardiac adult, above 25 mg is uniformly fatal without Fab.
- Stop and monitor: stop digoxin and interacting drugs; continuous ECG; pads on for unstable rhythms
- Electrolytes: check K⁺, Mg²⁺, Ca²⁺ and creatinine. Correct hypokalemia to 4.0–5.5 mEq/L; avoid potassium salts with bradycardia or heart block
- Activated charcoal: the label advises it after a massive acute ingestion, whatever the time since ingestion (enterohepatic recirculation). After smaller ingestions, timing follows protocol. Confusion calls for caution because of aspiration risk.
- Digoxin immune Fab (DigiFab): give for VT or VF; progressive bradycardia or second- or third-degree block not responsive to atropine; potassium above 5.5 mEq/L in adults (above 6 in children) with progressing toxicity; hypotension with end-organ dysfunction; ingestion of 10 mg or more in an adult (4 mg or more, or above 0.1 mg/kg, in a child), or an acute ingestion that can cause a steady-state level of 10 ng/mL or more; chronic level above 6 ng/mL in adults (above 4 in children). Doses are on the DigiFab page
- Bridges until Fab works: atropine for bradycardia; pacing (use with caution, by experienced teams); lidocaine or phenytoin for ventricular arrhythmias (label); follow local protocol or Poison Control. Sympathomimetics such as epinephrine can raise arrhythmia risk (label). Use the lowest effective dose and watch the rhythm.
- Dialysis: does not remove digoxin. Most of the drug sits in tissue.
- Antidote toxicity: Fab itself can cause hypokalemia (13%), worsening heart failure (13%), worsening AF (7%) and infusion reactions. It also makes digoxin assays misleading for days to weeks.
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical | ||
| Rhythm and heart rate | Continuous ECG in toxicity; at each dose change | New AV block, sinus pause, VT or bidirectional VT: hold digoxin, treat per Adverse Effects |
| Symptoms (GI, visual, confusion) | Each visit and after any dose change | New anorexia, nausea or yellow-green vision: check level and electrolytes before the next dose |
| Laboratory | ||
| Potassium | Before dose changes, with diuretics or illness, and in toxicity | Keep 4.0–5.5 mEq/L; above 5.5 with toxicity: digoxin immune Fab |
| Magnesium and calcium | Baseline and with diuretics or illness | Correct low Mg²⁺ and Ca²⁺. Rapid IV calcium can cause serious arrhythmias in digitalized patients; do not delay Fab for it |
| Creatinine clearance | Before maintenance dosing and when renal function changes | Falling CrCl: reduce maintenance per label Table 3 |
| Drug Levels | ||
| Serum digoxin | At least 6 h after the last dose, or just before the next dose; repeat after any dose change or new interacting drug | Heart failure: 0.5–0.9 ng/mL had the lowest mortality in the DIG post hoc analysis; AF: below 1.2 ng/mL. Toxicity risk rises above 1.2 ng/mL; above 2.0 ng/mL is the label toxic threshold. Treat the patient, not the number alone |
| Time to steady state | Plan the first level around steady state | About 7 days at CrCl 100 mL/min; up to 19 days at CrCl 10 mL/min |
| Infusion Safety | ||
| IV administration | Throughout IV push | Give over 5 minutes or longer; stop for hypotension or new bradycardia |
| After Fab | Digoxin assays read falsely for days to weeks | Use free digoxin and the clinical picture; potassium can fall sharply after Fab; check it frequently |
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| Succinylcholine | Potassium shift from muscle can cause arrhythmias in digoxin-treated patients | Check potassium before paralysis; monitor the ECG during RSI |
| Sympathomimetics (epinephrine, norepinephrine, dopamine) | Can increase arrhythmia risk | Use the lowest effective dose; monitor rhythm |
| Calcium (IV) | Rapid IV administration can cause serious arrhythmias in digitalized patients | Give slowly and only with a clear indication; do not delay Fab for hyperkalemia |
| Amiodarone | Digoxin AUC up 40% (injection); serum concentration up 70% (tablet) | Reduce digoxin 15–30% (injection) or about 30–50% (tablet); the labels differ, so individualize by level, or change frequency; measure level |
| Quinidine | Digoxin AUC up 54–83% (injection); serum concentration up 100% (tablet) | Reduce digoxin about 30–50% (both labels) or change frequency; measure level |
| Verapamil, diltiazem, beta blockers | Additive AV-node slowing: bradycardia and heart block | Monitor rate and PR interval; use together only with monitoring |
| Dronedarone, sotalol, dofetilide | Sudden death and proarrhythmia higher with digoxin | Individualize the dose and monitor QT and rhythm |
| ACE inhibitors, ARBs, NSAIDs, COX-2 inhibitors | Reduce renal digoxin excretion | Recheck the level and creatinine after starting |
IV Compatibility
- Preferred diluents: sterile water, 0.9% sodium chloride or 5% dextrose, at least 4 times the volume
- Do not mix with other drugs in the same container or give through the same IV line at the same time
- Verify with an institutional compatibility resource.
Special Populations
- Pediatrics: dose loads and maintenance by weight and by age, using the Pediatric Dosing table. AF rate control is not established in children.
- Neonates: premature and immature infants are especially sensitive. Digoxin-like substances, which interfere with immunoassays, turn up in up to half of neonates.
- Pregnancy: digoxin crosses the placenta. Needs may rise in pregnancy and fall after delivery. Check levels, and watch the newborn for vomiting and arrhythmias.
- Lactation: infant exposure reaches up to 4% of the neonatal maintenance dose. That is unlikely to matter clinically.
- Older Adults: lower renal clearance raises toxicity risk, so dose by renal function. The AGS Beers Criteria advise avoiding digoxin as first-line therapy for AF or heart failure. In heart failure, higher doses add nothing and may increase toxicity.
- Renal Impairment: the kidney does most of the excreting. In anuric patients the half-life is 3.5–5 days, so toxicity lasts longer. Reduce maintenance per Table 3. Dialysis does not remove digoxin.
- Hepatic Impairment: in acute hepatitis, plasma digoxin levels are generally in the healthy range. No specific adjustment is established.
- Obesity / Dosing Weight: base maintenance on lean body weight, and reduce it when lean weight is an abnormally small share of total mass. Chronic diarrhea (malabsorption) lowers absorption.
Field & Transport Considerations
- Scope: it depends on state and agency protocol. Most often you meet digoxin as a home medication or as a toxicity call.
- Storage & Stability: injection and tablets: store at 25 °C (77 °F), excursions 15–30 °C, dry place, protect from light
- Carried Concentration: adult injection 250 mcg/mL and pediatric injection 100 mcg/mL. The adult vial is 2.5 times as concentrated per mL. Draw a pediatric dose from the adult vial and it is a 2.5-fold overdose unless the volume is recalculated. Check the label before you draw up.
- Infusions in Transport: digoxin is not run as a continuous infusion. Give IV over 5 minutes or longer on a dedicated line; continuous ECG during transport for toxicity; atropine and pacing available
- Handoff Essentials: time and amount of last dose; ingestion time and amount; pre-Fab digoxin level with draw time; K⁺, Mg²⁺, creatinine and 12-lead; Fab vials given with times; charcoal given
Clinical Pearls
Pre-excited AF: Digoxin is contraindicated here. It does not block conduction down the accessory pathway, so the ventricular rate can speed up to fibrillation. Unstable? Electrical cardioversion.
Level timing: Wait at least 6 hours after the last dose, or draw just before the next one. An early level reflects distribution and overstates tissue load.
Therapeutic level, toxic patient: Here's the catch: a normal level can still mean toxicity. Each of these raises toxicity at normal levels: hypokalemia, hypomagnesemia, hypercalcemia, renal failure and low body weight. Treat the rhythm and potassium first.
Effect vs toxicity: Scooped ST depression and PR prolongation are drug effects, not toxicity. Toxicity shows up as new Mobitz I, accelerated junctional rhythm, nonparoxysmal atrial tachycardia with block and bidirectional VT.
IV vs oral equivalence: IV 50 mcg equals oral 62.5 mcg. IV 100 equals 125. IV 200 equals 250. IV 400 equals 500. IV is 100% bioavailable, oral 60–80%. Use these to convert maintenance, not loads.
Lethal-dose discriminator (CFRN, CCRN): In heart-disease patients, half die after 10–15 mg. A non-cardiac adult with more than 25 mg dies without Fab. Ingesting 10 mg or more meets the DigiFab criteria.
Pharmacology
Mechanism of Action
- Target: Digoxin blocks the sodium pump (Na⁺/K⁺-ATPase) in myocardium and conduction tissue.
- Myocardium: intracellular calcium rises. That boosts contractility and automaticity and slows conduction velocity.
- Autonomic: through indirect parasympathetic stimulation, it slows the SA and AV nodes.
- Clinical consequence: a bigger stroke volume and a slower ventricular rate in AF. At high concentrations, potassium leaves the cells and serum K⁺ climbs in toxicity.
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| IV | 5–30 min | 1–4 h | Days (half-life 1.5–2 days) |
| Oral tablet | 0.5–2 h | 2–6 h | Days (half-life 1.5–2 days) |
- Half-life: 1.5–2 days in healthy adults; 3.5–5 days in anuric patients
- Metabolism: only about 13% is metabolized, and not through cytochrome P450. Digoxin is a P-glycoprotein substrate.
- Elimination: urine clears 50–70% unchanged, and the amount tracks creatinine clearance.
- Distribution: the apparent volume is large, about 475–500 L. It crosses the blood-brain barrier and placenta. About 25% is protein bound.
Names & Classification
- Generic Name
- Digoxin
- Brand Names
- Lanoxin (US; tablets and injection); Lanoxin Injection Pediatric; many generic tablets and injections
- Pharmacologic Class
- Cardiac glycoside (Na⁺/K⁺-ATPase inhibitor)
- Therapeutic Class
- Inotrope; AV-nodal rate-control agent
- Controlled Substance
- Not controlled
- ISMP High-Alert
- No (not flagged; see editorFlags)
- Look-Alike / Sound-Alike
- None commonly reported. Digibind (discontinued) and DigiFab are different antidote products
- Error-Prone Abbreviations to Avoid
- Write mcg (not the Greek-mu abbreviation)
References
- Covis Pharma US, Inc. (2025). LANOXIN (digoxin) injection and LANOXIN Injection Pediatric [prescribing information]. DailyMed; label effective October 17, 2025. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=9ec84cac-6ecc-43dc-8006-6ccc029e2707
- Advanz Pharma (US) Corp. (2024). LANOXIN (digoxin) tablets [prescribing information]. DailyMed; label effective December 5, 2024. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d91e3646-4c63-4512-ab22-db39c085c4dc
- BTG International Inc. (2026). DigiFab (digoxin immune fab [ovine]) for injection [prescribing information]. DailyMed; label effective September 29, 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=c05ee6a5-c98b-45f4-83fd-40781639d653
- Joglar JA, et al. (2024). 2023 ACC/AHA/ACCP/HRS guideline for the diagnosis and management of atrial fibrillation. Circulation, 149(1), e1–e156. https://doi.org/10.1161/CIR.0000000000001193
- Andrews P, Anseeuw K, Kotecha D, Lapostolle F, Thanacoody R. (2023). Diagnosis and practical management of digoxin toxicity: a narrative review and consensus. European Journal of Emergency Medicine, 30(6), 395–401. https://doi.org/10.1097/MEJ.0000000000001065
- Beaulieu J, St-Onge M. (2024). Antidote use for cardiac arrest or hemodynamic instability due to cardiac glycoside poisoning: a narrative review. Resuscitation Plus, 100690. https://doi.org/10.1016/j.resplu.2024.100690
- American Geriatrics Society Beers Criteria Update Expert Panel. (2023). American Geriatrics Society 2023 updated AGS Beers Criteria for potentially inappropriate medication use in older adults. Journal of the American Geriatrics Society. https://pmc.ncbi.nlm.nih.gov/articles/PMC12478568/ (doi:10.1111/jgs.18372)
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.