

Bedside Snapshot
- Use It For
- Severe agitation needing parenteral sedation (off-label); postoperative nausea and vomiting (labeled); ED nausea and vomiting (off-label); migraine and acute headache (off-label)
- Adult Dose
- Agitation: 5–10 mg IM/IV; may repeat once at 15 min
- PONV prophylaxis: 0.625–1.25 mg IV at end of surgery (label max initial 2.5 mg)
- Migraine: 2.75 mg IM (studied dose). Differs from FDA label: 2.5 mg max is PONV-only
- Pediatric Dose
- PONV: 10–15 mcg/kg (0.01–0.015 mg/kg) IV, max 1.25 mg. Differs from FDA label (up to 0.1 mg/kg, ages 2–12 yr); not established under 2 yr. Agitation: not routinely recommended in children
- Onset / Duration
- IV/IM: 3–10 min, peak up to 30 min / 2–4 hr (alertness altered up to 12 hr); IM agitation doses: median 16–20 min to sedation
- Do Not Give / Hold If
- Known or suspected long QT (QTc >440 ms men, >450 ms women; congenital LQTS); hypersensitivity; SBP <90 mmHg; already sedated or SpO₂ <90%
- Watch For
- Torsades (QTc on ECG, monitor 2–3 hr); hypotension (BP); dystonia or akathisia (spasm, restlessness); oversedation with benzodiazepines or alcohol (SpO₂, EtCO₂)
- Reversal / Rescue
- No reversal agent. Torsades: magnesium 1–2 g IV; unsynchronized shock if pulseless or unstable. Dystonia: diphenhydramine 25–50 mg IV/IM. Droperidol hypotension: fluids, a non-epinephrine pressor
- Must Remember
- Dose depends on the indication: antiemetic 0.625–2.5 mg, agitation 5–10 mg. Screen QT risk factors, start low, and get an ECG as soon as it is safe
Indications
Emergency & Prehospital
- Severe agitation needing parenteral sedation: reach for it when de-escalation has failed and patient or staff safety is at risk. ACEP makes no agent-specific recommendation out of hospital, so local protocol governs (off-label)
- Nausea and vomiting: a low-dose antiemetic where protocols allow it. It is off-label outside the perioperative setting.
ED / ICU / Transport
- Severe agitation in the ED: ACEP 2024 (Level B) prefers droperidol plus midazolam (or an atypical antipsychotic plus midazolam) for faster control. When only one agent is given, ACEP prefers droperidol over midazolam alone (off-label)
- Migraine and acute headache: a parenteral dopamine antagonist you can use in place of metoclopramide or prochlorperazine (off-label)
- Nausea and vomiting refractory to other antiemetics: for nausea that persists after ondansetron has failed or does not suit the patient (off-label)
Other Uses
- Postoperative and procedural nausea and vomiting: prevention and treatment. This is the only FDA-labeled indication, and the label reserves it for patients who do not respond to other adequate treatments.
Dosing & Administration
Doses vary by protocol; follow local protocols and medical direction.
Available Forms
- Injection 2.5 mg/mL: 2 mL (5 mg) single-dose vial (American Regent, Hikma) and 1 mL (2.5 mg) vial (Hikma). It is the only US strength.
- Volume check: 1.25 mg = 0.5 mL; 2.5 mg = 1 mL; 5 mg = 2 mL; 10 mg = 4 mL
- EMS / transport: agency-specific. There is no oral or intranasal product.
Adult Dosing
| Indication | Dose & Route | Repeat / Max | Notes |
|---|---|---|---|
| Severe agitation, IM or IV (off-label) | 5–10 mg IM/IV | May repeat once if not sedated at 15 min; studied regimens totalled up to 20 mg (DORM II median total 10 mg, IQR 10–20 mg). Beyond that, change agent or escalate care | DORM II: 10 mg, then 10 mg at 15 min if needed. 5 mg IM is also effective and was used in older adults. Boxed warning: start low and titrate up with caution |
| Severe agitation, IV combination (off-label) | Droperidol 5 mg IV plus midazolam 5 mg IV | Up to 2 further doses (midazolam 5 mg in the trial) | High-alert (midazolam, ISMP). More patients sedated at 10 min than with droperidol 10 mg or olanzapine 10 mg IV alone; studied in ages 18–65. ACEP-preferred ED combination. Use capnography |
| PONV prophylaxis (FDA-labeled indication; guideline dose) | 0.625–1.25 mg IV at end of surgery | Max initial dose 2.5 mg (label) | Fifth consensus PONV guideline (2026): 0.625–1.25 mg effective, panel recommends 0.625 mg; give at the end of surgery; adverse effects are dose-related |
| Postoperative or procedural nausea and vomiting, treatment (FDA-labeled) | Up to 2.5 mg IM or slow IV | Max initial dose 2.5 mg; additional 1.25 mg only if benefit outweighs risk | Label maximum, not a target; lower doses carry less akathisia and QT risk. Reduce the first dose in older, debilitated or poor-risk patients. After failed prophylaxis, 1–1.25 mg was as effective as ondansetron (Fifth consensus guideline) |
| Nausea and vomiting, ED (off-label) | 1.25 mg IV | Max initial dose 2.5 mg (label) | Evidence for undifferentiated ED nausea is weak: in a placebo-controlled ED trial, superiority over placebo was not shown for droperidol 1.25 mg IV or ondansetron 8 mg IV. |
| Migraine or acute headache (off-label) | 2.75 mg IM (studied dose) | Single dose; repeat only per protocol | In a placebo-controlled trial, 2.75 mg IM improved 2-hour headache response (87% vs 57% placebo); akathisia, anxiety and drowsiness were the main adverse effects. Differs from FDA label: 2.5 mg is the label maximum initial dose, for PONV only |
Pediatric Dosing
| Indication | Dose (per kg) & Route | Max Single / Max Total | Notes |
|---|---|---|---|
| PONV prophylaxis, children (guideline dose) | 10–15 mcg/kg (0.01–0.015 mg/kg) IV | Max 1.25 mg | Fourth consensus PONV guideline (2020). Differs from FDA label: the label allows up to 0.1 mg/kg as the maximum initial dose, ages 2–12 yr; not established under 2 yr. Droperidol may be of limited efficacy in children, where 5-HT3 antagonists plus dexamethasone have the strongest evidence |
| Postoperative or procedural nausea and vomiting, age 2–12 yr (FDA-labeled) | Up to 0.1 mg/kg IM or slow IV | Label maximum initial dose 0.1 mg/kg. Cap 2.5 mg = adult maximum initial dose (NASEMSO Universal Care p. 13); further doses only with caution | A ceiling, not a target: about 7–10 times the guideline dose. Adjust for age and clinical factors |
| Children under 2 yr | Not established in children under 2 years | — | Use another antiemetic; see the ondansetron page for pediatric dosing |
| Severe agitation, children (off-label) | Not routinely recommended in children | — | NASEMSO guidance: not routinely recommended in children. Try verbal de-escalation first. See weight-based dosing |
Preparation & Administration
- Dilution: give undiluted from the 2.5 mg/mL vial
- IV push rate: slow IV (label). Hypotension is more likely with hypovolemia.
- IM: choose a large muscle. 10 mg is 4 mL.
- Light: protect from light and keep in the carton until use
- Before the dose: 12-lead ECG per the boxed warning when the clinical situation allows; check K⁺ and Mg²⁺ in at-risk patients
Dosing Notes: Agitation doses (5–10 mg) are above the label's 2.5 mg maximum initial dose. Those doses come from ED and prehospital trials, not from the label. The label does not recommend droperidol for any use except perioperative nausea and vomiting, and only when other treatments are ineffective or inappropriate. So every other use is off-label and protocol-driven. The boxed warning says to start low and adjust upward with caution.
Contraindications & Precautions
Contraindications
- Known or suspected QT prolongation: QTc >440 ms in men or >450 ms in women, including congenital long QT syndrome (label)
- Known hypersensitivity to droperidol
- Concurrent ziprasidone: the ziprasidone (Geodon) label contraindicates using the two together because they add to QT prolongation
Precautions
- Uses other than perioperative nausea and vomiting: the label does not recommend droperidol for any other use (it is not contraindicated). It reserves the drug for perioperative nausea and vomiting, when other treatments are ineffective or inappropriate. Agitation, migraine and ED nausea uses are off-label and protocol-driven
- QT risk factors: heart rate <50/min, significant cardiac disease, CHF, cardiac hypertrophy, class I or III antiarrhythmics, MAO inhibitors, other QT-prolonging drugs, low K⁺ or Mg²⁺, or drugs that cause them (diuretics). The boxed warning also names age >65, alcohol abuse, and co-administered benzodiazepines, volatile anesthetics or IV opioids. Start low and titrate with caution
- Pheochromocytoma: severe hypertension and tachycardia reported
- Older, debilitated or poor-risk patients: reduce the first dose
- Parkinson disease or dementia with Lewy bodies: dopamine blockade can cause severe neuroleptic sensitivity. It can worsen parkinsonism and extrapyramidal symptoms. Prefer a non-dopamine-blocking agent
- Co-sedation: benzodiazepines, opioids and alcohol pile on sedation and respiratory depression
Hold / Reassess If
- QTc >440 ms (men) or >450 ms (women) on a pre-dose ECG (label); QTc >500 ms or new ectopy after a dose: no further doses
- SBP <90 mmHg
- Already sedated, or SpO₂ <90% or a rising or flat EtCO₂ trace
FDA Boxed Warning: The QT can prolong, and torsades can follow, even at or below recommended doses. Some cases were fatal, and some struck patients with no known risk factors. Save droperidol for patients who fail other adequate treatment. Get a 12-lead ECG before giving it, and do not give it if the QT is already prolonged. Continue ECG monitoring for 2–3 hours afterward. Start low and go up with caution.
The QT Warning in Context: Much of the 2001 warning came from postmarketing reports, and many involved far higher doses. DORM II saw an abnormal QT in 1.3% of patients given a median 10 mg. Roughly half of those had another explanation. No patient developed torsades. Many ED protocols limit ECG monitoring to high-risk patients. Agency policy decides.
Adverse Effects & Toxicity
Common
- Hypotension and tachycardia: the most common adverse effects in the label. They are usually mild to moderate.
- Drowsiness: alertness can stay altered for up to 12 hr
- Restlessness, anxiety, dysphoria: including akathisia
- Extrapyramidal effects: dystonia and oculogyric crisis. About 1% occur after IM agitation doses.
- Postoperative hallucinations
Serious / Life-Threatening
| Effect | Recognition | Management |
|---|---|---|
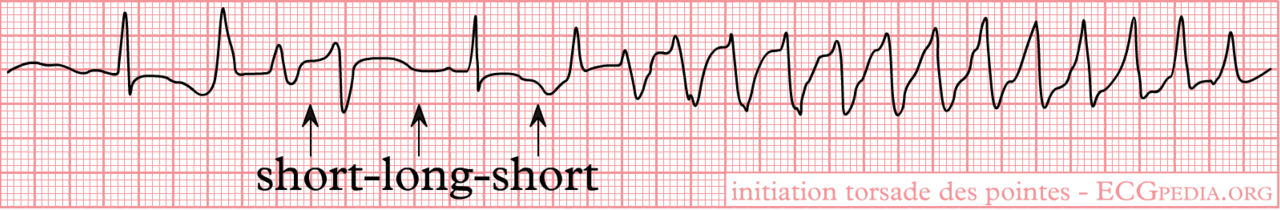
| QT prolongation, torsades de pointes | QTc >500 ms, R-on-T ectopy, polymorphic VT with long QT; dose-dependent | Stop QT drugs; correct K⁺ and Mg²⁺; magnesium; unsynchronized shock (defibrillation) if pulseless or unstable |
| Hypotension | SBP <90 mmHg, worse with hypovolemia | Supine, IV fluids; use a vasopressor other than epinephrine (paradoxical fall). Epinephrine is still indicated for anaphylaxis or cardiac arrest |
| Acute dystonia, akathisia | Neck, jaw or eye spasm; motor restlessness | Stop the dopamine antagonist. Dystonia: diphenhydramine or benztropine. Akathisia: diphenhydramine or a benzodiazepine (e.g. midazolam). Observe for recurrence |
| Oversedation, respiratory depression | SpO₂ <90%, rising or flat EtCO₂; more common with added benzodiazepines | Airway maneuvers, O₂, BVM; no further sedatives |
| Neuroleptic malignant syndrome (rare) | Fever, rigidity, autonomic instability, altered mental status, rising CK | Stop dopamine antagonists, cool, support; consider dantrolene |
| Anaphylaxis, laryngospasm, bronchospasm | Stridor, wheeze, urticaria, hypotension | Anaphylaxis protocol with IM epinephrine |
Overdose & Toxicity Management
- Signs: deep sedation, hypotension, QT prolongation and ventricular arrhythmias, extrapyramidal reactions
- Immediate care: airway, O₂, assisted ventilation if hypoventilating; continuous ECG; IV fluids for hypotension; keep warm; observe for 24 hr (label)
- Torsades: magnesium sulfate 1–2 g IV (pediatric 25–50 mg/kg, max 2 g); unsynchronized shock if pulseless or unstable; overdrive pacing or isoproterenol if recurrent
- Antidote: none. Extrapyramidal reactions: an anticholinergic such as diphenhydramine 25–50 mg IV/IM (pediatric: see the diphenhydramine page)
Monitoring
| Parameter | When / How Often | Target / Act If |
|---|---|---|
| Clinical: 12-lead ECG | Before the dose (boxed warning); in agitation, as soon as it is safe to obtain | QTc >440 ms (men) or >450 ms (women): do not give; use another agent |
| Clinical: cardiac monitor | Continuous for 2–3 hr after the dose (label); always after agitation doses or with risk factors | QTc >500 ms, R-on-T beats or polymorphic VT: stop QT drugs, correct electrolytes, give magnesium |
| Clinical: BP and HR | Baseline, then every 5–15 min until stable | SBP <90 mmHg: supine, fluids; HR <50/min raises torsades risk |
| Clinical: SpO₂ and waveform EtCO₂ | Continuous once sedated, especially with benzodiazepines or alcohol | SpO₂ <90% or rising or flat EtCO₂: airway support, no more sedatives |
| Clinical: sedation score (RASS or SAT) | Before the dose, then every 5–15 min | Not sedated at 15 min: consider one repeat dose; deep sedation needs constant airway watch |
| Clinical: extrapyramidal signs | Each reassessment and before discharge | Dystonia: diphenhydramine or benztropine. Akathisia: stop the dopamine antagonist; diphenhydramine or a benzodiazepine (e.g. midazolam) per protocol. Record the reaction |
| Laboratory: electrolytes | Baseline in at-risk patients (vomiting, alcohol use, diuretics) | Low K⁺ or Mg²⁺: replace before further doses |
| Laboratory: agitation workup | On arrival | Low glucose: dextrose; temperature >40 °C (104 °F) or rigidity: think NMS, toxicity or sepsis |
Interactions & Compatibility
Clinically Significant Interactions
| Drug / Class | Effect | What To Do |
|---|---|---|
| QT-prolonging drugs (class I and III antiarrhythmics; QT-prolonging antihistamines, antimalarials, calcium channel blockers, neuroleptics and antidepressants; methadone, ondansetron, haloperidol) | Additive QT prolongation, torsades | Label: do not co-administer; if unavoidable, ECG first and continuous monitoring |
| Ziprasidone (Geodon) | Additive QT prolongation; the ziprasidone label contraindicates giving it with droperidol | Do not combine. If droperidol was already given (by EMS or at triage), choose a non-QT-prolonging rescue such as a benzodiazepine per protocol |
| MAO inhibitors | Listed QT risk factor | Avoid; ECG and monitoring if used |
| Diuretics, laxatives, mineralocorticoid steroids | Low K⁺ or Mg²⁺ raises torsades risk | Check and correct electrolytes |
| Benzodiazepines, opioids, alcohol, general anesthetics | Additive sedation and respiratory depression; benzodiazepines, volatile anesthetics and IV opioids are also boxed-warning QT risk factors | Reduce the other drug's dose; capnography; wait 15 min before stacking |
| Epinephrine | May paradoxically lower BP after droperidol | Use a different vasopressor for droperidol hypotension; still give epinephrine for anaphylaxis or cardiac arrest |
| Levodopa and dopamine agonists | Opposing dopamine effects | Prefer a non-dopamine-blocking agent in Parkinson disease |
IV Compatibility
- Give undiluted by slow IV push through a flushed line. The US label lists no diluents or Y-site data.
- Verify with an institutional compatibility resource.
Special Populations
- Pediatrics: labeled for nausea and vomiting at age 2–12 yr. Guideline doses sit well below the label maximum. It is not established under 2 yr. Agitation use is not routinely recommended in children (NASEMSO). Doses are in the Pediatric Dosing table.
- Neonates: safety under 2 years is not established (label). Avoid it unless a specialist directs its use.
- Pregnancy: there are no adequate human studies. Animal data show no teratogenic effect. A slight rise in newborn rat mortality appeared at 4.4 times the upper human IV dose, but not at 44 times. Not recommended in labor and delivery (label). Use it only when benefit justifies the risk, such as agitation that endangers the patient.
- Lactation: it is unknown whether droperidol enters human milk. Use with caution and watch the infant for sedation.
- Older Adults: reduce the first dose (label). Age >65 is a boxed-warning QT risk factor. ACEP 2024 made no agent-specific recommendation for patients over 65 (consensus), so local protocol governs. In a prehospital study of patients aged 65 and older, mostly with dementia, 5 mg IM was used. The AGS Beers Criteria advise avoiding antipsychotics for behavioral symptoms of dementia or delirium unless other measures have failed and the patient threatens substantial harm.
- Renal Impairment: use with caution (label). No specific adjustment is established.
- Hepatic Impairment: use with caution (label). No specific adjustment is established. Expect a longer effect.
- Obesity / Dosing Weight: adult doses are fixed, not weight-based. Pediatric doses use actual weight, with an adult cap.
- Alcohol Intoxication: the most common cause of agitation in droperidol studies (86% in one US ED cohort). Alcohol abuse is a boxed-warning QT risk factor. Watch the airway and for vomiting. Expect low K⁺ and Mg²⁺.
Field & Transport Considerations
- Scope: Paramedic, RN and critical-care transport for agitation or nausea. It varies by state and agency protocol. ACEP 2024 made no agent-specific recommendation for out-of-hospital agitation (consensus), so the agency protocol governs.
- Storage & Stability: 20–25 °C (68–77 °F), with excursions to 15–30 °C (59–86 °F). Protect from light and keep in the carton.
- Carried Concentration: 2.5 mg/mL only. Confirm mg and mL aloud (10 mg = 4 mL).
- Agitation Calls: try verbal de-escalation first. No prone or hobble restraint, and nothing over the neck or chest. Once sedated, run continuous SpO₂, EtCO₂ and ECG.
- Handoff Essentials: time, dose and route of each dose, other sedatives, estimated weight (children), ECG and QTc if obtained, BP trend, sedation score, extrapyramidal effects.
Clinical Pearls
Droperidol vs Other Agitation Agents:
- Midazolam alone: ACEP 2024 prefers droperidol or an atypical antipsychotic when one agent is given. The reason is midazolam's adverse effects.
- Droperidol 5 mg IM vs lorazepam 2 mg or ziprasidone 10–20 mg IM: more sedated at 15 min (64% vs 25–35%); respiratory depression numerically lower (12% vs 36–48%)
- IV midazolam 5 mg plus droperidol 5 mg: more sedated at 10 min than IV droperidol 10 mg or olanzapine 10 mg alone
Screen for QT Risk Factors: Before every dose, check for long QT, low K⁺ or Mg²⁺, bradycardia, CHF, age >65, alcohol abuse, and other QT or sedative drugs. Torsades has also occurred with no known risk factors (boxed warning). Start low and keep the monitor on.
Give It 15 Minutes: Median time to sedation after IM droperidol is 16–20 minutes. Reassess at 15 minutes before a second dose. Avoid stacking benzodiazepines. In DORM II, 8% of patients were oversedated without complications. Oversedation was more common in those who got an added benzodiazepine: 16 of the 109 oversedated patients, 15%.
Exam Discriminator: Akathisia vs Agitation: New motor restlessness after a dopamine antagonist? Call it akathisia until proven otherwise. More droperidol makes it worse. Stop the dopamine antagonist, then treat with diphenhydramine or a benzodiazepine per protocol.
Hypotension After Droperidol: Epinephrine can paradoxically drop the BP here, and alpha-blockade is the reason. Give fluids and choose another vasopressor. Epinephrine stays the drug for anaphylaxis or cardiac arrest.
Know Which Dose You Are Giving: Antiemetic doses are 0.625–2.5 mg. Agitation doses are 5–10 mg. Say the indication at the cross-check, so a nausea order does not get drawn up as an agitation dose.
Pharmacology
Mechanism of Action
- Dopamine D2 blockade in the chemoreceptor trigger zone → antiemetic effect
- D2 blockade in limbic pathways → tranquilization and sedation, with less respiratory depression than benzodiazepines in ED trials
- Mild alpha-adrenergic blockade → peripheral vasodilation, hypotension
- Cardiac repolarization delay → dose-dependent QT prolongation (median QTc rises of 37–59 ms at 0.1–0.25 mg/kg IV in a 40-patient study cited in the label)
- Nigrostriatal D2 blockade → dystonia, akathisia, rarely NMS
Pharmacokinetics
| Route | Onset | Peak | Duration |
|---|---|---|---|
| IV | 3–10 min | Up to 30 min | 2–4 hr (alertness altered up to 12 hr) |
| IM | 3–10 min; agitation trials: median 16–20 min to sedation | Up to 30 min | 2–4 hr (alertness altered up to 12 hr) |
- Half-life: about 2 hr after IV doses in published pharmacokinetic studies. None of the current US labels states one. Clinical effects last longer than that.
- Metabolism and elimination: hepatic and renal
Names & Classification
- Generic Name
- Droperidol
- Brand Names
- Inapsine (original US brand); current US supply is generic (American Regent, Hikma)
- Pharmacologic Class
- Butyrophenone; dopamine D2 receptor antagonist (first-generation antipsychotic)
- Therapeutic Class
- Antiemetic; neuroleptic sedative for agitation
- Controlled Substance
- Not controlled
- ISMP High-Alert
- No
- Look-Alike / Sound-Alike
- None commonly reported; the main error is giving an agitation dose (5–10 mg) for a nausea order (0.625–2.5 mg)
References
- American Regent. (2023). Droperidol injection, USP: Prescribing information (DailyMed, updated March 20, 2023). U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=147e033d-d997-4ef6-8bb5-a9ba372590b2
- American College of Emergency Physicians Clinical Policies Subcommittee on Severe Agitation; Thiessen, M. E. W., Godwin, S. A., Hatten, B. W., et al. (2024). Clinical policy: Critical issues in the evaluation and management of adult out-of-hospital or emergency department patients presenting with severe agitation. Annals of Emergency Medicine, 83(1), e1–e30. https://doi.org/10.1016/j.annemergmed.2023.09.010
- Gan, T. J., Jin, Z., Ayad, S., Belani, K. G., Habib, A. S., Meyer, T. A., et al. (2026). Fifth consensus guidelines for the management of postoperative nausea and vomiting: Executive summary. Anesthesia & Analgesia, 143(3), 497–513. https://doi.org/10.1213/ANE.0000000000007816
- Gan, T. J., Belani, K. G., Bergese, S., Chung, F., Diemunsch, P., Habib, A. S., et al. (2020). Fourth consensus guidelines for the management of postoperative nausea and vomiting. Anesthesia & Analgesia, 131(2), 411–448. https://doi.org/10.1213/ANE.0000000000004833
- Calver, L., Page, C. B., Downes, M. A., Chan, B., Kinnear, F., Wheatley, L., Spain, D., & Isbister, G. K. (2015). The safety and effectiveness of droperidol for sedation of acute behavioral disturbance in the emergency department. Annals of Emergency Medicine, 66(3), 230–238. https://doi.org/10.1016/j.annemergmed.2015.03.016
- Taylor, D. M., Yap, C. Y. L., Knott, J. C., Taylor, S. E., Phillips, G. A., Karro, J., et al. (2017). Midazolam-droperidol, droperidol, or olanzapine for acute agitation: A randomized clinical trial. Annals of Emergency Medicine, 69(3), 318–326. https://doi.org/10.1016/j.annemergmed.2016.07.033
- Martel, M. L., Driver, B. E., Miner, J. R., Biros, M. H., & Cole, J. B. (2021). Randomized double-blind trial of intramuscular droperidol, ziprasidone, and lorazepam for acute undifferentiated agitation in the emergency department. Academic Emergency Medicine, 28(4), 421–434. https://doi.org/10.1111/acem.14124
- Meek, R., Mee, M. J., Egerton-Warburton, D., Graudins, A., Meyer, A., Pouryahya, P., Blecher, G., Fahey, J., & Crow, S. (2019). Randomized placebo-controlled trial of droperidol and ondansetron for adult emergency department patients with nausea. Academic Emergency Medicine, 26(8), 867–877. https://doi.org/10.1111/acem.13650
- National Association of State EMS Officials. (2022). National model EMS clinical guidelines, version 3.0. Universal Care Guideline, p. 13; Agitated or Violent Patient/Behavioral Emergency, pp. 59–61. https://nasemso.org/content.aspx?page_id=22&club_id=157064&module_id=701974
- Pfizer. (2025). Geodon (ziprasidone mesylate) prescribing information (DailyMed, revised January 2025). https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=8326928a-2cb6-4f7f-9712-03a425a14c37
- Silberstein, S. D., Young, W. B., Mendizabal, J. E., Rothrock, J. F., & Alam, A. S. (2003). Acute migraine treatment with droperidol. Neurology, 60(2), 315–321. https://doi.org/10.1212/01.wnl.0000042477.63516.b2
- American Geriatrics Society Beers Criteria® Update Expert Panel. (2023). American Geriatrics Society 2023 updated AGS Beers Criteria® for potentially inappropriate medication use in older adults. Journal of the American Geriatrics Society, 71(7), 2052–2081. https://doi.org/10.1111/jgs.18372
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.
AI Assistance Notice
AI was used to assist in organizing, paraphrasing, and formatting this information.