

Bedside Snapshot
- Indications
- Positive LEMON, MOANS or HEAVEN screen before induction
- Physiology that will not tolerate apnea (protocol thresholds, e.g. SBP < 90 mmHg, SpO₂ < 93%)
- Failed bag-mask ventilation or failed supraglottic airway
- Contraindications / Abort
- Abort an attempt at SpO₂ < 90% or after 30 s
- Stop after 3 attempts in total (per protocol); move to the next plan
- CICO declared: surgical airway now, not after more tries
- Critical Steps
- Screen and say the plan aloud before induction
- Assign roles: operator, oxygen, drugs, recorder
- Re-oxygenate between attempts with bag-mask and PEEP
- Confirm & Monitor
- Sustained waveform EtCO₂ over 5–6 breaths
- Depth, chest rise and breath sounds after every move
- Continuous SpO₂, ECG, EtCO₂ and blood pressure
Key Numbers
Decide the plan before induction. Once oxygenation is falling, every extra attempt costs more than the one before.
| Parameter | Value |
|---|---|
| Predictor screen | LEMON (laryngoscopy), MOANS (mask ventilation), HEAVEN (anatomy and physiology); any positive item triggers the plan |
| Attempts | 3 in total, then Plan B (supraglottic airway) or Plan C (front-of-neck access), per protocol. Guidelines limit attempts rather than fixing one number; DAS 2015 allows one further attempt only by a more experienced operator |
| Time per attempt | 30 s or less; abort at SpO₂ < 90% |
| Oxygenation between attempts | Bag-mask with PEEP and adjuncts until SpO₂ recovers to the protocol target |
| Physiologic risk | Hypotension, hypoxemia, acidosis or low reserve: resuscitate before induction; use protocol thresholds (examples on Pre-Procedure Assessment) |
| CICO declared | Cannot intubate and cannot oxygenate with mask and supraglottic airway: say it aloud, confirm paralysis while the kit is prepared, and go to Plan C without delay |
| Adult surgical tube | 6.0 mm cuffed endotracheal tube (see Cricothyrotomy) |
| Confirmation | Sustained waveform EtCO₂ over 5–6 breaths |
Overview & Principles
A difficult airway is one where a trained clinician has trouble with face-mask ventilation, laryngoscopy or tracheal intubation, or expects to. Prediction never rules it out. The point is the plan. Set it before induction, so a failed attempt does not become a hypoxic arrest.
How It Works
- Anticipate: screen the anatomy, the mask seal and the physiology before any induction drug goes in.
- Plan in three tiers: Plan A is the primary technique. Plan B is a supraglottic airway or bag-mask rescue. Plan C is front-of-neck access. It is a simplified scheme. DAS 2015 names front-of-neck access Plan D. Its Plan C is face-mask ventilation. So use your local plan letters.
- Oxygenation sets the clock: the time to desaturation limits each attempt. The number of attempts does not.
- Declare failure early: say the failed step out loud, call for help at the first failed attempt, and move to the next plan.
Where It Fits
The failed-airway sequence follows the Difficult Airway Society (DAS) 2015 and American Society of Anesthesiologists (ASA) 2022 guidelines. It starts with a limited number of optimized laryngoscopy attempts. Then comes a supraglottic airway or face mask. Surgical airway comes last, once the patient cannot be oxygenated. Intubation, RSI and cricothyrotomy each have their own technique. This page covers the decisions that connect them.
Indications & Contraindications
Indications
- Any airway where the LEMON, MOANS or HEAVEN screen is positive, or where the team expects difficulty
- Failed bag-mask ventilation or failed supraglottic airway: the next plan applies now
- Unexpected failure after induction, including a fall in SpO₂ during an attempt
Absolute Contraindications
None. A predicted difficult airway is a reason to plan. It is never a reason to delay an airway the patient needs.
Relative Contraindications & Cautions
- Cooperative patient with a predicted difficult airway: topical anesthesia with sedation may be safer than induction. Spontaneous breathing is kept. Choose per protocol.
- Unstable cervical spine: maintain manual in-line stabilization throughout.
- Surgical airway in a young child: age limits apply (see Special Populations).
Consider an Alternative
Awake intubation is the usual first choice for a cooperative patient with a predicted difficult airway or physiologic risk. Topical anesthesia with sedation keeps spontaneous breathing. Use noninvasive ventilation to bridge oxygenation when the patient can tolerate it. Use a supraglottic airway when ventilation works but the tube does not. Both belong to Plan B.
Abort / Stop Criteria
- SpO₂ falls below 90% during an attempt
- An attempt exceeds 30 s or makes no progress
- Three attempts have failed in total
- Hemodynamic collapse develops during laryngoscopy
Scope & Team Roles
| Provider Level | Typical Role | Notes |
|---|---|---|
| EMT | Assists | Bag-mask ventilation with adjuncts, suction and positioning. No intubation or surgical airway. |
| AEMT | Performs (protocol/credentialing required) | Supraglottic airway where state protocol allows. No intubation. |
| Paramedic | Performs (protocol/credentialing required) | Intubation and surgical airway. Scope varies by state and agency; credentialing required. |
| RN (ED/ICU) | Assists | Drug preparation and read-back, suction, monitoring and tube care. Operator set by unit policy. |
| Critical Care Transport (CFRN / CTRN / FP-C / CCP-C) | Performs (protocol/credentialing required) | Intubation and surgical airway per program credentialing. |
| Physician / APP | Performs | Operator for failed-airway decisions and surgical airway in most systems. |
Team Roles During the Procedure
- Operator: owns the plan and announces each attempt and each change of plan.
- Airway and oxygen manager: keeps the mask seal, PEEP and oxygen flow, and reports SpO₂ trends.
- Medication clinician: prepares and reads back drugs and doses, with a vasopressor drawn up.
- Monitor and recorder: times each attempt and records the device, EtCO₂ and SpO₂ nadir.
Pre-Procedure Assessment
Three screens work at the bedside in the emergency setting. Each one predicts a different step, so write down which one is positive. A negative screen is not a clear airway. None of them rules out difficulty, and you still need a Plan B and a Plan C.
| Tool | Predicts | Components |
|---|---|---|
| LEMON | Difficult laryngoscopy | Look, Evaluate (3-3-2), Mallampati, Obstruction, Neck mobility |
| MOANS | Difficult mask ventilation | Mask seal, Obstruction or obesity, No teeth, Age, Stiff lungs (reduced compliance) |
| HEAVEN | Difficult intubation with physiology | Hypoxemia, Extremes of size, Anatomy, Vomit/blood/fluid, Exsanguination, Neck mobility |
One emergency department study tested a LEMON-based score in a resuscitation room. Large incisors, a reduced inter-incisor distance and a reduced thyroid-to-floor-of-mouth distance were linked to a poorer laryngoscopic view. A 2021 emergency department cohort in Thailand reported that patients with positive LEMON criteria were less likely to receive neuromuscular blocking agents. The predictors did not track with first-pass success. In another emergency department study, only the anatomic HEAVEN criterion was associated with first-pass success. These studies are single-centre. This page reports no sensitivity or specificity for any of the three tools.
Anatomic Difficulty
| Component | Assess | Concerning Findings |
|---|---|---|
| L: Look externally | Facial appearance and anatomy | Facial trauma, large tongue, beard, limited mouth opening, prominent incisors, obesity |
| E: Evaluate 3-3-2 | Mouth opening, mentum to hyoid, hyoid to thyroid notch | Mouth opening under 3 fingerbreadths (FB); mentum to hyoid under 3 FB; hyoid to thyroid notch under 2 FB |
| M: Mallampati | Oropharyngeal view when possible | Class III (soft palate and base of uvula visible) or Class IV (hard palate only) |
| O: Obstruction | Airway patency | Tumor, hematoma, abscess, foreign body, angioedema, epiglottitis |
| N: Neck mobility | Cervical spine movement | C-collar, fusion, arthritis, pain or guarding |

Physiologic Risk
The thresholds below are examples. Use protocol values.
- Hypotension: SBP < 90 mmHg or shock index > 0.9. Correct before induction.
- Hypoxemia: An SpO₂ < 93% before laryngoscopy cuts the safe apnea time short.
- Acidosis: pH < 7.20 leans on high minute ventilation, and apnea takes that away.
- Low reserve: pregnancy, obesity, sepsis, low hemoglobin or ongoing bleeding.
These markers describe the physiologically difficult airway (see References). Think of them as examples, not guideline cut-offs. Severe ARDS, right heart failure and profound shock tolerate induction poorly. So resuscitate first. Get a vasopressor running, consider a reduced-dose induction agent, and consider awake intubation. Delayed sequence intubation suits an agitated, uncooperative hypoxemic patient who cannot be preoxygenated. It does not reduce the hemodynamic risk of induction.
Site / Device Check
Monitors first: SpO₂, ECG, blood pressure and EtCO₂ should all be running. Know where the bag-mask with PEEP valve, the supraglottic airways and the surgical airway kit are. Then name who opens each one.
Anatomy & Landmarks
| Landmark | Used For | Find It | Avoid or Change Plan If |
|---|---|---|---|
| Cricothyroid membrane | Plan C (front-of-neck access) | Between the thyroid and cricoid cartilages, below the laryngeal prominence | Under about 8 years, or laryngotracheal disruption |
| Thyroid isthmus | Structure to avoid | Crosses the midline over the membrane | Bleeding can obscure the field; follow the cricothyrotomy steps |
| Hyoid and thyroid notch | Bedside 3-3-2 measure (LEMON) | Measured with the head extended: mentum to hyoid, then hyoid to thyroid notch | Limited neck extension or distorted larynx: plan the surgical airway early |
Cricothyroid Membrane (CICO Plan)
- Find the laryngeal prominence: move your fingers down the midline to the cricoid ring.
- Palpate the membrane: it sits between the thyroid and cricoid cartilages.
- Mark the midline: if the membrane is not palpable, plan a vertical midline incision.
- Protect the neck: after trauma, keep manual in-line stabilization while you access the membrane, and do not extend the neck.
Equipment & Preparation
Equipment
| Item | Size / Spec | Notes |
|---|---|---|
| Video laryngoscope | Device per protocol | First device when available; keep a standard blade as backup |
| Direct laryngoscope | Macintosh and Miller blades | Blade size per patient and protocol |
| Bougie | Coudé (angled) tip | Use when only part of the glottis is visible |
| Supraglottic airway | Weight band per protocol | Size and cuff checked before induction |
| Bag-mask with PEEP valve | Adult and pediatric masks | Two-hand seal; oral and nasal airways ready |
| Waveform capnography | Mainstream or sidestream | Required on every tube and device |
| Surgical airway kit | #10 scalpel, bougie, 6.0 mm cuffed tube (adult) | Open at the call of CICO; see Cricothyrotomy |
| Needle cricothyrotomy kit | Catheter and jet device per protocol | Temporizing only; follow device instructions |
Patient Positioning & Preparation
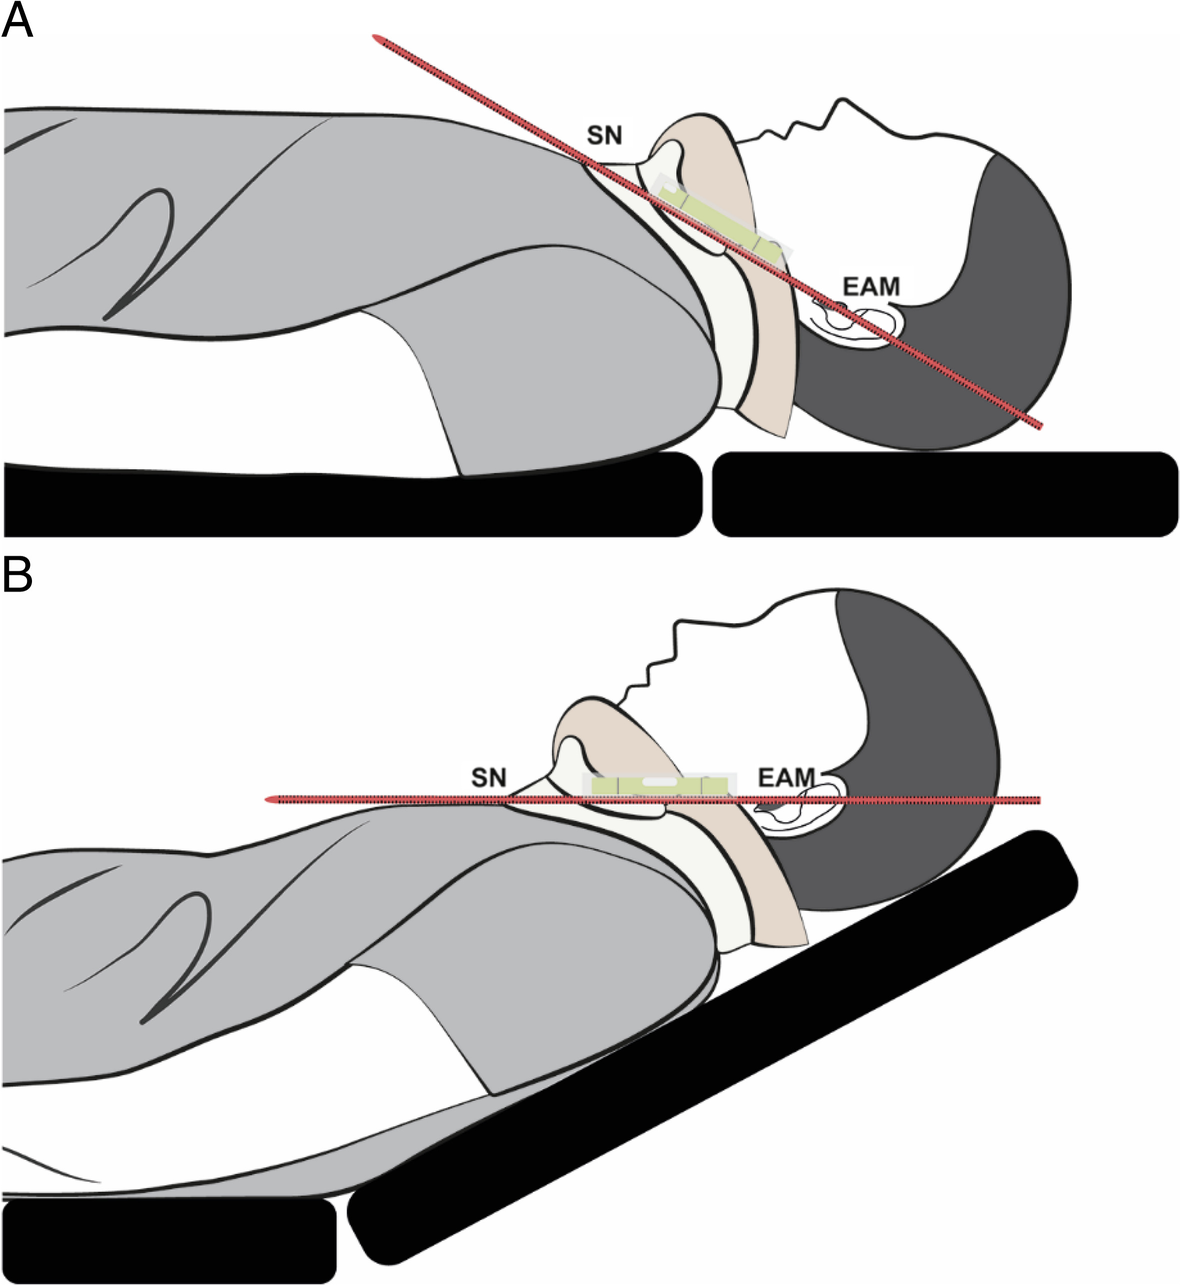
Preoxygenate with a tight mask seal and high-flow nasal oxygen or noninvasive ventilation until the protocol target is reached. Ramp the patient so the ear is level with the sternal notch.
Pre-Procedure Checklist
- Screen with LEMON, MOANS and HEAVEN; record each positive item
- Name Plan A, Plan B and Plan C, with the operator for each
- Agree the attempt limit (3), the time per attempt (30 s) and the SpO₂ abort value
- Suction on, with a rigid tip, and a clear view of the working area
- Monitors running: SpO₂, ECG, blood pressure and waveform EtCO₂
- Bag-mask with PEEP valve connected, with a two-hand seal rehearsed
- Supraglottic airway sized and checked; surgical kit located
- Vasopressor drawn up and running per protocol before induction
Medications & Settings
No drug doses live on this page. Dosing, weight basis and drug-specific cautions sit on the Rapid Sequence Intubation and Endotracheal Intubation pages. They also sit on the medication pages for rocuronium, succinylcholine, ketamine and etomidate. Induction and paralytic agents are high-alert drugs. Read back the weight, dose and units.
Step-by-Step Procedure
Phase 1: Prepare
- Screen before induction: record each positive LEMON, MOANS and HEAVEN item and the physiologic triggers.
- Brief the team: name Plan A, Plan B and Plan C, the operator for each, the attempt limit, the SpO₂ abort value, and that the team will call for help at the first failed attempt.
- Correct physiology: treat hypotension and acidosis per protocol before the first drug; have a vasopressor ready.
- Preoxygenate fully: tight mask seal, high-flow nasal oxygen or noninvasive ventilation until the protocol target is reached (commonly SpO₂ 95% or higher, or about 3 minutes or 8 vital-capacity breaths, head up). Leave a nasal cannula at 15 L/min under the mask for apneic oxygenation and keep it running through laryngoscopy.
- Position and suction: ramp the patient, suction on and the video laryngoscope in hand.
Phase 2: Perform
- Attempt Plan A: start the timer, call for help at the first failed attempt, and use the best view available, with a bougie when only part of the glottis shows.
- Stop at the limit: at 30 s, at SpO₂ below 90%, or with no progress, withdraw and resume bag-mask ventilation with PEEP.
- Re-oxygenate between attempts: return to the protocol SpO₂ target before any new attempt.
- Move to Plan B: after the failed attempts, place a supraglottic airway and confirm EtCO₂ before anything else.
- Declare CICO: if neither mask nor supraglottic airway oxygenates, make a last optimized bag-mask attempt and release any cricoid pressure. Say "cannot intubate, cannot oxygenate" aloud and go to Plan C. While the front-of-neck kit is prepared, confirm full paralysis (give a paralytic if not yet given, per protocol); do not delay the incision.
- Perform front-of-neck access: use the scalpel-bougie-tube technique on the Cricothyrotomy page, or a needle technique where the team is trained and protocol allows it.
Phase 3: Confirm & Secure
- Confirm the airway: waveform EtCO₂ over 5–6 breaths, with chest rise and bilateral breath sounds.
- Secure and record: fix the depth at the teeth or the cricothyrotomy mark, and record the time, attempts, device and EtCO₂ value.
Confirmation & Monitoring
Primary Confirmation
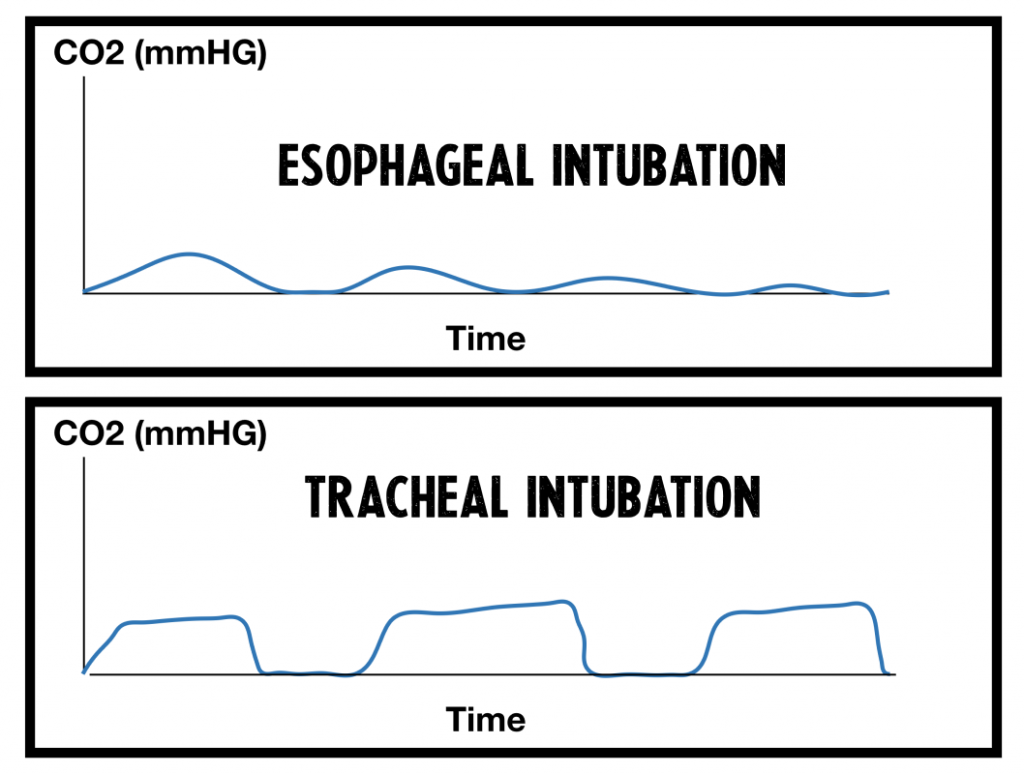
Waveform EtCO₂ is the one objective test of tracheal placement in a perfusing patient. Look for a sustained square waveform over at least 5–6 breaths. A typical value is 35–45 mmHg in a perfusing patient. Write down the time, the value and the waveform for every tube or device.
Cardiac Arrest (Low Flow)
In cardiac arrest, a low or absent waveform may mean low pulmonary blood flow. It doesn't have to mean a misplaced tube. Confirm with direct or video visualization of the tube passing the cords. Re-check EtCO₂ as perfusion changes. Don't remove a visualized tube on EtCO₂ alone. Airway attempts must not interrupt compressions for long. AHA 2025 Part 9 (Wigginton et al.) puts CPR quality first. It accepts bag-mask and advanced airway ventilation. It recommends continuous waveform capnography whenever an advanced airway is in place.
Secondary Confirmation
- Bilateral chest rise with each ventilation
- Symmetric breath sounds in both axillae, with no epigastric sounds or gurgling
- Improving SpO₂ in a hypoxemic patient
| Finding | Success | Failure / Malposition |
|---|---|---|
| EtCO₂ waveform | Sustained square wave over 5–6 breaths | Absent or decaying: treat as esophageal until proven otherwise (outside cardiac arrest; in arrest, see above) |
| Chest rise | Symmetric with each breath | Asymmetric or absent: right mainstem or unilateral intubation |
| Breath sounds | Equal bilaterally | One side louder: right mainstem; one side absent: pneumothorax or mainstem |
| Epigastric sounds | None | Gurgling over the stomach: esophageal intubation |
Ongoing Monitoring
- Continuous: waveform EtCO₂, SpO₂ and ECG, with trend review
- Blood pressure: continuous or every 1–2 minutes for the first 10–15 minutes after induction
- Each move: repeat the waveform check, depth and breath sounds
Troubleshooting
| Problem | Likely Cause | Fix |
|---|---|---|
| Poor glottic view | Anatomy, blood or secretions, head position | Re-ramp, suction, external laryngeal manipulation; switch to video or bougie |
| Tube will not pass the cords | Tip against the arytenoids; stylet too stiff | Withdraw 1–2 cm and rotate; check the stylet; use a smaller tube per protocol |
| Desaturation during attempt | Apnea time exceeded | Abort, bag-mask with PEEP, re-oxygenate before the next attempt |
| No waveform after placement | Esophageal or dislodged tube | Remove, bag-mask, then reattempt or place a supraglottic airway. In arrest, visualize the tube before removing it |
| Mask ventilation fails | Poor seal, obstruction, no teeth, beard | Two-hand seal, jaw thrust, oral or nasal airway, PEEP; go to Plan B early |
| Hypotension after the tube | Positive pressure, sedation, hypovolemia | Push-dose vasopressor and fluids per protocol; lower PEEP or rate |
| Right mainstem | Tube too deep; right bronchus more vertical | Deflate cuff, withdraw 1–2 cm while auscultating, reinflate, reassess |
| High peak pressure, shark-fin waveform | Bronchospasm, kink, auto-PEEP | Bronchodilator, check the tube, lower rate, longer expiratory time |
| Failure after 3 attempts | Anatomy or physiology unsuited to laryngoscopy | Place a supraglottic airway; if oxygenation fails, declare CICO |
Deterioration After the Tube Is Confirmed (DOPE)
- Disconnect and bag: take the patient off the ventilator and ventilate by hand with 100% oxygen.
- Check the waveform: confirm EtCO₂ and pass a suction catheter down the tube.
- Work through DOPE: Displaced tube first. Check depth, waveform and breath sounds. Then obstruction: secretions, a kink, biting or bronchospasm. Then pneumothorax: unilateral absent breath sounds and rising pressure, so decompress per protocol. Last comes equipment failure: the ventilator, the oxygen supply, the circuit. Switch to bag-mask.
Some teams tack on an S for stacked breaths, giving DOPES. This page sticks with DOPE, the same as the Intubation page.
If It Still Fails
- Oxygenate: bag-mask with a two-hand seal, jaw thrust and an oral or nasal airway.
- Place a supraglottic airway: the rescue when ventilation works but the tube does not.
- Declare CICO aloud: when oxygenation fails and neither route works.
- Surgical airway: go to the Cricothyrotomy page and perform it now.
Complications
| Complication | Recognition | Prevention | Management |
|---|---|---|---|
| Immediate: hypoxemia | SpO₂ falling during an attempt | Preoxygenate; apneic oxygenation; limit each attempt | Abort; bag-mask with PEEP; re-oxygenate |
| Immediate: esophageal intubation | No sustained waveform; gurgling | Waveform check every time | Remove the tube; ventilate; reattempt or use a supraglottic airway |
| Immediate: airway or dental trauma | Loose tooth, bleeding, cut lip | Do not lever on teeth; remove dentures | Remove fragments; suction; reassess the airway |
| Immediate: false passage at front-of-neck access | Bougie meets resistance early or no tracheal ring clicks; no air entry or EtCO₂ | Confirm the membrane; vertical incision if impalpable | Recheck position and EtCO₂; choose the next route per the Cricothyrotomy page |
| Delayed: aspiration | Hypoxemia, new infiltrate | Suction; cuff at 20–30 cm H₂O | Suction, ventilate, treat per protocol |
| Delayed: hypotension | Falling blood pressure after induction or tube | Optimize volume and vasopressor before induction | Push-dose vasopressor and fluids; lower PEEP or rate |
| Rare: pneumothorax | Unilateral absent breath sounds; rising pressure | Lung-protective ventilation | Needle decompression or chest tube (see Needle Decompression) |
Unrecognized Esophageal Intubation
- Recognize: no sustained EtCO₂ waveform, gurgling or falling SpO₂ after placement.
- Act: remove the tube and ventilate with bag-mask and oxygen before anything else.
- Reattempt: only after SpO₂ recovers, or place a supraglottic airway.
Special Populations
Pediatrics
Children desaturate faster. Vagal bradycardia can follow laryngoscopy. For tube size and depth, length-based tape or the pediatric protocol gives you the number. Confirm placement with waveform EtCO₂, exactly as in adults. Surgical cricothyrotomy generally stays off the table below about 8 years. The cut-off is contested, so go by local protocol. Under that age, the protocol names the needle or tracheotomy technique to use.
- Pediatric sizing: equipment sizing and Broselow
- Pediatric dosing: weight-based dosing
- Pediatric airway: pediatric airway
- Many pediatric protocols use cuffed tubes. Follow the protocol for cuff use and size.
- LEMON is less validated in children. Apply it with pediatric judgment.
- In children, a supraglottic airway is often the first rescue device.
- Infants and young children can develop bradycardia during laryngoscopy. Atropine or another response is per protocol.
Older Adults
- Reduced oxygen reserve: preoxygenate fully and expect fast desaturation
- Fragile dentition and mucosa: insert and laryngoscope gently
Obesity
- Ramp and use high-flow oxygen; the safe apnea time is shorter
- Video laryngoscopy is often the first device
Pregnancy
- Oxygen reserve is lower; preoxygenate thoroughly and expect rapid desaturation
- Left uterine displacement after about 20 weeks of gestation, to relieve aortocaval compression
- Aspiration risk is high: use a rapid-sequence approach with full preoxygenation
- Expect a smaller tube than for a nonpregnant adult of the same size
- Airway edema and aspiration risk both favor early video laryngoscopy. They also favor a smaller tube, per the obstetric airway protocol
Physiologically Difficult Patients
- Severe ARDS, right heart failure and profound shock tolerate induction poorly
- Resuscitate first: vasopressor running and a reduced-dose induction agent; consider awake intubation
- Use delayed sequence intubation only for an agitated hypoxemic patient who cannot be preoxygenated
Trauma and Cervical Spine
- Maintain manual in-line stabilization; remove an anterior collar only when the view requires it
- Expect blood and vomit; suction early and keep the bag-mask ready
Post-Procedure Care & Transport
Immediate Aftercare
- Recheck waveform EtCO₂, depth at the teeth or cricothyrotomy mark, and bilateral breath sounds
- Sedation and analgesia: paralytics stop breathing, not awareness. Start both once the tube is confirmed.
Ongoing Maintenance
- Cuff pressure 20–30 cm H₂O, checked after each move
- Recheck depth after every move and after any change in neck position
Transport Considerations
- Secure the tube and reassess after every move, including the stretcher and loading
- Altitude changes cuff pressure; check it during flights
- Rely on EtCO₂ and monitors in noise and vibration; a dislodged tube is a silent emergency
Document & Hand Off
- Time of each attempt, device, and final placement
- Tube or device size, depth, and method of confirmation
- Plan used (A, B or C) and any CICO declaration
- Medications and dose weight used
- Complications and response to each
Clinical Pearls & Pitfalls
Pearls
- Plan before the first attempt: Once SpO₂ is falling, it is too late to make the plan.
- Oxygen is the timer: Desaturation sets the limit. The attempt count does not.
- A negative screen is not a clear airway: keep Plan B and Plan C ready.
- Chest rise is not placement: Confirm with waveform EtCO₂, or with direct visualization in arrest.
Common Pitfalls
- Repeating the same attempt → change the device or technique.
- Waiting for lower SpO₂ before declaring failure → declare at the limit.
- Trusting breath sounds or fogging → confirm with EtCO₂.
- Planning the surgical airway only after the SGA fails → name Plan C in the brief.
Education & Skill Maintenance
Skill Maintenance
- Rehearse the failed-airway sequence in simulation with a timer and a called plan change
- Practice the CICO declaration and the front-of-neck access steps on a task trainer
- Run the pre-procedure checklist before every simulated and real airway
- Debrief every attempt: time, SpO₂ nadir, device and the reason for each plan change
References
- Apfelbaum JL, Hagberg CA, Connis RT, et al. 2022 American Society of Anesthesiologists practice guidelines for management of the difficult airway. Anesthesiology. 2022;136(1):31-81. https://doi.org/10.1097/ALN.0000000000004002
- Frerk C, Mitchell VS, McNarry AF, et al. Difficult Airway Society 2015 guidelines for management of unanticipated difficult intubation in adults. Br J Anaesth. 2015;115(6):827-848. https://doi.org/10.1093/bja/aev371
- Wigginton JG, Agarwal S, Bartos JA, et al. Part 9: Adult advanced life support: 2025 American Heart Association guidelines for cardiopulmonary resuscitation and emergency cardiovascular care. Circulation. 2025;152(16 suppl 2). https://doi.org/10.1161/CIR.0000000000001376
- Reed MJ, Dunn MJG, McKeown DW. Can an airway assessment score predict difficulty at intubation in the emergency department? Emerg Med J. 2005;22(2):99-102. https://doi.org/10.1136/emj.2003.008771
- Saoraya J, Vongkulbhisal K, Kijpaisalratana N, et al. Difficult airway predictors were associated with decreased use of neuromuscular blocking agents in emergency airway management: a retrospective cohort study in Thailand. BMC Emerg Med. 2021;21. https://doi.org/10.1186/s12873-021-00434-2
- Tan NE, Yoong KPY, Yahya HMF. Use of HEAVEN criteria for predicting difficult intubation in the emergency department. Clin Exp Emerg Med. 2022;9(1):29-35. https://doi.org/10.15441/ceem.21.059
- Prekker ME, Driver BE, Trent SA, et al. Video versus direct laryngoscopy for tracheal intubation of critically ill adults. N Engl J Med. 2023;389(5):418-429. https://doi.org/10.1056/NEJMoa2301601
- Mosier JM, Joshi R, Hypes C, Pacheco G, Valenzuela T, Sakles JC. The physiologically difficult airway. West J Emerg Med. 2015;16(7):1109-1117. https://doi.org/10.5811/westjem.2015.8.27467
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.