

Bedside Snapshot
- Indications
- Undifferentiated shock or hypotension (RUSH)
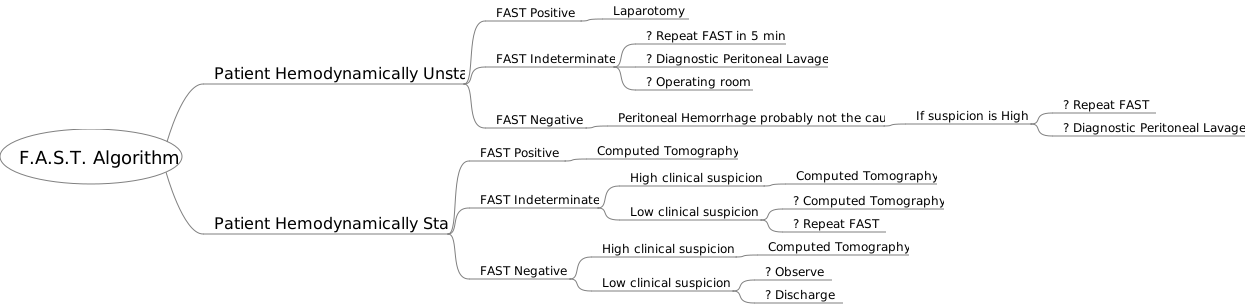
- Blunt or penetrating trauma: eFAST
- Dyspnea: lung sliding and B-lines
- Cardiac arrest: brief looks for reversible causes
- Contraindications / Abort
- Do not delay defibrillation, CPR or decompression
- CPR pause reaching 10 s: resume compressions
- Untrained operator scanning during arrest
- No usable window: treat, do not extend pauses
- Critical Steps
- Name the question before the pause
- Scan pericardium, RUQ, LUQ, pelvis, both lungs
- Lung sliding on both sides before excluding pneumothorax
- Record view, side and time
- Confirm & Monitor
- Repeat after each intervention and each move
- Correlate with ECG, EtCO₂, BP and SpO₂
- A negative FAST does not exclude injury
Key Numbers
Point-of-care ultrasound (POCUS) answers one question at a time, such as free fluid, lung sliding or cardiac filling. It is time-critical only when a fast answer changes the next intervention.
| Parameter | Value |
|---|---|
| Pause for an ultrasound look or pulse check during CPR | 10 seconds or less per pause; if uncertain, treat as no pulse and resume CPR. This is a common local-protocol limit, not an attributed guideline figure. |
| Lung sliding for pneumothorax (meta-analysis) | Ultrasound: 90.9% sensitive, 98.2% specific (pooled 1,048 patients). Supine chest X-ray: 50.2% sensitive. |
| eFAST windows | Pericardium, right upper quadrant, left upper quadrant, pelvis, and both lung fields |
| Cardiac activity during arrest | PEA or asystole cohort (Gaspari 2016, non-randomized): cardiac activity associated with survival to admission (OR 3.6) and to discharge (OR 5.7). Overall survival to discharge 1.6%; no activity was associated with non-survival, with 0.6% (95% CI 0.3–2.3) surviving to discharge. Not a stop rule. |
| Operator level for arrest scanning | Trained operators only, with a practiced local protocol |
| Sequence in traumatic arrest | Scan after indicated life-saving interventions; absent cardiac motion may have utility for prognostication only (NAEMSP, ACS-COT, ACEP 2025 joint compendium) |
Overview & Principles
POCUS answers one question per look. The operator hunts for the one finding that changes management right now: a pneumothorax that needs decompression, or a pericardial effusion that needs drainage. It adds to the physical exam and the monitor. It does not replace either one.
How It Works
- Focused question: Each view answers one question. Free fluid, lung sliding, pericardial fluid or cardiac filling. Know which one before you look.
- Sound and echo: Ultrasound bounces off tissue interfaces. Lung sliding shows up as movement at the pleural line. Air blocks the view of anything deeper.
- Repeatability: A negative look is a snapshot, not a verdict. Repeat it after any change in condition, after each intervention and after each move.
- Clinical integration: Read every finding against the vitals, ECG, capnography and exam. Never on its own.
Where It Fits
The RUSH exam (Rapid Ultrasound in SHock) sorts shock into the pump (heart), the tank (volume: IVC, abdomen, pleura) and the pipes (vessels). The eFAST adds lung sliding to the trauma FAST views. In arrest, ultrasound supports CPR. It looks for reversible causes (the H's and T's) during brief pauses, and it never stretches those pauses.
AHA 2025 Part 9 covers POCUS in the ALS setting. Follow your local protocol and medical direction.
| Shock Pattern | Typical RUSH Findings |
|---|---|
| Hypovolemic | Small, hyperdynamic LV; flat, small IVC |
| Cardiogenic | Poor LV function; B-lines; plethoric IVC |
| Obstructive | Pericardial effusion or tamponade; RV dilation or strain (PE); absent sliding (pneumothorax) |
| Distributive | Hyperdynamic LV; IVC may be small; no effusion or RV strain |
Indications & Contraindications
Indications
- Undifferentiated shock or hypotension: Sort it into pump, tank and pipes with the RUSH framework.
- Blunt or penetrating trauma: Run the eFAST for pericardial fluid, free intraperitoneal fluid and pneumothorax.
- Dyspnea or hypoxemia: Use lung sliding, B-lines and consolidation to separate the causes.
- Cardiac arrest: Brief looks for pericardial effusion, pneumothorax, hypovolemia and cardiac activity, once the indicated life-saving interventions are done in traumatic arrest.
Absolute Contraindications
Nothing rules it out when the exam is indicated. The probe is not a reason to delay a time-critical treatment.
Relative Contraindications & Cautions
- Wound or dressing at the probe site: Switch to another window, or lay a sterile barrier down first. Pressing on an open wound is off the table.
- Poor windows: Obesity, subcutaneous emphysema, bandages, chest tubes and packaging limit the views you get.
- Operator without training: Untrained hands on a deteriorating patient. A negative or unclear read does more harm than no read at all.
Abort / Stop Criteria
- Pulse check or CPR pause that has reached 10 seconds: resume compressions and finish the look later.
- Any defibrillation, decompression or drainage that is due: perform it first.
Scope & Team Roles
| Provider Level | Typical Role | Notes |
|---|---|---|
| EMT | Not in scope | Supports positioning and ECG pads |
| AEMT | Not in scope | Supports positioning and ECG pads |
| Paramedic | Performs (protocol/credentialing required) | Not in national model; state and agency credentialing |
| RN (ED/ICU) | Assists | Often operator in ED/ICU units with credentialing; follow unit policy |
| Critical Care Transport (CFRN / CTRN / FP-C / CCP-C) | Performs (protocol/credentialing required) | Scan in flight only under the transport protocol; movement limits image quality |
| Physician / APP | Performs | Operator for most arrest and shock scanning |
Team Roles During the Procedure
- Operator: chooses the view and reads the image; announces findings.
- Compressor: maintains compressions and manages the pause clock.
- Airway and oxygen: keeps ventilation and monitoring going.
- Recorder: time-stamps each view and each finding.
Pre-Procedure Assessment
Anatomic Difficulty
| Component | Assess | Concerning Findings |
|---|---|---|
| Chest wall | Rib spacing, dressings, subcutaneous air | Crepitus, open wound or dressing over the window |
| Abdomen | Distension, body habitus, prior surgery | Heavy distension or obesity limiting the RUQ or LUQ window |
| Heart window | Chest wall habitus, position | No subxiphoid or parasternal window; use another view |
Physiologic Risk
Scan at the decision points. In hypotension, a scan earns its pause when the answer changes the next step. Is it tamponade, tension, hemorrhagic physiology or pump failure? Let the clinical picture guide which one you chase.
Site / Device Check
- Machine: curvilinear (abdomen, lung) and phased-array (heart) probes; set depth and gain before the pause.
- Preset: cardiac, abdominal or lung presets; confirm each view by orientation marker.
- Patient: exposed chest and abdomen with a gel barrier; keep compressions and ECG pads clear.
Anatomy & Landmarks
| Site | Best For | Landmark | Depth / Angle | Avoid If |
|---|---|---|---|---|
| Subxiphoid | Pericardial fluid, cardiac filling | Below the xiphoid, probe pointed to the left shoulder | Probe nearly flat; aimed to the left shoulder | Abdominal distension or poor subxiphoid window |
| Parasternal long/short axis | Pericardium, LV and RV size | Left parasternal 3rd to 5th intercostal space | Probe marker to right shoulder | Chest wall injury or dressing |
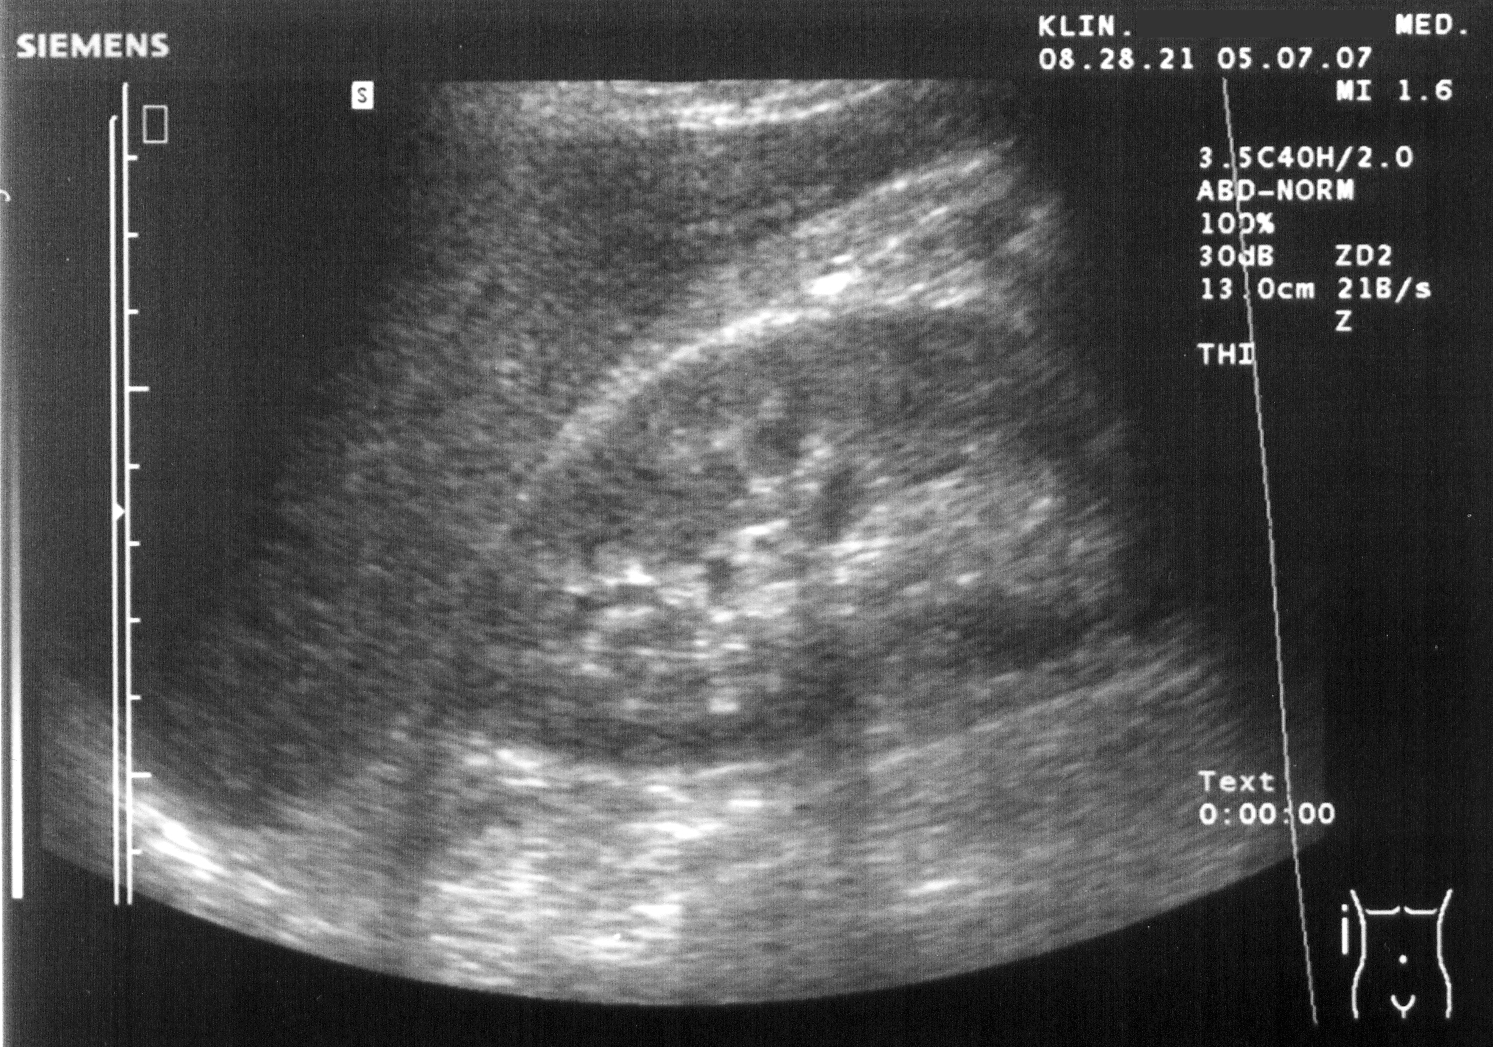
| RUQ (Morison's pouch) | Free fluid, hepatorenal recess | Mid to posterior axillary line, under the right costal margin | Oblique, looking to the diaphragm | Overlying wound |
| LUQ (splenorenal) | Free fluid, spleen | Left posterior axillary line, under the costal margin | Oblique, looking to the diaphragm | Overlying wound |
| Pelvis (suprapubic) | Free fluid in the pelvis, bladder | Transverse above the pubic symphysis | Sagittal then transverse | Empty or decompressed bladder (for example after Foley placement) |
| Lung | Pneumothorax (sliding), B-lines, consolidation | Anterior 2nd to 3rd ICS at midclavicular line; lateral chest | Linear for sliding; curvilinear for depth | Chest wall injury |
Subxiphoid View
- Position: supine, head slightly up; probe at the xiphoid, marker to the patient's right.
- Angle: keep the probe nearly flat against the abdomen, aimed toward the left shoulder; rock to find the four-chamber view.
- Look: fluid around the heart, RA and RV collapse, and gross cardiac motion.
- Confirm: sweep to find the effusion edge before calling it free fluid.
Pediatric
Same windows, with a smaller, higher-frequency probe where you have one. This page gives no pediatric thresholds.
RUQ and LUQ (FAST Abdomen)
- RUQ: mid-axillary line, rib space above the liver and the kidney; look for fluid between liver and kidney.
- LUQ: posterior axillary line; look for fluid around spleen and kidney and the diaphragm.
- Pelvis: suprapubic; look for fluid posterior to the bladder. A full bladder is the acoustic window; scan before placing a Foley when possible.
- Sweep: keep the probe on the same plane and look for the most dependent fluid.
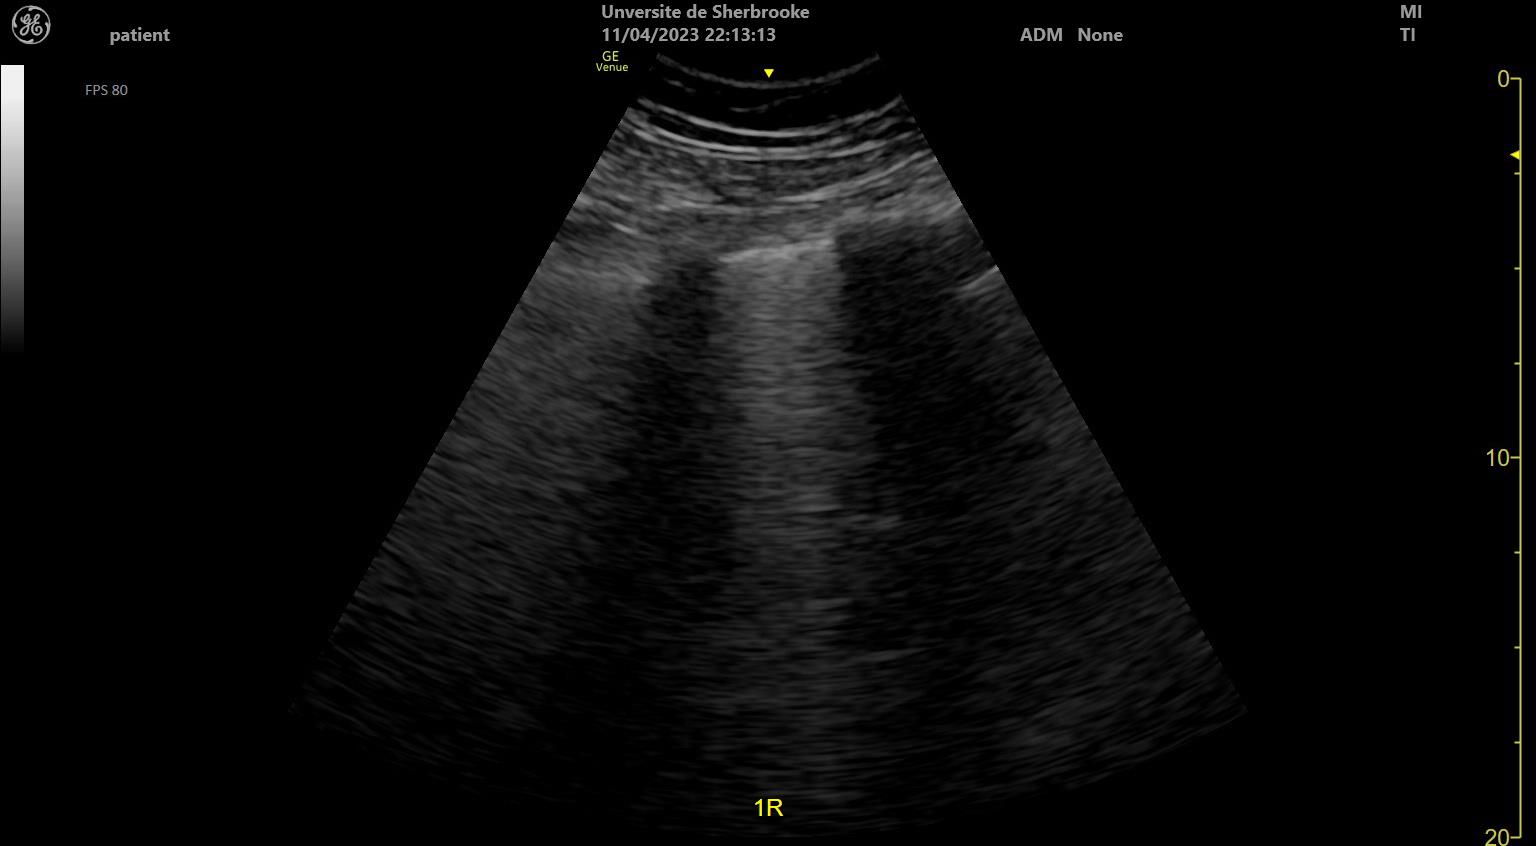
Lung Views
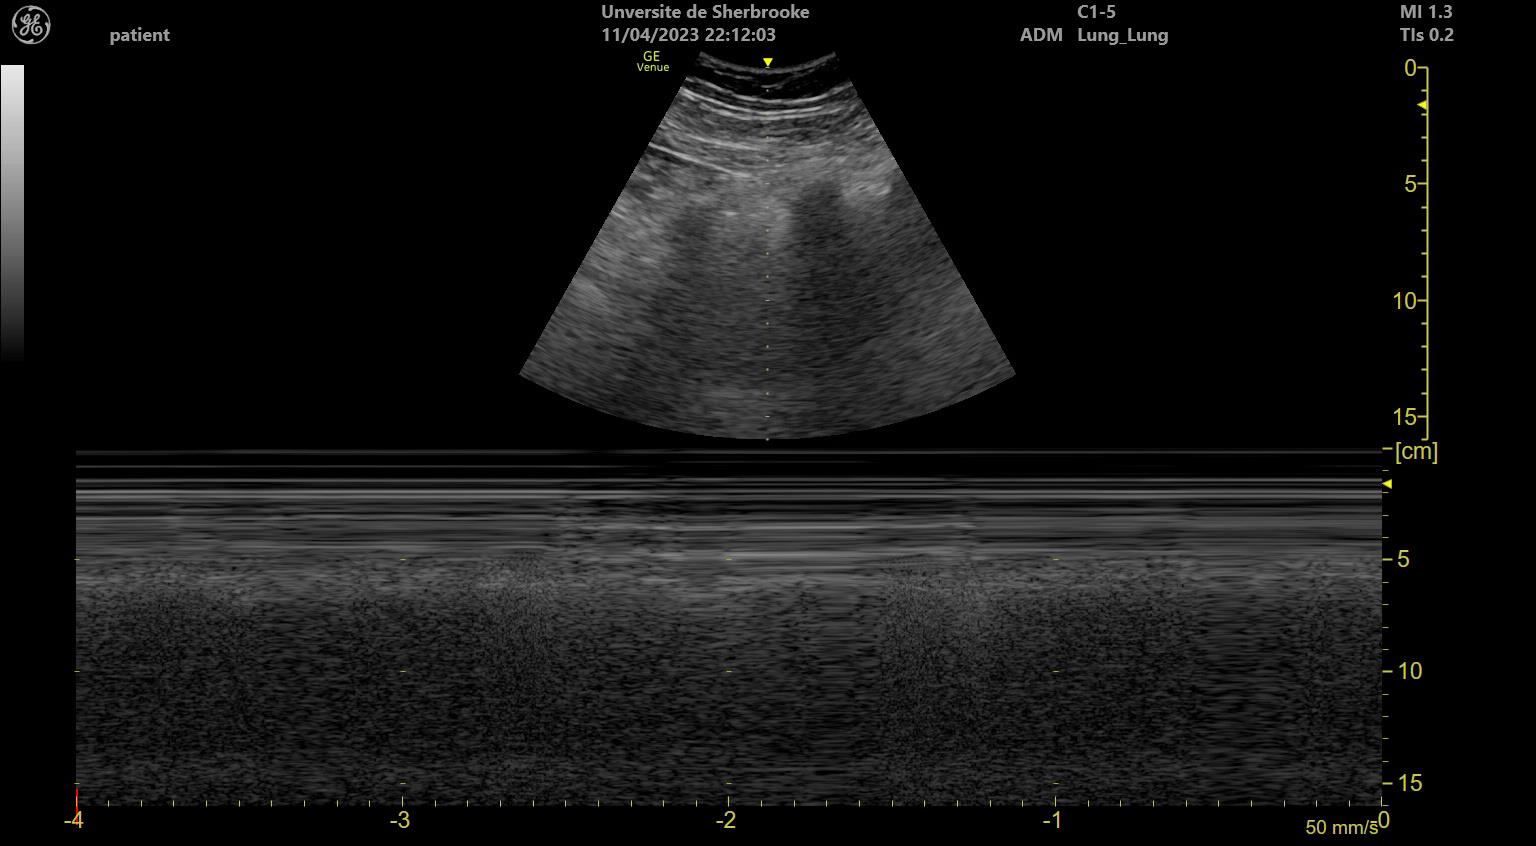
- Probe: linear probe on the anterior 2nd to 3rd intercostal space at the midclavicular line; compare sides.
- Look: pleural line sliding with breathing (normal) or absent sliding (concern for pneumothorax; absence is non-specific).
- Scan: move to the lateral chest and the bases to find the edge of sliding (lung point).
- Interpret: B-lines, consolidation and pleural effusion with the clinical picture.
Equipment & Preparation
Equipment
| Item | Size / Spec | Notes |
|---|---|---|
| Phased-array probe | Low frequency, small footprint | Cardiac views between ribs |
| Curvilinear probe | Low frequency, deep field | Abdomen and pelvis |
| Linear probe | High frequency, shallow field | Lung sliding and pleural line |
| Ultrasound gel | Water-based | Sterile barrier if skin is broken |
| Monitor and ECG | Continuous | Rhythm during the look |
| Pause timer | Visible to the team | Counts each interruption |
| Backup | Decompression and chest tube kit | For treatment if the scan shows a pneumothorax |
Patient Positioning & Preparation
No log-roll is needed for the FAST and cardiac views, RUQ and LUQ included. Keep the patient supine. If a window is poor and there is no spinal concern, a slight tilt can help. Keep compressions on a firm surface.
Pre-Procedure Checklist
- Question for the scan stated out loud
- Probe, preset and depth set before the pause
- Pause timer running and visible to the compressor
- Treatment kit open if a pneumothorax or effusion is found
- Chest and abdomen exposed; gel applied
- Monitor shows rhythm and EtCO₂
Step-by-Step Procedure
Phase 1: Prepare
- Name the question: free fluid, pneumothorax, pericardial fluid, cardiac filling or arrest cause.
- Set the preset: cardiac, abdominal or lung preset with the matching probe.
- Protect the team: confirm the compressor, the pause clock and the recorder.
Phase 2: Perform
- Start with the views the question needs: for shock, RUSH order; for trauma, eFAST order.
- Scan each window briefly: one or two sweeps, saved as a still image or clip.
- Look for the answer: fluid, sliding, cardiac motion or consolidation.
- Stop at 10 seconds in arrest: resume compressions and continue the look after the next cycle.
- Act on the finding: a pneumothorax needs decompression or chest tube; a tamponade needs pericardiocentesis or surgery per local protocol.
Phase 3: Confirm & Secure
- Record the findings: time, view, side, and the one-line impression.
- Repeat the scan: after each intervention or change in condition.
- Hand off: state what was scanned, what was not, and the next scan due.
Alternative Technique: Lung Sliding Only
Suspect a pneumothorax and need only the lung? Scan the anterior and lateral chest on both sides with a linear probe. Compare the sides before you call sliding absent.
Confirmation & Monitoring
Primary Confirmation
A clear image, labeled with its view, and the finding written down. For lung sliding, look again on both sides with the probe on the same site.
Secondary Confirmation
- Clinical match: the finding should fit the vitals, breath sounds, EtCO₂ and trend.
- Second view: the same finding in a second window (for example RUQ and LUQ).
- Definitive test when available: CT, echo or chest X-ray per protocol.
| Finding | Success | Failure / Malposition |
|---|---|---|
| Lung sliding | Present with breathing on both sides | Absent is non-specific: apnea or shallow breathing, mainstem intubation, pleural adhesions or pleurodesis, bullae and ARDS. A lung point confirms pneumothorax; its absence does not exclude a large one. Treat tension physiology clinically. |
| Free fluid | Anechoic stripe in RUQ, LUQ or pelvis | Echogenic (clotted) fluid still appears as free fluid; confirm in a second window |
| Pericardial fluid | Echo-free space around the heart | Pleural fluid can look similar. On parasternal long axis, pericardial fluid lies anterior to the descending aorta and pleural fluid posterior to it. An anterior echo-free stripe may be epicardial fat. Confirm in a second window. |
| Cardiac motion | Visible activity in arrest | No activity is not a stop rule by itself. In traumatic arrest, absent cardiac motion may have utility for prognostication only (NAEMSP, ACS-COT, ACEP 2025 joint compendium) |
Ongoing Monitoring
- Repeat the look after each intervention or change in vitals.
- Continuous ECG, capnography and BP (per monitor).
- Re-scan after transport moves and before handoff.
Troubleshooting
| Problem | Likely Cause | Fix |
|---|---|---|
| No subxiphoid heart view | Gas or bowel distension, obesity | Use parasternal or apical window; angle and depth change |
| Pericardial view shows only fluid in front | Probe too high or too far anterior | Move down and angle up and left |
| Lung sliding absent on one side | Pneumothorax, mainstem intubation, pleural adhesions, bullae, apnea or shallow breathing, or poor contact | Check for lung point; reposition tube; confirm contact; treat tension physiology clinically |
| Cannot see liver or kidney in RUQ | Probe too anterior or caudal, rib shadowing, or bowel gas | Move cephalad and posterior along the mid to posterior axillary line; fan through the intercostal space; ask for a held inspiration if the patient can cooperate |
| Image noisy or washed out | Wrong preset or gain | Reset preset and gain before the pause |
| Pause longer than 10 seconds | Too many views in one pause | Stop, resume compressions and plan the next look |
| Finding unclear | Limited window or artifact | Repeat on the other side; use a second window; treat if unstable |
If It Still Fails
- Unstable with unclear findings: Treat the most likely cause. Tension physiology gets decompression. Hemorrhage gets volume and blood products. Do it per protocol.
- Arrest with no usable view: Keep up CPR and defibrillation. Do not extend a pause to chase a better image.
Complications
| Complication | Recognition | Prevention | Management |
|---|---|---|---|
| Immediate: prolonged CPR pause | Pause clock over 10 seconds | Plan the window before the pause | Resume compressions at once |
| Immediate: treatment delayed by scanning | Defibrillation or decompression waiting | Treat first; scan in parallel only | Start the treatment on the clinical picture |
| Delayed: missed injury | Hollow-organ or retroperitoneal injury after a negative FAST | Repeat exam; correlate with clinical course | Serial exams; CT per protocol |
| Delayed: misread effusion | Pleural fluid taken for pericardial fluid | Second view; confirm with echo | Repeat view; definitive echo |
| Rare: skin injury from probe pressure | Skin redness or wound | Light pressure on injured skin; use gel | Clean and dress; reassess |
Life-threatening
Scanning that holds up decompression for a tension pneumothorax, or pericardiocentesis for tamponade with arrest, is the single most dangerous error here. Treat first.
Special Populations
Pediatrics
- Same views, with a smaller, higher-frequency probe where you have one.
- This page gives no pediatric thresholds for volume or effusion size. Follow pediatric protocols.
- A 2026 systematic review and GRADE meta-analysis of pediatric blunt abdominal trauma rated the evidence very low. It made no recommendation for FAST to identify clinically important intra-abdominal injury.
- Link: Pediatric cardiac arrest, Pediatric shock, Equipment sizing.
Older Adults
- A thinner chest wall, and more gas or bowel distension, may limit the windows you get.
- Pleural and cardiac findings still need to be matched to the clinical picture.
Pregnancy
- Relieve aortocaval compression with left lateral tilt or manual uterine displacement. Supine hypotension can look like shock.
- The gravid uterus can crowd out the RUQ and LUQ views.
- A negative FAST does not rule out uterine or fetal injury. Obtain obstetric assessment and fetal monitoring per protocol.
- In maternal arrest, do not let an ultrasound look delay CPR or perimortem delivery guidance.
Obesity
- You need a deeper field here. Use a curvilinear probe at a lower frequency.
- Negative windows are less reliable. Repeat the look or use another test.
Trauma and Spinal Precautions
- Scan supine, with spinal precautions in place. The RUQ and LUQ windows are done supine at the mid to posterior axillary line and need no log-roll.
- Only a true posterior chest or back window needs a log-roll. Those windows are not part of eFAST, so do not add movement for them.
Post-Procedure Care & Transport
Immediate Aftercare
- Document each view and the findings before moving the patient.
- Re-scan after each intervention and after any change in rhythm.
Ongoing Maintenance
- Repeat the look at intervals set by the team, and after each treatment.
- Keep the probe clean and gel changed between patients.
Transport Considerations
- Vibration and noise limit image quality; rely on the monitor and clinical trend.
- Re-scan after each move, not only at the start.
- Lung sliding and B-line reads are less reliable in motion; confirm on the ground when possible.
Document & Hand Off
- Time and reason for each scan
- Views obtained and views not obtained
- Findings per side or quadrant
- Probe, preset and operator
- Pause times during arrest
- Response to treatment and the next scan due
Clinical Pearls & Pitfalls
Pearls
- One question, one look: Pick the single decision first, then let one view answer it.
- Lung sliding rules out pneumothorax at that site: Absent sliding is the cue to correlate clinically and look again.
- Pauses are the cost: A 10-second look is 10 seconds of compressions you did not deliver.
- Negatives are provisional: A negative is a time stamp, not a finding for the rest of the call. Repeat the look as the picture changes.
Common Pitfalls
- Scanning every view in arrest. Ask one question per pause and stop there.
- A negative FAST is not a clearance. Repeat it and correlate with the picture.
- Mistaking pleural fluid for pericardial, or epicardial fat for effusion. Check how it sits against the aorta and get a second view.
- Waiting on an image before decompression. Treat first.
Education & Skill Maintenance
Skill Maintenance
- Practice the pause clock with a manikin during CPR training.
- Review saved images at debriefs and compare with the final diagnosis.
- Confirm the local credentialing and quality review requirements.
References
- Scalea TM, Rodriguez A, Chiu WC, et al. Focused Assessment with Sonography for Trauma (FAST): results from an international consensus conference. J Trauma. 1999;46(3):466-472. https://doi.org/10.1097/00005373-199903000-00022
- Lichtenstein DA, Mezière GA. Relevance of lung ultrasound in the diagnosis of acute respiratory failure: the BLUE protocol. Chest. 2008;134(1):117-125. https://doi.org/10.1378/chest.07-2800
- Alrajhi K, Woo MY, Vaillancourt C. Test characteristics of ultrasonography for the detection of pneumothorax: a systematic review and meta-analysis. Chest. 2012;141(3):703-708. https://doi.org/10.1378/chest.11-0131
- Perera P, Mailhot T, Riley D, Mandavia D. The RUSH exam: Rapid Ultrasound in SHock in the evaluation of the critically ill. Emerg Med Clin North Am. 2010;28(1):29-56. https://doi.org/10.1016/j.emc.2009.09.010
- Gaspari R, Weekes A, Adhikari S, et al. Emergency department point-of-care ultrasound in out-of-hospital and in-ED cardiac arrest. Resuscitation. 2016;109:33-39. https://doi.org/10.1016/j.resuscitation.2016.09.018
- Wigginton JG, Agarwal S, Bartos JA, Coute RA, Drennan IR, Haamid A, et al. Part 9: Adult Advanced Life Support: 2025 American Heart Association Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2025;152(16 suppl 2):S538-S577. https://doi.org/10.1161/cir.0000000000001376
- National Association of EMS Physicians, American College of Surgeons Committee on Trauma, American College of Emergency Physicians. Prehospital Trauma Compendium: Prehospital Management of Adults with Traumatic Out-of-Hospital Circulatory Arrest. Joint position statement and resource document. Prehosp Emerg Care. 2025. https://doi.org/10.1080/10903127.2024.2428668
- Evaluation of Pediatric Patients with Blunt Abdominal Trauma: A Systematic Review, Meta-Analysis, and Practice Management Recommendations. J Am Coll Emerg Physicians Open. 2026. https://doi.org/10.1016/j.acepjo.2026.100493
Medical Disclaimer
- For Educational Purposes Only: This content is intended for educational reference and should not be used for clinical decision-making.
- Not a Substitute for Professional Judgment: Always consult your local protocols, institutional guidelines, and supervising physicians.
- Verify Before Acting: Users are responsible for verifying information through authoritative sources before any clinical application.